Why We Keep Doing This Anyway
I have placed more urethral catheters than I care to count across years of ward rounds and night shifts, and the uncomfortable truth is that despite every guideline claiming otherwise, we still do it for convenience more often than clinical necessity. The protocol says restrictive indication, the protocol says consider condom catheter or briefs first for incontinent patients, and I nod along while grabbing the 16Fr silicone pack off the trolley because the alternative is changing a soak-through pad at 3 AM again. That does not make it right, but it makes it real, and I would rather be honest about that than write something that sounds like a pharmaceutical brochure. The actual procedure itself is mechanically simple, which is partly why so many people get complacent about the steps that follow. You pass a lubricated inflatable tube through the urethra into the bladder, inflate the balloon with sterile water, and pull it back until it rests against the trigone. That is the entire geometry of it. Complications start when you treat simplicity as a reason to skip verification.
What People Mean When They Say Placing A Foley Catheter
The term covers two distinct acts that beginners lump together: the initial insertion, which is the part everyone worries about, and the ongoing maintenance, which is where most actual harm happens. Urologists and wound care nurses will split these into separate discussions because the risk profiles are completely different. Initial placement complications like false passage creation or sphincter trauma tend to be acute and visible. Catheter-associated urinary tract infections, urethral meatal erosion, and bladder stone formation are chronic, slow, and almost entirely preventable if someone had paid attention during the first twenty-four hours. Indications that justify the include urinary retention with volumes over 400 ml confirmed by bladder scan, accurate output monitoring in critically ill patients, perineal wound protection in terminal palliation, and perioperative use during procedures lasting longer than two hours. Contraindications are fewer than most textbooks suggest, but they matter more. Known urethral disruption from pelvic fracture, recent urological surgery in the distal urethra, and inability to advance past the external sphincter after gentle persistent attempts all signal that you should stop and call urology rather than pushing harder. I learned that last one the hard way in 2019 with a seventy-eight-year-old male post-TURP who had a subtle false passage I missed on the first attempt, and by the time I recognized it the patient was leaking hematuria around the catheter and I had to convert to a suprapubic under sedation. The cystoscopy showed a three-millimeter mucosal tear at the prostatic urethra that would have healed on its own if I had simply stopped after resistance met without force.
The Procedure As It Actually Unfolds
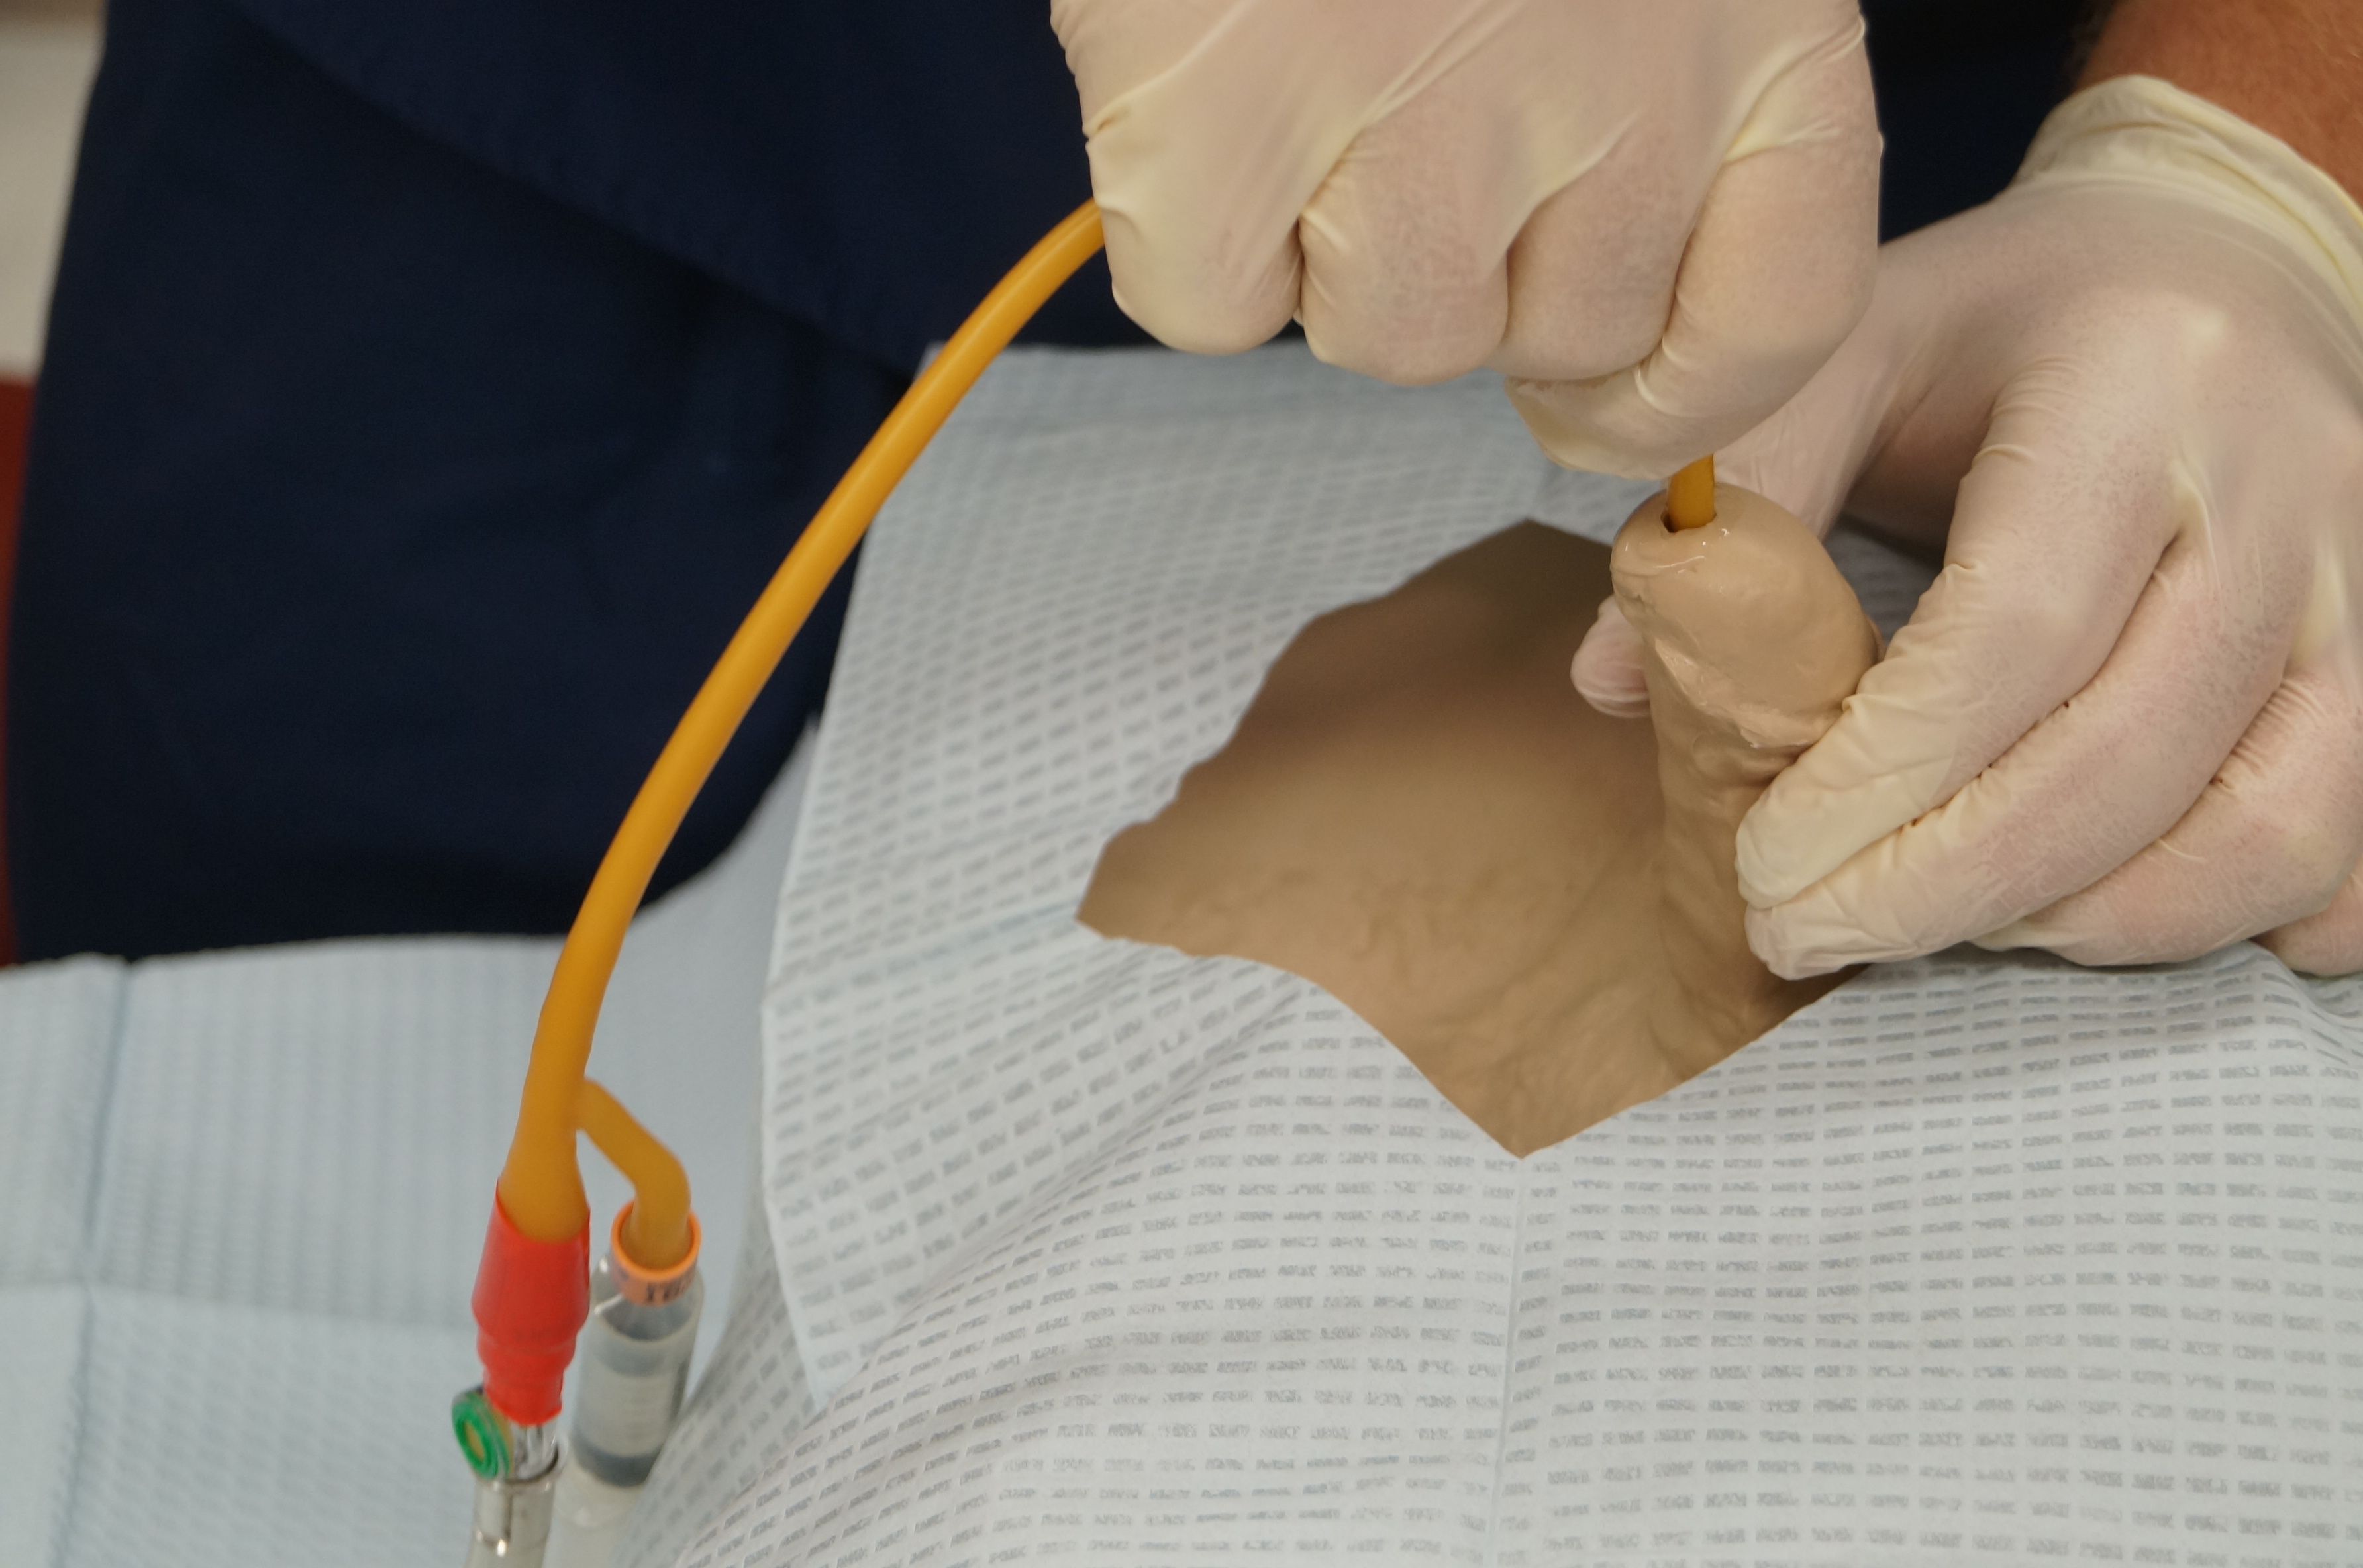
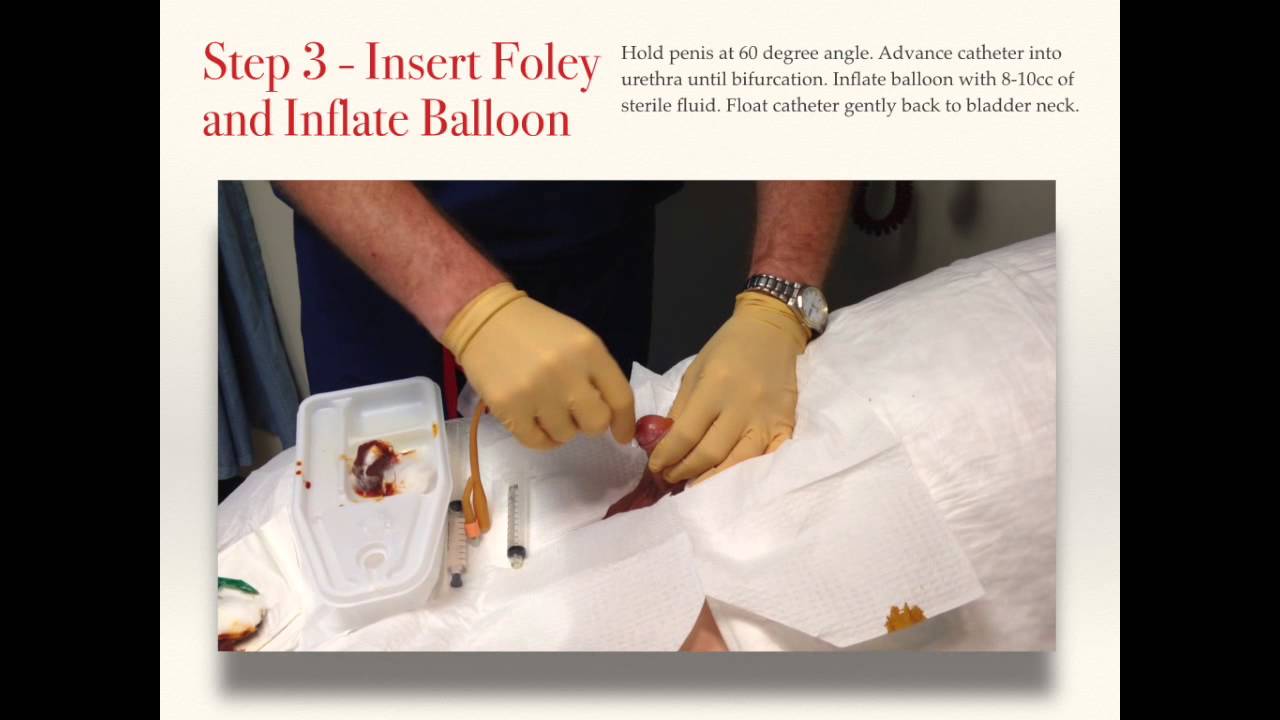
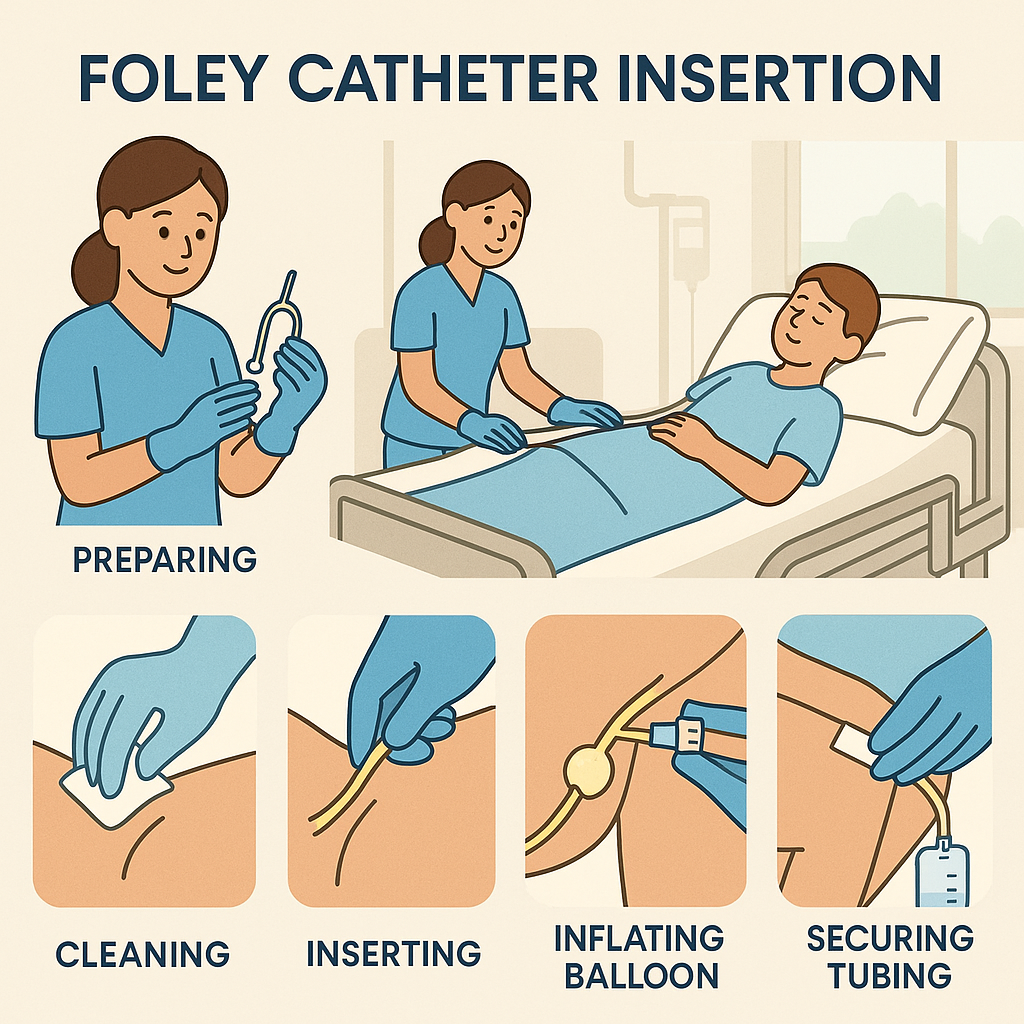
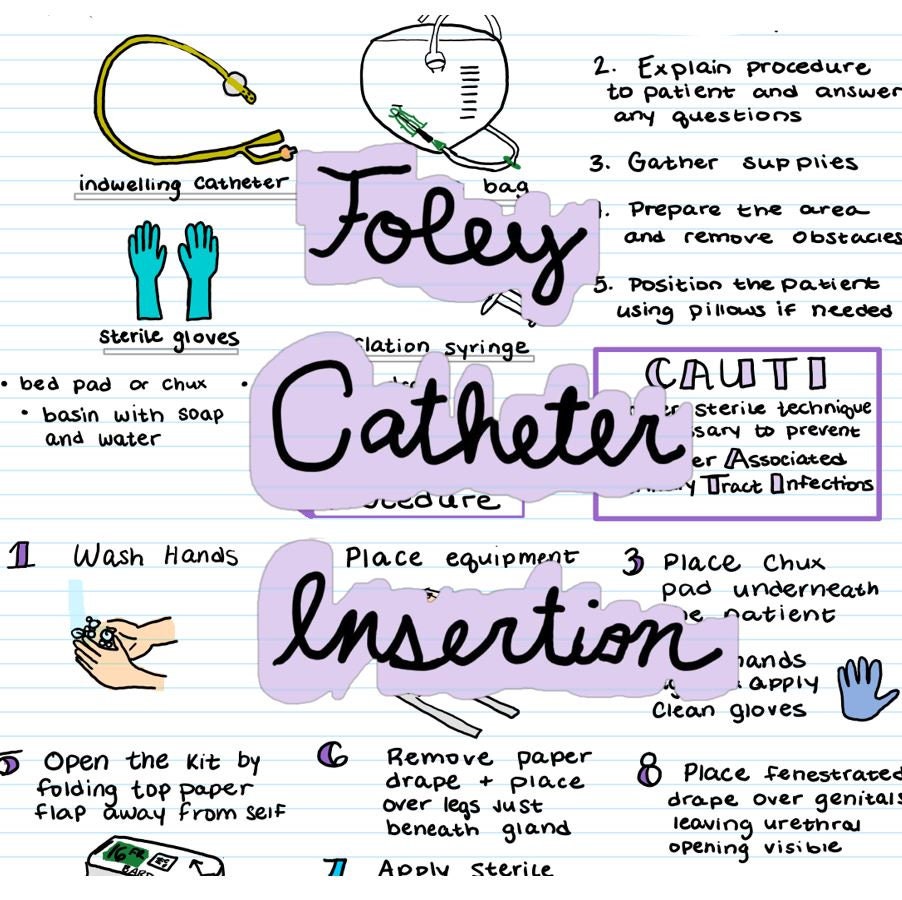
Start with a bladder scan. Not always mandatory, but it saves you from inserting an indwelling catheter into a patient who voided three hours ago and has a residual of eighty milliliters. The scan takes forty seconds and prevents a lot of downstream irritation. Gather your kit: a 14 to 16Fr silicone Foley is the workhorse size for most adults, 5 ml sterile water for balloon inflation, a syringe, waterproof drape, chlorhexidine swabs, sterile gloves, and lidocaine jelly 2% in a single-dose applicator. Some units stock pre-lubricated closed-system kits that include the syringe and swabs already in the pack, which reduces contamination risk by eliminating the sterile field setup, though they cost roughly three times as much per unit and the plastic packaging can sometimes tear during removal. Position the patient supine with hips slightly abducted. For males, retract the foreskin if present and do not forget to replace it afterward, which I cannot emphasize enough because paraphimosis develops within hours and is a genuine urological emergency. Cleanse the meatus and distal urethra with a chlorhexidine swab using a single forward stroke from the meatus outward, discard the swab, and apply lidocaine jelly. The jelly does two things: it reduces friction during insertion and provides local anesthetic effect that makes the passage through the external sphincter less uncomfortable, especially in elderly patients with urethral sensitivity. Wait ninety seconds for the anesthetic to take effect before proceeding, because rushing this step increases sphincter spasm risk significantly. Hold the penis at a sixty-degree angle to the body wall for males, which straightens the penile urethra and aligns the meatus with the introduction path. Advance the catheter tip gently through the meatus and into the urethra. You will feel resistance at the external urethral sphincter around ten to twelve centimeters in most adult males, which is normal. Apply steady gentle pressure without forcing, breathe with the patient if they are anxious, and the sphincter will relax and you will pass through. Urine return confirms vesical entry. Advance another two to three centimeters before inflating the balloon, because inflating against the trigone causes severe bladder spasm and hematuria that can persist for days.
Get the Full Details

Inject exactly 5 to 10 ml of sterile water into the inflation channel using the provided syringe. Do not use tap water, saline, or contrast medium, because incorrect solutions cause crystallization inside the balloon and make deflation impossible, which is a terrifying problem to discover when you need to remove the catheter and the balloon will not collapse. I once managed a case where a previous provider had used 20 ml of normal saline instead of sterile water, and six months later when we tried to remove the catheter the balloon had developed a saline-induced crystal shell that refused to deflate. We ended up cutting the catheter and performing cystoscopic balloon rupture under local anesthesia, which added two hours to the patient's stay and caused significant urethral trauma that took three weeks to heal. Secure the catheter to the thigh or lower abdomen using a proprietary securement device rather than tape alone, because evidence shows this reduces meatal trauma and unintentional extubation by roughly forty percent compared to standard adhesive tape. Connect to a sterile drainage bag positioned below bladder level at all times, and ensure the tubing has no kinks or dependent loops where urine can pool and become a culture medium for bacterial proliferation.
What Goes Wrong in Practice
False passage creation is the most common procedural error, occurring in approximately five to ten percent of first-time male catheterizations according to most published series. The mechanism is straightforward: the catheter tip breaches the urethral mucosa rather than passing through the lumen, usually at the bulbous urethra or prostatic apex where curvature changes. Signs include resistance without progressive advancement, blood at the meatus, and perineal pain. The fix is to withdraw the catheter completely, apply more lidocaine jelly, wait longer, and attempt again with a smaller French size, typically 12Fr. If the second attempt also fails, stop and consult urology for guidewire-assisted placement under direct vision rather than making a third blind attempt, which multiplies trauma risk exponentially. Balloon inflation in the urethra rather than the bladder is rare but devastating. If you inflate the balloon before confirming free urine return and sufficient advancement, the 5 ml balloon will expand inside the urethral lumen and cause immediate severe pain, tissue necrosis, and potentially complete urethral destruction. The prevention is mechanical: confirm urine flow, advance two additional centimeters, then inflate. If the patient experiences sudden severe pain during inflation, stop immediately, aspirate the balloon, withdraw the catheter slightly, and reassess before re-attempting. Catheter-associated urinary tract infection remains the most common healthcare-associated infection worldwide, accounting for roughly thirty to forty percent of all hospital-acquired infections according to CDC surveillance data. The single most effective prevention is not antibacterial coating or silver alloy tubing, both of which show marginal benefit at best, but rather daily assessment of continued indication and prompt removal when no longer needed. Each additional day of indwelling catheterization increases UTI risk by approximately three to ten percent, and by day seven the colonization rate approaches one hundred percent in unantibiotic-covered patients. I review catheter indications every morning during ward rounds as a non-negotiable habit, and my unit's CAUTI rate dropped from 4.2 to 1.8 per thousand catheter-days after implementing this practice, which is a meaningful difference when you are talking about patient safety at scale.
Advanced Nuances Beginners Miss
The choice between latex and silicone matters more than most protocols acknowledge. Latex is cheaper and has better initial handling characteristics, but it causes more tissue reaction and encrustation over time. Silicone is biocompatible, less encrustation-prone, and suitable for longer-term indwelling use, but it is stiffer and slightly more difficult to insert, especially in patients with urethral stricture. For expected indwelling duration under fourteen days, either material performs acceptably. Beyond that, silicone becomes clearly preferable, and I switch to 100% silicone catheters for any patient I anticipate keeping catheterized for more than two weeks. Bladder irrigation through the Foley is sometimes necessary for hematuria management, particularly post-TURP or in patients with clot retention. Use a three-way catheter with a larger lumen, typically 22Fr or 24Fr, and irrigate with continuous normal saline flow at a rate that keeps the effluent pink rather than red. Monitor output carefully and watch for signs of fluid absorption syndrome, which is rare with saline but possible with glycine or water-based irrigants. The key practical tip is to never stop the irrigation flow completely until the effluent is clear and the bleeding has definitively resolved, because intermittent closure causes clot reformation that is much harder to manage than continuous low-flow irrigation. Pediatric and pediatric-sized anatomy requires different thinking entirely. Neonates and infants use 5 to 8Fr catheters, and the entire insertion depth is measured in centimeters rather than tens of centimeters. The external sphincter is proportionally tighter, and the risk of urethral trauma from standard adult technique is unacceptably high. If you are not routinely working with pediatric patients, do not attempt this population without direct supervision from a pediatric urologist or neonatologist, because the anatomical margins for error are measured in millimeters rather than centimeters.
The Removal That Nobody Talks About
Deflating the balloon seems trivial until it is not. Aspirate the inflation channel slowly and completely, then gently apply counter-traction to the pubic area while withdrawing the catheter along the natural urethral curve. If resistance occurs, do not pull forcefully. Re-aspire the balloon, wait thirty seconds, and try again. Persistent resistance suggests balloon dysfunction, urethral stricture, or possibly an inflated balloon that was never fully deflated due to crystallization from incorrect inflation fluid. In that scenario, instill five milliliters of sterile water into the inflation channel to help dissolve any crystal adhesion, wait, and re-aspirate. If the balloon still will not deflate, urology consultation is required for cystoscopic intervention, and attempting blind forceful removal risks urethral avulsion, which is a surgical emergency with significant long-term morbidity including strictures requiring multiple reconstructive procedures. After removal, document the catheter type, size, inflation volume, indication for placement, duration of indwelling time, any complications during insertion or removal, and the patient's renal function status going forward. This creates a traceable record that helps future providers understand why the catheter was placed and whether re-insertion might face similar challenges. I have seen too many patients bounce between services with no documentation of difficult prior catheterizations, and each fresh provider attempts standard insertion without knowing that a previous urethral tear exists, leading to repeat injuries and delayed appropriate urological referral. The uncomfortable reality is that Foley catheters are neither as benign nor as universally indicated as the frequency of use might suggest. They save time for overworked clinical staff, they provide objective output measurement in critical care, and they offer dignity preservation in selected palliative scenarios. But they also introduce infection risk, urethral trauma, prolonged immobilization, and psychological distress that patients rarely volunteer unless asked directly. Every placement decision should survive the question of whether the same clinical goal could be achieved with less invasive means, and every removal should happen at the first opportunity when the indication no longer applies. The catheter that stays in one day longer than necessary is a failure of judgment, not a failure of technique, and distinguishing between those two categories is what separates competent practitioners from careless ones.
When to Call for Help Before You Begin
Certain anatomical and clinical situations warrant early urology involvement rather than repeated blind attempts. Known urethral stricture with prior dilation history, recent pelvic trauma with suspected urethral injury, history of neurogenic bladder with complex sphincter dynamics, previous suprapubic catheter placement indicating chronic difficult access, and active genital or perineal infection all represent scenarios where standard catheterization carries elevated risk. A gentle retrograde urethrogram can map stricture location and severity in thirty minutes and prevents the catastrophic false passage that results from ignoring these warning signs. I keep a low threshold for calling urology early in these situations because the procedure takes fifteen minutes under direct vision and saves the patient from three attempted blind insertions that each cause incremental trauma and delay appropriate definitive management.