Understanding Anatomical Planes Without the Textbook Fluff
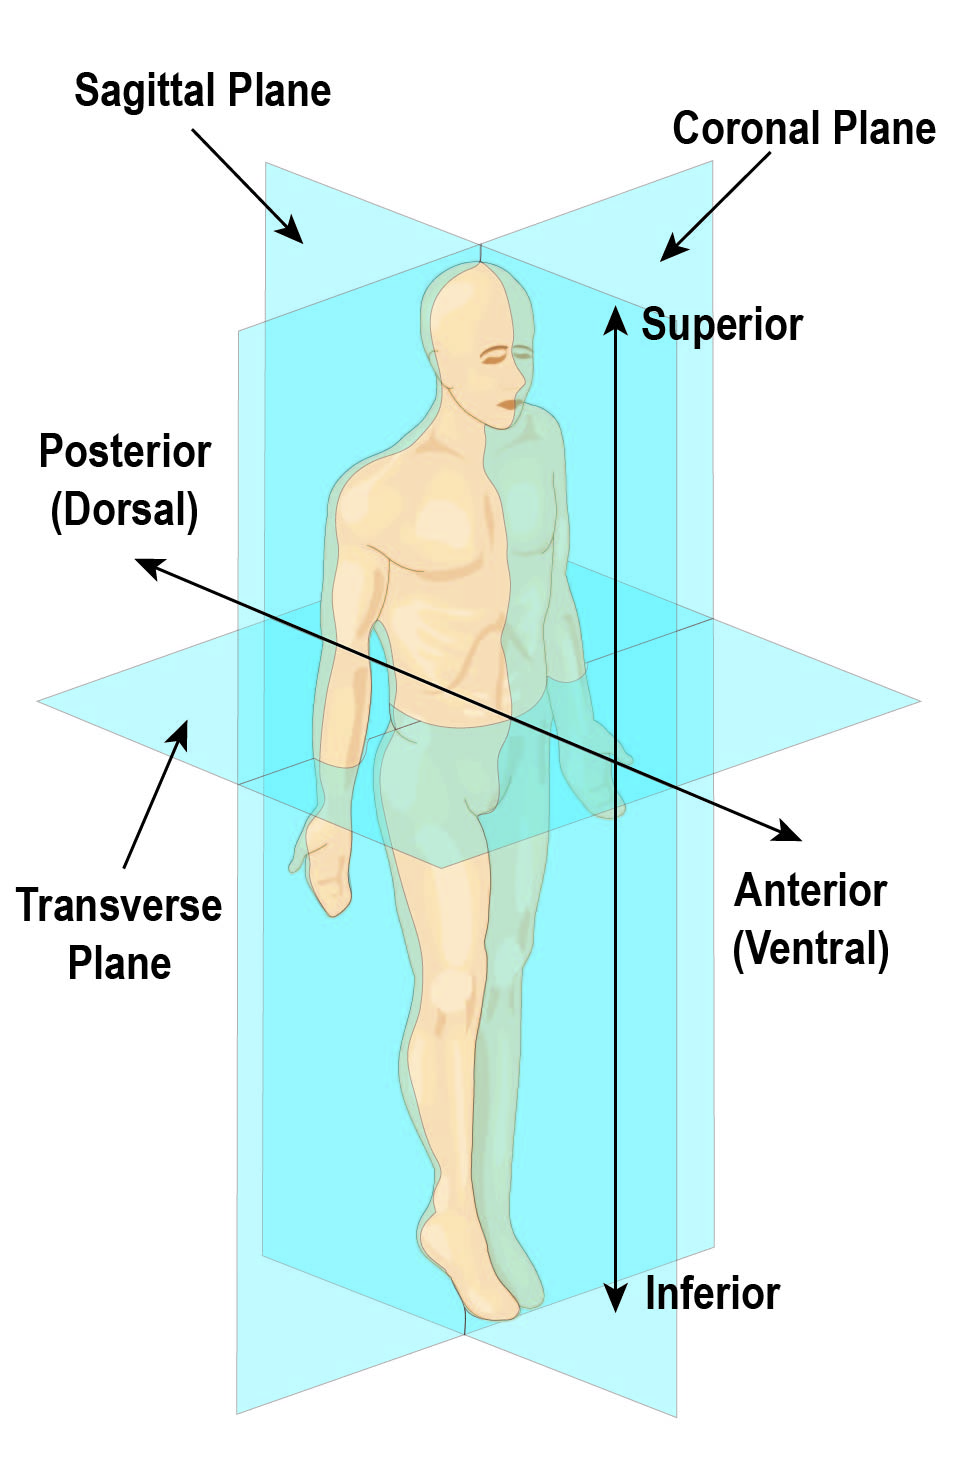
You open a CT scan on your screen and suddenly you're looking at a cross-section of someone's abdomen, and someone asks what plane that's in. If you hesitate, you've spent too much time memorizing terms and not enough time actually using them in the real world. The three main Planes Of The Body are the sagittal, coronal (frontal), and transverse (axial) planes. They divide the body into different views for imaging, surgery, and anatomical reference. That's the definition. Here's what nobody tells you about actually working with them. The sagittal plane divides the body into left and right portions. The mid-sagittal plane runs straight down the middle. Oblique sagittal is anything off-center. I remember early on I kept confusing the radiologist's reference to a "sagittal reformatted image" with an actual sagittal slice from the scanner. On most CT scanners, the raw acquisition is axial. Sagittal images are post-processed reconstructions. So when someone says "look at the sagittal," they usually mean a reformation, not a direct acquisition. It costs extra reconstruction time and sometimes the resolution looks degraded compared to the original axial stack. This matters when you're scrolling through 500 slices and trying to find a small lesion. A reformatted sagittal view might smooth over something you'd catch in the native axial data. My workaround was to always pull the original axial series back up if a sagittal reformation looked ambiguous. Takes about thirty seconds and saved me from missing a two-millimeter mass once. The coronal plane splits the body into front and back sections. The transverse or axial plane cuts it into top and bottom. These are the bread and butter of medical imaging. Most scanners acquire in the axial plane by default because of how the gantry works. MRI can acquire in any plane natively, which is why you'll see true coronal slices more often in MR studies. I work with both. Here's a counter-intuitive thing: just because a coronal view exists doesn't mean it's better for every structure. For example, the pancreas sits in a weird retroperitoneal position and its long axis runs somewhat obliquely across the body. Standard axial slices cut through it nicely, but a coronal reformation might slice it at an unfavorable angle depending on patient positioning. I learned this the hard way during residency when a coronal view made a pancreatic lesion look smaller than it actually was in axial. I went back to the axial source images and measured it properly. The lesion was six millimeters bigger. That difference changed the staging.
Another thing beginners miss: oblique planes matter more than textbooks admit. In musculoskeletal imaging, you'll often need an oblique sagittal view to properly align with the ACL in the knee, or an oblique axial view for the rotator cuff tendons. The standard planes are a starting point, not a rule. You rotate the reconstruction plane to match the anatomy you're trying to visualize. I spend more time adjusting oblique angles than I do scrolling through standard views now. It's a skill that takes maybe two months of deliberate practice to get comfortable with, and then it becomes second nature.
Practical Tips for Actually Using These Planes
If you're learning this for the first time, don't just read about the planes. Open a free DICOM viewer and load up a public dataset. Radiopaedia and the TCIA website have free cases. Scroll through axial slices, switch to coronal and sagittal reformats, and notice where structures disappear or appear as you move between planes. This takes about twenty minutes and will teach you more than a week of flashcards. I wish someone had told me this sooner. The spatial relationship between planes only clicks when you've actually manipulated the images yourself. Also, pay attention to patient positioning. A patient rotated slightly in the scanner will throw off your coronal and sagittal reformatting. You'll see the spine curve when it shouldn't, or the shoulders will sit at different heights in the coronal view. In those cases, you need to reorient the dataset before trusting any measurements. Most modern workstations have an auto-reformat feature, but it's not perfect. I've seen it make the liver look like it has a mass because the reformat angle was off by a few degrees. Manually adjusting the plane alignment takes maybe ten seconds and prevents that kind of error. The main limitation of relying on reformatted planes is partial volume averaging. When you reconstruct a sagittal slice from axial acquisitions, each reformatted slice is actually a blend of adjacent axial data. Fine details get blurred. This is especially noticeable in high-resolution studies of the inner ear or the pituitary gland. For those structures, native plane acquisition is always preferable. If your scanner supports it, ask for thin-slice native coronal or sagittal sequences instead of relying on reformatting. The difference in diagnostic quality is measurable.
Get the Full Details

When Planes Of The Body Fall Short
Not every clinical question fits neatly into these three planes. Complex trauma cases often require 3D volume rendering or curved planar reformats that trace along a vessel or the GI tract. The standard orthogonal planes can miss injuries that run along an oblique path. I've seen a splenic laceration that looked subtle in axial and coronal views become obvious on a curved reformat following the spleen's natural contour. Similarly, spinal nerve roots are hard to assess in standard planes because they exit at angles that don't align with any single reformation. You need multiplanar reconstructions with adjustable angles for that. It's slower and requires more manual work, but it's necessary when the standard views aren't enough. There's also the issue of radiation dose. If you're ordering additional reformatting for a study that was already borderline on dose, some institutions will push back. CT dose index values matter in pediatric and young adult cases. A standard abdominal CT with routine multiplanar reformats is different from one where you're requesting multiple specialized oblique reconstructions. The raw dose is the same since reformats are computed from the same dataset, but the perceived need for additional imaging can lead to repeat scans, and that's where dose adds up. It's a minor point but worth keeping in mind, especially in follow-up cases where you're tracking disease over time.