How to Actually Use a Planes Of The Body Diagram When Reading CTs or MRIs
Most people look at a Planes Of The Body Diagram and stop there. They memorize the three labels—sagittal, coronal, axial—and think they understand spatial anatomy. That is not the same thing as being able to read cross-sectional imaging. The diagram is a starting point, not a reference you pull out when you are stuck.
I have spent years reading radiology on PACS workstations. The diagrams in anatomy textbooks show perfect perpendicular cuts through a symmetrical body. Clinical scans are rarely like that. Patients arrive rotated, tilted, or positioned asymmetrically because they cannot lie flat. If you are matching textbook planes to real studies without accounting for patient rotation, you will mislabel everything.
Using a Planes Of The Body Diagram Correctly in Practice
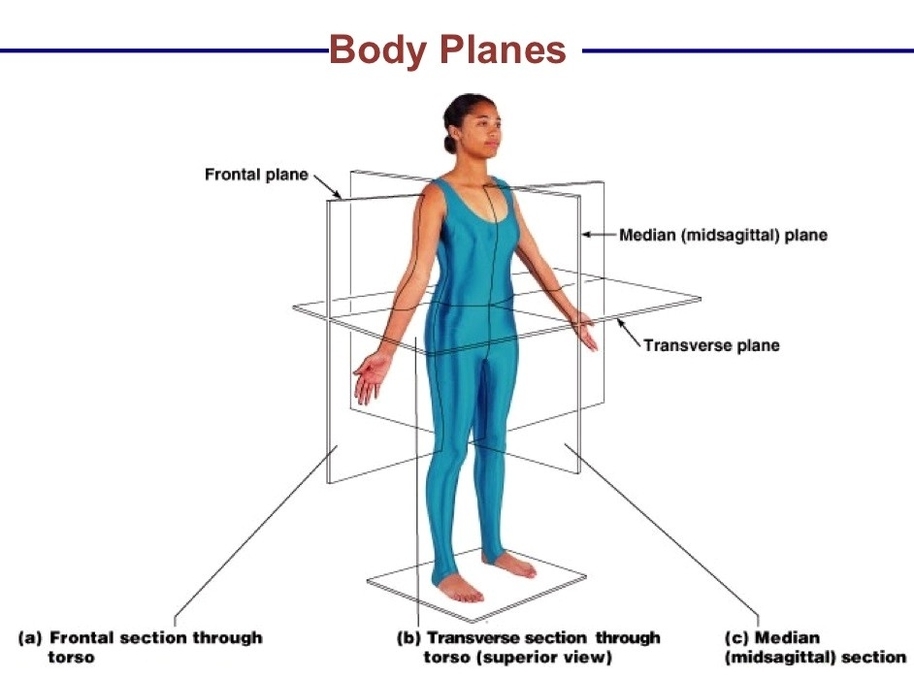
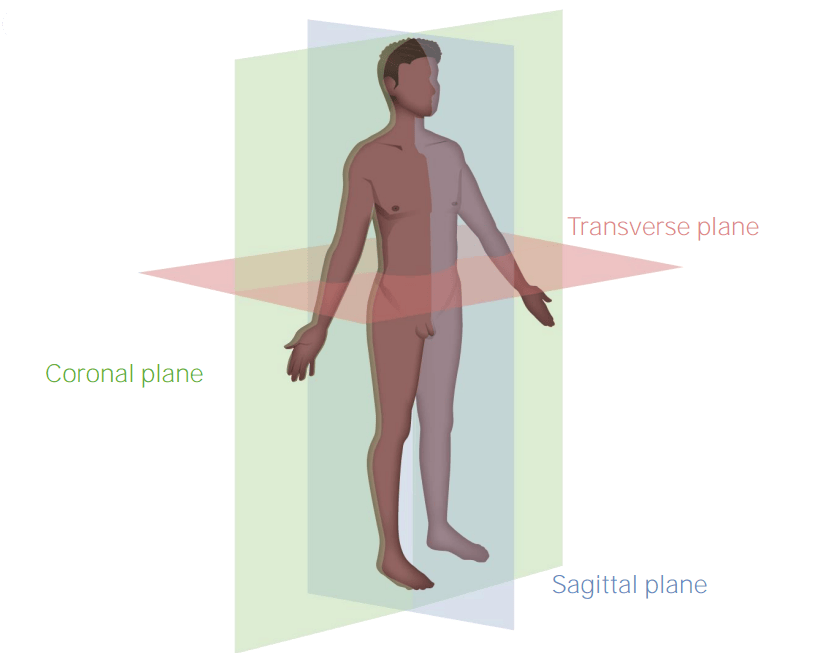
The sagittal plane divides left from right. In imaging terms, a true sagittal slice runs parallel to the midline. A paramedian sagittal slice is off-center but still sagittal. Oblique sagittal is where most beginners get tripped up—it looks sagittal but is actually angled, and the structures on it do not correspond to standard anatomical references. You can use the Planes Of The Body Diagram as a mental anchor to check whether your reconstruction is truly sagittal. If the vertebral bodies and the spinal canal are not aligned in a single vertical column, your plane is oblique and needs correction.
The coronal plane divides anterior from posterior. It runs perpendicular to the sagittal plane. On a coronal reconstruction, you should see the shoulders symmetrically, the iliac crests level with each other, and the spine centered. If one hemidiaphragm appears higher than the other without an obvious pathological reason, the patient was likely rotated during the scan. I encountered this exact problem on a chest CT where the coronal slices showed what initially looked like a right hemidiaphragm elevation. The diagnostician on call was about to call a possible subpulmonic effusion. I reoriented the multiplanar reconstruction using the patient's actual spinous process line instead of assuming symmetry, and the "elevation" disappeared. It was purely rotational artifact. This happens more often than you would expect, especially in trauma and obese patients.
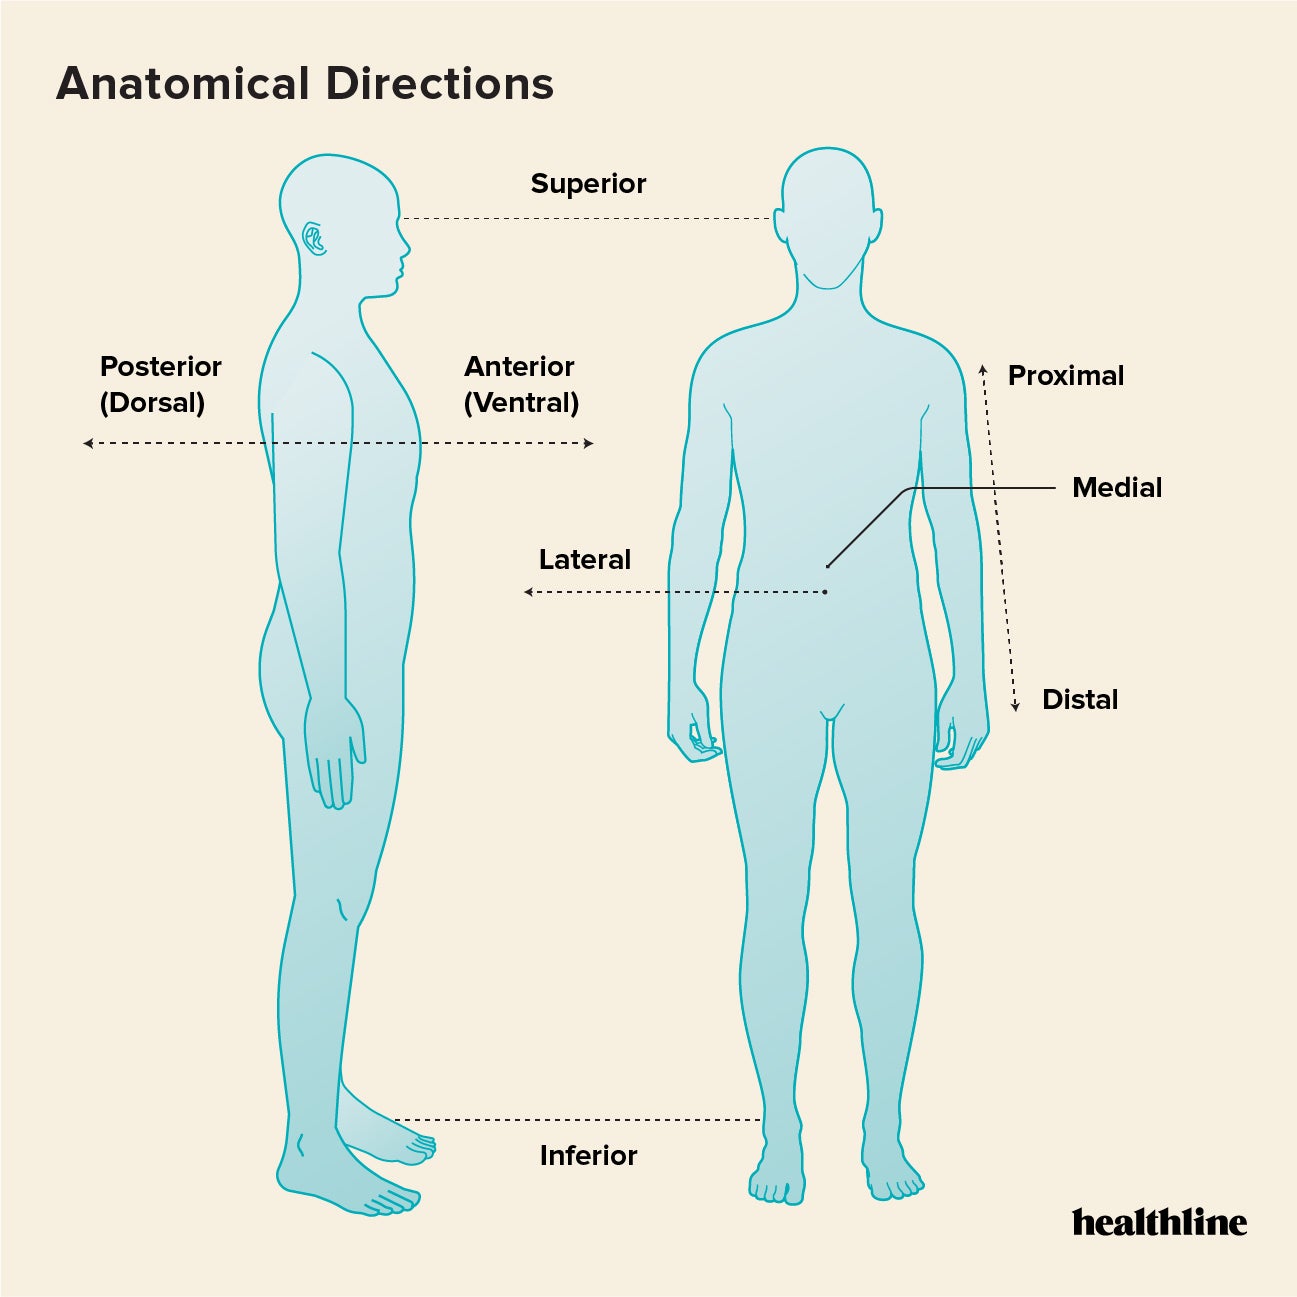
The axial plane divides superior from inferior. This is the standard acquisition plane for most CT protocols. Axial images are intuitive because they match the way we typically view cross-sections. The confusion comes when people forget that axial does not mean horizontal in the room. It means perpendicular to the long axis of the body. For the cervical spine, the long axis is tilted forward. Axial cuts through the C-spine are angled relative to the floor of the scanning room. If you interpret C-spine axial images as if the patient were lying perfectly straight, you will misread the uncovertebral joints and the neural foramina.
Here is the practical workflow I use. First, I confirm the orientation by finding the midline sagittal and a true coronal reference. These two planes tell me immediately whether the patient was positioned correctly. Then I switch to axial and adjust my interpretation based on what the reference planes revealed. This takes about thirty seconds and prevents more errors than I can count.
What the Diagram Does Not Tell You
Anatomy diagrams show idealized planes. They do not show that clinical imaging routinely includes oblique reconstructions that serve a purpose. Cardiac CT uses oblique axial and short-axis views that follow the heart's orientation, not the body's. MRI of the knee often uses a true sagittal plane that is oblique relative to the body because the knee is flexed and the femur is angled. If you rigidly apply textbook sagittal-coronal-axial to every study, you will misinterpret these intentional obliques as positioning errors.
Another issue is that the three standard planes do not always provide the best view for a given structure. The gallbladder, for example, is often better visualized on an oblique plane that follows its long axis rather than on a strict axial cut. The pancreatic duct is similarly easier to trace on a reformatted oblique coronal. The Planes Of The Body Diagram gives you the framework. It does not replace the judgment about when to tilt the reconstruction.
Common Mistakes That Waste Time
The most frequent error I see is treating the Planes Of The Body Diagram as a checklist rather than a spatial reference. People verify "is this sagittal?" without checking whether it is a true or paramedian sagittal. They confirm the plane exists but miss that the slice is three centimeters off the midline and therefore showing the spleen instead of the stomach. Plane identification and slice localization are two different skills. The diagram teaches the first. You learn the second by actually looking at hundreds of studies.
A second mistake is assuming the diagrams apply uniformly across all modalities. X-ray is projectional, not sectional. A plain film does not show any of the three planes directly—it projects everything onto a single 2D surface. Ultrasound is operator-dependent and produces whatever plane the transducer is held in, which may not align with any of the standard anatomical planes at all. MRI and CT are the modalities that give you volumetric data suitable for multiplanar reconstruction. The Planes Of The Body Diagram is relevant primarily to those two.
When the Standard Three Planes Fail You
There are scenarios where sagittal, coronal, and axial are simply insufficient. Complex fractures of the pelvis and acetabulum often require oblique planes tailored to the fracture lines. Pre-surgical planning for hip arthroplasty uses custom reconstructions that follow the femoral neck axis. Tumors that span multiple anatomical compartments may be better mapped on curved planar reconstructions that unwrap tubular structures. I once spent twenty minutes trying to characterize a renal mass on standard axial and coronal views, only to resolve it in under a minute by creating an oblique plane along the renal hilum. The mass was clearly exophytic and separate from the collecting system once viewed from that angle.
This is the honest limitation of relying on the Planes Of The Body Diagram: it covers the standard cases well, and standard cases make up the majority of routine imaging. But when you encounter the non-standard cases, the diagram alone will not guide you. You need to understand the underlying spatial geometry so well that you can generate your own planes on the workstation.
What to Actually Download
If you are looking for a static image of a Planes Of The Body Diagram, there are plenty of free resources from anatomy departments and radiology education sites. What you will not find as a free download is a functional interactive model where you can rotate the planes in real time and see how they intersect with actual anatomy. That requires either a 3D anatomy application or a PACS workstation with MPR capability. The free diagrams are useful for initial learning. They become inadequate the moment you need to apply them to real clinical cases.
The most practical approach is to keep a simple reference diagram open while you train on cross-sectional atlases. Radiology libraries like Radiopaedia and the ACR Atlas provide annotated axial, coronal, and sagittal examples paired with labels. You read the diagram, then immediately apply it to a real scan. This pairing builds the spatial intuition that a static image alone cannot provide.
I stopped relying on printed diagrams after my first year of residency. They were helpful for learning the vocabulary, but fluency came from continuous practice on actual studies. The Planes Of The Body Diagram is a tool, not a destination. Use it to build your mental model, then move on to the cases.
Gallery Planes Of The Body Diagram
Anatomical Planes Of Human Body
Body planes diagram
Body Planes and Anatomical Directions Pt. 2 Diagram | Quizlet
Anatomical Planes Of Human Body
The 3 Anatomical Body Planes and The Movements In Each