Reading Chest Radiographs for Pleural Fluid
I still get calls from residents at 2 AM when a PA chest x-ray shows blunting of the costophrenic angle and they want to know if it's real or artifact. It happens more often than you'd think. The thing about detecting pleural effusion on plain film is that the classic textbook presentation—the meniscus sign, the obliterated diaphragm shadow—is only visible when there's enough fluid. We're talking roughly 200 to 300 milliliters on a PA view before it becomes reliably detectable. Less than that and you're guessing, and guessing is how you miss things. The lateral decubitus view is what actually matters in practice. When you can't tell if a basal opacity is consolidation or fluid, laying the patient on their side with the suspected side up lets gravity do the work. Free-flowing fluid layers along the lateral chest wall. If the fluid tracks up the wall, it's mobile. If it stays put, you're probably looking at loculated fluid or something else entirely. I had a case last year where a CT showed a massive unilateral effusion but the decubitus film showed almost no layering. Turns out the patient had multifocal pneumonia with parapneumonic fluid that was already starting to fibrinize. The x-ray didn't lie—it just told you something important about the nature of the fluid.
What You're Actually Looking For on a Pleural Effusion X Ray
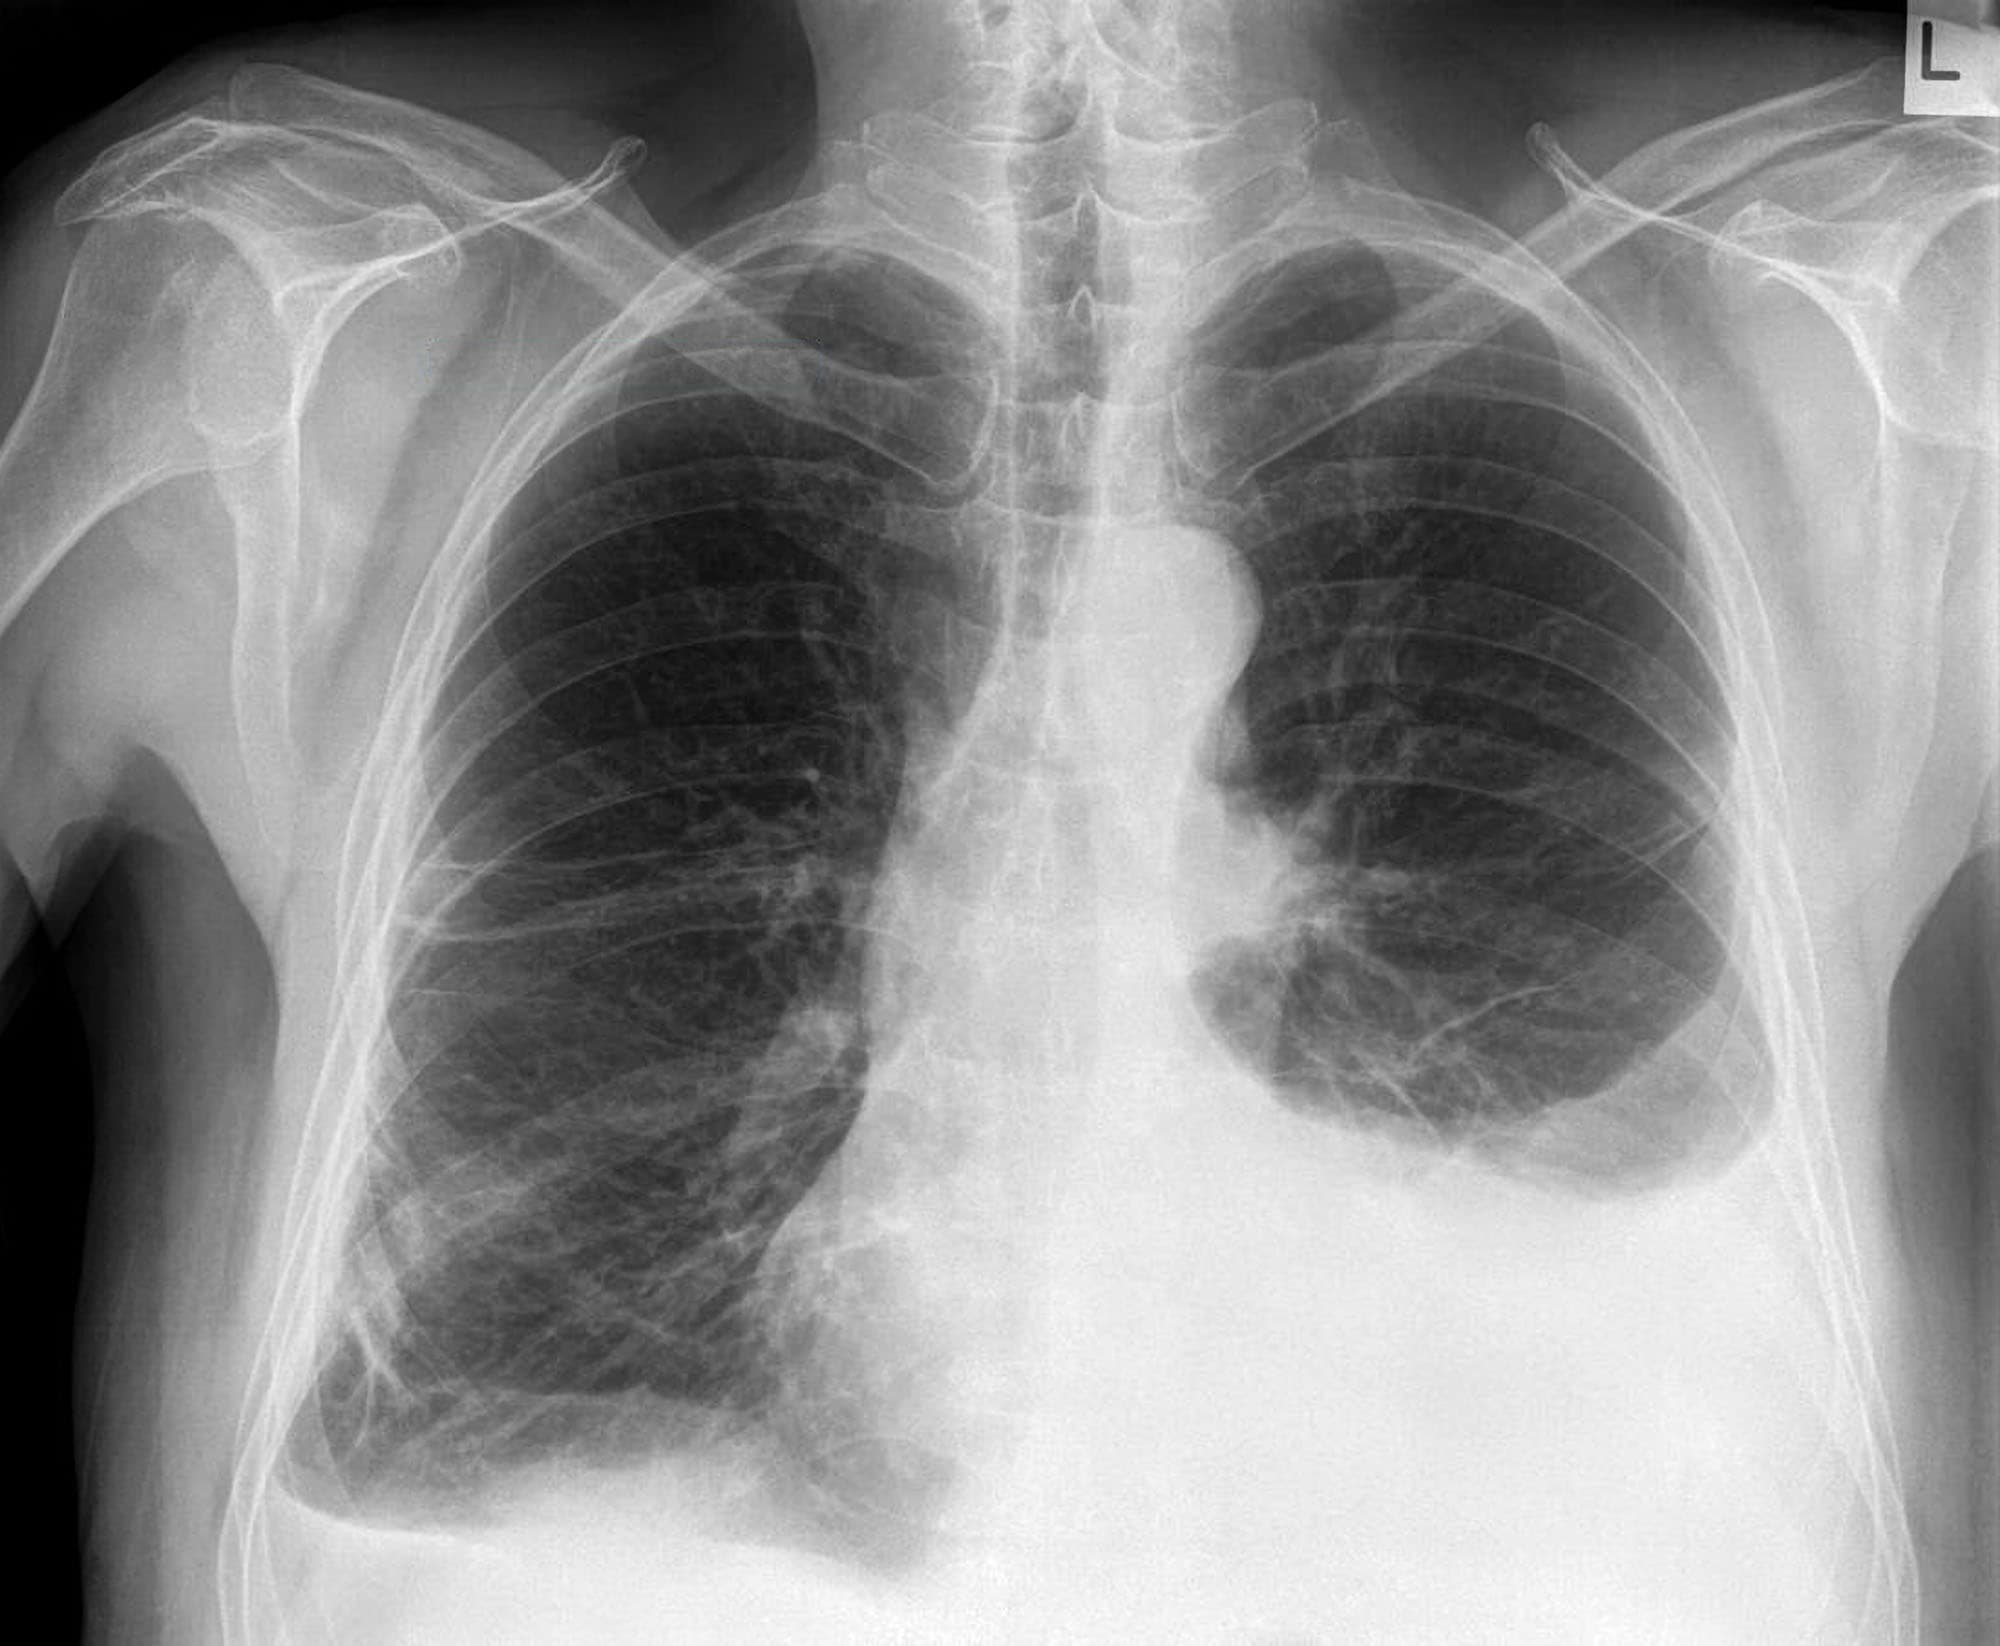
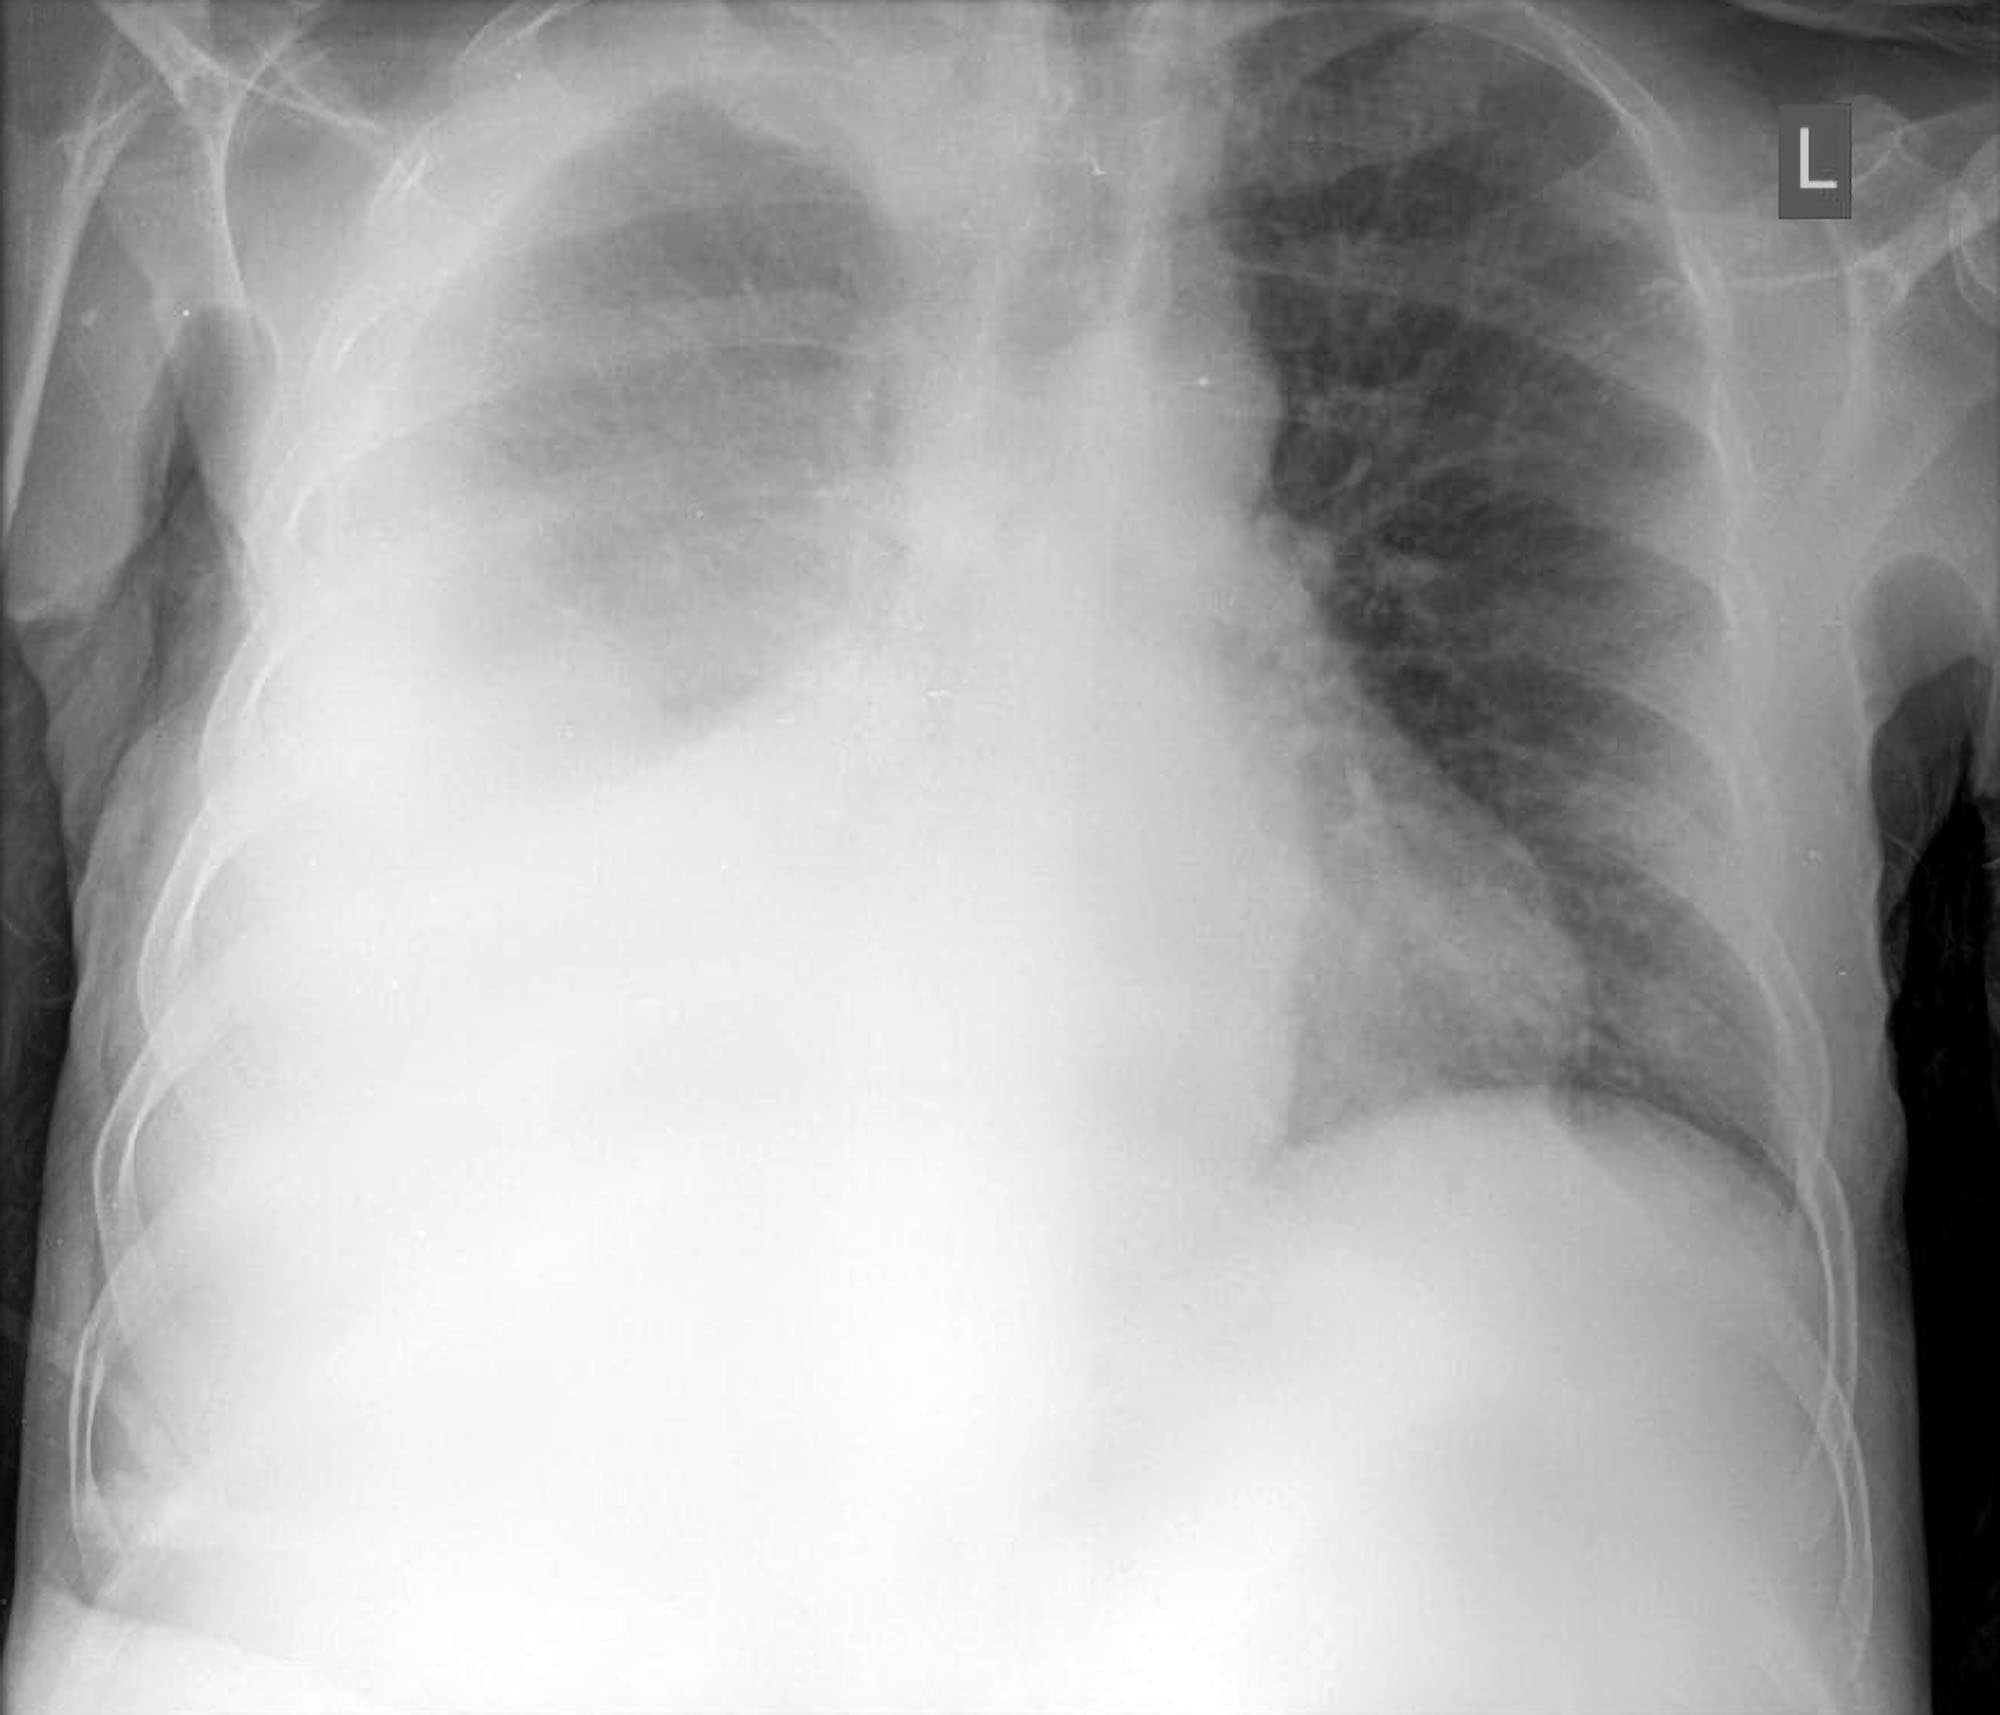
Start with the costophrenic angles. On a properly positioned PA film with full inspiration, both angles should be sharp and acute. Blunting can mean a small effusion, but it can also mean pleural thickening from prior inflammation, a rounded atelectasis bubble, or even just a poorly inspired film where the diaphragm sits too high. The key differentiator is whether the blunting has a meniscus—curving upward laterally—or whether it's a flat, geometric edge. Meniscus suggests free fluid. Flat edges suggest chronic pleural change. The lateral view catches what the PA view misses. The posterior costophrenic sulcus is the deepest part of the pleural space when upright. As little as 50 milliliters can blunt it on a lateral film compared to the 200 to 300 milliliters needed on PA. If you're ordering chest x-rays for suspected effusion and only getting a PA, you're underdetecting by a meaningful margin. I've seen three separate readers disagree on whether a small effusion was present on a PA-only study. The lateral changed two of their calls. There's a nuance with supine films that everyone forgets. When a patient is bedbound and you get an AP supine portable, fluid doesn't pool at the bases the way it does upright. It spreads out along the posterior pleural space as a diffuse haziness over the entire hemithorax. The classic "white out" appearance on a supine film can represent liters of fluid, but it can also be diffuse consolidation or pulmonary edema. The landmark sign here is the oblique fissure—if it's displaced laterally or inferiorly, that's fluid pushing on it. Also, look for the medial costophrenic sulcus. Even supine, that pocket sometimes retains a bit of air that gets compressed by underlying fluid.
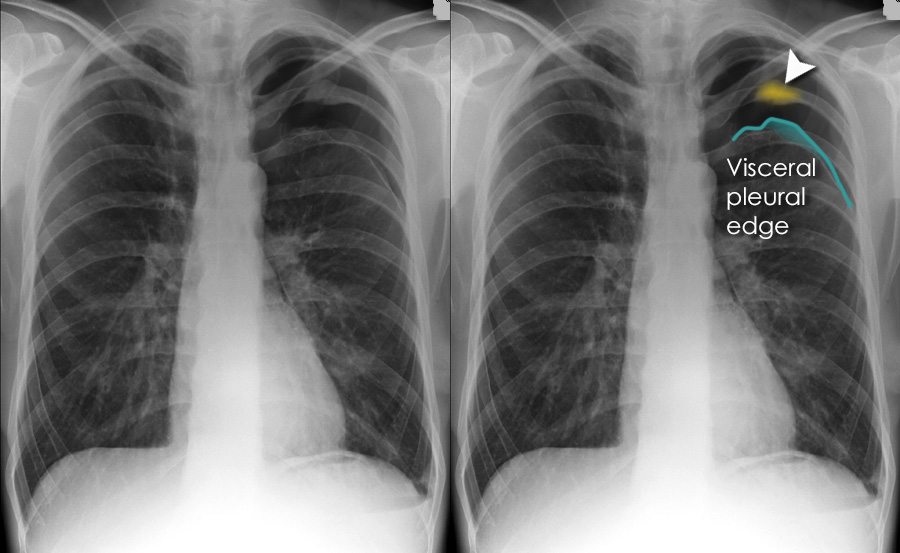
One thing that trips people up: pneumothorax and effusion can coexist, and the x-ray findings interact in ways that mask each other. A hydropneumothorax shows an air-fluid level. But with a simple concurrent pneumothorax and small effusion, the effusion can actually make the pneumothorax harder to see because the fluid displaces lung peripherally and creates a false impression of normal lung markings. I learned this the hard way on a trauma call where the initial read called a clear right chest, the CT showed a moderate pneumothorax and a small effusion, and the attending reminded me that fluid at the base can pull the lung away from the chest wall in a way that hides the apical pneumothorax on the same film. Quantifying effusion size on x-ray is more art than science. You can estimate volume by how much of the hemithorax is opacified—a rough rule of thumb says one-sixth of a hemithorax opacity corresponds to roughly 500 milliliters, two-thirds opacity is around 1500 milliliters—but this breaks down quickly with chronic effusions where the lung has re-expanded somewhat or with loculated collections that don't follow gravitational patterns. Ultrasound is strictly superior for volume estimation and for determining if fluid is free-flowing versus loculated. If you need to know how much fluid is there for procedural planning, skip the x-ray math and just use bedside ultrasound. It takes about ninety seconds and tells you the depth of the fluid pocket at any given intercostal space. The main limitation of plain film for pleural effusion is sensitivity at the low end and specificity when the presentation is atypical. Small effusions get swallowed by overlying breast shadows, enlarged cardiac silhouettes, or poor inspiratory effort. Atypical presentations—like subpulmonic effusions that mimick an elevated hemidiaphragm, or posterior loculated collections that only show as a vague density on the lateral—require a high index of suspicion and often a follow-up CT anyway. If the clinical picture doesn't match the x-ray findings, don't chase the film. Order the CT or the ultrasound.
Get the Full Details