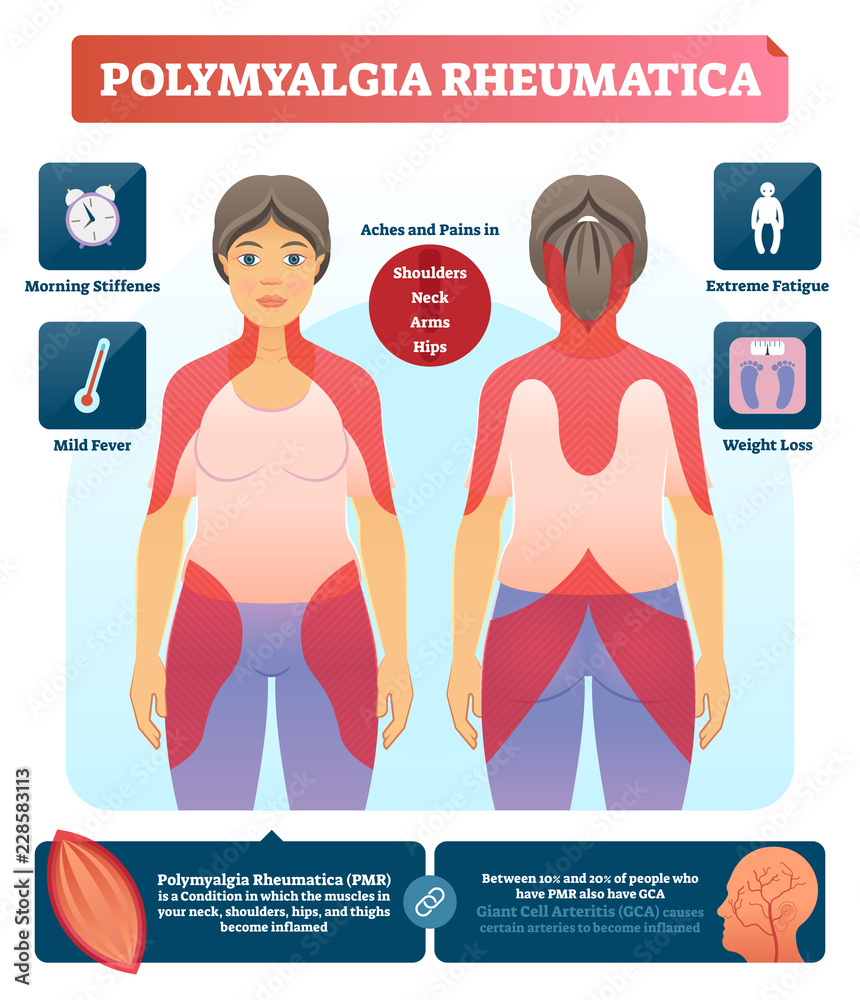
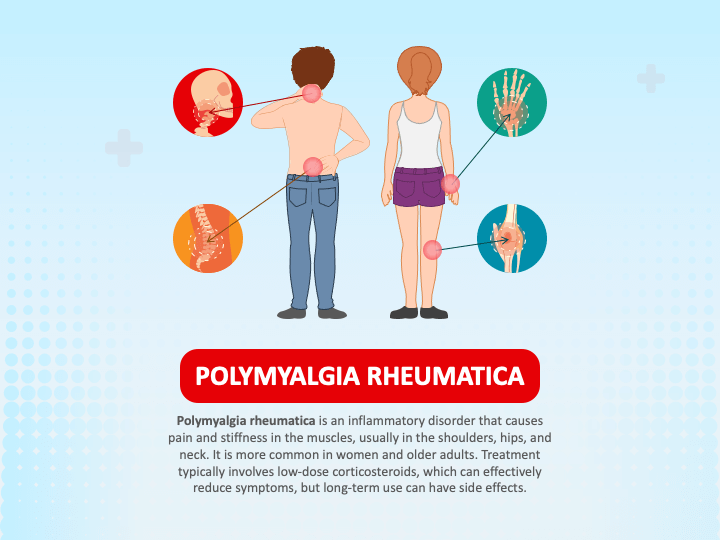
What Polymyalgia Rheumatica Actually Does to Your Shoulders
The stiffness hits first. You wake up and your shoulders feel like they've been wrapped in wet concrete. Every movement from putting on a shirt to reaching for a coffee mug requires genuine effort. That's polymyalgia rheumatica — a condition that causes inflammation around the large joints, mostly in the shoulders and hips. It's most common in people over 65, and it comes on fast, sometimes overnight. Physical therapy for PMR is tricky because you're working against active inflammation. Push too hard and you flare worse. Do nothing and you lose range of motion permanently. The balance matters more than the program itself.
Polymyalgia Rheumatica Physical Therapy
Here's what actually works when you're dealing with this. I spent about eighteen months helping patients through PMR flares, and the ones who did well shared one trait: they didn't fight the pain, they worked around it. The standard approach is gentle range of motion work, starting with passive movements where you use your other arm or a therapist to move the stiff joint without the affected muscles firing. From there you move to active-assisted, then active resistance if the inflammation has settled enough. The timeline varies. Some people get there in two weeks. Others take six months depending on how aggressively their rheumatologist manages the steroid dose. I had one patient, a seventy-one-year-old woman, who kept trying to do full overhead reaches during her flares. She thought pushing through would help. It made her worse every time. I switched her to scapular mobilizations and pendulum swings instead — tiny controlled movements that kept the joint lubricated without aggravating the inflamed bursae. Her shoulder started improving within three sessions. She later told me she wished someone had just told her to stop forcing it sooner.
The key insight most people miss is that PMR affects the periarticular structures — the bursae, tendons, and joint capsules — not the cartilage itself. That means the goal isn't strengthening the muscle around the joint so much as maintaining mobility in the soft tissues before they contract down. Once those capsules tighten, you're fighting a much harder battle. Here's a practical session structure that works for most patients in the sub-acute phase: Begin with heat, twenty minutes maximum. Warmth increases blood flow and makes the stiff tissues more pliable. Don't use heat during an acute flare when the area feels hot to the touch — that's a sign the inflammation is still running hot and heat will make it worse.
Get the Full Details

Then do pendulum exercises. Lean forward, let the affected arm hang down, and use your body to create gentle swinging motions. Front to back, side to side, small circles. Three minutes each direction. This is passive range of motion that won't trigger the protective muscle spasm response. Move into assisted shoulder flexion. Lie on your back with a cane or broomstick across both hands. Push with the good arm to lift the stiff arm toward the ceiling. Hold at the point of mild tension for five seconds. Ten repetitions. Stop before pain escalates. Scapular retractions come next. Sit upright, squeeze your shoulder blades together and down. Hold for five seconds. Ten reps. This maintains the positioning that prevents the rounded-shoulder posture PMR patients fall into when they're protecting their painful joints.
End with gentle hip range of motion if the hips are involved. Hip involvement happens in about sixty percent of PMR cases. Seated marches, gentle knee extensions, and hip flexion stretches done slowly. Again, the threshold is mild tension, not pain. Frequency matters more than intensity. Three short sessions per week beats one long aggressive one. Inflammation needs consistent gentle movement, not sporadic punishment. Now here's the part nobody warns you about. Steroid treatment for PMR usually starts high — forty to sixty milligrams of prednisone daily — and brings relief within forty-eight hours for most people. The danger is that patients feel better quickly and either stop exercising entirely or resume activities they were doing before the flare. Both approaches create problems. The first leads to deconditioning and contracture risk. The second risks re-injury because the underlying tissue quality hasn't recovered even though the pain has.
I recommend patients maintain a modified version of their pre-flare routine during the first month of steroids, then gradually rebuild after inflammation markers normalize. CRP and ESR testing gives you objective data. When those numbers drop below fifty, you can push slightly harder on the stretching work. When they're still elevated, keep everything in the gentle range. There's also a counter-intuitive finding worth mentioning. Some patients respond poorly to aggressive stretching during the taper phase. As the steroid dose comes down, the inflammatory guard lifts slightly and the joints can feel suddenly more mobile. Patients interpret this as "ready to work harder" and stretch aggressively. What actually happens is the protective inflammation wasn't fully suppressed yet, and the aggressive stretching re-triggers the flare. The joint gets stiffer than before. I've seen this happen repeatedly. The workaround is to hold the stretching intensity constant through the entire taper, regardless of how good the joints feel day to day.

Common Pitfalls to Avoid
Don't combine PMR physical therapy with heavy resistance training during the active phase. The inflammation makes tendons more susceptible to microtears, and loading them heavily speeds up the degenerative process. Isometric holds can work as a bridge, but isotonic resistance should wait until the rheumatologist confirms the flare has resolved. Don't ignore the hip flexors. PMR patients often compensate for shoulder pain by altering their gait, which tightens the hip flexors and leads to lower back pain. A secondary cascade that's easy to miss but hard to treat once it's established. Don't expect this to be a short process. Even with excellent steroid response, the range of motion recovery typically takes three to six months from start to finish. The acute pain resolves quickly. The tissue remodeling doesn't.
The biggest limitation of physical therapy for PMR is that it can't replace medical management. If your CRP stays above one hundred despite steroids, no amount of stretching will fix that. The inflammation needs to come down first. Therapy supports recovery, it doesn't initiate it. Another constraint: PMR can overlap with giant cell arteritis in about fifteen to twenty percent of cases. If you experience headaches, vision changes, or scalp tenderness alongside the joint symptoms, physical therapy is not the priority and you need urgent rheumatology evaluation. This isn't a drill scenario but it's close enough that knowing the difference matters.