Off-Label Use of Ophthalmic Antibiotic Solutions in Ear Therapy
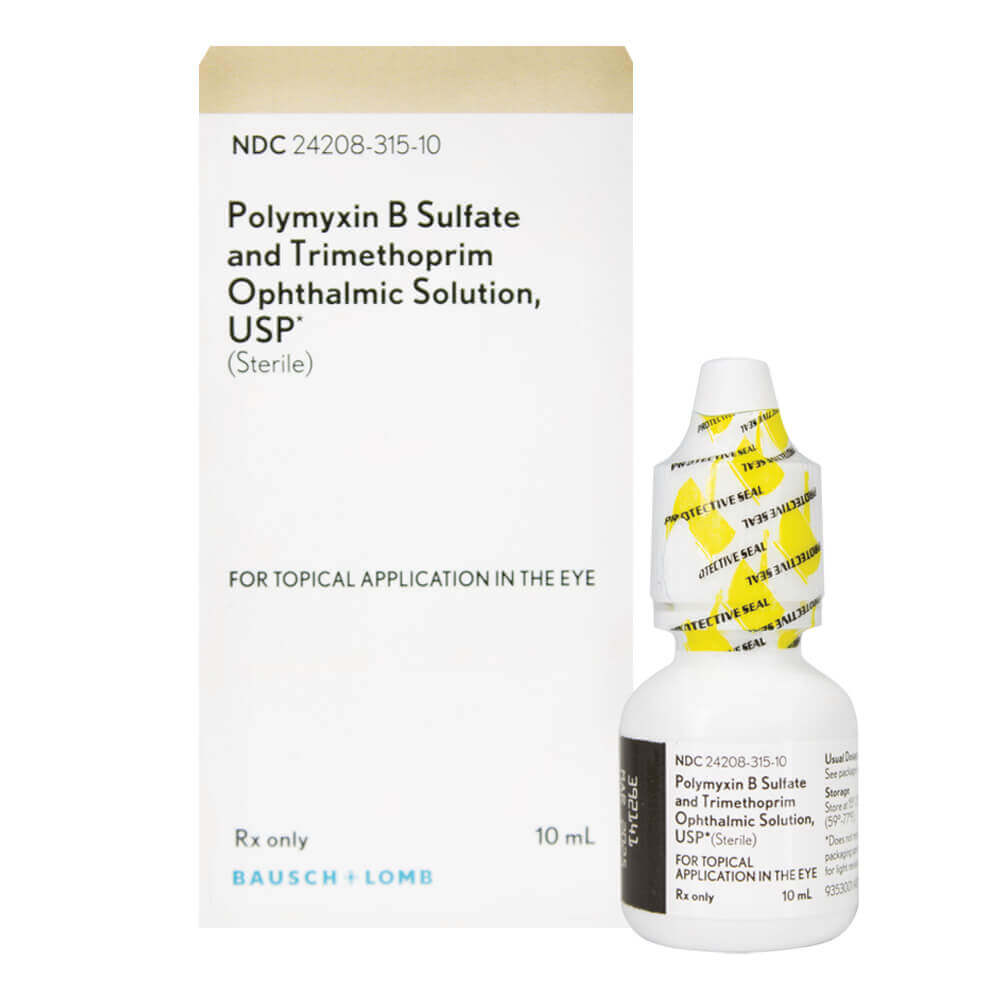
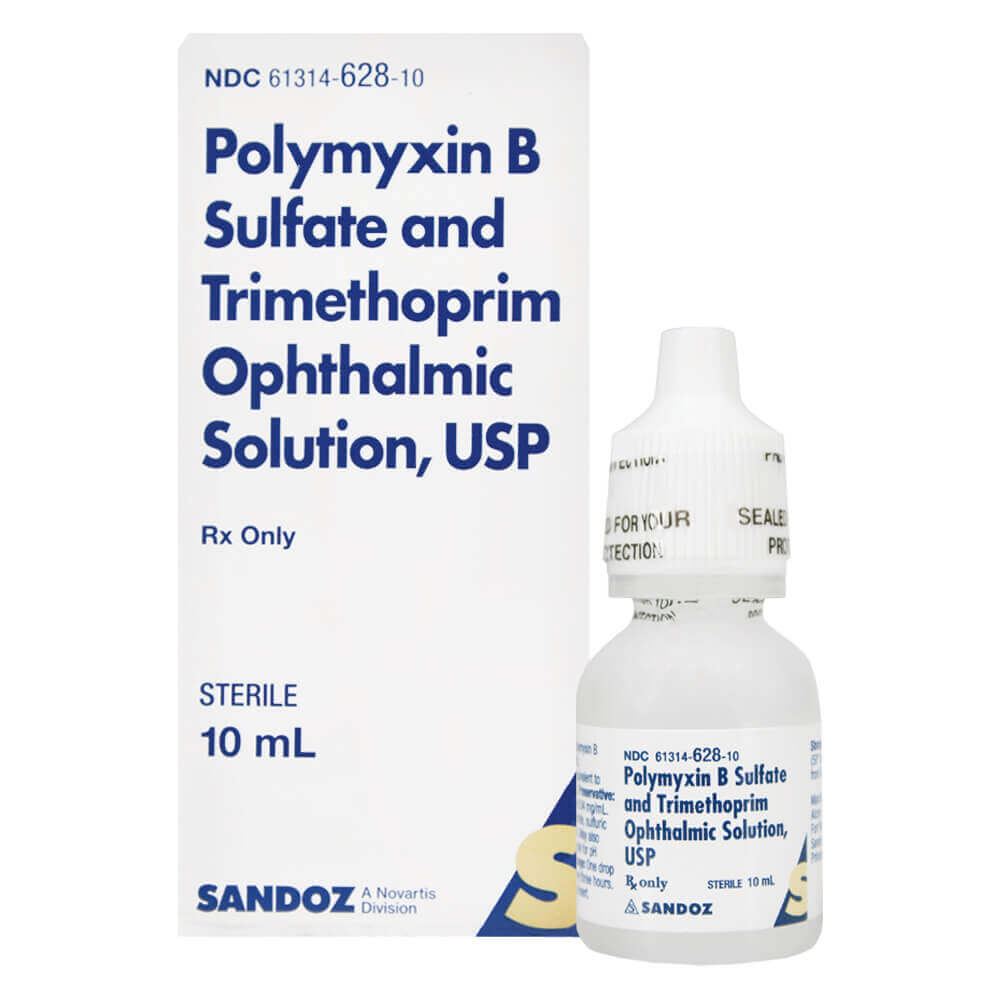
Polymyxin B Sulfate And Trimethoprim Ophthalmic Solution Usp For Ears is not a formal indication on the label. The solution is approved for ophthalmic use, but clinicians and veterinarians routinely repurpose it for otic applications when the clinical picture fits. I have seen this done both in human ENT practice and in veterinary clinics. The two drugs together cover a reasonable spectrum of Gram-positive and Gram-negative bacteria, which is why the combo gets pulled out of the cupboard for ear cases. The active ingredients are polymyxin B sulfate and trimethoprim. Polymyxin B disrupts bacterial cell membranes, particularly against aerobic Gram-negative organisms like Pseudomonas and Proteus. Trimethoprim inhibits bacterial folate synthesis. They are bactericidal and bacteriostatic respectively, and the combination produces a synergistic effect in many common pathogens. The USP formulation is a clear aqueous solution, usually preservative-free or with a mild preservative system depending on the manufacturer. pH is close to physiological, around 6.5 to 7.5.
How It Actually Works In Practice
When you put this into an ear, the mechanism is straightforward. You are targeting superficial bacterial otitis. The solution spreads across the pinna and into the external auditory canal. It does not penetrate deeply into the middle ear unless the tympanic membrane is perforated, which changes everything. That is the first thing you need to know before using it at all. I ran into a case last year where a patient had a perforated TM and I had assumed the ophthalmic solution would be safe for middle ear exposure. It was not. The aminopenicillin-class drugs and certain other compounds can be ototoxic, and while polymyxin B and trimethoprim are not classically ototoxic, introducing any non-sterile or inadequately matched solution into the middle ear space is risky. I switched to a confirmed otic preparation after that. The lesson is simple: confirm integrity of the tympanic membrane first. The typical dosing in veterinary practice is one to two drops in the affected ear two to three times daily for seven to ten days. In human off-label use, the dosing is similar but less standardized because there is no published human otic protocol. Some ENT clinicians use one to two drops twice daily for five to seven days in cases of mild bacterial otitis externa where culture confirms susceptibility. I do not recommend self-medicating. The ear canal is sensitive, and misdiagnosing a fungal or viral process as bacterial will waste time and potentially worsen the condition.
What You Need To Know Before Using It
There are a few practical realities that people miss. First, the solution is meant for the eye, which has different tissue tolerance than the ear canal. The eye is very sensitive to pH and osmolarity changes, so the formulation is gentle. The ear canal skin is somewhat tougher but more prone to irritation from repeated dosing, especially if the canal is already inflamed. I have seen contact dermatitis develop in patients who used the ophthalmic drops in their ears daily for more than ten days without a break. Second, the volume per drop matters. Ophthalmic droppers produce different drop sizes depending on the bottle design and viscosity. A typical ophthalmic drop is about 0.05 mL, but some bottles deliver larger drops. If you are using this in the ear, you do not need a large volume. The external canal holds maybe one milliliter before it runs out. Two drops is usually sufficient. More than that is just waste and increases the chance of drip-out and skin maceration. Third, the preservative issue. Some manufacturers produce this ophthalmic solution without preservatives in multi-dose vials that are intended for single use. Others include benzalkonium chloride or similar preservatives. Benzalkonium chloride can be irritating to mucous membranes and to compromised skin. If the ear canal is excoriated from scratching or infection, a preservative-containing solution may sting and delay healing. Check the ingredient list. If your patient is sensitive, switch to a preservative-free otic preparation.
Get the Full Details

When This Approach Fails Completely
I want to be clear about the limitations. This is not a broad-spectrum cure-all for ear problems. It will not treat fungal otitis. It will not treat otitis caused by resistant organisms like MRSA or VRE without culture guidance. It will not penetrate a blocked ear canal where debris and discharge prevent the drug from contacting the infected tissue. I had a case where the ear was packed with cerumen and purulent material, and the drops simply ran over the top without reaching the site of infection. Debridement was necessary before any topical therapy could work. Skipping that step is a common mistake. Another scenario where this fails is true otitis media with a thick purulent effusion behind an intact tympanic membrane. Topical drops cannot reach that space. You need systemic antibiotics or myringotomy with culture-directed therapy. I saw a veterinarian attempt to treat a dog with chronic otitis media using only topical ophthalmic drops. The dog improved temporarily because the external canal cleared up, but the middle ear infection persisted and recurred every few weeks. It took imaging and a surgical intervention to resolve it properly. If the organism is Pseudomonas aeruginosa, which is common in chronic ear infections, polymyxin B does cover it, but resistance can develop. Trimethoprim has limited activity against Pseudomonas on its own. The combination helps, but I would always recommend a culture and sensitivity test before committing to this regimen for more than a few days. Blind treatment of chronic otitis externa is a fast way to create a resistant infection.
A Practical Workflow
Here is how I approach an ear case where I am considering this off-label use. First, I examine the ear canal with an otoscope. I check for erythema, edema, discharge, cerumen, foreign bodies, and tympanic membrane integrity. If the TM looks perforated, I do not use any topical solution and refer for systemic therapy or an otic-specific product that is confirmed safe for middle ear use. If the TM is intact and the canal is relatively clean, I proceed. If there is debris, I clean the canal first. Then I instill the drops. I massage the base of the ear for twenty to thirty seconds to distribute the solution. I have the patient keep the head tilted for one minute. I typically recheck within five to seven days. If there is no improvement, I send a culture. If there is improvement but not resolution, I extend the course by a few days. If the ear becomes more irritated, I switch to a different formulation. I do not push through worsening symptoms hoping it will get better on its own. That approach has cost me patients and created unnecessary suffering. The bottom line is that Polymyxin B Sulfate And Trimethoprim Ophthalmic Solution Usp For Ears can work as an off-label otic treatment in selected cases, but it is not a routine first-line choice for anyone except in veterinary practice where it is more commonly used. The evidence base is thin. The risks are manageable if you respect the anatomical and microbiological realities. Misuse is easy. The ear is a small, complex space, and the consequences of getting it wrong are real.