The Polyvagal Ladder Worksheet: How It Actually Works
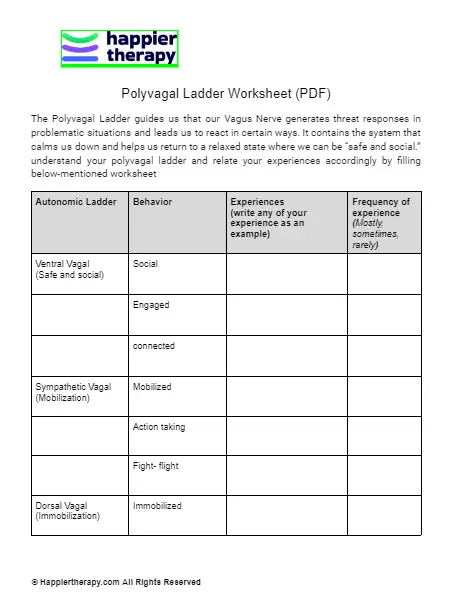
Most people I talk to about polyvagal theory get stuck on the hierarchy part. They can recite ventral, sympathetic, dorsal. The real problem is figuring out where you are in a given moment and what to do about it. That's where the Polyvagal Ladder Worksheet comes in, and honestly it's more useful than people give it credit for if you actually use it right. The worksheet is straightforward. It maps the three primary neural states from Stephen Porges' theory onto a visual ladder, with specific markers for each rung. You check off what applies to you right now — breathing pattern, muscle tension, social engagement cues, thought patterns — and it points you toward an intervention that matches that state. It's not a diagnostic tool. It's a quick reference for self-regulation during moments when you're already dysregulated and thinking clearly is hard. I've used this with clients in coaching settings, therapy prep work, and honestly just for my own tracking. The version I find most practical has a left column for self-observation, a middle column for matched interventions, and a right column for follow-up notes. You fill it out during or right after an episode, not weeks later when you've reconstructed the memory.How to Use a Polyvagal Ladder Worksheet
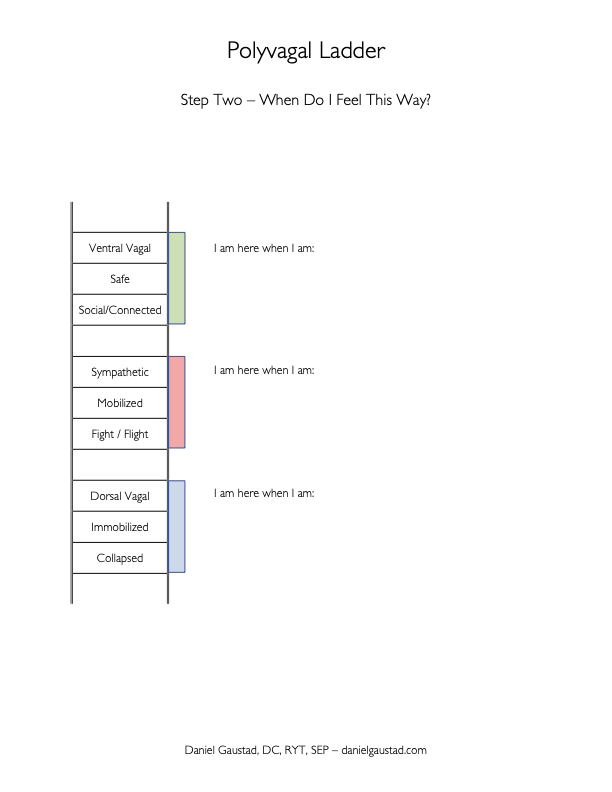
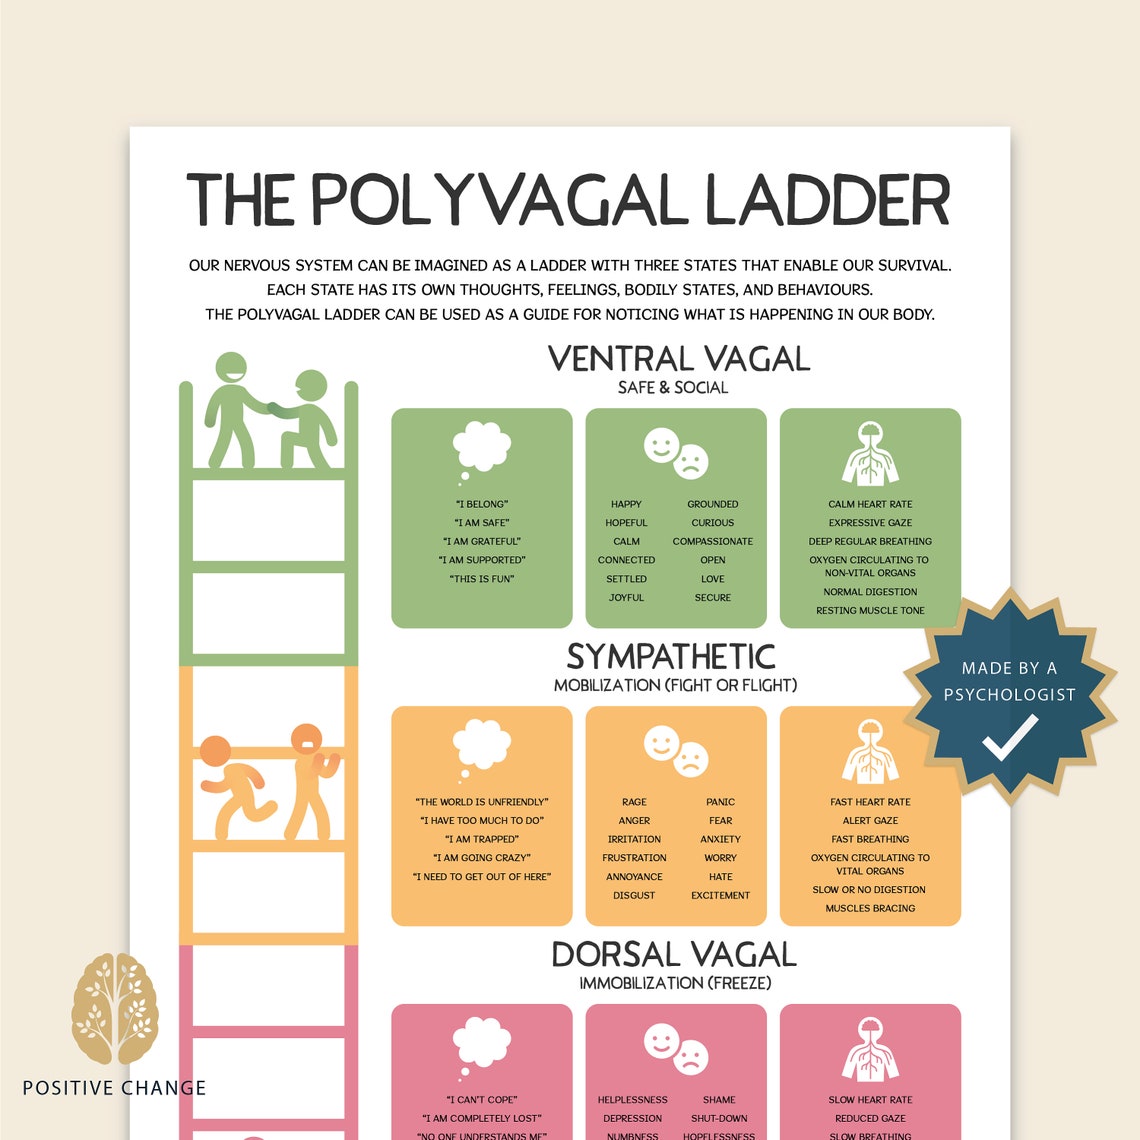
The basic method is simple but people mess it up by overthinking it. You sit down with a recent incident — a panic response, a shutdown episode, a rage outburst — and go back through it rung by rung. Start at the bottom. Dorsal vagal is characterized by collapse, dissociation, numbness, stomach issues, desire to disappear. If you check that box, the interventions are limited. You don't ask someone in dorsal shutdown to "breathe deeply" or "practice mindfulness." That won't land. The actual work is gentle orienting — soft sensory input, warm blankets, humming, slow rocking. These feel trivial. They're not. Middle rung is sympathetic. Heart racing, jaw tight, thoughts spinning, irritable, can't sit still. This is where most people end up. Standard breathwork, movement, cold water on the face, progressive muscle relaxation — these actually work at this level because the body is already mobilized and just needs an exit ramp.
Top rung is ventral vagal. Calm, connected, able to engage socially, sleeping well, appetite normal. Interventions here are maintenance — gratitude practice, social connection, creative expression. The goal isn't to reach this state urgently. The goal is to stay here longer so the lower rungs don't trigger as easily. The key detail everyone misses is timing. You fill the worksheet within 24 hours of the episode. After that, the nervous system story gets edited by your narrative brain and the markers become unreliable. I've seen people come back two weeks later and confidently check ventral vagal boxes for what was clearly a sympathetic spike. Memory doesn't preserve physiological states accurately.
Where This Tool Falls Apart
I need to be blunt about the limitations because most content out there treats this as a complete framework. It isn't. The polyvagal ladder assumes a relatively intact nervous system to begin with. It works decently for people with situational anxiety, stress management issues, or mild dysregulation. It is nearly useless for complex PTSD where the nervous system is chronically stuck in a survival state regardless of present-moment threats. People with significant trauma histories will often find themselves between rungs with no clean category. Another issue: the worksheet tends to produce false positives on the sympathetic rung. Almost any discomfort gets labeled sympathetic because people equate "not calm" with "fight or flight." But chronic fatigue, depression, and metabolic issues can mimic sympathetic arousal without actually being sympathetic activation. The sheet doesn't have a medical screening filter built in. I had a client for months working on "sympathetic regulation" when she actually had undiagnosed hypothyroidism. The worksheet couldn't catch that. She needed blood work, not box breathing. The dorsal vagal interventions also have a narrow window. Once someone is deeply in dorsal shutdown — the kind where they can't speak coherently or move purposefully — the worksheet's suggestions are too abstract to implement without a supportive person present. Humming and orienting require a baseline of agency that the state itself removes. In those cases, you need someone else in the room to guide the process, and the solo worksheet format breaks down entirely.
Get the Full Details

What Beginners Miss
Here's the thing nobody puts in the marketing copy: the ventral vagal state is not the same as being happy or productive. You can be socially engaged and internally devastated. The ventral markers are about neural safety signaling — visible facial muscles, regulated breathing, ability to tolerate ambiguous social input. A person can appear fine on the surface and be running on pure sympathetic fuel underneath. The worksheet catches this if you train yourself to look at the physiological indicators rather than the behavioral performance. The other counter-intuitive point is that moving up the ladder isn't always the goal. Sometimes the sympathetic state is the appropriate response — you're dealing with an actual threat. Forcing yourself into ventral vagal when you should be mobilizing can create a kind of spiritual bypassing where you're disconnecting from legitimate danger signals. The worksheet should track whether the state matches the context, not just whether it's the "best" state. I also found that tracking duration matters more than I expected. Someone who hits sympathetic for ten minutes and returns to ventral has a very different profile than someone who stays in sympathetic for eight hours. The Polyvagal Ladder Worksheet works better when you add a time estimate column. It changes the intervention strategy significantly. Short spikes get quick resets. Prolonged activation needs a different protocol — usually starting at a lower rung and working up gradually rather than trying to jump straight to ventral.
Getting the Worksheet
There isn't one universally standardized version. I've seen PDFs from coaching programs, therapy worksheets on clinical sites, and blank templates you can make yourself. The versions I recommend are the ones that include the three columns I mentioned — observation, intervention, follow-up — plus a date and duration field. Without the duration field, you lose the tracking data that makes this actually useful over time. A lot of free versions float around therapy resource sites. Search for "polyvagal ladder worksheet PDF" and you'll find several. Pick the one that leaves room for your own notes rather than the ones that are fully pre-filled with examples. The blank format forces you to do the actual work instead of reading someone else's interpretation. If you want something more structured, there are paid versions from trauma-informed coaching programs that include guided prompts and a tracking component across multiple sessions. Those are worth it if you're going to use this regularly. If it's a one-time lookup, the free versions are fine.
The bottom line is that this worksheet is a mapping tool, not a treatment. It helps you name what's happening in your nervous system in real time. That naming alone reduces the intensity of many episodes because it creates a small gap between stimulus and reaction. But it doesn't fix underlying dysregulation, and it doesn't replace professional support when the patterns are severe or persistent. Use it for what it is — a practical checklist — and don't expect it to do work it wasn't designed to do.