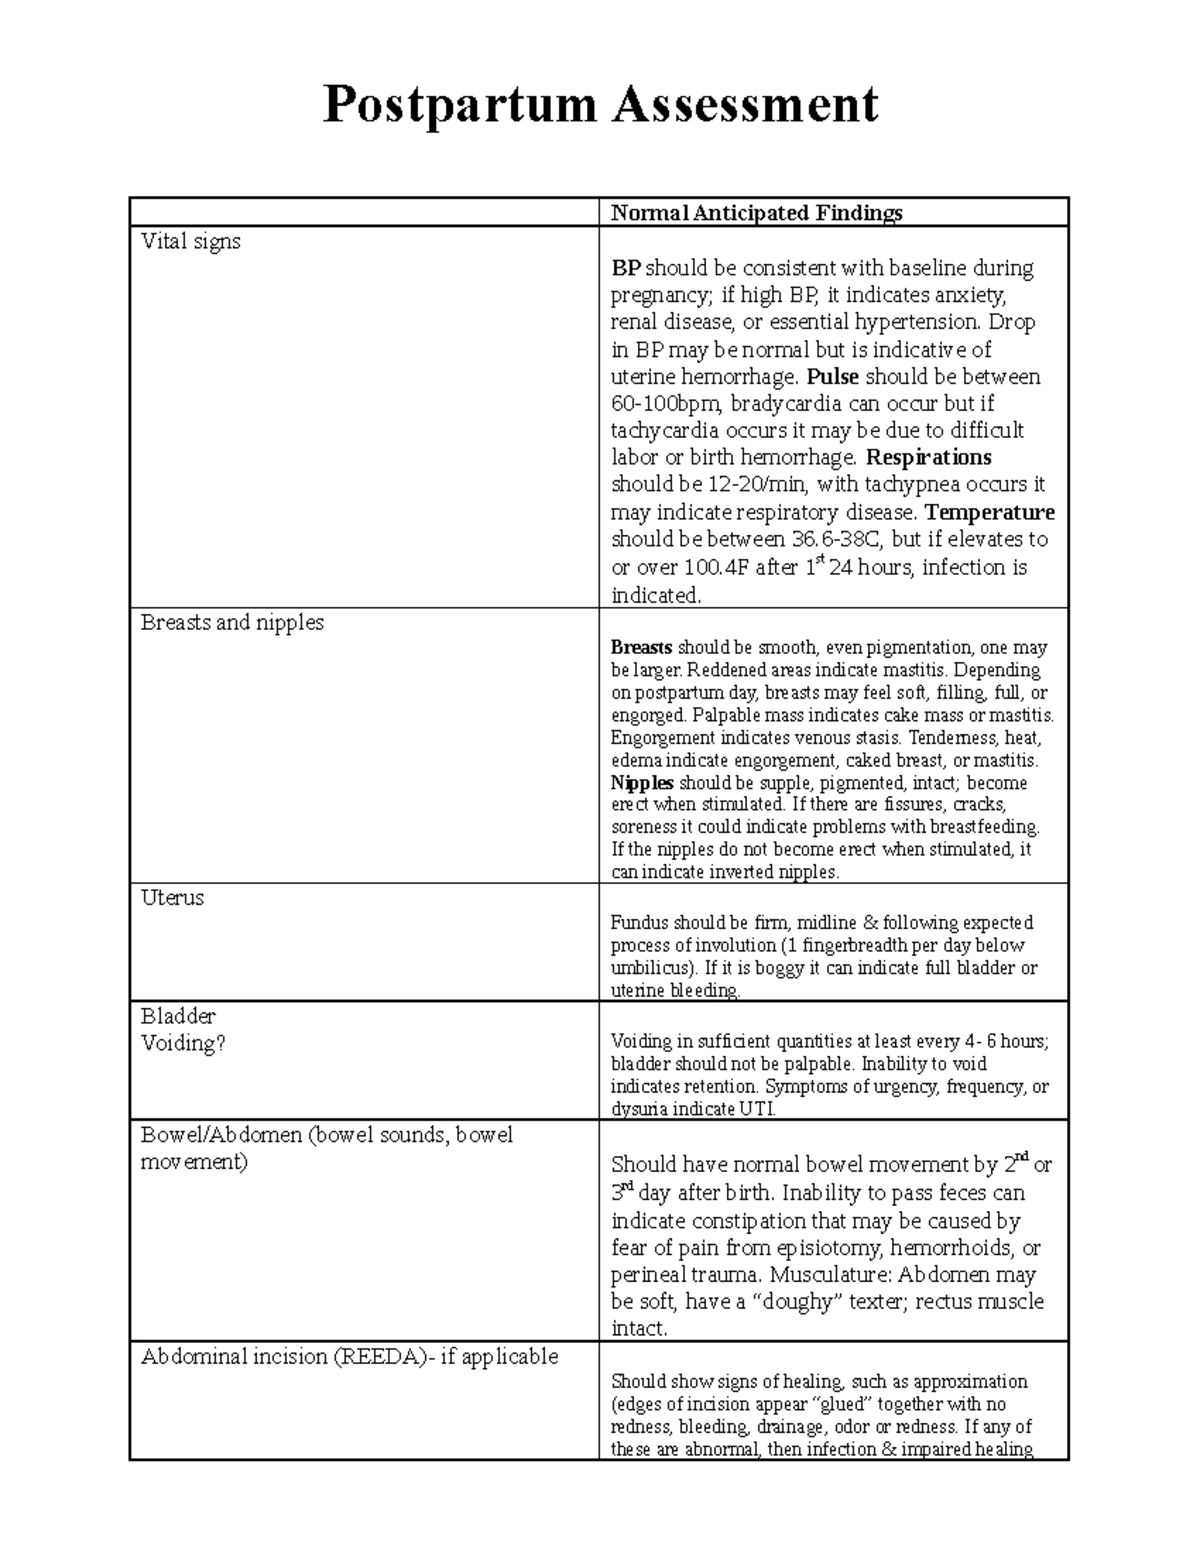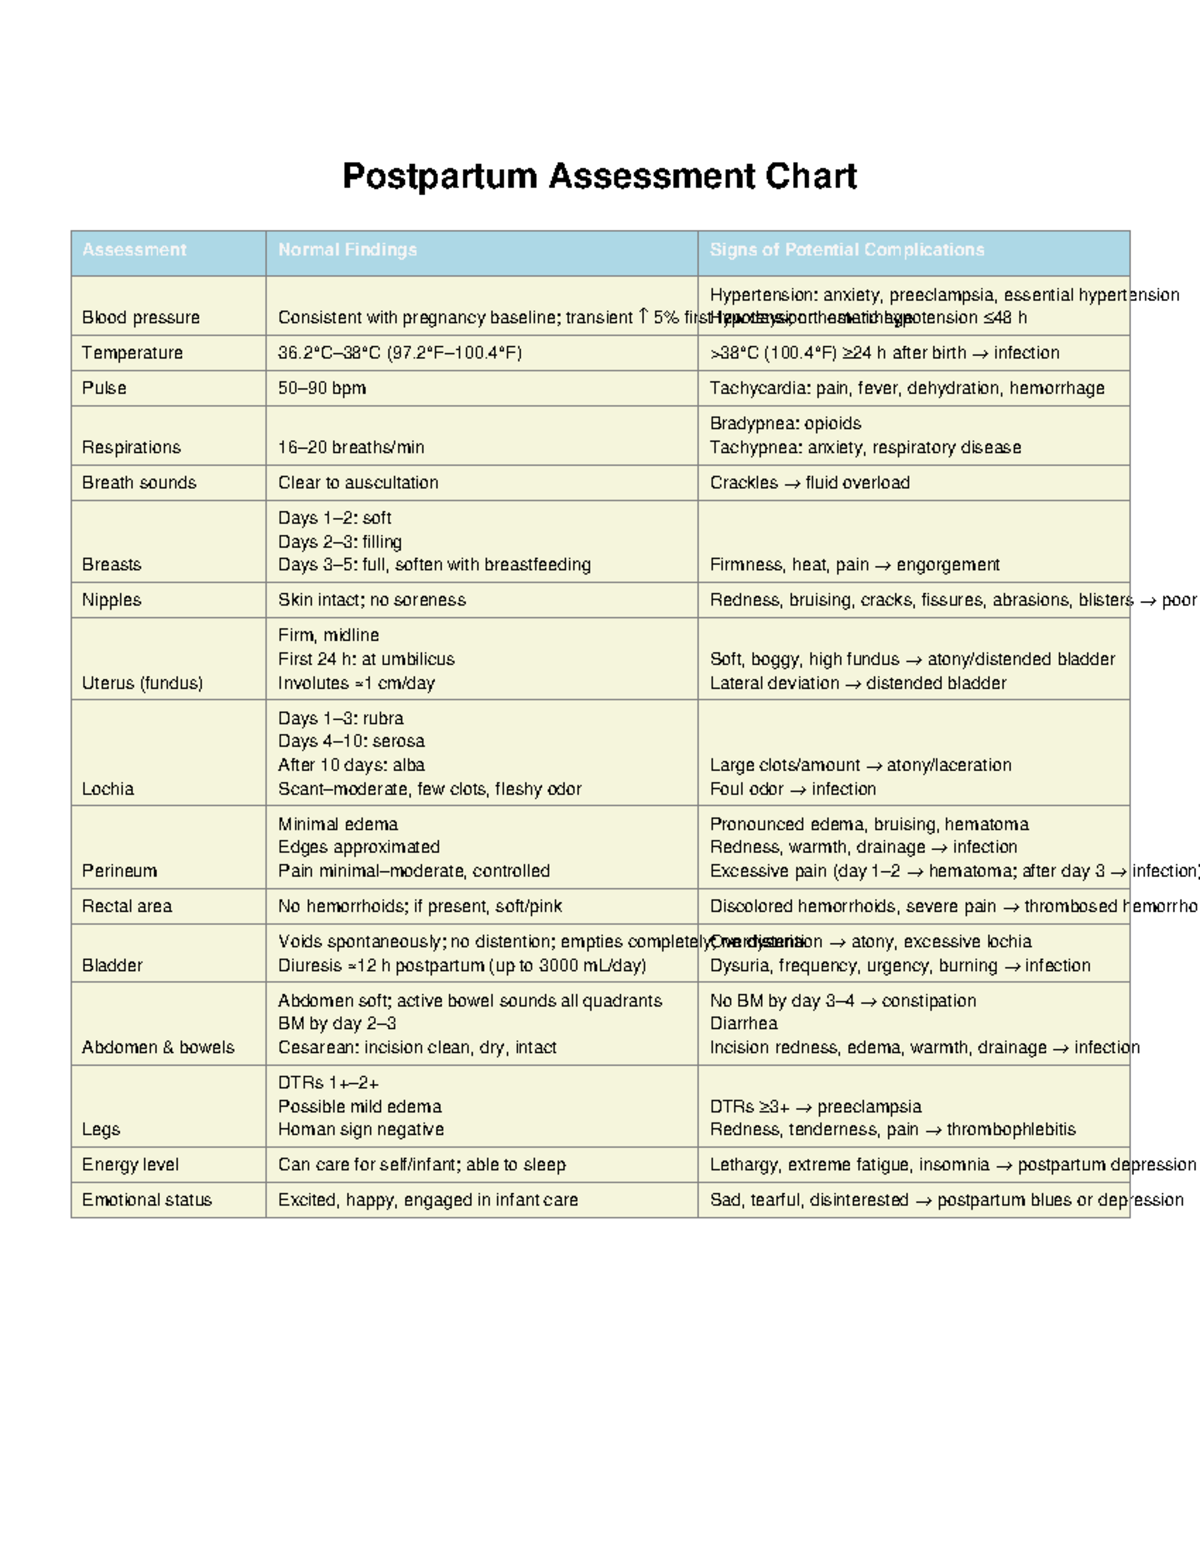
Postpartum Assessment Normal Findings
I spent years doing postpartum assessments on a labor and delivery floor before moving to clinic work. You'd be surprised how many people get this wrong, especially the fundal check. People assume the uterus should be tender because it's contracting, but tender isn't normal. Firm, yes. Tender, that means endometritis or retained tissue. You'd be amazed how often a nurse charts "firm and slightly tender" as if that's routine. It isn't. That's a patient you escalate. The fundamentals start with the fundus. Check it every fifteen minutes the first hour after delivery, then every fifteen minutes for an hour, then every thirty minutes for two hours, then every four hours and before each voiding and bowel movement. Position matters just as much as firmness. The fundus should be firm, midline, and at the level of the umbilicus immediately after placenta delivery. From there it descends roughly one fingerbreadth or one centimeter per day. By ten to fourteen days it's usually no longer palpable abdominally. If it's boggy, massage it until firm. If it stays boggy after massage and you've emptied the bladder, call the provider. A displaced fundus to the right or left usually means a full bladder pushing the uterus over. That's the easiest fix in the world once you figure it out. Lochia is where a lot of confusion lives. It follows three stages. Lochia rubra happens days one through three, bright red, heavier than a period but never soaking a pad in under an hour. Lochia serosa comes next, pink to brown, lighter flow, days three through ten or so. Lochia alba runs from about day ten through week six, yellowish-white or pale. Any foul odor is abnormal regardless of the stage. A fishy smell doesn't belong here. Neither does passing large clots after the first twenty-four hours. If a patient is soaking a pad in under an hour or passing clots larger than a plum after the first day, that needs attention immediately.
Vital signs deserve a moment on their own. Temperature can rise slightly in the first twenty-four hours from dehydration and exertion, but anything over 100.4 Fahrenheit is a line you don't cross without investigating. A temp of 100.4 or higher after the first day means chorio, UTI, endometritis, or a breast issue. Pulse usually sits lower than the pregnancy baseline, often in the sixties and seventies. That's normal. Blood pressure should track with the pre-eclampsia questions. If a patient had low-grade blood pressure issues during pregnancy, watch them closely postpartum since that fluid mobilization can unmask things. Breast assessment has its own set of expectations. In the first few days you're checking for engorgement, nipple integrity, and whether colostrum or milk is coming in. Nipples shouldn't be cracked or bleeding. If they are, the latch is wrong and that's a lactation consult situation, not something you ignore. Engorgement around days three to five is normal physiology. Full, firm breasts that are warm but not red and hot. True mastitis is different. Mastitis presents with a wedge-shaped red area, fever, and flu-like symptoms. Don't confuse the two. One needs supportive care and frequent feeding. The other needs antibiotics and probably a doctor's visit. Perineal assessment depends on what happened during delivery. If there was a second-degree laceration or an episiotomy, the area should be intact with minimal edema and no hematomas. Sutures should be in place with no dehiscence. Redness, warmth, purulent drainage, or opening of the wound edges are all abnormal. I had a patient once where the nurse documented "moderate edema, expectable" on the perineum but the patient hadn't actually had a tear. She'd had an unassisted vaginal delivery with no trauma. There was no reason for moderate edema. Turns out she had a superficial hematoma forming near the fourchette that wasn't visible at a quick glance. The swelling was posterior and left-sided. If you're doing a perineal check, look at it from the patient's feet up with good lighting. Don't just glance and move on.
Bladder function typically returns within six to eight hours after delivery for spontaneous voiders. Catheterized patients vary. You want to ensure they're emptying adequately. Retention leads to uterine displacement and increased bleeding risk. Bowel function is a different timeline. Most patients don't have a bowel movement until three to five days postpartum, sometimes longer if they're on opioid pain meds or iron supplements. That's normal. Constipation is expected. Stool softeners are standard practice for a reason. Lower extremity assessment is the part people skip. Look for asymmetry, warmth, tenderness along the calf, and Homan's sign is historically taught but unreliable and no longer recommended as a standalone test. You're looking for signs of deep vein thrombosis. Postpartum patients are hypercoagulable. A patient complaining of calf pain on one side who also has recent C-section history and limited mobility needs a Doppler before you write it off as soreness from labor positioning. Emotional screening is part of the physical assessment too. The baby blues affect up to eighty percent of new mothers, typically peaking around day three to day five and resolving within two weeks. Sadness, mood swings, tearfulness without clear triggers. That's the blues. Postpartum depression is different. It persists beyond two weeks, interferes with functioning, and includes symptoms like anhedonia, worthlessness, or thoughts of harm. Screening tools like the Edinburgh Postnatal Depression Scale are valid and take about two minutes to administer properly. Don't rush it.
Get the Full Details

One thing nobody warns you about: the abdomen itself changes in ways people don't mention. Skin may show striae that are purple or red initially and fade to silver over months. Diastasis recti is common. You can check it by having the patient lift her head while supine and feeling for a gap along the midline. A gap up to two fingerbreadths is normal immediately postpartum and improves over time. A gap wider than that or one that domes significantly needs follow-up. Also, the umbilicus can look different. Some patients notice it protruding slightly after delivery. Usually resolves as the abdominal wall tones back. There's a practical trick for fundal checks that saves time and reduces patient discomfort. Ask the patient to void first. A full bladder shifts the uterus and makes every subsequent check less accurate. Then have the patient lie supine with knees slightly flexed. That relaxes the abdominal wall enough to palpate properly without gagging the patient. If you have to press hard to find the fundus, the abdomen is too rigid or the uterus is genuinely small from atony. Document both observations. The biggest pitfall I see is charting normal findings as if they're noteworthy without context. "Fundus firm, midline" is a complete sentence that tells someone nothing about when you checked it or what the lochia looked like. Your documentation should capture the timeline. When did you last assess? What changed since the prior check? Normal findings matter less than trends. A fundus that was midline and firm at 0600 and is now deviated to the right at 1000 is a clinical event even if both assessments individually fall within normal range.
I also want to flag something about pain management documentation. Many postpartum patients receive epidural analgesia or patient-controlled narcotics. This blunts normal assessments. A patient on an epidural may not report bladder distension until it's severe. They may not feel perineal pain from a hematoma forming. If someone has regional anesthesia, you're the only one who can catch these issues. Check more frequently. Don't rely on patient reporting alone. C-section incisions follow their own rules. The incision should be approximated with minimal erythema around the edges. Serous drainage is normal for the first day or two. Purulent drainage, widening of the incision edges, or fever above 100.4 after the first day are red flags. Subcutaneous lipolysis is another thing people mistake for infection. It's a sterile inflammatory response to suture material in the fat layer that produces a clear to slightly bloody serous discharge around postoperative days five through seven. It looks alarming. It's not infectious. But you can't tell the difference without evaluating the patient properly. If you're studying for boards or preparing for your first postpartum rotation, the mnemonic BRASS is still commonly taught: Breasts, Return of bladder and bowel function, Adaptation to blood loss and lochia, Soul adjustment, and Stoma or surgical wound. It's a decent checklist but it oversimplifies things. The emotional assessment piece especially gets compressed into one letter when it deserves as much clinical attention as the physical findings. Depression screening isn't optional. It's standard of care and you should be competent in administering and interpreting the tool regardless of what your program emphasized.
For reference materials, the ACOG practice bulletins on postpartum care and the WHO recommendations on intrapartum and postpartum care are the primary sources. The postpartum hemorrhage guidelines specifically address the assessment cascade that precedes intervention. Understanding what normal looks like is the only way you'll recognize the first deviation. And the first deviation is where everything changes.