Powerchart Oncology: What It Actually Is and Why It Keeps Existing
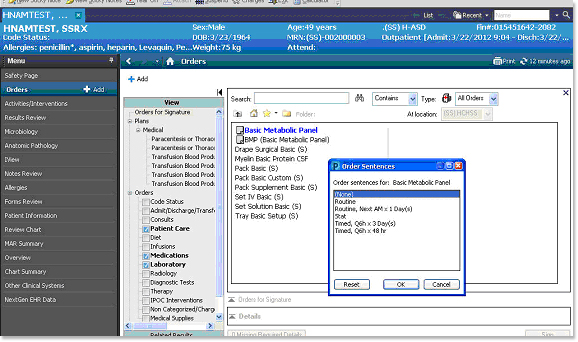
Powerchart Oncology is Cerner's order-entry module for cancer treatment. It lives inside the Cerner electronic health record platform and handles chemo orders, infusion scheduling, dose calculations, and pharmacy verification workflows. If your hospital runs Cerner, you're using it whether you like it or not. The user interface hasn't changed dramatically in years, and a lot of people who trained on it leave before they ever get good at it. The official documentation lives on Cerner's support portal, which requires a valid client login. I found the most useful sections were the ones nobody reads first — the error code tables and the drug formulary mapping notes. When the system throws a rejection on a carboplatin order, for example, the Powerchart Oncology User Guide explains why, but only if you know which rejection category to look under. Most of my team learned this the hard way by copying error messages into a shared doc and cross-referencing them after each shift. To actually open the module, you need role-based access provisioned by your local informatics team. Just having an order entry role isn't always enough. Chemo prescribers typically require a separate oncology order set credential that gets configured differently depending on whether your site uses Millennium or the newer HealtheLife environment. Ask for the ONCO-ORDER access string during your credentialing process instead of waiting until you're standing at a workstation with an expired order session.
How the Order Workflow Actually Feels
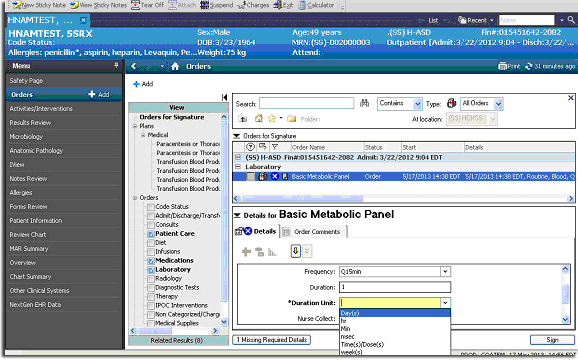
A typical chemo order starts in the Powerchart order entry screen, goes through a pharmacy verification queue, then lands in the infusion nursing workspace. That's the ideal path. In practice, there are three points where the order stalls: incomplete weight or BSA fields, missing premedication orders bundled with the chemo, and lab value holds that don't auto-populate correctly from the lab system. BSA calculation is the first thing that goes wrong. The system uses either Mosteller or DuBois depending on your institution's configuration. I've seen two nurses on the same unit calculate BSA differently because one was looking at a saved patient note from a prior admission and the other was pulling it fresh. Neither was wrong within their own frame. Set a standard at your site and put it in the order set notes so the next person doesn't have to guess. The pharmacy verification queue is where most delays happen. Pharmacists see a list of orders waiting for verification, and they prioritize by acuity and by who pushed the order button first. If you're ordering a time-sensitive regimen like FOLFIRINOX, put the urgency in the order comments field, not in a separate message flag. The comments field is what shows up on their verification screen. The message flag requires an extra click and half the pharmacy staff never check it during peak hours.
A Specific Problem I Ran Into
Last year I was helping a new oncology fellow who ordered oxaliplatin with a dose based on a BMI over 40. The system flagged the order for a renal function review and sent it to pharmacy, but the pharmacy kept rejecting it with a cryptic comment about "dose validation threshold exceeded." Nobody could figure out what threshold the system was checking against. Turns out the institution had a hard cap configured at 120% of the standard dosing weight in the order set rules, and the fellow's order was hitting it because the system was auto-capping at actual body weight instead of ideal body weight for the dose calculation. The workaround was simple once we found it: the fellow switched the dosing basis to IBW in the order dialog, added a comment noting the clinical justification for using actual body weight, and the pharmacy accepted it on second pass. The real fix required changing the order set configuration, which took the pharmacists about three weeks because they had to get medical director sign-off on adjusting the cap rule. The Powerchart Oncology User Guide covers the standard workflows adequately, but it doesn't address what happens when your institution uses combination order sets. A combination set bundles multiple drugs, premeds, hydration fluids, and lab pulls into one clickable order. The problem is that if one component needs an adjustment — say you're holding the hydration bag because the patient has a potassium of 3.1 — you can't edit just that part without breaking the whole set and recreating it manually. I learned this during a night shift when I spent twelve minutes trying to toggle off a single element inside a combo set before I realized the system treats the bundle as atomic. The solution is to unbundle the order set at your institution level and keep individual components separately orderable. It's a configuration decision, not a workflow one, so it requires an informatics request, but it saves time once it's done. Another thing that trips people up is the lab hold feature. When you order chemo that requires a ANC or platelet count above a certain threshold, the system checks the most recent lab result at the time of order entry. But if that result is older than your institution's time window — typically forty-eight hours for inpatients, twenty-four for outpatients — the order won't auto-approve. The Powerchart Oncology User Guide mentions this, but it doesn't emphasize that the clock resets only when a new lab result posts. Ordering a repeat CBC just to clear the hold is standard practice, and some sites have a standing order protocol that lets nurses draw the lab without a physician order in these cases. Check your local policy before you assume you need to call the attending back every time.
Get the Full Details
Downsides and When It Breaks
Powerchart Oncology works fine for straightforward regimens. FOLFOX, R-CHOP, TCH, ATRT — these are well-mapped to order sets and the system handles them cleanly. Where it struggles is with experimental protocols, off-label dosing, and pediatric crossover cases where the adult order sets don't apply. There's no workaround inside the system for truly novel regimens. You build a custom order, document the protocol number in the comments, and hope the pharmacy reviewer is familiar with the study. I've seen orders sit in verification for hours because the pharmacist couldn't match the regimen to a formulary entry. The drug formulary sync is another bottleneck. When a new chemo drug gets FDA approval and your hospital formulary committee adds it, there's usually a lag between the formulary update and the Powerchart order set availability. During that window, clinicians order the drug as a manual entry and rely on pharmacy to route it correctly. It works, but it's slower and more error-prone. If your site is adopting a new agent, push for the order set to be built before the go-live date rather than after. There's also the reporting side. Adherence tracking, dose intensity calculations, and outcome dashboards all pull from Powerchart Oncology data, but the reports are only as good as the data entered. Missed fields, inconsistent drug naming conventions, and variation in how different providers document cycles and lines all degrade the output. I've seen dose intensity reports that were off by ten to fifteen percent simply because two attendings used different names for the same drug in the system.
Practical Shortcuts That Actually Help
Save your most-used order sets as favorites, not just within the module but as a personal shortlist. The system lets you pin up to ten frequently used combinations, and having your standard regimens there cuts order entry time from about two minutes per order to under thirty seconds. It sounds minor but over a busy clinic day it adds up. Use the copy function sparingly. Copying a prior cycle's order is convenient but it copies everything including lab holds, premed schedules, and infusion rates from the previous cycle. If the patient's renal function or weight changed, you're importing outdated constraints. Always audit the copied order line by line before you send it. I stopped relying on the one-click copy after I nearly sent a cycle three dose that was still pulled from cycle one's reduced amount due to a prior neutropenic event. Bookmark the local pharmacy phone number in your browser. Not the central switchboard. The direct line to the oncology pharmacy technicians who handle verification intake. When an order is stuck and the status screen isn't updating, a quick call to them is faster than clicking through the message board or opening a formal consult request. They can usually tell you within thirty seconds whether it's waiting on them, waiting on a physician response, or blocked by a lab hold they can see but you can't.
The Powerchart Oncology User Guide is a reference, not a training program. The real learning happens from doing the orders, making the mistakes, and figuring out where the system fights you versus where it's just working as designed. Once you understand which battles are worth picking, it becomes manageable. Most of the friction comes from configuration choices made years ago that nobody questions anymore. Asking why something works the way it does usually leads to a simpler answer or a workaround someone already figured out.