
Why We Even Bother With Pragmatic Goals
Most people walking into a speech clinic for the first time think language is just vocabulary and grammar. They show up with a checklist of target sounds and some sentence frames they need to drill. What they don't realize until around session six or seven is that their kid can produce a perfectly structured compound sentence but will still stand three feet away from a peer and narrate the other child's movements like a sports announcer. That's the pragmatic gap, and it's the part that eats up most of our clinical hours. I spent the first decade of my career treating articulation and phonology exclusively. When I finally moved into pragmatic language work, the shift was not subtle. You go from measurable, observable targets to something that feels squishy and subjective almost immediately. A child either uses a reciprocal greeting or they don't. There is no middle ground on paper. In practice, you spend weeks figuring out what "doesn't" actually looks like in their head.
The Framework Behind Pragmatic Language Goals Speech Therapy
The approach most of us use isn't a single program. It's a collection of evidence-based frameworks that overlap heavily. The most common starting point is the Social communication, interaction, communication, and regulation (SCIP) framework or the work by Dr. Lucy Billingsley and colleagues on social-pragmatic intervention. Another widely used model comes from Dr. Michelle Garcia Winner's social thinking methodology, which gives you concrete vocabulary for things like "hidden social rules" and "expected versus unexpected behaviors." There's also the Theory of Mind curriculum by Baron-Cohen and colleagues that targets perspective-taking directly. What ties these together is the assumption that pragmatic language is teachable, not just something a child absorbs incidentally. That assumption has held up reasonably well across decades of research, though the effect sizes vary depending on age, baseline ability, and how consistently the skills are practiced outside the therapy room. The numbers typically show moderate gains in functional communication over twelve to twenty weeks of focused work, which is better than nothing and worse than most parents expect going in. Here is what that looks like on a Tuesday morning with a nine-year-old who has autism spectrum disorder and a baseline expressive language score around the fifth percentile. You are not targeting sounds. You are targeting the sequence of behaviors that happens before a child successfully joins an ongoing play group. The target might be: observe first, then make a relevant comment, then wait for a response before continuing. Three steps. Most kids with pragmatic delays attempt step one and then steam ahead into step three without any bridge between the two.
The intervention portion usually involves explicit instruction in small groups of three to five children, combined with video modeling, role-play, and real-time coaching during unstructured social periods. The explicit instruction teaches the child what to look for. The role-play builds rehearsal. The real-time coaching handles the messy transition from practiced to spontaneous. Each piece does different work, and skipping any of them tends to collapse the whole thing.
Get the Full Details
What Actually Happens in a Session
A typical group session runs forty-five minutes and follows a loose arc. The first ten minutes are always warmer and more structured. You might do a brief social story review or a video clip analysis where the kids watch a short scene and identify what went right or wrong in the interaction. This is not filler. The warm-up primes the social-cognitive system before you ask them to perform under more ambiguous conditions later. The middle chunk is where the heavy lifting happens. This is usually role-play or structured social games with embedded teaching points. The game itself is secondary. The teaching point is primary. If you are running a board game session, the goal is not whether they win or lose. The goal is whether they can accept a loss without leaving the table, whether they can offer a simple congratulatory statement to the winner, and whether they can ask for a turn without interrupting someone mid-sentence. Those are the actual targets. The board game is just the container. The last ten to fifteen minutes are typically a cooler-down period where you review what happened, give specific feedback, and sometimes assign a home practice task. The feedback portion is where a lot of groups fumble. Generic praise like "good job playing nicely" does not transfer. Specific, behavior-anchored feedback does. You tell the child exactly what they did that worked and what you want to see next time. "You waited for Sam to finish his sentence before you started talking. Next time, try waiting for him to look at you after he finishes, not just after he stops talking." That level of detail matters more than clinicians usually give it credit for.
Individual sessions follow a similar logic but with more direct adult scaffolding. You might work on a single pragmatic skill like initiations, responses, topic maintenance, or repair strategies. Topic maintenance is the one that quietly destroys most kids' social lives without anyone noticing. A child can initiate and respond perfectly and still fail at keeping a conversation going past two turns. They either pivot too sharply to a new topic or they loop back to the same narrow interest regardless of the other person's cues. Fixing that requires explicit teaching of question-asking as a conversation-maintenance tool, which most people assume is automatic and then get surprised when it is not.
A Specific Problem I Ran Into
About four years ago I had a client, a twelve-year-old girl with a verbal diagnosis of autism and strong expressive language for her age. She could produce complex sentences and had a large vocabulary. She also could not maintain a conversation past two turns without turning it into a lecture about a single niche interest. Standard conversation mapping exercises failed with her. She would parrot back the steps perfectly when role-playing with me but revert the moment she was in a less structured setting. The breakthrough came when I stopped treating it as a pragmatic language deficit and started treating it as a self-monitoring deficit. She knew the steps intellectually. She just could not detect when she had gone off track in real time. I started using a very low-tech workaround: a colored wristband she could check against a small card in her pocket. Green meant keep going, yellow meant check in, red meant pause and ask the other person a question. The wristband was not the intervention. It was a visual prompt for self-monitoring. The intervention was the repeated practice of pausing, scanning for cues, and asking a reciprocal question. It worked slowly. She went from zero self-corrections during a five-minute interaction to about one every three sessions over eight weeks. That sounds small. It was the difference between her getting invited to stay after school sometimes and never. The wristband strategy faded out after about six months as the self-monitoring became more automatic. She still needs reminders in highly stressful or unstructured social environments, which is normal for this population and something parents should plan for.

Counter-Intuitive Things No One Warns You About
The first thing that catches people off guard is that pragmatic skills often regress under stress or cognitive load. A child who can handle a structured group activity at school might completely lose those same skills at home on a tiring afternoon. This is not defiance. It is a well-documented phenomenon. The prefrontal resources required for pragmatic monitoring are finite, and they deplete faster in autistic and ADHD populations than in neurotypical peers. Any intervention plan that only measures progress in the clinic is measuring the wrong thing. You need generalization data from natural settings, and you need to track whether progress holds when the child is tired, hungry, or overwhelmed. The second thing is that explicit instruction in pragmatics can sometimes make performance worse before it gets better. When you teach a child to consciously monitor social cues, they become more self-aware and more anxious in social situations. I have seen kids who were previously comfortable approaching peers suddenly freeze because they are now auditing every interaction against a mental checklist. The solution is to pair explicit instruction with graded exposure and anxiety management, not to abandon the explicit work. The explicit piece is still necessary. It just needs to be introduced slowly and paired with desensitization to the social environment itself. A third point that beginners miss is the difference between social communication and social cognition. Social communication is the observable behavior: initiating, responding, maintaining, repairing. Social cognition is the underlying mental capacity: understanding that others have thoughts and perspectives different from your own, inferring intent, recognizing emotional states from subtle cues. You can drill social communication skills all day and hit a ceiling if the social cognition piece is not developing alongside it. The two feed each other, and interventions that ignore the cognitive foundation tend to produce fragile generalization.
When This Approach Completely Falls Apart
Pragmatic language goals speech therapy does not work for every client, and it is honest to say that upfront. Children with significant intellectual disability who have not yet reached a developmental level of three to four years in adaptive communication often do not benefit from standard group-based pragmatic intervention. The abstract reasoning required to understand perspective-taking and hidden social rules is simply not available to them at that stage. For those kids, the work is more concrete: turn-taking with objects, basic requesting, joint attention through play. Those are foundational skills that come before pragmatics in the developmental sequence. Another scenario where this approach struggles is when the child has co-occurring anxiety disorders that are not being addressed simultaneously. Social anxiety can completely block the transfer of taught pragmatic skills because the child is too preoccupied with threat detection to engage in the cognitive work of interpreting social cues. In those cases, you need to either integrate anxiety treatment into the plan or refer out for concurrent therapeutic support. Pushing pragmatic goals harder when anxiety is the primary blocker usually just increases avoidance behavior. A third failure mode is when the family environment does not support generalization at all. I have seen kids make solid progress in clinic and then lose everything within three months because the home environment actively discouraged the new behaviors. A parent who sees a child using a taught strategy to enter a conversation and then corrects the child for being "too pushy" or "showing off" is effectively undermining the intervention. This is not about blaming parents. It is about recognizing that pragmatic skills live in the real world, and the real world has its own social rules that may conflict with what you taught in the room.
How to Set Goals That Actually Stick
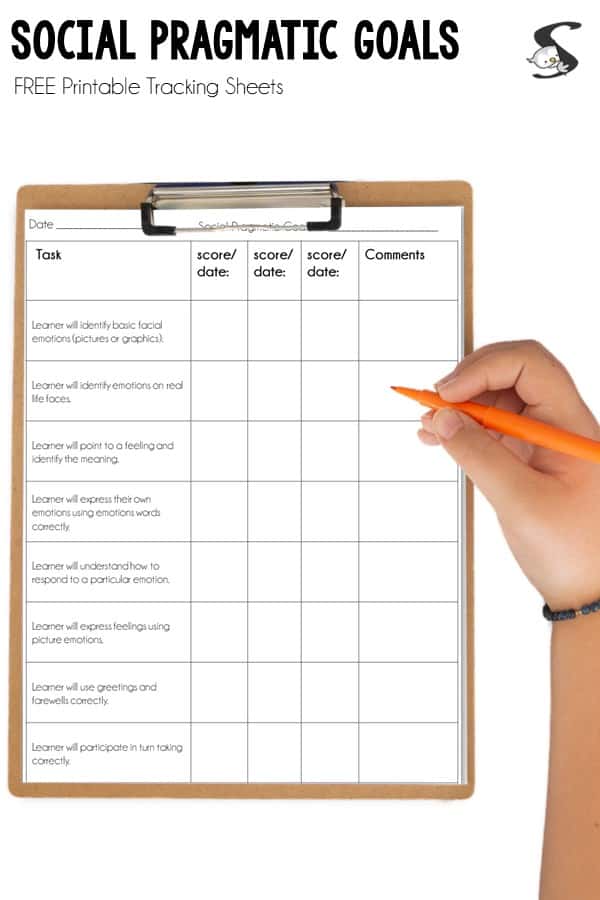
The mistake most people make when writing pragmatic goals is framing them as broad behavioral expectations. "The child will initiate social interactions with peers" is not a useful clinical goal. It tells you nothing about frequency, context, complexity, or conditions. A functional goal looks more like this: "Given a structured small-group activity with two familiar peers, the child will initiate an interaction with a relevant comment or question in 4 out of 5 opportunities across 3 consecutive sessions." That goal is measurable, contextualized, and time-bound. Another common error is writing goals that target only one direction of the interaction. Pragmatics is reciprocal. If you only train initiation without training response, you get children who can start conversations but cannot sustain them. If you only train verbal repair without training nonverbal repair, you miss a huge chunk of how people actually fix broken interactions. The best pragmatic goals address the full cycle: initiation, maintenance, repair, and termination. Termination is the one most often omitted. Knowing how to exit a conversation politely is just as socially important as knowing how to start one, and kids rarely learn this implicitly. Progress monitoring should happen at two levels. The first is session-level tracking of whether the child meets the target under the specified conditions. The second is monthly or bi-monthly generalization checks in natural environments. The generalization check can be as simple as a brief teacher or parent report, but it needs to be systematic. A child who hits the target in the clinic but never uses the skill anywhere else is not making functional progress, regardless of what the session data shows.

Materials and Resources
There is no single comprehensive curriculum for pragmatic language intervention that covers every population and every skill level. Most clinicians assemble materials from a few core sources. Social Thinking Publishing produces a range of materials that are widely used in school and clinical settings, though they are best suited for children with at least emerging reading and abstract reasoning skills. The SCIP Curriculum by the STAR Institute is another well-structured option that integrates sensory, communication, and social components, which matters because pragmatics does not exist in a vacuum for many of the kids who need it most. For lower-cost or free alternatives, there are published lesson plans and activities through ASHA's practice portal and through university-affiliated clinics. Video modeling materials can be created in-house with minimal equipment. A smartphone and a basic video editing app are sufficient to produce short modeled scenarios tailored to the specific skills you are targeting. This is one area where custom-made materials often outperform commercial programs because they can be matched exactly to the child's interests and social context. If you are looking for downloadable goal banks or template documents, ASHA's Practice Portal and the Georgia Institute of Technology's Center for Excellence for Autism Research both host freely available resources. Many state education departments also publish example IEP goals for social communication that you can adapt rather than build from scratch.
What the Research Actually Says
The evidence base for pragmatic language intervention is decent but not overwhelming. Meta-analyses generally show moderate effect sizes for group-based social-pragmatic interventions, with larger effects for children who have higher baseline language and cognitive abilities. The research is stronger for school-age children than for preschoolers, and stronger for autism spectrum populations than for children with isolated pragmatic language disorder, which is a diagnostic category that remains poorly defined in the literature. What the research does not show well is long-term maintenance. Most studies track outcomes for three to six months post-intervention, and some show meaningful decay after that point. This is why the generalization and maintenance planning I mentioned earlier is not optional. It is the part of the intervention that determines whether the gains last beyond the semester they were taught. There is also a growing body of work on peer-mediated intervention, where neurotypical peers are trained to model and reinforce pragmatic skills during natural interactions. Some of this research shows effects that rival or exceed clinician-directed intervention, particularly for maintenance and generalization. The trade-off is that peer-mediated approaches require careful structuring and ongoing supervision to prevent the reinforcement of inappropriate social behaviors or the creation of dependency on peer prompts. They are not a replacement for direct therapy but they are a valuable supplement.
Practical Takeaways
The main takeaway is that pragmatic language intervention is genuinely hard work and it requires patience that most clinicians and parents do not naturally have for this domain. It is easy to fall into the trap of measuring progress by how well a child performs in a controlled setting and calling it a day. That measurement is necessary but insufficient. The real test is whether the child uses the skill when no one is watching and when the social situation is messy and unpredictable. Another practical point is that you need to involve the people who are actually present in the child's daily social life. Teachers, paraprofessionals, parents, coaches, camp counselors. Anyone who spends regular unsupervised time with the child is part of the intervention ecosystem. If they are not reinforcing or at least not inadvertently undermining the skills you are teaching, the intervention will fail regardless of how well it is designed. The final point is that pragmatic language development does not stop when formal intervention ends. The skills being targeted here are lifelong. A twelve-year-old who learns to read conversational cues and repair breakdowns will still need to refine those skills through high school, college, and into the workplace. The intervention plant is not a destination. It is a foundation for a set of competencies that keep evolving.


