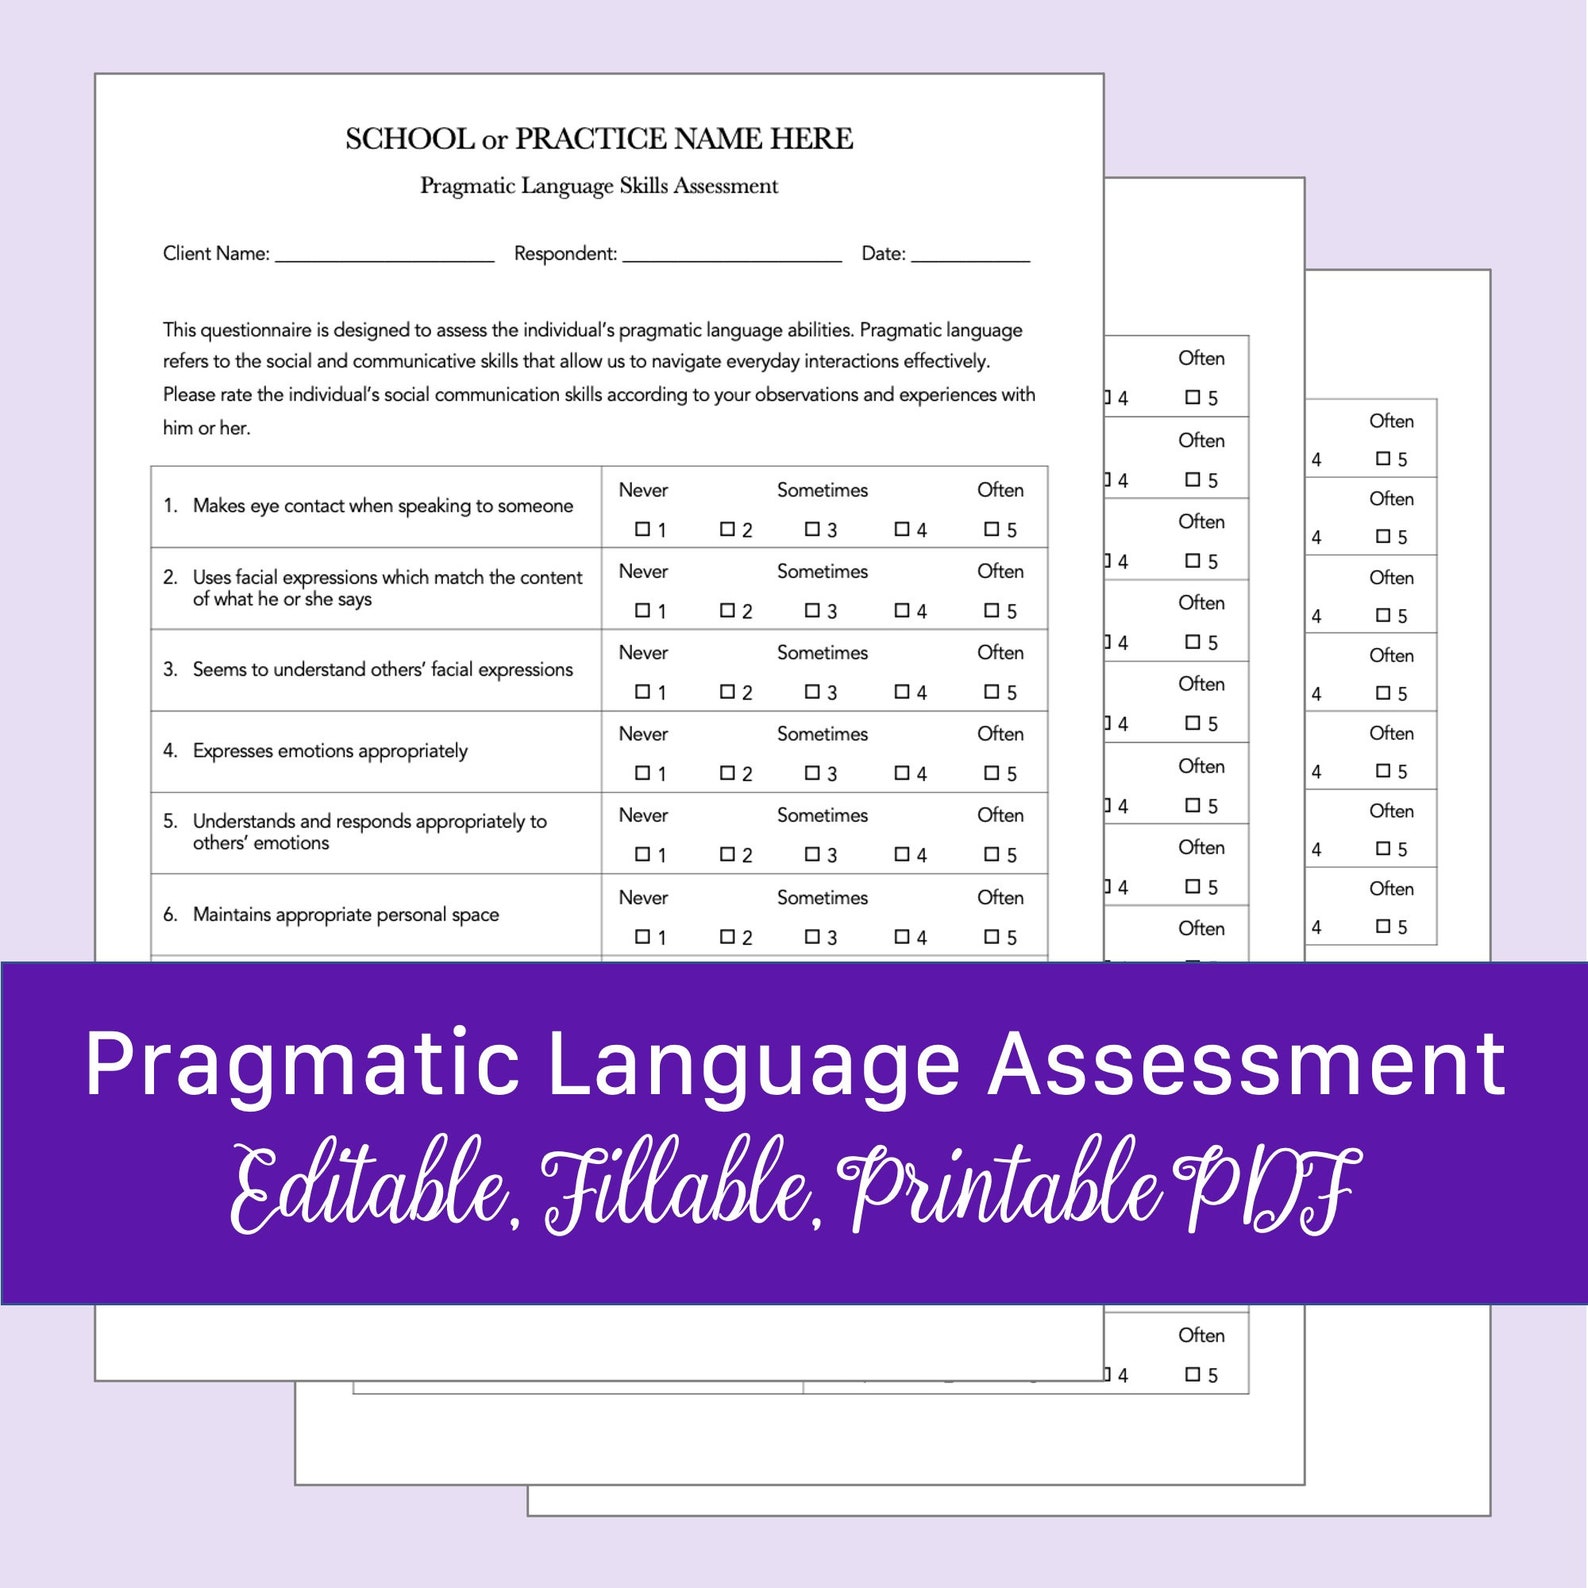
Pragmatics Assessment Speech Therapy
Most clinicians do a poor job assessing pragmatics because they're testing social skills instead of communication skills. There is a difference and it changes how you design the whole intervention plan. When I first started doing this work, I was handed a checklist from a textbook and told to tick boxes about eye contact and turn-taking. That approach produces data that looks tidy but tells you nothing about what actually happens when a child tries to get something done in a real conversation. Standardized instruments like the CECAF or the PLS-5 pragmatic subscales give you norm-referenced scores. They are useful for establishing eligibility and tracking broad progress. They miss the micro-level breakdowns that actually drive therapy decisions. A child can score in the average range on a structured parent report and still fail completely when asked to maintain a topic during peer play. The gap between structured test conditions and unstructured social demands is where the real deficit lives. I learned this the hard way with a nine-year-old who had a history of social communication disorder. His SSI-4 scores were borderline, his parents said he was fine at home, and his classroom teacher reported no concerns. I watched him try to join a group of kids at recess. He asked an irrelevant question about the weather, ignored three verbal redirects, and then walked away when the conversation moved forward without him. The standardized tools had told me he was close to typical. Direct observation told me he could not track conversational flow at all. That mismatch is the reason I stopped relying exclusively on questionnaire-based data.
Building a Practical Assessment Battery
You need three data sources working together. Caregiver and teacher rating scales give you the baseline of what happens across settings and over time. Narrative samples and language sample analysis reveal structural gaps in discourse organization and referential clarity. Structured interaction tasks show how a child handles specific pragmatic demands like repair, clarification, and topic management under mild pressure. For the rating scale component, the Social Communication Intervention Questionnaire and the Children's Communication Checklist version 2 are the standard options. I use both because they emphasize different things. The SSCIQ focuses on specific pragmatic skills and gives you granular item-level data. The CCC-2 gives you a broader profile and flags potential comorbidities like pragmatic language impairment alongside other language domains. Run both, compare the profiles, and note where they disagree. Disagreement between informants is itself diagnostic data. For language sampling, I collect between three and five minutes of semi-structured play-based interaction for younger children and narrative retell or conversational interview for school-age kids. The goal is not to count total words or mean length of utterance. I am tracking pragmatic markers: how often the child initiates, how they handle non-responses, whether they check for listener understanding, how they manage overlaps and interruptions. You can code this manually in about 20 to 30 minutes per sample if you focus on the relevant categories rather than trying to code everything.
Structured tasks fill the gaps. I use minimally supportive interaction probes like the Referential Communication Task, the Two-Option and Three-Option Choice Tasks, and short constraint-based games where one partner has information the other needs. These tasks create controlled pragmatic demands without turning the session into a pretend social skills class. A child who can handle reference and information exchange in a low-stakes game is showing functional pragmatics. A child who collapses under the same demand is showing where the breakdown happens.
Get the Full Details

What Actually Matters in the Data
The most useful metric I track is repair initiation rate. It is a single number that predicts intervention responsiveness better than almost anything else on a standard battery. If a child rarely initiates repair when communication breaks down, they are either not noticing the breakdown or they lack the motor plan to request clarification. Both possibilities require different treatment approaches. A child who initiates repair frequently but does so inappropriately has a different profile entirely. They perceive the breakdown but lack the linguistic or social tools to fix it efficiently. Another metric that gets ignored is listener-directed modification. This is the frequency with which a speaker adjusts their output after receiving negative feedback from a listener. It sounds simple. Most children with pragmatic disorders show striking deficits here. They repeat the same unclear message three or four times with increasing volume or frustration instead of reformulating. Tracking this metric over a few samples gives you a clear picture of flexibility versus rigidity in real-time interaction.
A Specific Edge Case and How I Handled It
I had a twelve-year-old who scored in the average range on every standardized pragmatics measure but was failing socially at school. His teachers reported chronic misunderstandings and peer conflicts. His parents said he had one friend and spent most recess alone. Standardized tools said he was fine. Something was clearly wrong. I stopped using them and switched to video-recorded naturalistic observation over three separate sessions across two weeks. The problem was not in his expressive language or his ability to follow simple conversational rules. It was prosodic timing. He consistently overlapped speakers by approximately 200 milliseconds, which is too early to be interpreted as eager participation and too late to be interpreted as a greeting. Listeners perceived him as interrupting. He perceived himself as being ignored. Neither side was wrong. They were just misaligned on conversational rhythm. The workaround was straightforward but non-obvious. I used a visual beat-tap intervention where he practiced waiting for a visible cue before initiating utterances. I recorded his natural speech, slowed it to 75 percent speed, and had him tap along with the turns. Then we moved to live interaction with a timer light that changed color on the expected turn boundary. Over six sessions, his overlap rate dropped from roughly 18 overlaps per minute to about four. His social acceptance ratings from teachers improved measurably within two weeks of the intervention shift. The standardized tools would have sent him to group social skills training. The observation data pointed to a timing issue that group training would not have addressed.
Common Pitfalls That Waste Time
The biggest mistake I see is treating pragmatics assessment as a one-session event. Pragmatics is inherently variable. A child might perform adequately on a structured task with a familiar clinician and completely fall apart in an unstructured setting with peers. Single-session data is noisy. Spread assessment across at least three sessions in different contexts whenever possible. The extra time pays for itself in accuracy. Another mistake is over-indexing on verbal output. Pragmatic competence includes nonverbal channels: gaze direction, posture shifts, proxemic positioning, gesture use. A child who maintains appropriate eye contact but cannot manage conversational repair has a different clinical picture than a child who uses gesture effectively but fails at lexical-level reference. Code the nonverbal channel separately. Combine the scores only after you have analyzed them independently. A third mistake is using role-play as assessment. Role-play is an intervention technique. It is not a valid assessment condition because it removes the unpredictability that defines real pragmatic interaction. I have seen clinicians spend 45 minutes watching a child role-play a store transaction and then write a full report based on that interaction. The child performed well. The report said the child had adequate pragmatic skills. The child could not buy a snack at the cafeteria without adult prompting. Role-play data is useful for intervention planning. It is not useful for baseline assessment.

When Pragmatics Assessment Does Not Work
This approach assumes a certain level of cognitive and linguistic foundation. Children with significant intellectual disability, severe receptive language disorder, or limited verbal output may not have enough baseline communication to make pragmatic assessment meaningful. In those cases, the assessment shifts toward functional communication analysis: what does the child currently do to get needs met, what modalities do they use, and where do the breakdowns occur. The framework is the same. The tools change completely. Using a standard pragmatic battery with a nonverbal child who communicates through AAC is producing invalid data. Switch to functional communication monitoring and naturalistic observation of AAC use instead. Another scenario where this model fails is autism with high support needs where sensory processing dominates interaction patterns. A child may appear pragmatically impaired because they are overloaded by environmental input, not because they lack pragmatic competence. In those cases, assessment in a regulated sensory environment produces more accurate results than assessment in a typical clinic room. The tool is not broken. The context is. Adjust the context and re-assess.
Putting It Together
Start with caregiver and teacher ratings across at least two settings. Collect language samples in semi-structured interaction. Run targeted structured tasks that isolate specific pragmatic functions. Track repair initiation and listener-directed modification as your primary metrics. Record sessions when possible for later coding. Watch for mismatches between standardized scores and naturalistic behavior and treat those mismatches as the most clinically valuable data you will collect. Adjust your assessment context for sensory or cognitive factors rather than forcing the child into a standardized procedure that was never designed for their profile. Pragmatics assessment is not about producing a number. It is about mapping where communication actually breaks down so you can target intervention precisely.