How Precautions Work in Occupational Therapy Practice
Occupational therapists don't just prescribe exercises and move on. We identify activity restrictions — commonly called precautions — and build them into every intervention plan. A single missed precaution can undo months of surgical healing or trigger a regression. I've seen it happen. The core concept is straightforward: a precaution is a specific limitation placed on a patient's movement, activity, or use of a body part based on their diagnosis, surgical procedure, or underlying pathology. The OT's job is to recognize those limitations, communicate them clearly, and adapt the therapeutic process around them without sacrificing functional progress.
How to Identify and Apply Precautions Occupational Therapy
Here's the actual workflow. First, pull the referral or medical record. Look for surgeon-specific notes if there's been a procedure. General diagnoses like "osteoarthritis" or "CVA" carry their own standard precautions. Post-op diagnoses carry far more specific ones. Then cross-reference with the patient's current presentation — a textbook precaution list means nothing if the patient has comorbidities that shift the risk profile. Next, document the precautions in the plan of care. This isn't optional paperwork. It's a safety mechanism. Every therapist on the case needs to see them. I've worked in settings where the precaution was written on one sheet and the treating therapist was pulling from a different system. That gap is where mistakes happen. Then you modify the intervention. Adaptive equipment, splinting, task analysis, environmental modification — whatever the situation demands. The goal is always the same: the patient makes progress toward independence while staying within the boundaries you've established.
Common Precautions by Condition
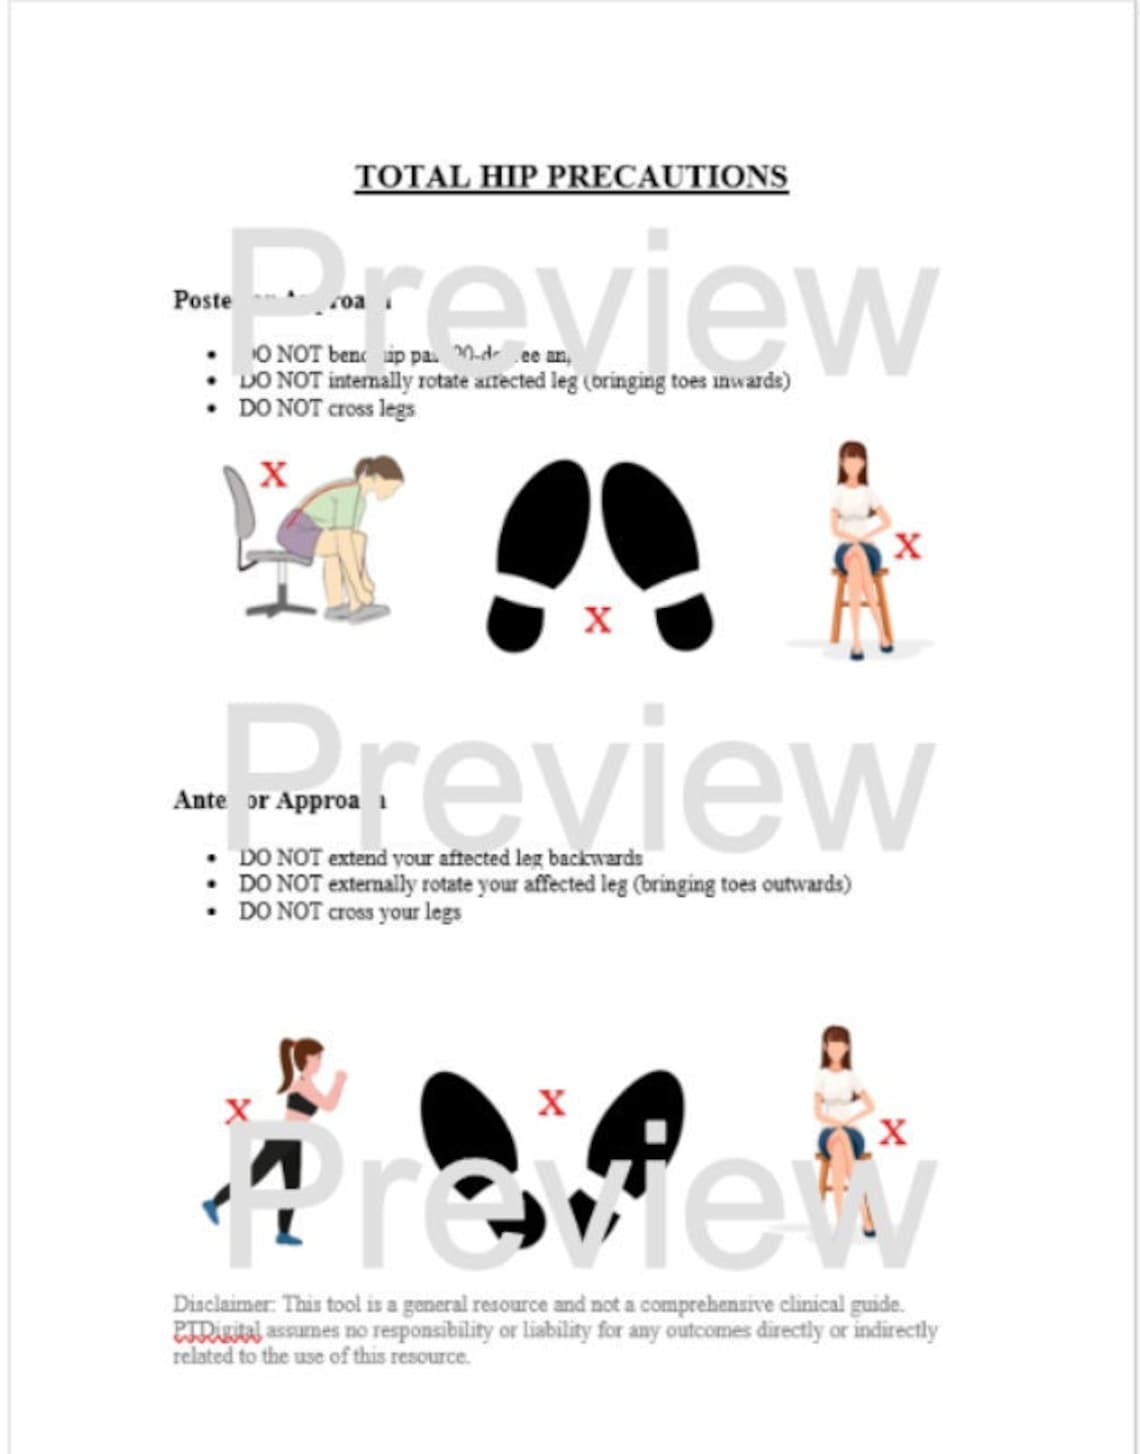
Post-surgical cases dominate my caseload and they carry the hardest-to-memorize precaution lists. Total hip replacement typically involves no flexion beyond 90 degrees, no adduction past midline, no internal rotation. Total shoulder replacement varies by surgical approach — posterior approach precautions are stricter than anterior. Wrist fracture immobilization usually means no loading through the affected extremity until cleared. You need to know which surgery was performed, because the precautions change accordingly. Neurological conditions bring their own set. Post-stroke patients often have hemineglect, which means you don't just warn them about one-sided activity — you structure the environment and the task so neglect doesn't become a safety hazard. Spinal cord injury precautions include autonomic dysreflexia monitoring, pressure relief schedules, and skin integrity checks. Rheumatoid arthritis patients need joint protection principles: avoid sustained grip, minimize weight-bearing through inflamed joints, pace activities. Fall precautions are universal but often under-addressed. A patient who has fallen once in the clinic should be treated as a fall risk in every subsequent session unless proven otherwise. That's not pessimism. It's baseline safety.
Get the Full Details

The Problem Nobody Talks About
Precautions create a tension between safety and function. Strip a post-shoulder-surgery patient of too many movements and they lose independence in dressing and feeding. Push too hard and you risk re-injury. The balance depends on phase of healing, tissue tolerance, and the patient's actual goals. Two therapists working the same patient with the same precautions will make different calls. That's normal. But it needs to be documented so the reasoning is traceable. Another issue is precaution drift. Early in treatment you're strict. By week four, when the patient is improving, the precautions get looser without any formal review or clear-out from the referring provider. I've encountered this repeatedly. The safe move is to request written clearance before relaxing any surgical or medical precaution. Don't assume the tissue is ready just because the patient feels ready. Patient-reported improvement and tissue-level healing are not the same thing.
A Specific Case
Three years ago I had a patient who'd had a distal radius fracture repaired with a volar plate. The precaution was clear: no resisted wrist extension, no weight-bearing through the upper extremity. The patient was a retired carpenter. He needed to lift, grip, and support himself to transfer. Standard adaptive equipment wasn't solving the problem — he needed to regain enough proximal control to compensate for the wrist limitation during transfers and community mobility. What worked was shifting the focus to scapular and trunk mechanics. We trained him to use a platform walker with modified weight distribution through the scapular girdle rather than the wrist. We also introduced a custom forearm trough that transferred load away from the wrist entirely while still allowing forward progression. It took six weeks of consistent work and weekly re-assessment of pain and swelling. The precaution held the entire time. He returned to his workshop modifications about ten weeks out. The workaround wasn't breaking the precaution — it was finding an alternate movement strategy that respected it.
Documentation That Actually Matters
Write the precaution, the rationale, the adaptation, and the patient's response. Not "patient tolerated activity well." Write what was modified, what was avoided, and what the functional outcome was. If a precaution was lifted or modified, document the source of that decision. Surgeon note, phone conversation with dates, clinical justification — something verifiable. This protects the patient and it protects you. Insurance reviews and legal inquiries don't care about your intent. They care about what you wrote down.

When Precautions Aren't Enough
Sometimes the precautions essentially rule out the activities the patient needs for daily living. A total hip precaution that prevents sitting below a certain height is a dealbreaker for someone who lives in a walk-up apartment with a low toilet and a low car. No amount of exercise fixes that. The appropriate response is environmental modification — raise the toilet, install a grab bar, recommend a vehicle with higher seating. If you can't modify the environment and the precautions block essential function, you escalate to the referring provider. That's not a failure of therapy. It's a recognition of a boundary. Precautions in occupational therapy are not suggestions. They are clinical constraints that define the space in which effective treatment happens. Work inside that space carefully. Document everything. And never let the patient's motivation override the tissue's healing timeline.