Fetal Heart Rate Monitoring During Pregnancy: What Actually Matters
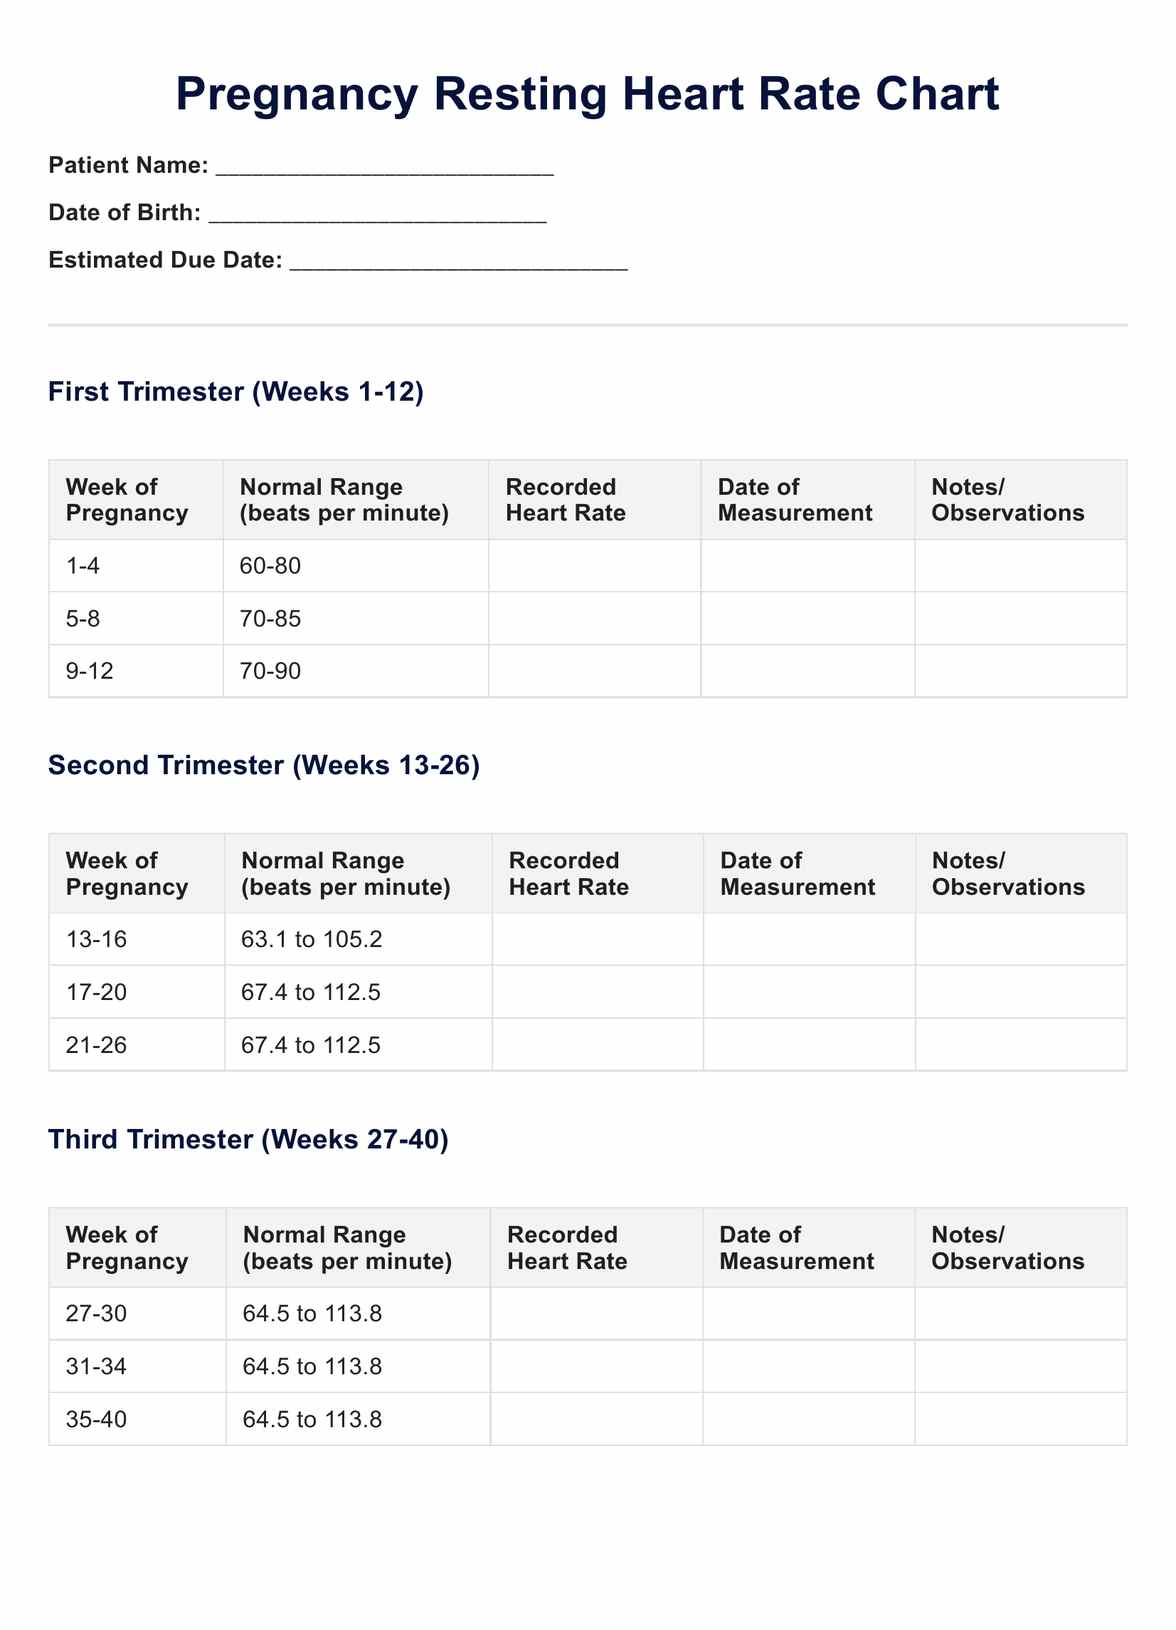
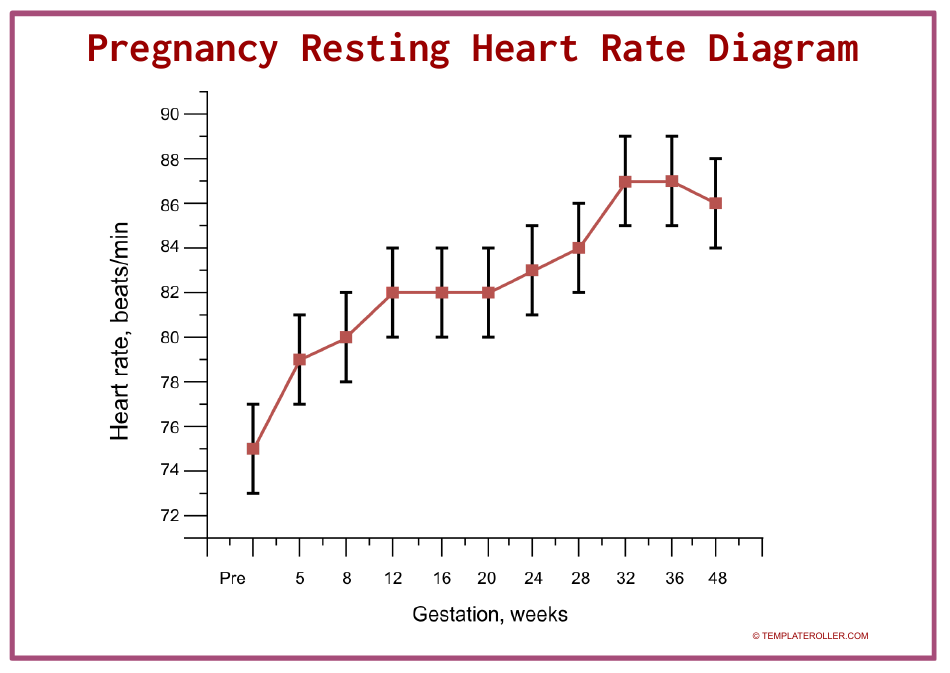
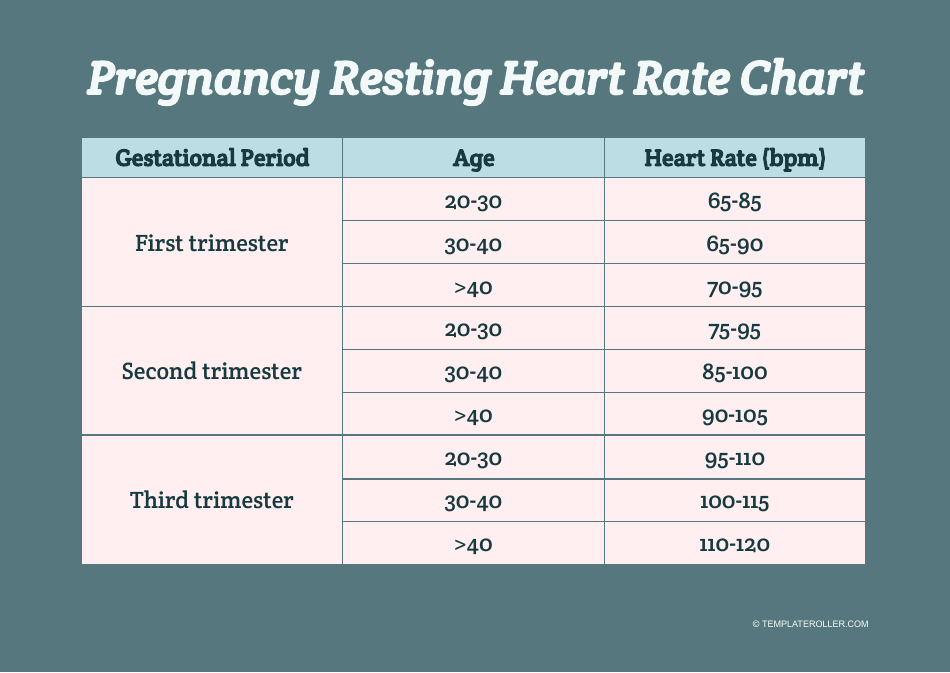
I spent three years working in a maternity ward before moving to telehealth, and I still encounter patients who panic because their at-home Doppler picked up a reading that doesn't match the chart online. Let me explain how fetal heart rate monitoring actually works in practice, what's normal, and what I learned the hard way about when to stop worrying and when to call the clinic. A normal fetal heart rate during pregnancy varies significantly by gestational age. Between 6-10 weeks, the fetal heart typically beats between 90-110 beats per minute, gradually increasing to around 170-180 bpm by week 9-10. From roughly 10 weeks onward through term, the normal range settles between 110-160 bpm. That's the textbook range, but here's what the textbooks don't emphasize enough: fetal heart rate is remarkably variable and influenced by movement, sleep cycles, maternal position, and even the timing of contractions if you're in labor. The American College of Obstetricians and Gynecologists defines normal baseline fetal heart rate as 110-160 bpm with moderate variability (6-25 bpm) and accelerations present. Decelerations require clinical correlation and aren't automatically concerning depending on type and timing. Early decelerations typically mirror head compression during contractions and are benign, while late decelerations suggest uteroplacental insufficiency and warrant immediate evaluation.
How I Actually Monitored Heart Rates in Practice
When I was floor nursing, I used a standard Doppler for routine checks and a Cardiotocography (CTG) machine for continuous monitoring in high-risk cases. The handheld Doppler gives you a spot reading, usually between 20-30 seconds, which is sufficient for routine visits at 32+ weeks. For stress testing or late pregnancy monitoring, we'd hook patients up to the CTG for 20-40 minutes and look for the patterns I mentioned above. Here's the thing nobody tells you: at-home Dopplers are notoriously unreliable for detecting variability and accelerations. They give you a number, but that's it. A single reading of 145 bpm means almost nothing clinically. You need to observe the heart rate over time to assess variability, which is the real predictor of fetal well-being. The variability tells you whether the autonomic nervous system is functioning properly. I had a patient at 38 weeks who came in panicking because her at-home Doppler showed 155 bpm, which she'd read on a website as "too high." She was in active labor by the time she arrived because she'd waited two hours comparing numbers online. The fetal heart rate was perfectly normal for someone contracting every 3-4 minutes. Labor increases heart rate through catecholamine release, and that's expected.
What I Learned About False Alarms and Missed Signs
The most common pitfall I saw was patients focusing on absolute numbers rather than patterns. A baseline of 150 bpm with moderate variability and accelerations is far more reassuring than a baseline of 130 bpm with minimal variability. Variability is the single best predictor of fetal acid-base status in the antepartum period. When variability drops below 5 bpm for extended periods, that's when we get concerned, not when the absolute number sits slightly outside a range. Conversely, I encountered one case where a patient reported decreased fetal movement but normal heart rate on her Doppler. She dismissed it because the number looked fine. The heart rate was 140 bpm, but she hadn't felt movement in six hours. We ran a biophysical profile and found oligohydramnios with a zero amplitude pocket. She delivered a baby with meconium-stained fluid and low Apgars. The takeaway: movement assessment and heart rate monitoring are separate evaluations. Don't use one to invalidate the other. Another nuance beginners miss is the effect of maternal medications. Beta-blockers, magnesium sulfate, and certain anesthetics can cross the placenta and blunt fetal heart rate variability. I had a patient on magnesium for preterm labor whose tracings looked suspiciously flat. Once we adjusted the dosage and monitored her levels, the variability returned to normal. If you're on any medications, tell your provider before interpreting heart rate data.
Get the Full Details
When to Seek Immediate Evaluation
Sustained heart rate above 160 bpm (tachycardia) lasting more than 10 minutes warrants assessment, especially if accompanied by decreased movement, fever, or dehydration. Maternal tachycardia from infection or hyperthyroidism transfers to the fetus. Conversely, sustained bradycardia below 110 bpm requires prompt evaluation to rule out conduction abnormalities or hypoxic compromise. Accelerations are generally reassuring. A reactive non-stress test shows at least two accelerations of 15 bpm above baseline lasting 15 seconds each within a 20-minute window. This pattern suggests an intact fetal nervous system and adequate oxygenation. Absence of accelerations in a gestation past 32 weeks triggers further testing, usually a contraction stress test or biophysical profile. Here's where the limitations become apparent: at-home monitoring devices cannot reliably assess these patterns. They give you a number, not a tracing. If your at-home device shows an unusual reading, don't panic immediately, but don't ignore persistent abnormalities either. Call your provider and describe what you observed, including duration and any associated symptoms like decreased movement or contractions.
Practical Tips for Home Monitoring
If you choose to monitor at home, position yourself on your left side to optimize uterine blood flow. Use lubricant on the Doppler and apply firm but gentle pressure. Locate the heart sound first, then count for a full 60 seconds rather than trying to time shorter intervals. The fetal heart is typically heard best in the quadrant opposite the baby's back, which varies by position and gestational age. Record your findings with the time, position, and any activity you were doing. This documentation helps your provider distinguish between normal variants and genuine concerns. A reading of 155 bpm after walking upstairs is different from 155 bpm at complete rest. Context matters more than the number itself. I've seen too many patients spiral into anxiety over readings that were perfectly benign. But I've also seen too many dismiss genuine concerns because the number looked "fine." The middle ground is learning to recognize what normal variability looks like when you hear it consistently, then reporting persistent deviations or any change from your baby's usual pattern. Trust your instincts about movement more than any single heart rate number.
The bottom line: fetal heart rate monitoring is a tool, not a diagnosis. Normal ranges exist, but interpretation requires clinical context and pattern recognition that a handheld device simply cannot provide. Regular prenatal visits with appropriate testing remain the standard of care. If something feels off, call your provider rather than self-diagnosing from online charts or sporadic Doppler readings.