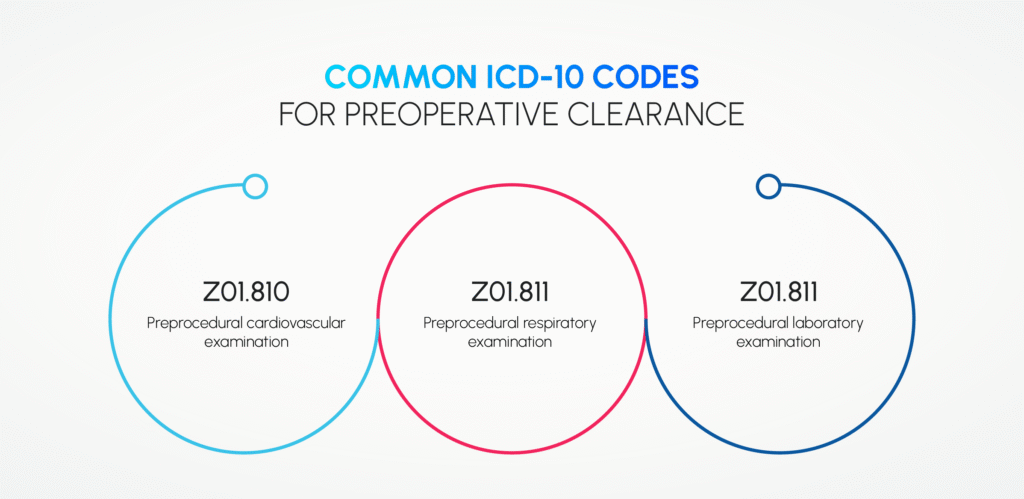
Getting Z codes right before surgery saves a lot of headaches later
I'm talking about the Z codes in ICD-10 that cover preoperative exams. Specifically Z01.818, which is the code for other special preprocedural examinations, and Z01.812 for preprocedural laboratory examination. Most people who work in medical billing or surgical scheduling run into these daily. You need them to justify why a patient is getting labs or imaging before a procedure that's already been planned. Here is how it works in practice. When a surgeon schedules a patient for an elective appendectomy, the hospital needs a reason to run the preop CBC, CMP, and EKG. Without a Z code, those tests often get denied as not medically necessary because they're not tied to a diagnosis. The Z01.818 code fills that gap. It tells the payer that yes, this patient needs an exam before the surgery, and no, the exam isn't the same thing as the surgery itself.
Preoperative Exam Icd 10 coding rules you actually need to know
There is a difference between a standard preoperative exam and what you see coded as Z01.818. The Z01.818 code is specifically for when the preoperative examination is done for surgical clearance but there is no identified abnormal finding during that exam. If the preop visit uncovers something new, like elevated blood sugar during a routine check before a knee replacement, you need to add the new diagnosis code alongside the Z code. Just using Z01.818 alone in that situation will flag an audit risk. Another thing most coders miss is the distinction between Z01.818 and Z02.89. Z02.89 is for exposure examinations, which sounds similar but covers different scenarios. If a patient comes in preoperatively and the surgeon orders a chest X-ray because of occupational exposure history, that goes to Z02.89, not Z01.818. Mixing these two up is one of the top reasons I see claim denials in surgical preop work. The Z01.42 code also comes up sometimes, which is for gynecological exams before certain procedures. If you are prepping a patient for abdominal surgery and the surgical team orders a recent pelvic exam as part of the clearance, that may warrant Z01.42 if it meets the criteria. But the rule here is the exam must be a standard of care requirement for the procedure, not just a nice-to-have.
I ran into a specific problem about two years ago that took me three weeks to resolve properly. We had a patient scheduled for a elective carpal tunnel release. The surgeon ordered a preop stress echocardiogram because the patient had a history of palpitations, even though they were currently asymptomatic. The initial claim came back denied because we only had Z01.818 and no cardiac diagnosis code. The payer argued the echo was not standard for carpal tunnel surgery. The workaround I used was to layer the codes correctly. I kept Z01.818 as the primary code for the preoperative examination context, then added I47.9 for paroxysmal tachycardia, unspecified as the secondary diagnosis since the patient's history of palpitations had previously been documented under that term. I also added an ABO modifier on the claim to indicate that this was an additional service beyond what is routinely covered for the surgical episode. The second submission went through without issues. The key takeaway is that Z01.818 is a circumstance code, not a diagnosis code, and payers will reject it as the sole code on a claim line. There is a nuance with Medicare that catches a lot of people off guard. Medicare does not always cover Z01.818 as a standalone service in all settings. In the outpatient hospital setting, Medicare may bundle the preoperative exam into the global surgical package depending on the CPT code range for the procedure. You need to check the specific NCCI edit pairs and the Medicare Physician Fee Schedule before submitting. Using Z01.818 without verifying coverage for the specific surgical CPT code is where the real money gets lost in denials.
Get the Full Details

Private payers are not much better. UnitedHealthcare and Aetna both have their own policies on preoperative examination coverage, and they differ from each other. Some require documentation of medical necessity that goes beyond the Z code alone. You might need a surgeon's note on the claim form or in the attached documentation explaining why the preop exam is needed for this particular patient. Having a template note from your surgical staff that addresses the common payer requirements will save you several hours of appeal work per month. The Z00.5 category also overlaps here occasionally. Z00.5 is for routine child health examination, and if a pediatric patient is having preoperative labs as part of a wellness visit before surgery, some coders try to double-dip with Z00.5 and Z01.818. That is not appropriate. You can use Z00.5 if the visit genuinely qualifies as a routine wellness exam, but you cannot use both codes to justify the same lab work. Pick the code that best represents the primary purpose of the encounter. For anyone using an encoder or CDI tool, Z01.818 shows up under the Z01 series in the 2026 ICD-10-CM tabular list. Make sure you are on the current version. The code descriptor changed slightly from earlier years, and using the old descriptor in your documentation templates will create confusion during audits. The current descriptor reads as an encounter for other special preprocedural examination.
One more practical point that nobody talks about enough. The timing of when you use Z01.818 matters. If the preoperative exam happens on the same date of service as the surgery itself, you generally should not use Z01.818 on that claim. The global surgical package absorbs the preop evaluation into the procedure. The code is meant for separate encounters where the clearance exam is scheduled independently before the surgery date. I have seen clinics bill Z01.818 on the day of surgery and get slapped with overbilling violations. It happens more often than you would think. If you need a reference or a code lookup tool, the CDC publishes the full ICD-10-CM official guidelines at icd10.cdc.gov. For payer-specific preoperative coverage policies, you would need to check each carrier's medical policy document directly since those change regularly. CMS puts the Medicare coverage matrix online, but private payer documents are scattered across their provider portals.