Wound Bed Prep and Why Staging Feels Like Guesswork Until It Doesn't
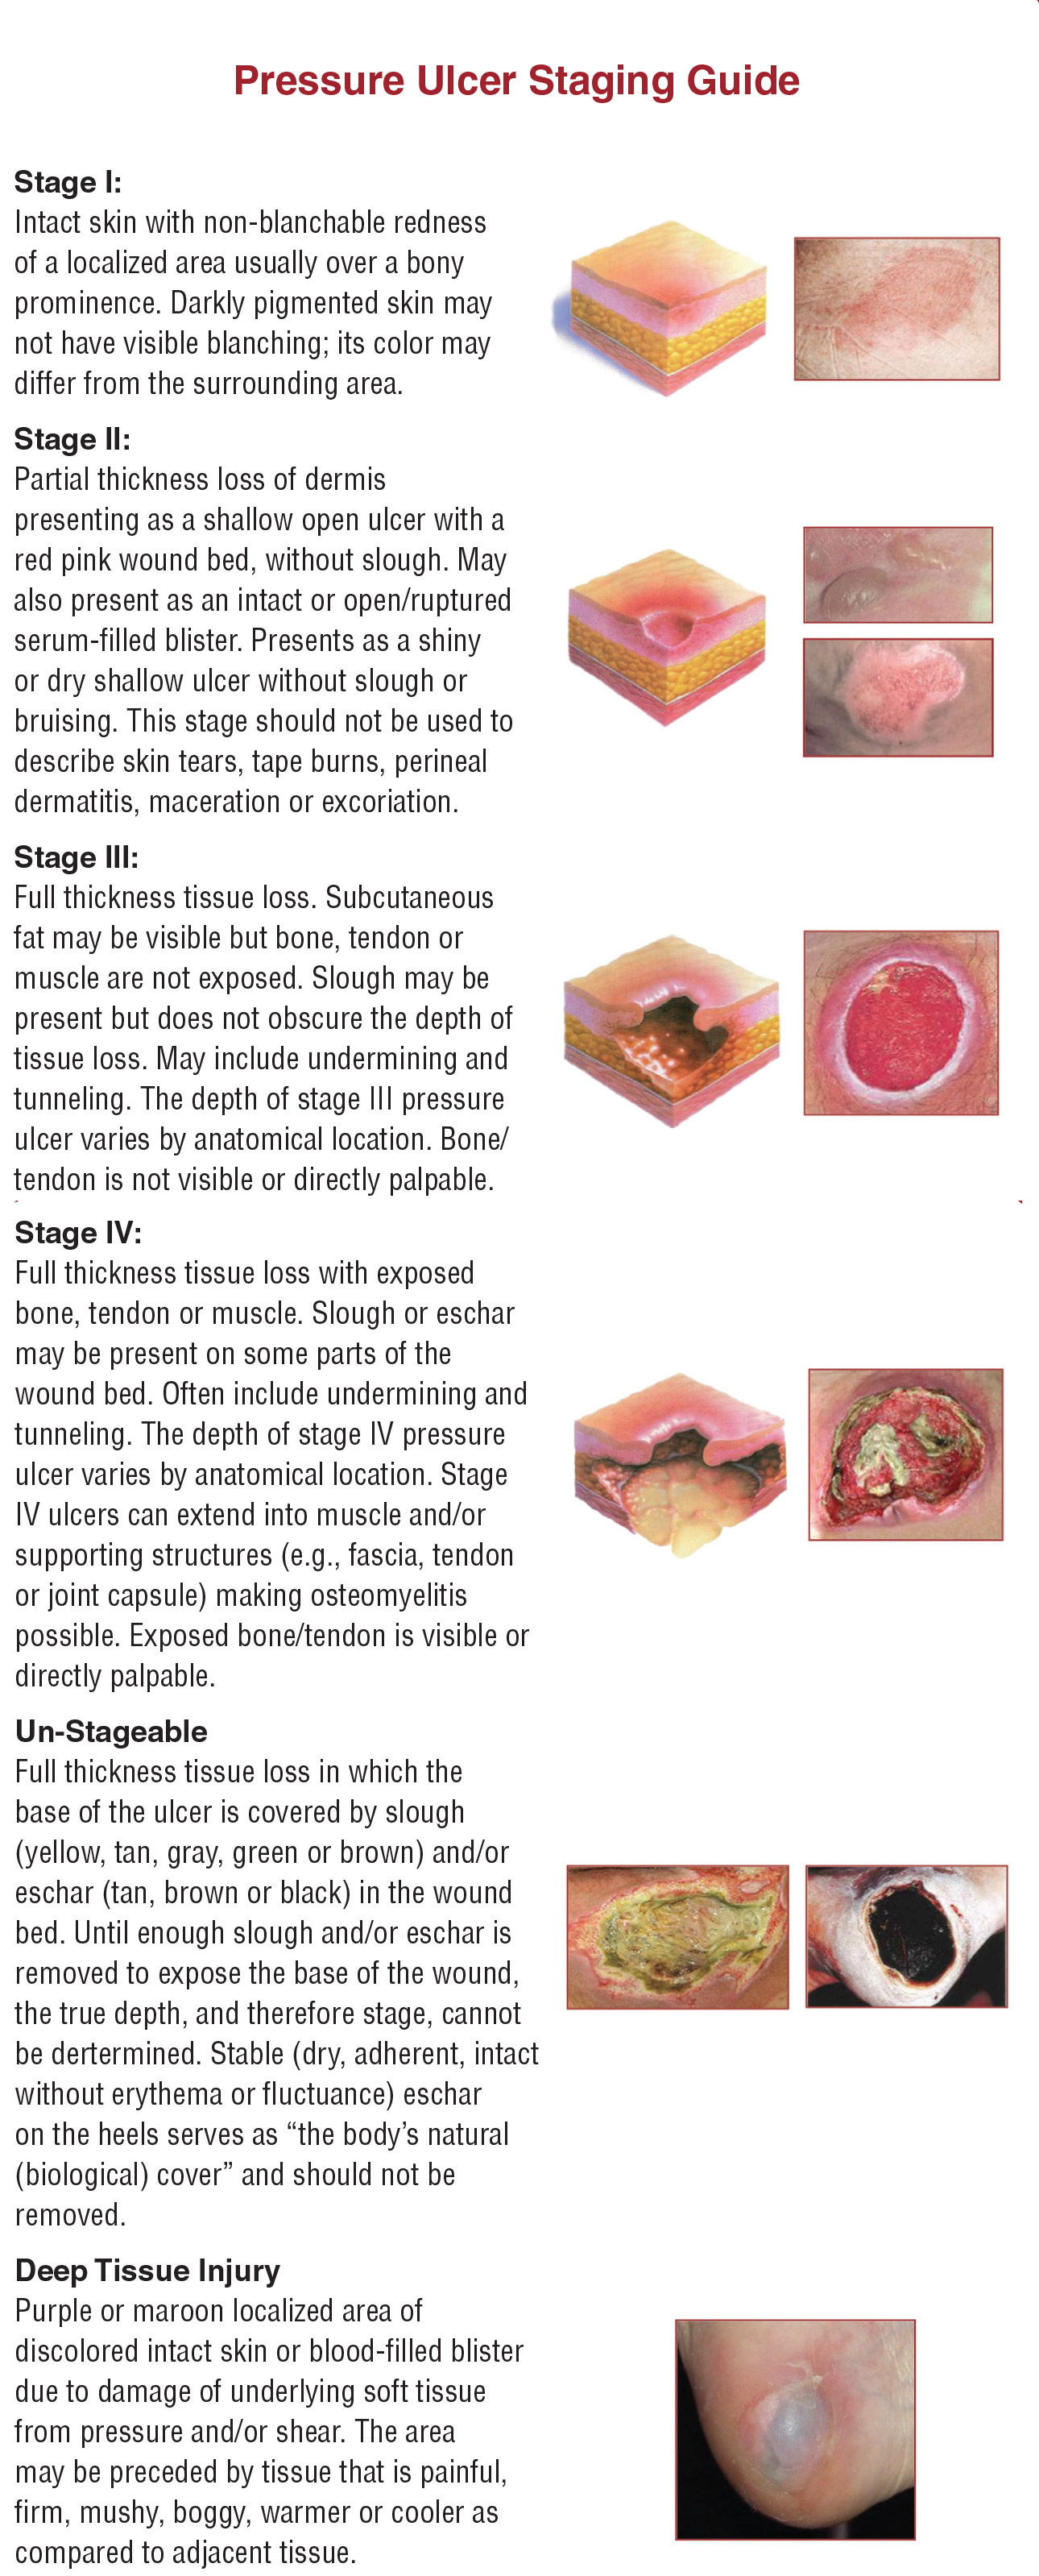
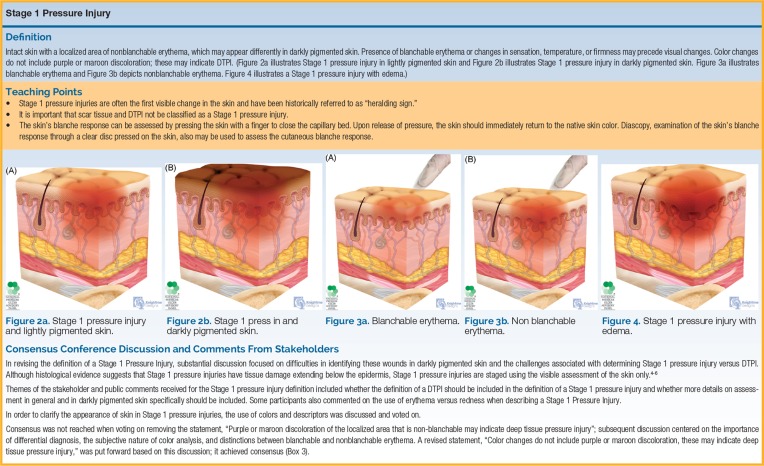
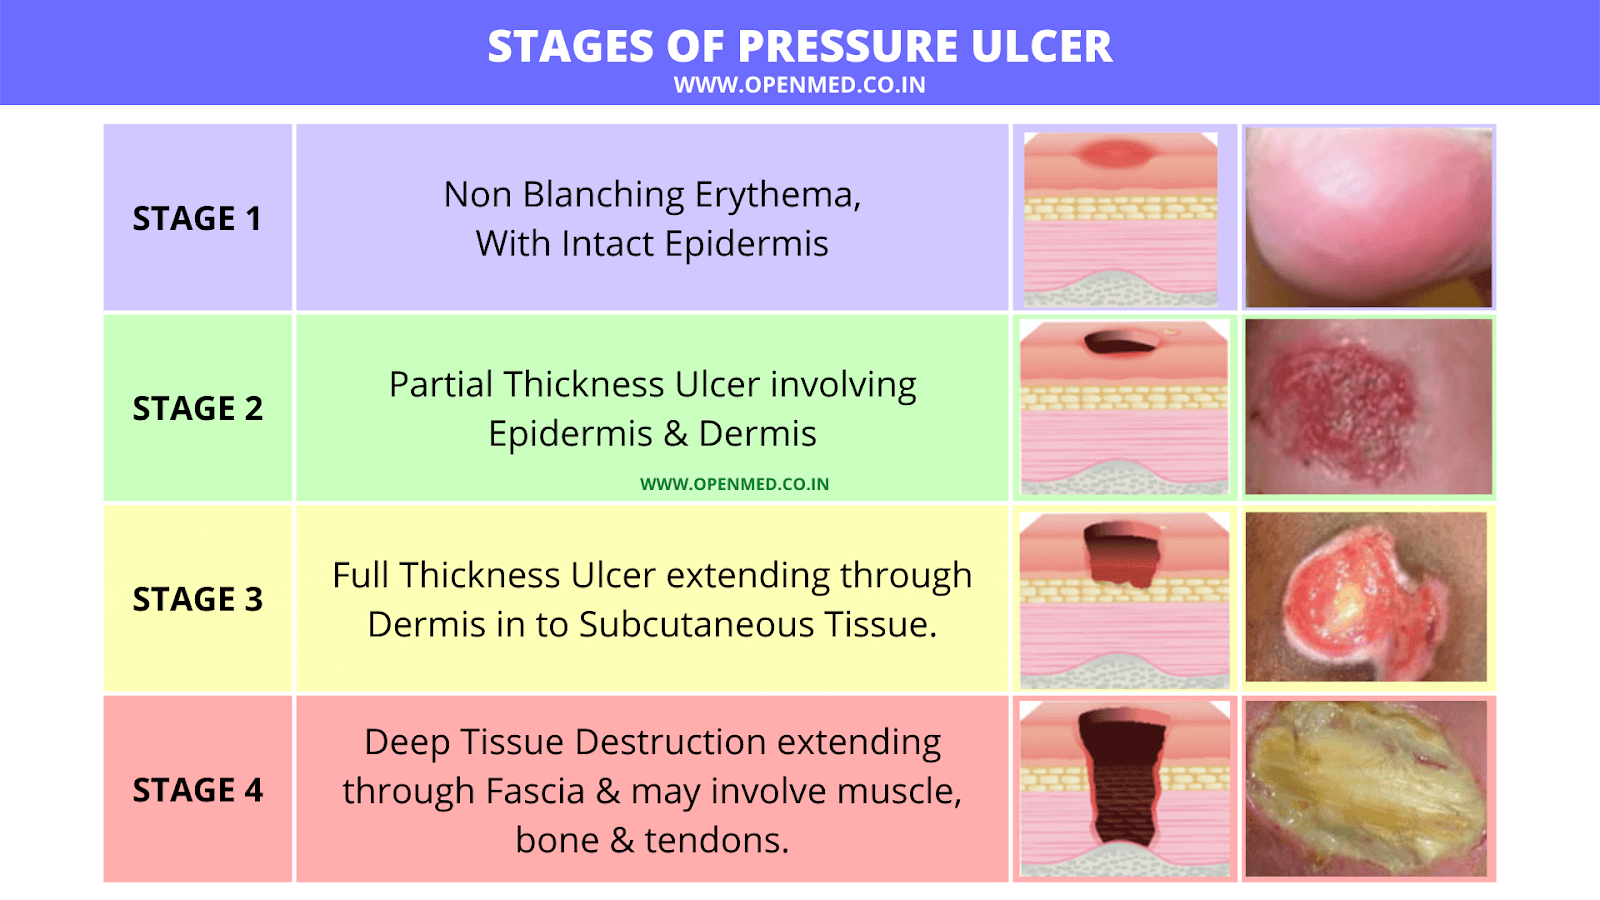
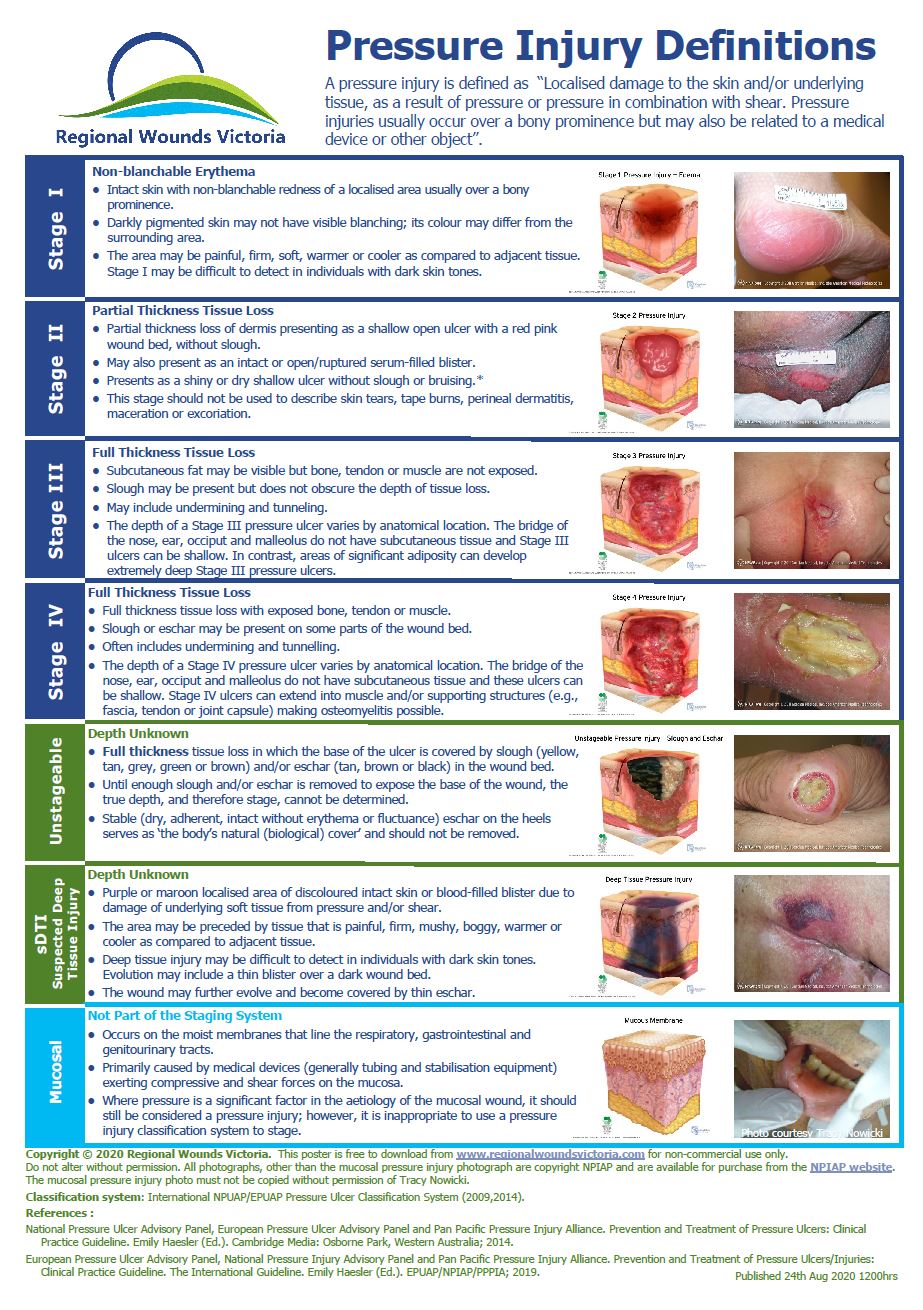
I spent about six years on a surgical floor before moving into wound care consulting, and the thing I see most wrong isn't the dressings — it's the staging documentation. Nurses and even some residents will look at a sacral ulcer and call it a Stage 3 because they can see fat, but miss that 2mm of slough on the medial wall is technically obscuring the base, which by NPUAP/EPUAP 2019 guidelines means Unstageable until you clear it. I've had wound nurse consultants come in and completely re-stage patients based on photos I'd already documented, and 80% of the time the original stager had just looked at the wrong part of the wound. The current framework comes from the 2019 International Guideline by the NPUAP, EPUAP, PPPIA, and WUWHS. The stages are Stage 1 through Stage 4, plus Unstageable and Deep Tissue Pressure Injury. That last one is where most people mess up, so let me be blunt about that separately. Stage 1 is non-blanchable erythema on intact skin. The key word is intact. If there's any break in the skin, it's not Stage 1, no matter how superficial it looks. In darker skin tones, the discoloration may present as persistent redness, blue, or purple hues rather than pink — and here's the practical thing they don't always emphasize enough: press on the surrounding skin, not the lesion itself. The area that doesn't blanch when you release is your indicator. I've seen people press directly on the discolored patch and then get confused when nothing happens.
Stage 2 involves partial-thickness skin loss with exposed dermis. It looks like a shallow open ulcer, a blister, or an abrasion. Crusted areas do not count. If there's eschar, you can't call it Stage 2 yet. The depth varies by anatomical location — skin over the nose, ears, occiput, and malleoli is thin, so what looks like a Stage 2 there might actually be deeper than it appears on the thigh. Stage 3 is full-thickness skin loss where subcutaneous fat may be visible but bone, tendon, or muscle is not exposed. Undermining and tunneling are common complications that the stage number alone doesn't capture, which is why you need to document those separately with clock-face notation. A Stage 3 with 4cm of undermining at the 6 o'clock position is clinically different from a Stage 3 without it, even though the stage is the same on paper. Stage 4 exposes bone, tendon, or muscle. This is where it gets serious. Osteomyelitis risk climbs significantly once you see bone, and even a small amount of exposed capsule or periosteum on a joint counts here. I once had a patient who was technically Stage 3 by looking at the anterior wound bed, but the posterior wall had eroded down to the iliac crest — that's Stage 4, and the staging should reflect the deepest extent.
Unstageable means the true depth is obscured by slough or eschar. Yellow, tan, gray, green, or brown slough, or black/brown eschar. You cannot determine the stage until enough of this is removed to see the wound base. I've seen this misapplied constantly — someone will describe a wound with thin yellow slough and call it Unstageable, but if you can clearly see through the slough to the wound base and identify depth, it's actually a Stage 3. The rule is: can you see the base? If yes, stage it. If no, Unstageable. Deep Tissue Pressure Injury (DTPI) is the one that causes the most arguments at case conferences. It presents as persistent non-blanchable deep red, purple, or maroon discoloration of intact skin, or a blood-filled blister. The tissue underneath is damaged even though the surface looks relatively okay. Here's the counter-intuitive part that catches people: DTPI can evolve rapidly. I had a patient with a small maroon patch on the greater trochanter that I documented as DTPI on a Monday, and by Wednesday it had fully sloughed into what turned out to be a Stage 4. Don't wait and "reassess in a few days." Document the progression. If it deteriorates, update the stage — don't stick with DTPI just because that's what you first called it. Mnemonic devices like S1 through S4 are popular in student programs, but they're insufficient for clinical practice. The 2019 guidelines added important clarifications that older mnemonics don't cover — particularly around moisture-associated skin damage (MASD) being distinguished from pressure injuries, and the recognition that medical device-related pressure injuries form a distinct category.
Get the Full Details
Speaking of medical device-related PI, that's another area where staging gets confused. A nasal cannula causing pressure damage on the maxilla follows the same staging criteria, but you have to document the etiology separately. I've seen people stage these as Stage 2 when they were actually more severe because the device compressed tissue against bone in a way that created deeper injury than the surface appearance suggested. Always remove the device and reassess after 30 minutes of offloading before final staging. The biggest limitation of the staging system itself is that it's a snapshot. A Stage 3 doesn't tell you whether it's improving, worsening, or staying the same. Two wounds can both be Stage 3 and have completely different prognoses based on perfusion status, comorbidities, and wound bed characteristics. That's why the pressure injury staging guide should never be the only documentation — you need measurements, exudate amount, wound bed color percentages, peri-wound skin condition, and pain score every time you assess. The stage number alone is almost useless for tracking. Another practical bottleneck: the staging system doesn't account for wound size. A 1cm² Stage 3 and a 15cm² Stage 3 get the same letter but require radically different management. Some institutions have adopted the TIME framework (Tissue, Infection, Moisture, Edge) alongside staging to fill this gap, and honestly it's more useful for daily clinical decision-making than the stage number by itself.
For documentation, I recommend photographing every assessment with a ruler in frame and a side view showing depth. Front-on photos make everything look shallower than it is. The side-angle shot showing the wound profile relative to surrounding skin level is worth more than three paragraphs of text description.