Pressure Regulated Volume Control Ventilation
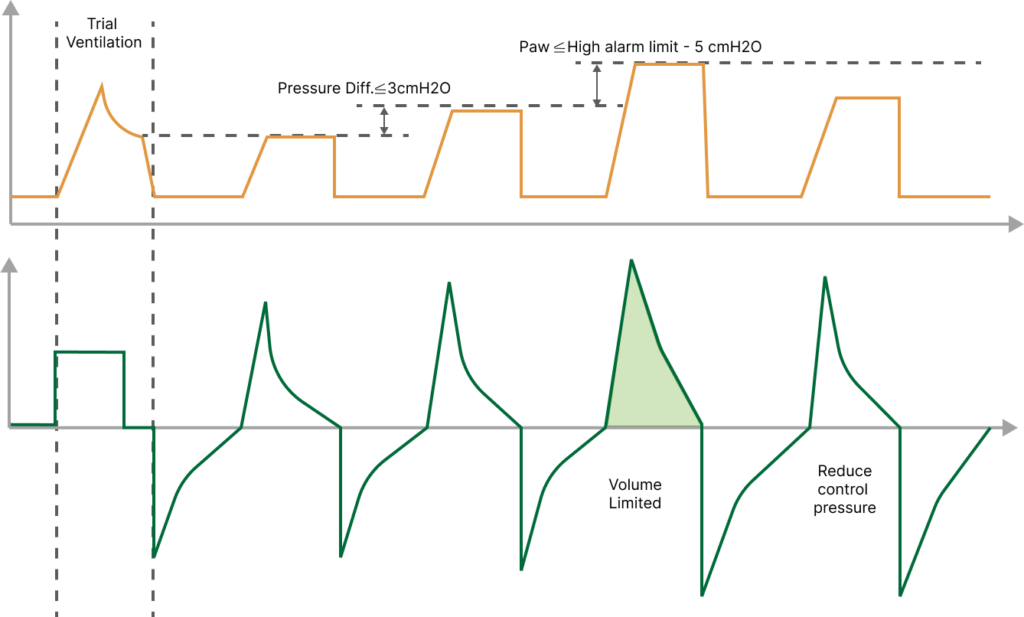
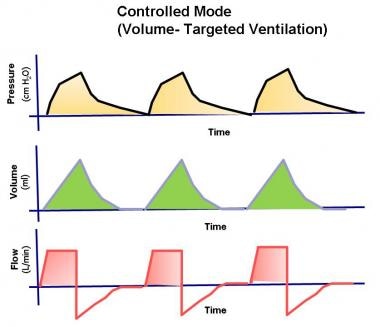
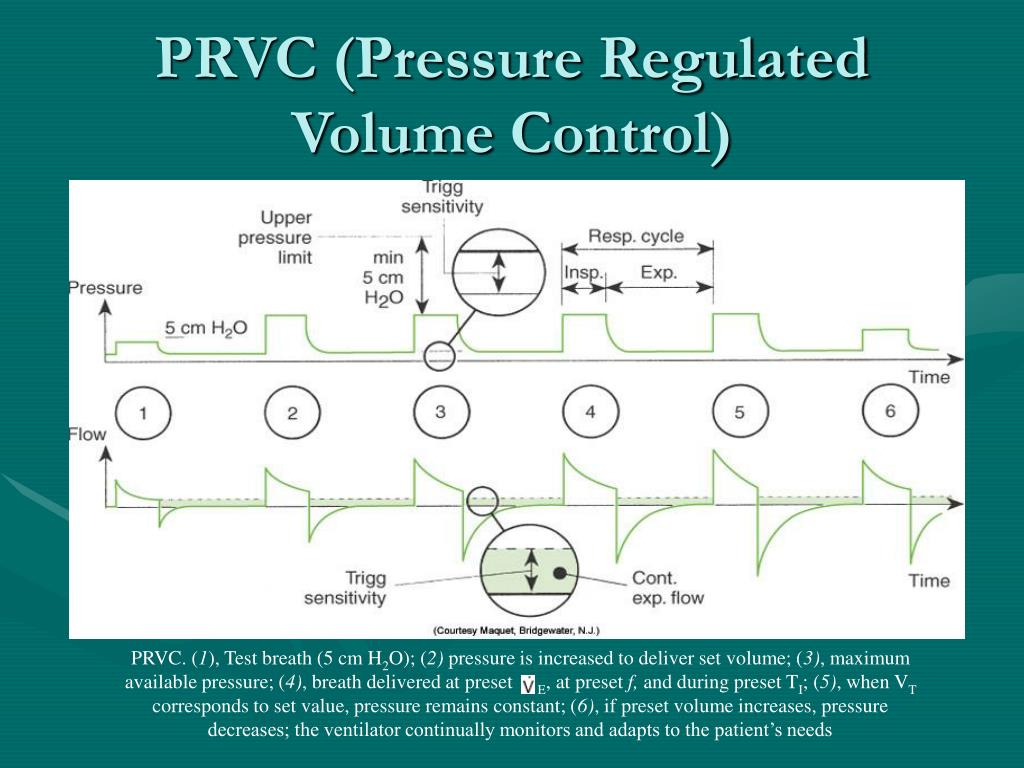
Most people think this mode is just pressure control with a volume target slapped on top. It's not. It's fundamentally different from both pressure control and volume control, and treating it like either one will get you in trouble at 3 AM.The mode works by delivering a set tidal volume, but the machine adjusts the peak inspiratory pressure each breath to hit that target. The pressure curve is decelerating, which means lower peak pressures compared to volume control while still maintaining minute ventilation. The pressure limit is set by you, and the ventilator backs off if it can't reach the volume without exceeding it. Start with your patient's ideal body weight. For ARDS patients, I usually begin at 6 to 7 ml/kg, not 8. The old textbooks still say 8, but the ALVEOLI trial changed the standard of care years ago, and a lot of people haven't caught up. Set your PEEP based on oxygenation needs. 5 cmH2O is the floor, but most of these patients need 8 to 12. Set your respiratory rate to get a minute ventilation around 5 to 6 liters. The machine will then automatically find the pressure it needs each breath to deliver your tidal volume.
The key variable most residents miss is the I:E ratio. It's fixed at roughly 1:2 in most ventilators running this mode, which you can't change. If your patient has severe obstructive disease and needs more expiratory time, this mode isn't going to help you. I've seen people fight with it trying to get longer expiratory phases before switching to something else.
What Actually Happens Breath to Breath
Every single breath, the ventilator measures what it delivered and adjusts the pressure for the next one. If the lung compliance drops — a common scenario in evolving ARDS or when secretions build up — the machine will gradually increase pressure until it hits your set limit. At that point, the volume delivered drops below your target. The display still shows the target volume, but the actual volume is less. This is where people get confused and think the ventilator is broken. When compliance improves, the opposite happens. The machine backs off pressure automatically. You don't have to manually adjust anything. That's the whole selling point, and it mostly works as advertised.
Get the Full Details
The Problem I Ran Into Last Month
I had a patient on this mode post-liver transplant. He had a sudden drop in compliance — likely from abdominal compartment syndrome — and the ventilator was maxing out the pressure limit, which meant his tidal volume was falling. His SpO2 was fine, but his PaCO2 was climbing toward 60. I spent twenty minutes going back and forth with the resident who wanted to just crank the pressure limit higher. The pressure limit was already at 35, and the patient's plateau pressures were effectively there too. Increasing it further risked barotrauma without actually solving the problem. The fix was checking abdominal girth and bladder pressure. The real issue wasn't ventilator settings. Once we decompressed the abdomen, compliance improved and the mode went back to doing its job. The ventilator was actually working correctly the whole time — it was telling us something was wrong. That's the thing about this mode: the pressure curve is a diagnostic tool, not just a setting.
Counter-Intuitive Things Beginners Miss
The auto-PEEP calculation is unreliable in this mode on many ventilators. The machine estimates it, but if your patient is generating significant respiratory effort or has intrinsic PEEP, the number on the screen is often wrong. Don't use it to guide your external PEEP adjustments. Measure it manually with an end-expiratory hold if you need accurate data. Another thing nobody tells you: trigger sensitivity behaves differently here than in pure pressure support. The flow-trigger window is narrower in some modes, and if the patient has severe auto-PEEP, they might struggle to trigger a breath before the next mandated one arrives. I've seen this in COPD patients where the ventilator was cycling so fast that the patient couldn't initiate anything. Switching them to a pure pressure support mode or adding a brief pressure relief period fixed it.
Where This Mode Falls Apart
Severe bronchospasm. The decelerating flow pattern fights against the patient's increased resistance, and you'll see massive pressure fluctuations breath to breath. It becomes unstable. Switch to volume control with a prolonged expiratory time or pressure control with a lower rate. Pneumothorax. If compliance suddenly drops, the mode will keep trying to hit the volume target by increasing pressure. You could push plateau pressures into dangerous territory before you notice. Monitor plateau pressures closely, not just peak pressures. Peak pressures can stay deceptively low in the early stages. Neuromuscular blockade failure. If the patient starts breathing spontaneously against this mode, the interaction between patient effort and the mandatory breaths creates bizarre waveforms. Some ventilators handle it better than others, but it's generally messy. Keep the patient adequately sedated and consider paralysis if you need to rely on the mode properly.

Practical Monitoring Parameters
Check plateau pressure every four hours minimum. In stable patients it stays under 30 cmH2O. If it's creeping up, compliance is dropping. Check it at the bedside with an end-expiratory hold — the number on the screen is sometimes delayed or averaged in a way that hides the real value. Monitor driving pressure. That's plateau pressure minus PEEP. Keeping it under 15 cmH2O is associated with better outcomes. This mode makes driving pressure easier to track because it stabilizes tidal volume, but the pressure changes still tell you everything you need to know about lung stress. Look at the pressure-time waveform. It should show a smooth decelerating pattern. If you're seeing spikes or irregularities, check for secretions, biting the tube, or a water trap in the circuit. I've wasted more time adjusting settings on vent machines that just had a puddle of condensate blocking the flow sensor.
How Long It Typically Stays Useful
In post-operative patients, maybe two to four days before they're breathing well enough to transition off. In ARDS, it can run for a week or longer if compliance is stable. The main reason people switch is either the patient is improving and ready for spontaneous breathing trials, or the lung mechanics have deteriorated beyond what the mode can compensate for. There's no hard rule on duration — it depends entirely on the underlying pathology. If you're using this mode and you're not periodically reassessing whether the patient still needs it, you're not using it properly. It's not a set-it-and-forget-it mode. The automatic adjustments are helpful, but they don't replace clinical judgment.