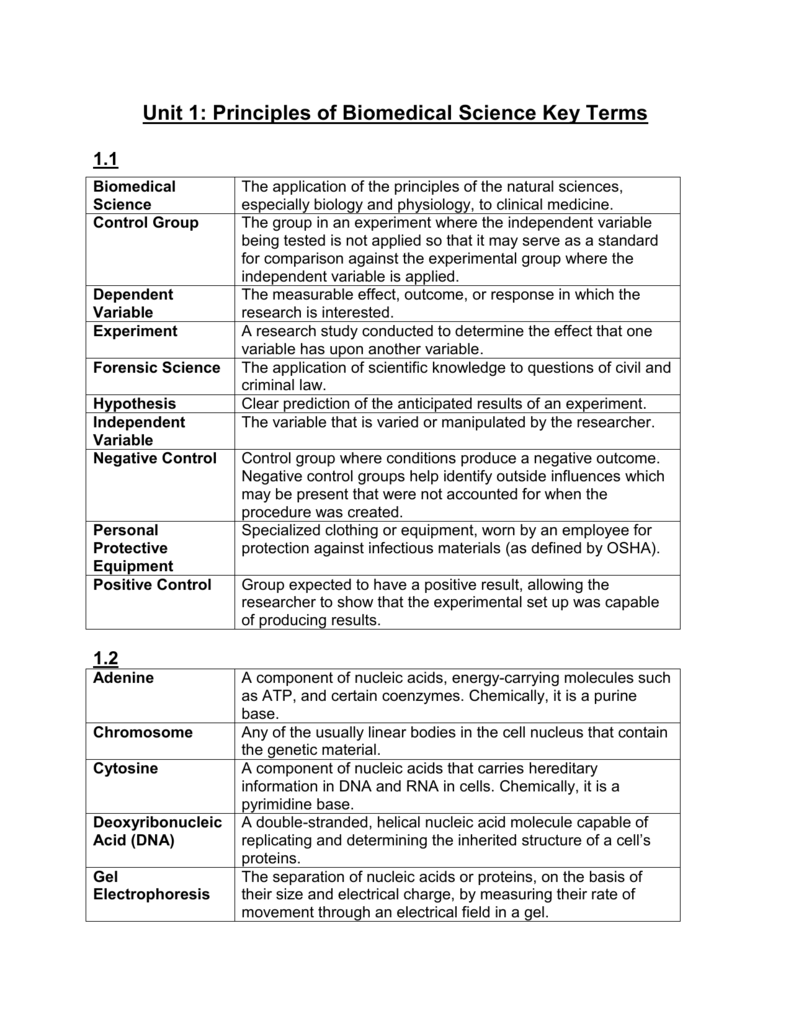
The Reality Of Working In A Biomedical Lab
Most people studying Principles Of Biomedical Science come at it from a classroom angle, but the actual application looks very different. I spent seven years in a hospital pathology lab running chemistry, haematology, and immunology sections before moving into quality management. The gap between exam questions and bench work is wider than most students expect. The core idea is straightforward: use scientific methods to analyse biological samples and produce reliable data for clinical decision-making. But reliability is the hard part. I remember running a batch of liver function tests where the bilirubin values were consistently five percent low compared to the reference method. Took three days to track it down to a temperature sensor drift in one of the incubators. The instrument was calibrated. The QC passed. The patient results were still quietly wrong. That's the thing nobody tells you about these principles. They work perfectly until a real-world variable violates an assumption you didn't know you were making. Analytical validity depends on controlled conditions. Biological samples do not respect controlled conditions. Serum from a lipemic patient will interfere with colorimetric assays. Hemolysis releases intracellular potassium. A tourniquet left on too long concentrates proteins and skews albumin results. These aren't edge cases. They are daily occurrences.
The Validation Gap Between Theory And Practice
When you validate a new test method, textbooks walk you through precision, accuracy, linearity, and reference interval confirmation. What they don't emphasize is that validation is never finished. Reagent manufacturers change suppliers. Lot numbers shift. Instrument software updates alter algorithms. I once validated an immunoassay for thyroid hormones against a published reference method and got perfect correlation. Six months later, the manufacturer reformulated the calibrator without updating the package insert. The correlation held numerically but the absolute values drifted by nearly twelve percent. Clinical interpretations changed for every patient on that assay. External quality assessment schemes exist precisely because internal checks aren't enough. A lab can pass every internal QC run and still have a systematic bias that only becomes visible when results are compared across laboratories. UKNEQAS and similar programs catch this. Using them as a formality rather than a diagnostic tool is one of the most common mistakes I see from junior staff.
Quality Management Is Where The Real Work Lives
The most important principle in biomedical science isn't any single technical concept. It's the framework that holds everything together. ISO 15189 structures how a lab operates from sample receipt to result delivery. Document control, competency assessment, complaint handling, corrective actions. It sounds bureaucratic until a regulator shows up or a clinician challenges a result and you need to prove every step was performed correctly. I once had a pathologist dispute a creatinine result for a patient being assessed for chemotherapy dosing. The value was borderline and the clinical picture didn't align. Pulling the records, I traced the entire pre-analytical chain. The sample had been drawn from a line drawing saline solution. The result was technically accurate for the sample as received but clinically misleading. The principle here isn't just about running the test correctly. It's about understanding what the test result actually represents in context.
Get the Full Details
Clinical Decision Limits Versus Reference Intervals
Reference intervals tell you what is typical for a healthy population. Clinical decision limits tell you when a result requires action. Confusing the two is dangerous. A vitamin D level within the laboratory reference range might still be insufficient for a patient with osteomalacia. A troponin result below the 99th percentile reference limit doesn't rule out myocardial infarction in a symptomatic patient. These distinctions matter because someone's treatment plan depends on them. I've seen junior scientists flag every result outside a reference interval without considering clinical context. That's not wrong. It's just incomplete. Good biomedical science requires knowing when to escalate, when to repeat, and when to suggest clinical correlation. The lab report is not the final word. It is input into a larger diagnostic process.
What The Textbooks Leave Out
Most courses cover the major analytical techniques. Spectrophotometry, chromatography, immunoassays, molecular methods. They explain the theory adequately. What they rarely cover is the maintenance burden. Columns degrade. Lamps dim. Reagents hydrolyse. Calibrators expire. I replaced a mass spectrometer source every eight months because the clinic processed a high volume of LC-MS/MS toxicology samples. The manufacturer's recommended interval was twelve months. Real-world usage doesn't match recommended usage. Staffing is another gap. The principles assume competent personnel performing standardized procedures. In practice, labs run with tight rosters, sick cover, and training gaps. I've seen senior technicians stretch a single day to cover two sections because the float pool wasn't available. Fatigue leads to transcription errors. Transcription errors lead to wrong results. The principle is sound. The execution is fragile.
A Practical Approach To Learning This Field
If you are studying Principles Of Biomedical Science, spend time in the lab alongside the theory. Every principle makes more sense when you have seen it fail and fixed it. Learn to read instrument flags. Understand what triggers a hemolysis index, an icterus index, a lipemia index. These indicators are early warnings that your result may be compromised before you even see the number. Keep a troubleshooting log. Write down every anomaly you encounter, what you suspected, what you tested, and what the root cause turned out to be. After a year, you will have a personal reference guide that no textbook can match. I still use mine occasionally. Patterns emerge that you wouldn't notice otherwise.

Limitations You Need To Accept
No analytical method is perfect. Every test has a known range of uncertainty. Reporting uncertainty properly is a requirement under ISO 15189 but many labs handle it inadequately. A hormone level reported as 45 pmol/L with a reference interval of 30 to 60 might carry an expanded uncertainty of fifteen percent. That means the true value could reasonably sit anywhere between thirty-eight and fifty-two. Whether that matters depends entirely on how close the result is to a decision limit. Point-of-care testing introduces additional variability. The same glucose measured on a bedside meter and in the central lab can differ by ten to fifteen percent. Guidelines account for this but clinicians sometimes treat them as interchangeable. They are not. Understanding the limitations of each method is part of responsible practice. The field is changing. Automation handles more of the routine work. Artificial intelligence assists with pattern recognition in haematology screens and urinalysis. These tools reduce manual workload but they don't eliminate the need for human oversight. Algorithms make mistakes too. I reviewed an AI-flagged morphology screen that missed a rare blast cell because it fell outside the training dataset's distribution. A trained eye caught it during a second look.
Where To Find More Resources
The Institute of Biomedical Science publishes extensive guidance documents and a journal that covers practical issues beyond academic theory. The Royal College of Pathologists produces quality guidelines that are directly applicable to lab work. Online courses from recognized institutions can fill gaps in formal education. There is no single downloadable resource that covers everything because the field is too broad and too context-dependent for that. The best material is scattered across standards, textbooks, and the accumulated experience of people who have spent years in the lab. The principles themselves are not complicated. Applying them consistently under real conditions is what takes experience. That is the honest answer.


