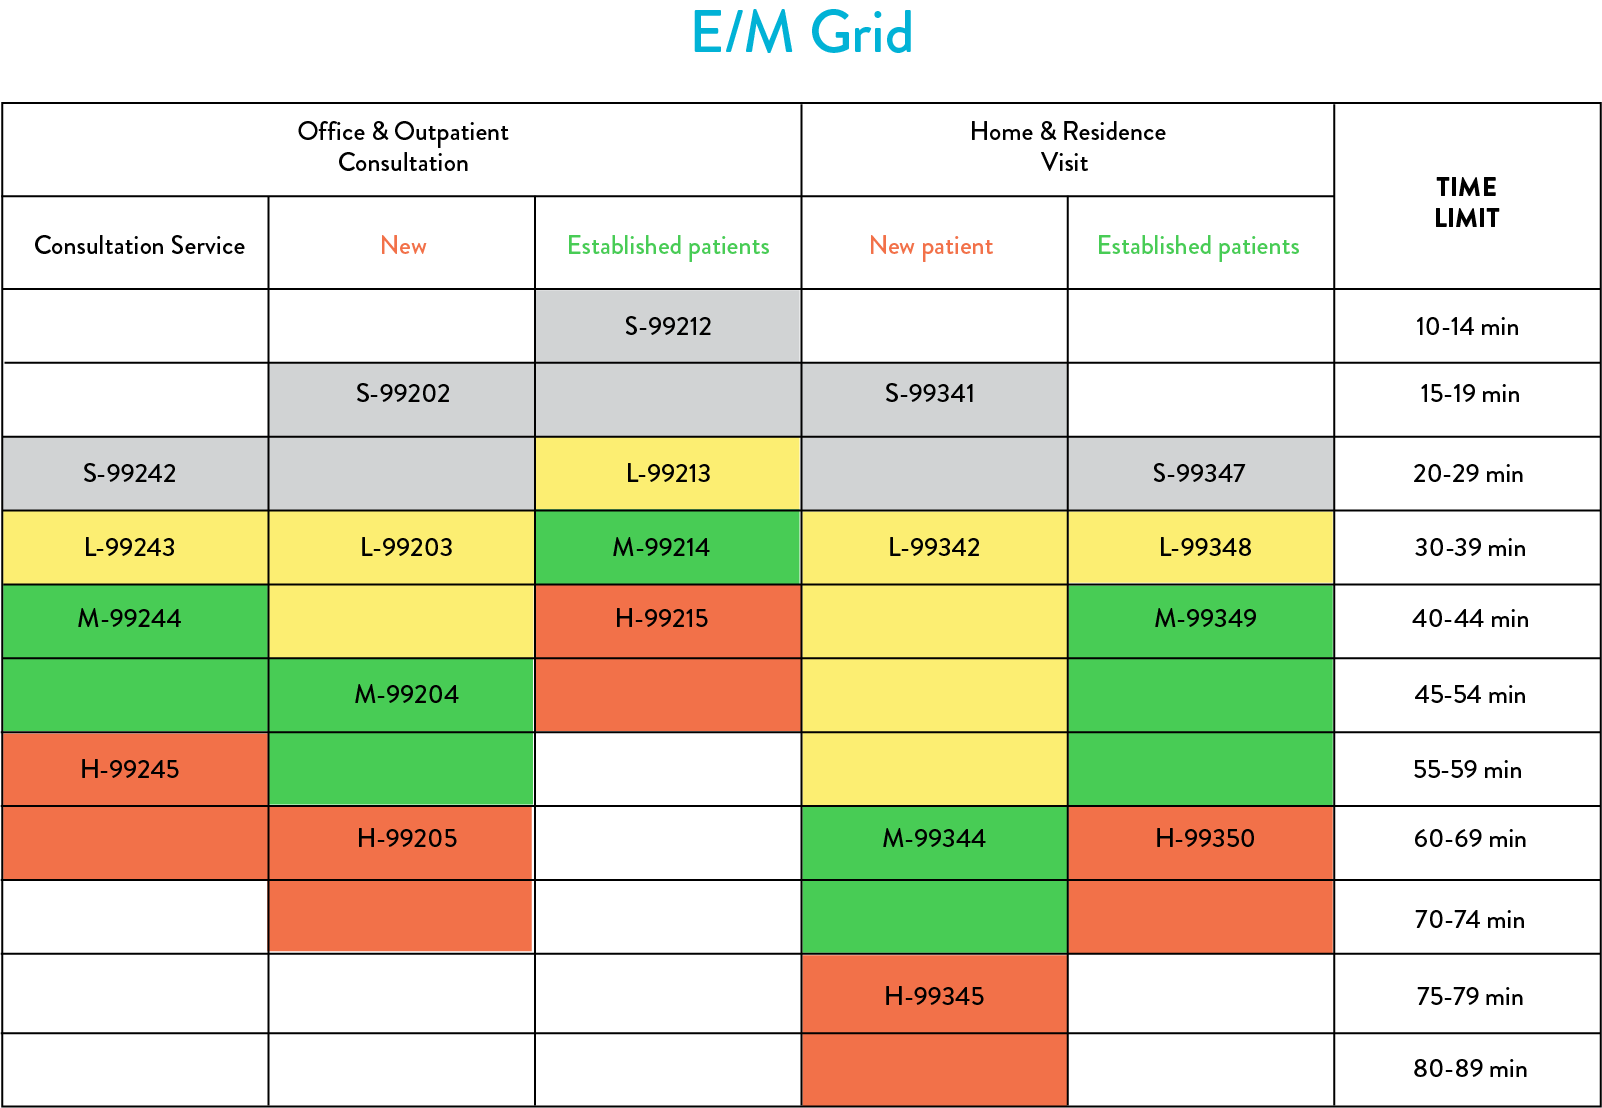
Printable Evaluation And Management Coding Cheat Sheet
Verma
2026-08-23
The Problem With E/M Coding Cheat Sheets
Most printable evaluation and management coding cheat sheets you'll find online are garbage. They summarize the 2023 E/M updates correctly but then leave you hanging on the parts that actually matter in real practice. Like how the time threshold for prolonged services shifted to 30 minutes beyond the total time for E/M codes, or which documentation elements actually survive audit season. I spent three years in audit defense before I stopped buying pre-made sheets and started building my own.
The first one I made back in 2019 covered everything from the old history/exam/MDM framework through the transition year. It was a mess. The 2021 and 2023 revisions to the E/M guidelines changed the game enough that carrying a 2019 version into an audit is basically volunteering for a billable error. That's why I keep a current
Printable Evaluation And Management Coding Cheat Sheet
on my desk at all times, and I update it every time CMS publishes a new guidance document.
What Actually Matters in These Sheets
A useful E/M cheat sheet needs to cover three things in sequence: code selection, documentation requirements, and the time calculation. Most sheets get the first two right and fumble the third. Time is where the audits happen.
For office visits, the decision is between total time and MDM. Pick whichever yields the higher level. That's it. But the tricky part is knowing what counts toward total time. Only time spent on the date of the encounter counts. That includes reviewing orders, documenting, ordering tests, and talking to other clinicians. It does not include time spent on paperwork that gets filed after the patient leaves. I learned this the hard way when a Medicare audit in 2020 flagged a pattern where we'd been billing time for documentation completed at the end of the day rather than during the encounter window. The workaround was straightforward — I added a clock-in reminder at the top of the template that says "start your timer now, not later."
Here's a nuance most cheat sheets miss: counseling and coordination of care during an E/M visit count toward total time regardless of whether they're the primary reason for the visit. If you spend 25 minutes explaining a treatment plan for diabetes and the visit clocks in at 38 minutes total, you're at least a level 4. That's been consistent since the 2021 revision, but a lot of coders still default to MDM-first thinking and undervalue the time component.
Building Your Own Sheet
I use a single-page layout with three sections. The left column has the E/M code table with the total time ranges and MDM complexity thresholds. The middle column has the prolonged services note — 30 minutes beyond the lowest eligible time increment, not a flat 30 minutes from the start of the visit. The right column has the high-risk medication reconciliation checkbox and the chronic care management cross-reference.
The specific problem I ran into that forced me to redesign the sheet involved opioid prescribing documentation. Our clinic was billing E/M codes alongside opioid risk assessments, and the auditor wanted to see that the assessment was documented within the same encounter, not referenced from a separate form. I added a small section at the bottom that maps the chronic disease management elements onto the MDM table so you can see at a glance which elements double as risk assessment documentation.
For the template itself, I set up a Google Doc with conditional formatting. When I update it for a new year's guidance change, I just adjust the color codes and print a fresh batch. The current version runs about $12 to print in bulk on our clinic's laser printer. Paper quality matters — I use 24-pound bond because the thinner stuff smudges when you're filling it out with a ballpoint pen during a busy clinic day.
Pitfalls That Actually Cost Us Money
Level 5 under the new guidelines requires high-complexity MDM or 60+ minutes of total time. High complexity MDM demands data points from at least two distinct sources. The catch is that the data sources need to be clearly identifiable in the note. Listing "labs ordered" isn't enough. You have to specify what was ordered and where it came from. An audit of our practice in 2023 found that three of our five star-rated level 5 encounters had insufficient data source documentation. The fix was adding a mandatory data sources line to every E/M note template.
Another issue is the crossover between E/M and procedure coding. If you're doing a minor procedure in the same visit as an E/M, you need a separately identifiable E/M service and you need to append modifier 25. Most cheat sheets mention this in passing. The practical reality is that payer policies vary wildly on what qualifies as separately identifiable. Medicare is stricter than commercial payers on this point. I keep a separate one-page addendum for modifier 25 documentation requirements that I tuck behind the main sheet.
The honest limitation of any printable cheat sheet is that it can't handle ambiguous cases. When the patient's condition doesn't cleanly fit the MDM table, or when the time threshold falls in that awkward gray zone between levels, you're going to need clinical judgment, not a laminated card. That's why I don't recommend relying on these sheets as the sole reference. They're speed tools for the routine stuff. The edge cases still require going to the full CMS guidelines or consulting a certified professional coder.
Where to Get One
If you want something current and accurate, the AMA publishes an official E/M coding quick reference that gets updated annually. It's not free, but it's reliable. For a free option, the AAPC forum has community-maintained sheets that tend to be more current than the generic health system templates. I use a hybrid approach — the AMA sheet for the code tables and my own additions for the procedural crossover documentation.
Gallery Printable Evaluation And Management Coding Cheat Sheet
Printable Evaluation And Management Coding Cheat Sheet - Printable Calendars AT A GLANCE
Printable Evaluation And Management Coding Cheat Sheet
Printable Evaluation And Management Coding Cheat Sheet - Printable Sight Words List
Printable Evaluation And Management Coding Cheat Sheet
Printable Evaluation And Management Coding Cheat Sheet