Why nurses actually use these sheets during med-surg shifts
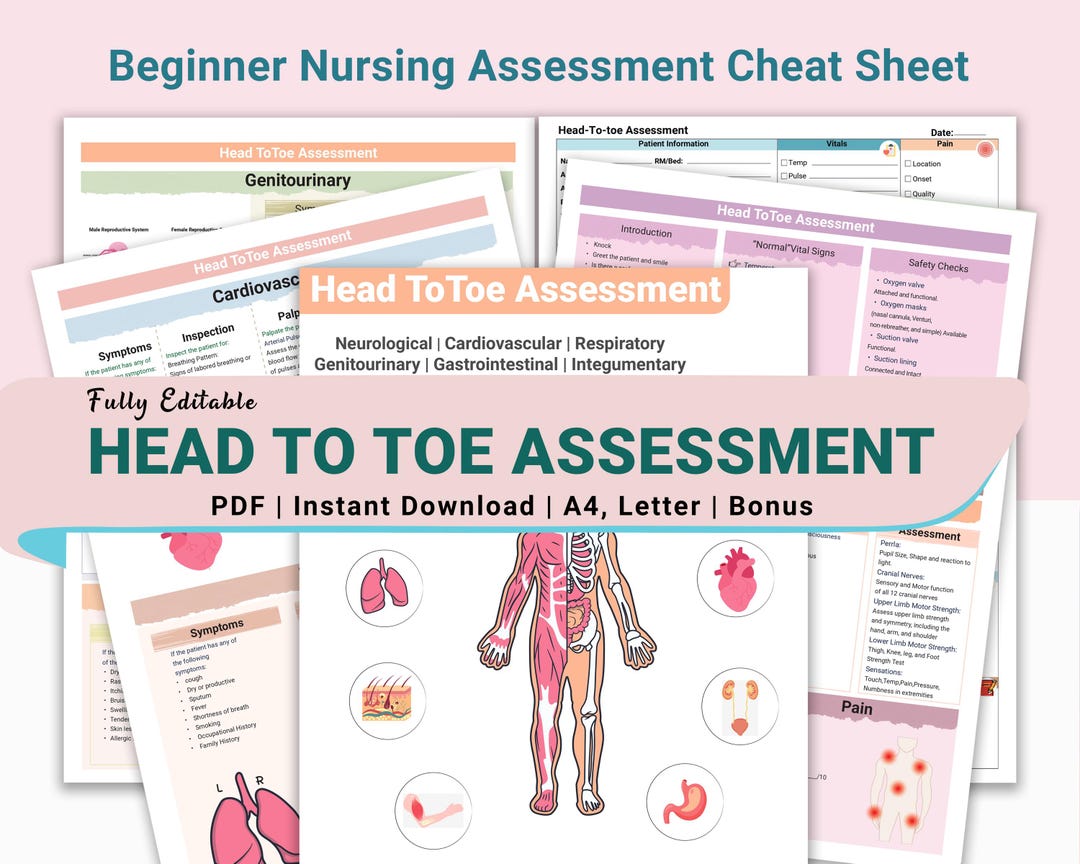
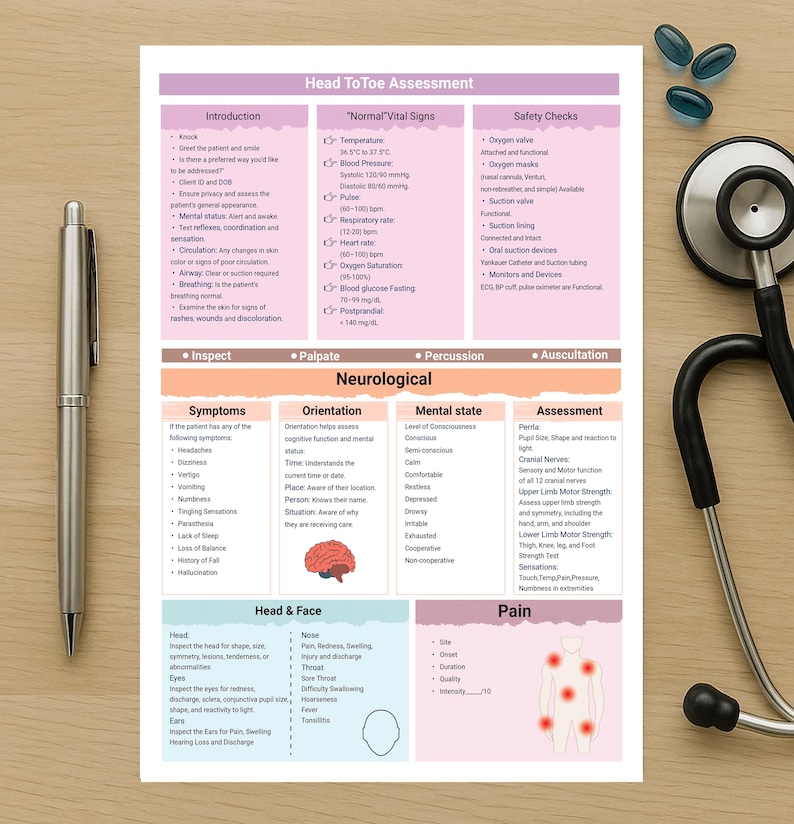
A Printable Nursing Assessment Cheat Sheet is essentially a laminated reference that cuts your head-to-toe assessment time down from twelve minutes to under four. I built mine out of necessity during my third year on the floor when I was covering two float patients and a newly post-op admit simultaneously. The version hanging in the med-surg bay at my hospital gets used about six times per shift by different nurses on the unit. It is not a substitute for your clinical judgment, but it does stop you from forgetting to check pedal pulses on a cardiac admit or missing a decubitus ulcer in the sacral area because you rushed through the skin portion. Start by mapping the exact assessment framework your facility requires. Most hospitals follow a modified head-to-toe or ABCDE structure, and the last thing you want is a sheet that uses Glasgow Coma Scale categories your unit does not recognize. I learned that the hard way when I printed one from a nursing student forum and spent twenty minutes realizing it did not include a urine output column—something we chart per hour on the telemetry floor. The practical workflow is straightforward. Find a template that matches your unit's order set. Add columns for baseline vitals, current vitals, change indicators, and a notes field. Keep it to one side of an 8 by 11 sheet so you can scan it without unfolding. Laminate it or put it in a pocket sheet protector. Write the headers with a fine-point Sharpie. The marker lasts longer than ballpoint when you are holding the sheet one-handed while starting an IV.
If you want something ready-made, search for a Printable Nursing Assessment Cheat Sheet from a credible source like a university nursing skills page or an affiliated hospital's education department. Avoid the free PDFs that get reposted on random blogs because those often skip neuro checks or include outdated pain scale terminology. I keep a folder on my phone with three verified versions and swap in whichever one my current charge nurse prefers for the shift.
How to actually use the sheet without turning it into paperwork theater
The biggest mistake I see is nurses treating the cheat sheet as a documentation form rather than an assessment aid. It should guide your physical exam, not replace it. Use the sheet to track what you find, not to generate findings on demand. When I walk into a room, I glance at the sheet first to recall the sequence, then I go line by line while I am with the patient. I do not go back to the station after every room to fill it out. That is how you end up with charting that looks perfect but reflects what you remember, not what you actually assessed. I developed a personal workaround for a specific problem that came up during a flu surge when we were short-staffed and I had four new admits in a single hour. The cheat sheet was taking too long to complete because I kept stopping to verify whether a finding was new or baseline. I added a small legend in the corner with abbreviations for common baselines: PMH for past medical history items that are expected, CBD for chronic but currently stable findings, and STAT for anything that required immediate action. That saved me roughly eight minutes per assessment over a twelve-hour shift. It is not glamorous, but charting accuracy improved because I stopped guessing on instead of looking it up mid-documentation. Here is a counter-intuitive point that most beginner guides miss: the cheat sheet works best when you keep it slightly incomplete. Do not pre-fill normal values. If you write 98.6 throughout every column, you will subconsciously assume everything else is normal too. Leaving the vitals column blank forces you to actually measure and record rather than copy the last set from the flow sheet. That one habit caught a hypotensive drop on my unit last spring that would have been missed if I had just written in the numbers from the nurse's station board.
Get the Full Details
Common pitfalls that make these sheets useless
There are three scenarios where a Printable Nursing Assessment Cheat Sheet actively fails you. First, when the patient has complex comorbidities that require specialty assessments beyond a general med-surg framework. A cheat sheet designed for general admission will not cover a post-cardiac surgery chest tube check, a stroke neuro series, or a burn unit wound measurement. In those cases, the sheet becomes cluttered noise. Use a unit-specific supplemental sheet alongside the general one instead of trying to cram everything onto a single page. The second pitfall is template rigidity. I worked a weekend shift where our charge nurse switched from a flow-sheet-based charting system to a narrative notes system without warning. My printed cheat sheet had checkboxes and drop-down columns that did not map to the new format. We adapted by using the same sheet for assessment tracking but switching to narrative for documentation. The cheat sheet stayed useful, but only because I decoupled it from the charting method rather than letting it dictate how I recorded data. The third limitation is the most blunt one: these sheets do not teach assessment skills. They organize them. If you do not know how to auscultate bowel sounds or palpate a pulse accurately, a laminated card will not fix that. I have seen new grads rely on the sheet as a crutch and then panic when a patient presents with an atypical finding that is not on the list. The sheet is a checklist, not a clinical reasoning tool. Use it to maintain consistency across assessments, not to replace your training.
The workaround I recommend is pairing the cheat sheet with a brief verbal debrief after each complex assessment. Tell a coworker what you found and why. That process surfaces gaps in your understanding faster than any template can. I do this with my preceptees when they are still building confidence. It takes three minutes and it is more effective than adding another column to the sheet.
What makes one sheet better than another
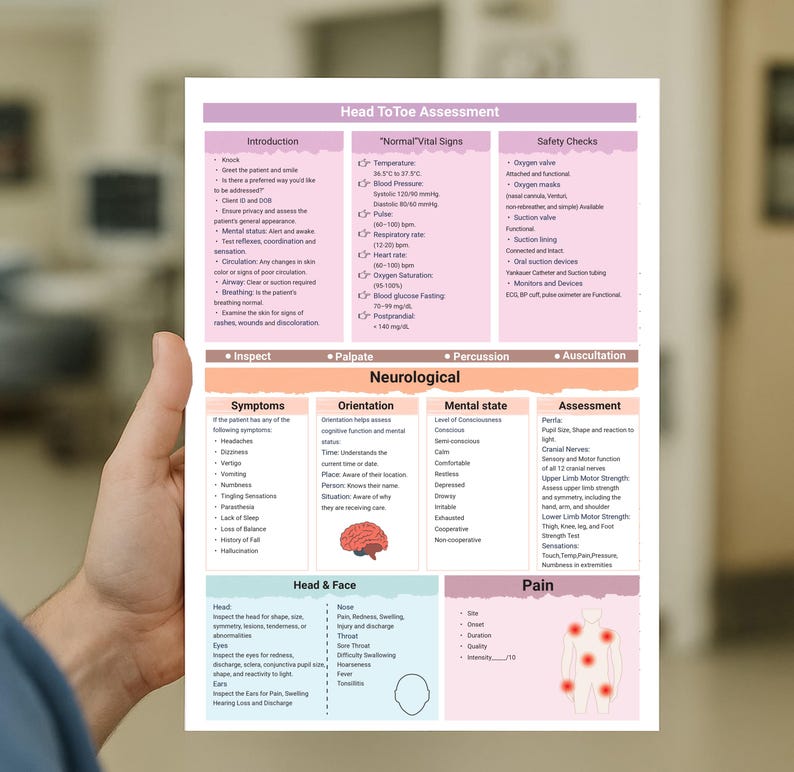
Not all Printable Nursing Assessment Cheat Sheet resources are equal. The ones worth using share three traits: they are aligned with a recognized nursing framework like Gordon's Functional Health Patterns or a standard head-to-toe sequence, they leave room for clinical notes rather than forcing checkbox compliance, and they are updated to reflect current evidence-based practice. Outdated sheets still list findings like reflex ankle clonus as a routine screening item when current guidelines recommend it only for specific neurological indications. That kind of obsolete content wastes assessment time and can lead to false positives that trigger unnecessary interventions. A good sheet includes a quick reference section for normal ranges by age group. Pediatric vital sign norms are different enough from adult norms that mixing them up is a real risk on a float assignment. I once floated to a pediatric step-down unit and nearly documented adult baseline ranges on a teenager's sheet before catching the error. Adding a small age-based norm table to the bottom of my personal sheet eliminated that problem entirely. It added one extra line to print but prevented a documentation discrepancy that would have required a chart correction later. For sourcing, the most reliable options are nursing education departments at teaching hospitals, professional organizations like the American Association of Critical-Care Nurses for specialty sheets, and accredited continuing education platforms. Steer clear of sites that require email registration to download a basic assessment template. That is usually a lead-generation tactic, and the sheet itself tends to be generic filler. I found my current working version by downloading a skills checklist from a state nurse practice website and adapting it to our unit's format. It took about twenty minutes and has not needed a major update in three years.

When to stop relying on the sheet and start trusting your assessment
There comes a point where carrying the cheat sheet becomes redundant for experienced nurses. I stopped using mine for routine overnight checks on stable patients after about eighteen months on the unit. The sequence was internalized. The sheet still hangs in the med-surg bay for new float nurses, students, and assessments on patients I do not know well. Keeping it accessible is a safety net, but continuing to pull it out for every single admission after you have mastered the rhythm is a sign you have not fully integrated the skill yet. The sheet remains essential when you are covering an unfamiliar patient population or rotating to a new unit. I used mine extensively during my first week on the oncology floor because the assessment priorities differed from med-surg. Mucositis checks, port site evaluations, and neutropenic precautions are not part of a general admission sheet. A specialized Printable Nursing Assessment Cheat Sheet for oncology would have been useful there, but my general sheet still helped me stay organized during the transition even though it required adaptation. The bottom line is that a well-designed assessment cheat sheet reduces cognitive load during high-acuity shifts and provides a consistent framework for less experienced nurses. It is not a magic solution, it has clear limitations with complex or specialized populations, and it will not compensate for weak foundational skills. Use it as a structured aid, adapt it to your unit's actual requirements, and retire it from your pocket once the assessment sequence becomes automatic. That is how it functions in practice without becoming clutter or false security.