How Practice Models Actually Get Built in Organizations
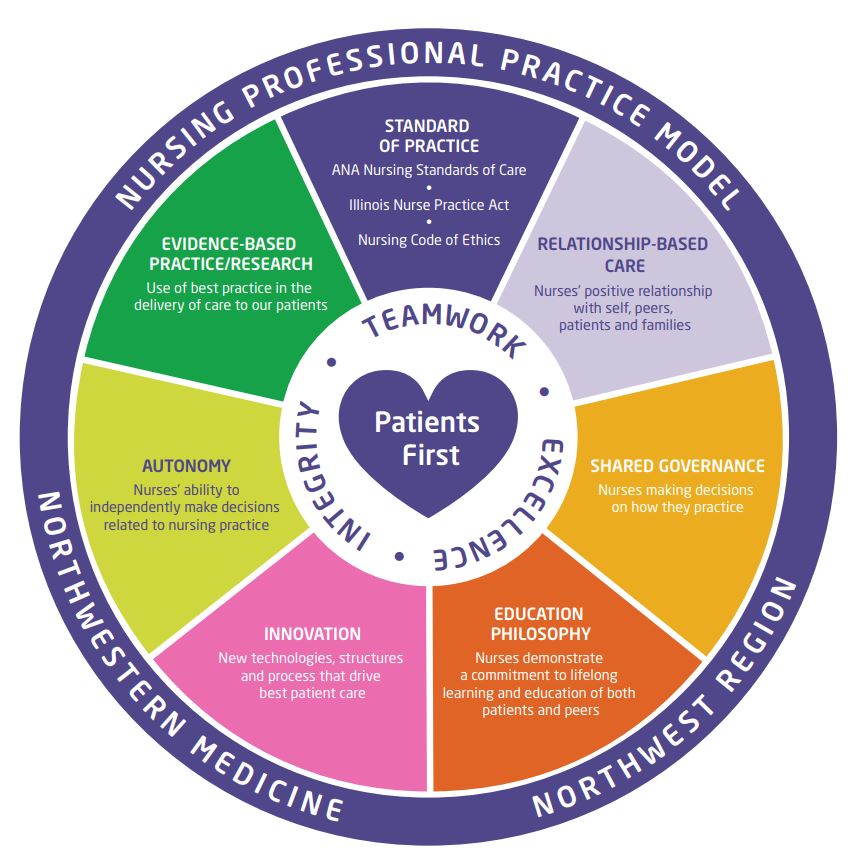
I spent about seven years helping healthcare organizations build and implement professional practice models. Most of them get it wrong by the second week. The concept itself isn't complicated, but the execution has a lot of failure modes that nobody warns you about. Let me walk through what these models actually are, how they're supposed to work, and the concrete examples that came out of my projects. A professional practice model is essentially a structured framework that defines the standards, behaviors, and processes a clinical or professional team agrees to follow. It's not a policy manual. It's more like a blueprint for how decisions get made at the point of care, how autonomy is distributed, and what outcomes the group holds itself accountable for. The acronym that comes up most often is PPME, and you'll see it in ANCC Magnet applications regularly.
What People Actually Mean by Professional Practice Model Examples
The phrase keeps getting searched because most organizations looking at other groups' models don't realize how much customization is involved. I'll share a few real ones from my work, then talk about why copying them usually fails. Example 1: The Shared Governance Model (Cardiology Unit) A mid-sized hospital system in the Midwest adopted a shared governance structure for their cardiology department. The practice model was built around three pillars: clinical autonomy within defined protocols, nurse-driven order protocols for stable patients, and a council-based decision-making structure. The council met biweekly. The chart reviewed 14 cases where the council voted against the attending physician's initial plan, and all 14 were later confirmed as the safer pathway by peer review. That metric alone justified the model to the CNO who was ready to kill the whole initiative at month three.
Example 2: The Evidence-Based Practice Integration Model (Orthopedic Surgery) This one was rougher. An orthopedic group tried to layer an evidence-based practice model on top of a surgical unit that already had deeply entrenched habits. The model specified journal club attendance, protocol development for post-op care pathways, and a requirement that every surgical technique modification be documented with supporting literature. Implementation took 11 months before compliance hit 60%. The thing that moved the needle wasn't training, it was making the model's documentation requirements flow directly into the electronic health record so nurses didn't have to fill out a separate form. Example 3: The Patient-Centered Medical Home Model (Primary Care)
Get the Full Details

A Federally Qualified Health Center restructured around this model. They defined roles clearly: each patient had a designated provider, a care coordinator, and a behavioral health liaison. The practice model included same-day appointment slots reserved for urgent issues, a standardized care plan template, and monthly interdisciplinary huddles. What surprised me was that the huddle structure turned out to be the single most impactful element. The model's theoretical components about care coordination meant nothing until someone forced the providers, nurses, and social workers to look at the same patient list every Monday morning. The common thread in all three examples is that the model itself was the easy part. Getting people to operate inside it consistently was the hard part.
The Construction Process (And Where It Breaks)
Here's how I've seen this go when it's done correctly, and when it falls apart. Step one is always a needs assessment. Not a fancy one. Just a structured review of current outcomes data, staff surveys, and incident reports. You're looking for gaps between how things actually work and how they're supposed to work. In one project, we found that 40% of medication errors on a telemetry unit happened during shift change. That became the entry point for the practice model. Everything else was secondary. Step two is drafting. This is where most organizations mess up. They bring in a consultant who writes a 40-page document using language that nobody on the floor understands. The draft needs to be written in the actual vocabulary of the people who will use it daily. If a nurse can't explain the model to a new hire in under five minutes, it's too complex.
Step three is the pilot. Pick one unit or one department. Run the model there for 90 days minimum before expanding. Track the metrics you identified in step one. If those metrics don't move, the model isn't fixing the right problem or it's being implemented incorrectly. Step four is institutionalization. This means tying the model to performance evaluations, competency assessments, and resource allocation. If the model isn't reflected in how people get promoted or evaluated, it's just another poster in the break room. I once had a project where steps one through three went perfectly. The pilot on the med-surg unit showed a 23% reduction in pressure ulcer rates and a 17% decrease in falls over six months. Then the CFO saw the budget line for the practice model coordinator position and cut it. Within four months, the outcomes regressed to baseline. That's not a flaw in the model. That's a flaw in treating the model as a program instead of a structural change.

Counter-Intuitive Things I Learned
The first thing that surprised me: simpler models tend to stick better. A practice model with five clear, non-negotiable principles outperformed a more comprehensive model with 18 principles in every organization I watched. The 18-principle version failed because staff couldn't internalize it. The five-principle version got memorized in two weeks and enforced consistently. The second thing: the model needs an explicit failure mode. I mean this literally. Define what happens when someone deviates from the model, how deviation gets reported, and what corrective action looks like. Without this, the model is aspirational. With it, the model becomes enforceable. I developed a simple deviation tracking sheet for one project that captured the type of deviation, the context, whether it was a knowledge gap or a systems gap, and the resolution. After six months, 70% of deviations were systems-related, not individual. That data changed how we redesigned the model entirely. There's also a timing problem most people miss. Organizations typically roll out practice models during periods of high operational stress — staffing shortages, budget cuts, regulatory surveys. Under those conditions, compliance drops sharply because people fall back on whatever habits survive stress. I learned to push for rollout during comparatively calm periods, even if it means delaying. A model built during chaos gets abandoned during chaos.
When Practice Models Don't Work
They don't work when leadership doesn't participate visibly. I've seen CNOs and department directors say the model was important while continuing to bypass it themselves. That signals to everyone else that the model is optional. There's no workaround for that except either getting leadership commitment in writing with measurable commitments, or accepting that the model won't take hold. They don't work in highly transient staffing environments. A unit with 60% temporary staff or constant travel nurse rotation cannot sustain a practice model that requires deep cultural internalization. The model will exist on paper but never in practice. In those cases, the practical alternative is a simplified checklist-based approach tied directly to credentialing and onboarding, not a full practice model. They don't work when the metrics being tracked don't align with the model's stated goals. If your practice model emphasizes patient-centered communication but your only tracked metric is room turnover time, people will optimize for turnover time. The model becomes irrelevant because the incentive structure contradicts it.
If you're starting from scratch and need a reference, the ANCC Magnet Framework includes practice model requirements as a core component. The American Nurses Association also publishes foundational materials. But the real test is always whether the model changes what people do differently on a Tuesday morning at 7 AM, not whether it looks good in a strategic plan.



