What progesterone therapy actually does in PCOS
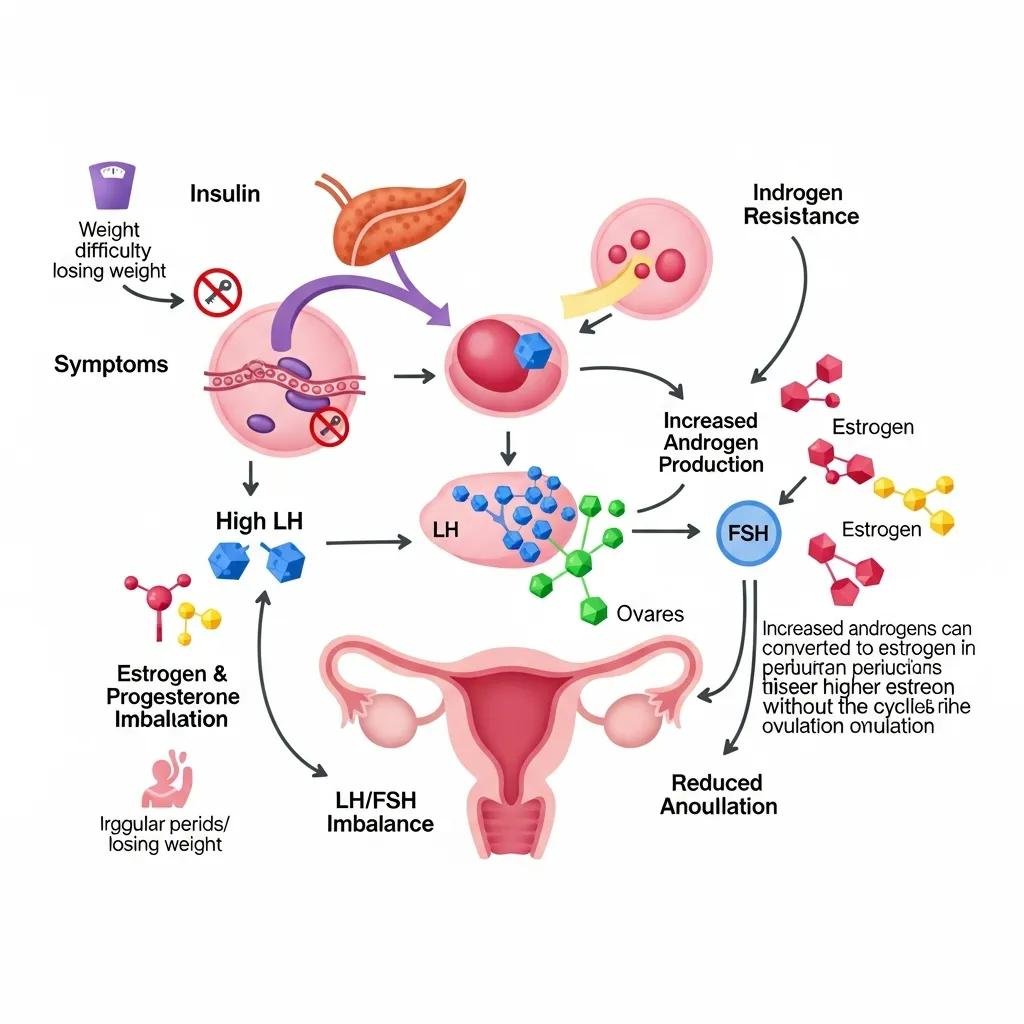
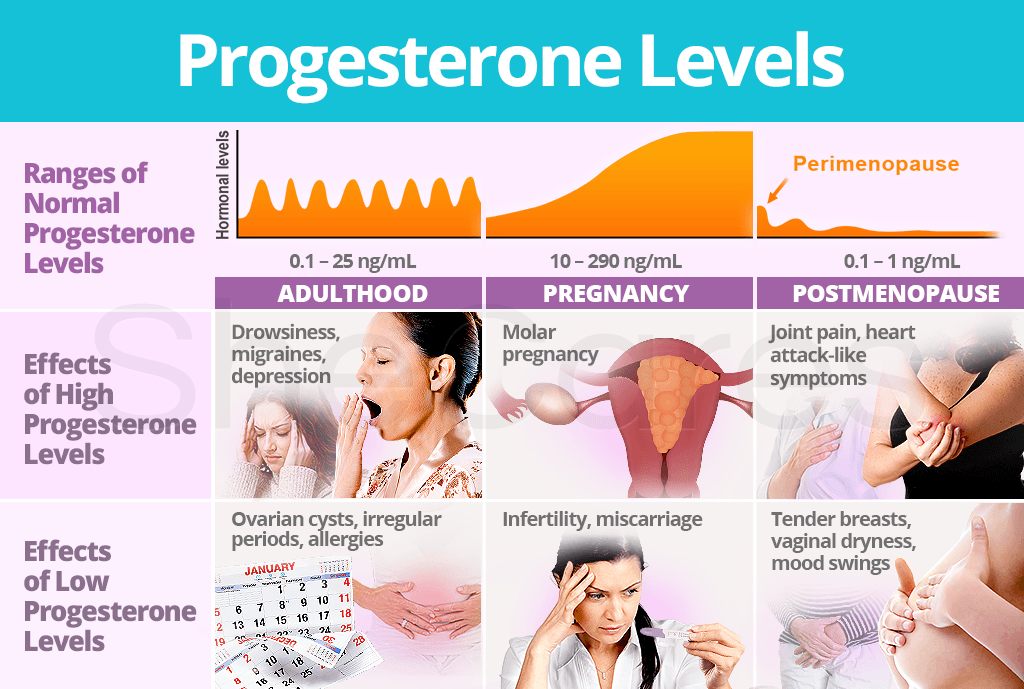
Most people hear about progesterone for PCOS and assume it fixes the underlying hormonal problem. It doesn't. Progesterone is a symptom manager, not a cure. Its primary role is protecting the uterine lining from the continuous estrogen exposure that happens when you aren't ovulating regularly. Without ovulation, you don't form a corpus luteum. Without a corpus luteum, you don't produce progesterone. So your endometrium keeps thickening under unopposed estrogen, and that is the mechanism that leads to hyperplasia and, in rare cases, progression to endometrial cancer. Cyclic progesterone interrupts that process by triggering a withdrawal bleed roughly once a month.The two main approaches are cyclic therapy and continuous therapy. Cyclic therapy means taking progesterone for 10 to 14 days each month, then stopping it and waiting for a bleed. Continuous therapy means taking a low dose every day, usually in combination with estrogen, to prevent endometrial buildup altogether. Cyclic is more common for women who are not actively trying to conceive and still have some endogenous estrogen. Continuous combined is more typical for perimenopausal women or those who cannot tolerate monthly withdrawal bleeds. Here is the protocol most clinicians use for cyclic therapy. Medroxyprogesterone acetate, commonly known as Provera, comes in 5 mg or 10 mg tablets. The standard dosing is 10 mg daily for 10 to 14 days. You take it at the same time each evening because drowsiness is a real side effect, and taking it at night prevents you from feeling drunk during the workday. Drospirenone, the progesterone component in Yaz or Beyaz, is sometimes used off-label at 4 mg daily for 14 days per month, though it is FDA-approved for PCOS only as part of the combined oral contraceptive pill, not as standalone progesterone therapy. Micronized progesterone, sold as Prometrium, is another option at 200 mg daily for 14 days, and it is bioidentical, which matters if you are sensitive to synthetic progestins. The bleed should arrive within 2 to 7 days after you stop the progesterone. If it does not arrive within 14 days, you take a pregnancy test first. I have seen this confuse people repeatedly. When the bleed fails to show up, it is usually either pregnancy or a very thin endometrium that has nothing to shed. If the lining is thin because estrogen levels are low, adding more progesterone will not fix the problem. That is when you need to reconsider whether PCOS is the actual diagnosis or whether there is a separate hypothalamic or thyroid issue complicating things.
The counter-intuitive thing nobody tells you is that progesterone does not regulate your cycle in any meaningful way. It creates an artificial bleed, not a natural ovulatory cycle. People confuse withdrawal bleeding with a period. It is not the same thing. A real period follows ovulation. A withdrawal bleed follows progesterone cessation. If you are hoping progesterone will restore regular ovulation, you are looking at the wrong medication. Metformin, letrozole, or lifestyle intervention are what address ovulation. Progesterone just cleans up the mess the missing ovulation leaves behind. Another thing that catches people off guard: progesterone has zero effect on the androgen symptoms of PCOS. It will not reduce hirsutism, clear acne, or slow hair loss. If your main concern is excess androgens, you need spironolactone, finasteride, or a combined oral contraceptive with an anti-androgenic progestin like drospirenone or desogestrel. Progesterone alone does not touch testosterone or DHT. I had a patient who took cyclic progesterone for eight months and was furious when her acne did not improve. She thought she was being treated for PCOS broadly. She was not. She was being treated for endometrial protection specifically. Here is an edge case that took me weeks to figure out. A patient on continuous low-dose medroxyprogesterone for endometrial protection started experiencing spotting between scheduled bleeds. Not heavy bleeding, just consistent brown discharge for three weeks straight. We checked the endometrial thickness via transvaginal ultrasound and it was 3 mm, which is thin. The spotting was not coming from hyperplasia. It was coming from the medroxyprogesterone itself destabilizing the already-thin endometrium. The workaround was switching her to micronized progesterone 200 mg cyclically instead of continuous medroxyprogesterone. The spotting stopped within two cycles. Bioidentical progesterone has a different receptor binding profile than synthetic progestins, and for some women with thin linings, that difference matters enough to change the side effect picture entirely.
There are downsides worth being blunt about. Weight gain is reported by a notable percentage of patients on medroxyprogesterone, though the data is messy and hard to separate from PCOS-related metabolic changes. Mood changes are more common with synthetic progestins than with micronized progesterone. If you have a history of depression or anxiety, start with Prometrium and monitor closely. Breakthrough bleeding is the most frequent complaint, especially during the first three months of continuous therapy. Most patients adapt, but some do not, and switching formulations usually resolves it. Progesterone therapy does not improve insulin resistance. It does not lower LH levels. It does not reduce ovarian volume. It protects the endometrium and nothing else in the PCOS treatment hierarchy. If you have not had an endometrial biopsy or transvaginal ultrasound to check lining thickness before starting, you should. Starting progesterone without knowing your baseline endometrial status is careless. A thick lining on ultrasound means you might need a diagnostic D&C before you begin cyclic progesterone, because you do not want to trap abnormal tissue inside while pretending to manage it with a monthly bleed. The evidence for progesterone in PCOS is solid for endometrial protection and weak for everything else. Cochrane reviews and ACOG guidelines support its use for preventing hyperplasia in anovulatory women. They do not recommend it as a primary treatment for PCOS itself. That distinction matters because patients walk out of clinics thinking they are being treated for their condition when they are actually being treated for one complication of their condition. Neither is bad. But confusing the two leads to unrealistic expectations and unnecessary frustration when the hair growth and irregular cycles persist despite "treatment."
Get the Full Details

If progesterone therapy is not appropriate for you, the alternatives depend on why. If you cannot tolerate any form of progesterone due to mood side effects, a levonorgestrel IUD provides local progestin exposure to the endometrium with minimal systemic absorption. It thins the lining effectively and eliminates the need for oral cycling. If your concern is infertility and you want to ovulate, letrozole is the first-line pharmacologic option. If metabolic dysfunction is the dominant issue, weight loss and metformin address root causes that progesterone never touches. The right treatment depends entirely on which PCOS symptom you are prioritizing. Progesterone is not optional if you go more than 90 days without a bleed and you are not pregnant. That is the clinical threshold most guidelines agree on. Beyond 90 days of anovulation, the risk of hyperplasia increases measurably. The prescription itself is straightforward, but the decision-making around it is where most people get confused. Know what you are treating, know what the medication will not treat, and go in with realistic expectations instead of hoping a single drug will reorder your entire hormonal system.