Understanding How Food Actually Moves Through Your System
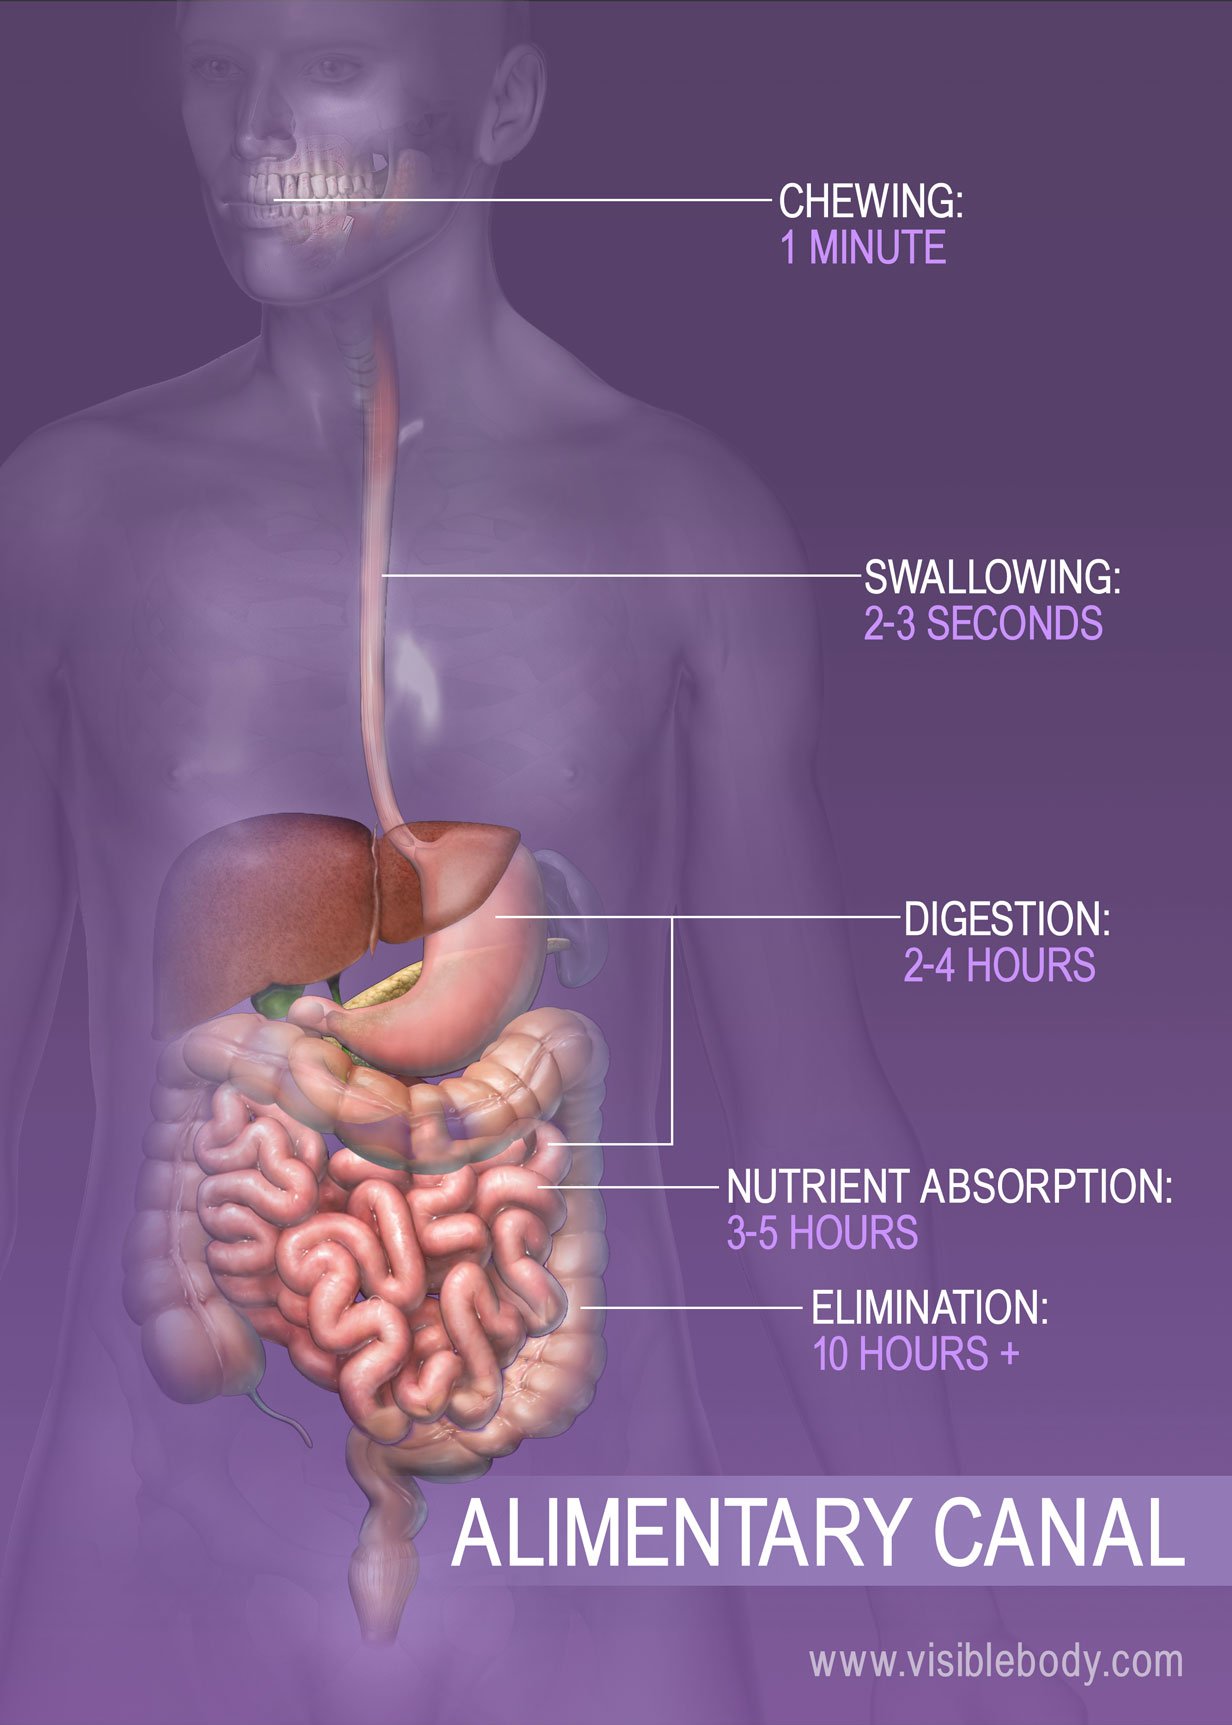
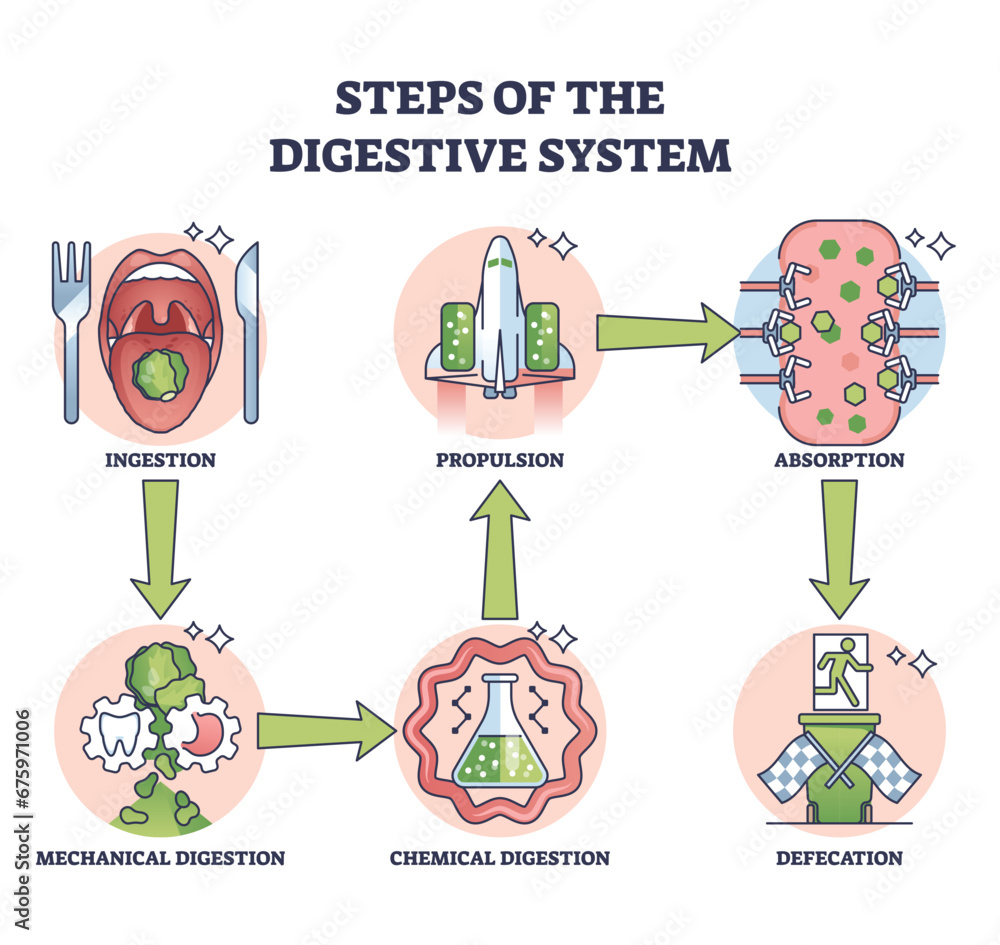
Most people think digestion starts in the stomach. It doesn't. The real work begins the moment you swallow, and if propulsion slows down anywhere along the line, everything downstream gets messy. I spent years watching this process fail in clinical settings, and the patterns are predictable once you know what to look for. Propulsion refers to the coordinated muscular contractions that push food boluses, chyme, and eventually waste through the entire gastrointestinal tract. It operates via two mechanisms: peristalsis, which is the primary propulsive force, and segmentation, which mixes contents but also contributes to forward movement. The esophagus uses both striated and smooth muscle, while the rest of the tract relies entirely on smooth muscle controlled by the enteric nervous system, sympathetic input, and parasympathetic pathways. The myenteric plexus, located between the circular and longitudinal muscle layers, is the main coordinator. It sends signals that create a wave of contraction behind the bolus and relaxation ahead of it. This happens continuously, even during fasting, in what's called the migrating motor complex. That's why skipping meals doesn't give your gut a rest—it just changes the rhythm.
How It Works Under Normal Conditions
Swallowing initiates the process. The upper esophageal sphincter opens, the bolus enters the pharynx, and the primary peristaltic wave pushes it downward. If that wave fails to clear the esophagus completely, a secondary peristaltic wave kicks in automatically. I've seen patients with esophageal dysmotility where both waves were weak, and they'd end up with significant residual material after every meal. That's not normal, and it's not something you just live with. In the stomach, propulsion is more about mixing and gradual emptying than rapid transport. The antrum generates strong contractions that push small amounts of chyme through the pylorus. The pyloric sphincter acts as a gatekeeper, allowing only particles smaller than about 2 millimeters to pass. Anything larger gets pulled back into the body of the stomach for further mechanical breakdown. Once in the small intestine, segmentation dominates. This isn't pure propulsion—it's back-and-forth mixing that exposes nutrients to the absorptive surface. But there is also slow, continuous aboral movement driven by the basic electrical rhythm of the interstitial cells of Cajal. These pacemaker cells set the pace for the entire GI tract. In the duodenum, the rate is about 12 cycles per minute. It slows progressively down the tract, reaching roughly 8 cycles per minute in the ileum.
The ileocecal valve prevents reflux from the colon back into the small intestine while allowing chyme to enter gradually. The colon itself moves content through mass peristalsis—strong, propulsive contractions that occur several times a day, usually triggered by the gastrocolic reflex after eating.
Get the Full Details

When Propulsion Fails
I remember a case that stuck with me. A patient in their sixties presented with chronic constipation, bloating, and occasional vomiting. Standard workup showed no mechanical obstruction. We ran a gastric emptying study and a full GI transit study using radiopaque markers. The results showed delayed propagation through the entire colon, but the small bowel was fine. The diagnosis was colonic inertia. We started with polyethylene glycol and bisacodyl, but the real turning point was adding lubiprostone, a chloride channel activator that increases intestinal fluid secretion and enhances propulsive contractions. After about three weeks, transit improved noticeably. She hadn't had a proper bowel movement in months, and within a month she was back to daily. Not a quick fix, but it confirmed that when propulsion is the problem, prokinetics and osmotic agents hit different parts of the same pathway. Common causes of impaired propulsion include diabetic gastroparesis, where hyperglycemia damages the vagus nerve and slows gastric emptying. Opioid use is another major factor—I see this constantly. Opioids bind to mu-receptors in the enteric nervous system, reducing peristaltic activity and increasing sphincter tone. The result is slowed transit throughout the entire tract. Narcotic bowel syndrome isn't just about pain tolerance; it's literally about the gut stopping. Other culprits include hypothyroidism, electrolyte abnormalities like hypokalemia, post-surgical adhesions affecting neural pathways, and conditions like scleroderma where smooth muscle gets replaced by fibrous tissue. In scleroderma, the propulsion mechanism isn't just slow—it's structurally compromised. No amount of prokinetic medication will restore what fibrosis destroys.
Practical Assessment Approaches
If you're dealing with suspected propulsion issues, the first step is always to rule out mechanical obstruction. A CT scan or upper GI series with contrast will show whether food is physically blocked or just moving slowly. I've seen cases where clinicians attributed symptoms to dysmotility when there was actually a stricture or tumor. That mistake delays the right treatment significantly. Gastric emptying scintigraphy remains the gold standard for assessing gastric propulsion. Patients eat a meal labeled with a radioactive tracer, and imaging tracks its passage over four hours. Normal values show less than 10 percent retention at four hours. Beyond that threshold, gastroparesis is likely. For small intestinal and colonic transit, the wireless motility capsule is increasingly common. It measures pressure, pH, and temperature as it travels through the gut, giving you a map of where propulsion is adequate and where it stalls. The alternative is the SmartCap system or radiographic marker studies, but the capsule gives you functional data that static imaging can't provide.
Manometry—specifically high-resolution esophageal manometry—assesses the coordination and strength of esophageal contractions. If you're evaluating chest pain or dysphagia, this test tells you whether the peristaltic wave is present, weak, absent, or spastic. The Chicago Classification system categorizes findings into disorders like achalasia, distal esophageal spasm, or ineffective esophageal motility. Each has a different management approach.

Management Strategies
Dietary modification is always the first line. Small, frequent meals reduce the workload on a sluggish GI tract. Low-fiber foods during acute episodes prevent bulk from stagnating in areas of poor propulsion. I've watched patients with severe gastroparesis go from eating two large meals a day to six small pureed meals, and their symptoms dropped dramatically within days. The stomach doesn't care about your schedule. It cares about volume and consistency. Prokinetic agents have limitations. Metoclopramide increases acetylcholine release and improves gastric emptying, but the black box warning for tardive dyskinesia after long-term use is real. I've seen patients develop irreversible movement disorders from months of use. Domperidone is an alternative with less CNS penetration, but it carries QT prolongation risk and isn't widely available in all markets. Prucalopride, a selective 5-HT4 receptor agonist, has become a go-to for chronic idiopathic constipation with colonic inertia. It enhances colonic propulsive motility without the dopamine-related side effects of metoclopramide. The data supports it for patients who've failed osmotic and stimulant laxatives. It's not a first-line treatment for everyone, but for the right candidate, it's genuinely effective.
For gastroparesis, erythromycin acts as a motilin receptor agonist and can acutely stimulate gastric contractions. The problem is tachyphylaxis—receptors desensitize within weeks. So it's useful for short-term rescue or bridging to other therapies, not for long-term maintenance. Neuromodulators like low-dose tricyclic antidepressants address the visceral hypersensitivity that often accompanies motility disorders. The propulsion might still be slow, but the pain signal gets dialed down. This combination approach—treating both the motor dysfunction and the sensory amplification—tends to work better than targeting either alone.
When Medications Don't Touch It
Surgical options exist but carry significant risk. Gastric electrical stimulation, sometimes called a gastric pacemaker, involves implanting electrodes on the stomach wall connected to a pulse generator. It helps some patients with refractory gastroparesis, but response rates are around 50 to 60 percent, and complication rates are notable. I've seen lead migration and infection requiring revision surgery. It's not a cure. For severe colonic inertia unresponsive to all medical therapy, subtotal colectomy with ileorectal anastomosis is the last resort. It removes the primary site of the problem but trades one set of complications for another—chronic diarrhea, urgency, and potential pelvic floor dysfunction from the altered anatomy. Patients need to understand this isn't a return to normal. It's damage control. The fundamental issue with propulsion disorders is that they're rarely isolated to one segment. The GI tract operates as a continuous unit, and dysfunction in one area often cascades. Slowed gastric emptying means less chyme reaching the small intestine, which alters the migrating motor complex pattern downstream. Reduced colonic propulsion leads to bacterial overgrowth from stasis, which further impairs motility through inflammatory mediators. Treating just the symptom area without addressing the network effect usually results in temporary relief at best.

I learned this the hard way early in my career. A patient with overlapping gastroparesis and slow-transit constipation got treated for each condition separately with no regard for how they interacted. The prokinetic for the stomach worsened her colonic symptoms by pushing more content into an already slow system. It took recognizing the integrated nature of the problem before we could make progress. Splitting the tract into compartments is convenient for classification but wrong for treatment.