Why Most People Mess Up Study Design Before They Even Start
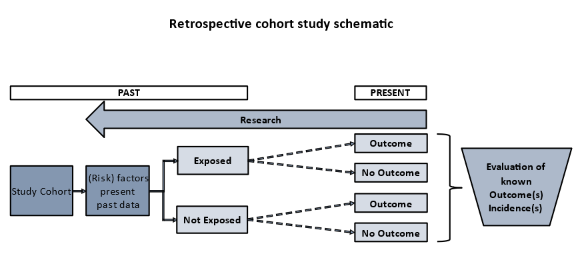
I spent about six years running observational studies before I stopped making the same errors other people make. The core confusion comes from thinking prospective and retrospective are just labels on a timeline. They're not. They're fundamentally different ways the data generating process works, and picking the wrong one for your question will waste months of work. A prospective study identifies a group of people who do not yet have the outcome you care about, measures their exposures, and follows them forward. You set the exposure status at baseline and wait for events. A retrospective study starts with people who already have the outcome and looks backward to reconstruct their exposure history. The temporal direction is opposite, but more importantly, the sources of bias are completely different. Here's the thing nobody tells you clearly: in a prospective cohort study, you control what gets measured and when. In a retrospective case-control study, you are entirely dependent on whatever was recorded before the study began. If the electronic health record didn't capture a specific lab value, it doesn't exist for your analysis. You can't ask patients to reconstruct it accurately. I learned this the hard way during a study on statin use and new-onset diabetes where the exposure of interest was a continuous variable, but the clinic had only been documenting dose categories in a free-text field since 2019. I spent three weeks manually extracting and standardizing those entries before realizing the misclassification was going to bias my odds ratios toward the null by roughly 20 percent. The workaround was to use a validated prescription database as the primary exposure source and use the clinical records only for sensitivity analysis. That alone changed the significance of two of my endpoints.
Prospective cohort studies give you incidence rates, risk ratios, and a clearer causal narrative because the exposure precedes the outcome by design. Retrospective case-control studies give you odds ratios, which approximate relative risks only when the outcome is rare. When the outcome isn't rare, that approximation breaks down and your effect size becomes meaningless to clinicians who think in terms of risk. I've seen too many papers report an OR of 2.4 for a fairly common outcome and treat it like a relative risk of 2.4. It isn't. The practical difference in execution is stark. A prospective study on a chronic disease outcome with a five-year latency might require 800 participants followed for an average of four years to power a hazard ratio of 1.3. That's expensive and it takes time. A retrospective case-control study on the same question using existing hospital data could be designed, approved, and run in under six months with a fraction of the budget. The tradeoff is that you inherit whatever confounding structure already exists in the data, and you have no guarantee that the key confounders were actually measured. Nested case-control studies sit somewhere in between. You draw cases and controls from an existing prospective cohort. This gives you the temporal clarity of a prospective design while keeping costs down because you only measure expensive biomarkers on a subset of participants. I used this approach for a study on inflammatory markers and cardiovascular events where the full cohort had baseline blood draws but I could only afford to run high-sensitivity CRP assays on cases and a matched sample of controls. The design cut my lab costs by about 85 percent without sacrificing the temporal sequence that makes causal inference defensible.
One counter-intuitive point about retrospective studies: they're not inherently weaker than prospective ones if you design them carefully. A well-executed retrospective cohort study using a large administrative database can answer questions that would be impossible prospectively, simply because the sample sizes are orders of magnitude larger. The problem is that people treat retrospective designs as shortcuts rather than legitimate study types requiring their own rigor. Registration, pre-specification of the analytical plan, and sensitivity analyses for unmeasured confounding are just as important in retrospective work. Some journals now require a RECORD checklist for retrospective studies, which covers the specific reporting items that administrative data demands. Another nuance that trips people up: loss to follow-up in prospective studies doesn't just reduce power. It introduces attrition bias if the people who drop out differ systematically from those who stay. In my diabetes and statins study, about 14 percent of participants were lost to follow-up, and a comparison of baseline characteristics between retained and lost participants showed that those lost had significantly higher baseline HbA1c. That meant the remaining cohort was progressively healthier over time, which biased the incidence rate downward. I addressed this with inverse probability weighting, which adjusted for the differential dropout, but it was a reminder that prospective studies require active retention strategies from day one, not after you notice the attrition pattern. For retrospective studies, the equivalent threat is selection bias, and it's harder to detect. If your cases come from a tertiary hospital and your controls come from primary care, the exposure distribution in your control group may not represent the population that produced the cases. This is the Berkson's paradox problem, and it can create spurious associations or mask real ones. The fix is to define your source population first and then draw both cases and controls from that same population. It sounds obvious until you realize most people skip this step because it's easier to just grab available data.
Get the Full Details

How to Actually Design and Run These Studies
Start by defining your research question in PICO format, then map it to the study design that matches the temporal relationship you need to establish. If the exposure is rare, a case-control design is efficient. If the outcome is rare, a cohort design is more appropriate. If you're studying a drug safety signal with a short latency period, a retrospective database study might give you answers faster than waiting to accrue cases prospectively. For prospective cohorts, the critical decisions are at the planning stage. Define your exposure and outcome clearly enough that another researcher could reproduce the measurement. Establish your follow-up protocol, including how often you'll contact participants and what happens when they miss a visit. Build your retention strategy into the budget from the beginning. I've seen prospective studies fail not because of bad science but because the retention budget was an afterthought. You need resources for transportation reimbursement, flexible appointment scheduling, and periodic check-ins that aren't tied to data collection. For retrospective studies, your first task is data auditing. Before you write a single line of analysis code, you need to understand the structure, completeness, and quality of your data source. Run frequency tables on every variable you plan to use. Check for impossible values, duplicate records, and inconsistent coding. I once spent two weeks troubleshooting what I thought was a programming error before realizing the billing codes in the dataset had been recoded mid-study. The same procedure had two different codes depending on the year. This kind of temporal inconsistency is invisible until you hit it in your analysis.
Sensitivity analyses are non-negotiable in retrospective work. Run your primary analysis, then vary the inclusion criteria, the matching strategy, and the confounder set. If your results flip direction with a minor specification change, your findings are not robust. Report those sensitivity analyses. Readers and reviewers will look for them whether you provide them or not. The biggest mistake I see is treating prospective and retrospective as a hierarchy where prospective is always superior. They answer different questions with different constraints. A prospective study on a disease with a 20-year latency and a low incidence rate might never reach statistical significance within a reasonable timeframe and budget. A retrospective study using a large claims database might give you a clear answer in a year, even if the causal inference is weaker. Knowing which tradeoff your question can absorb is the skill that separates competent researchers from the rest.