PSA Numbers and What They Actually Mean in Practice
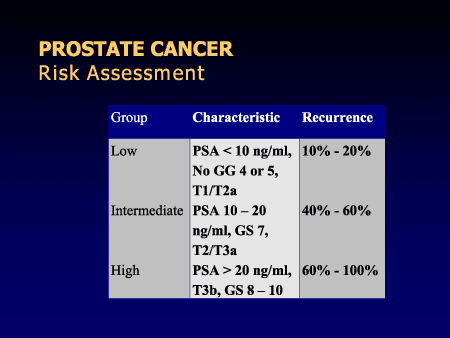
The prostate-specific antigen test is the entry point for almost every Prostate Cancer Risk Assessment pathway in the US and UK. A raw PSA value tells you very little on its own. A 4.2 ng/mL reading in a 55-year-old man with a 30cc prostate is clinically meaningless compared to the same number in a 72-year-old with a 65cc gland. The test has been around since 1986, and we still argue about the right cutoff like it's 1994. Here's the thing most patient guides skip: PSA velocity matters less than people think. The old rule was that a rise of more than 0.75 ng/mL per year warranted a biopsy. Studies from the past decade show that velocity is noisy. A single elevated PSA followed by a normal one usually means nothing. Two elevated values taken six weeks apart is worth more. Three values over 12 months is where the signal starts emerging from the noise.
Building a Real Prostate Cancer Risk Assessment from Scratch
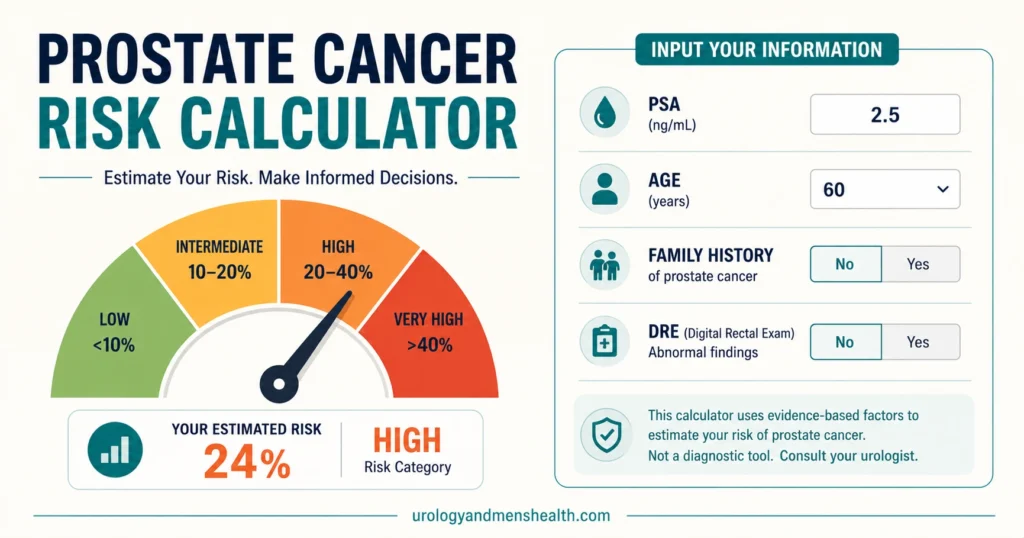
I started working with these tools around 2012, before MRI became standard. Back then we relied heavily on the PCPT risk calculator and the ERSPC model. Both required entering age, PSA, DRE result, and sometimes family history. The PCPT calculator was trained on biopsied men from the trial, which means it overestimates risk in unscreened populations. I learned this the hard way when a 58-year-old with a PSA of 3.1 and a normal DRE got flagged as 12% risk by the tool, but his MRI showed nothing and a subsequent targeted biopsy was negative. The modern approach combines multiple data points. You start with the PSA, adjust for prostate volume using the PSA density calculation. A PSA density above 0.15 ng/mL/cc is the conventional threshold, though some centers now use 0.12 for younger men. Then you layer in the MRI. Multiparametric MRI with PI-RADS scoring has largely replaced blind systematic biopsy as the first-line imaging modality for men with elevated PSA. A PI-RADS 3 lesion is the real headache in practice. It's indeterminate. I've seen radiologists call the same PI-RADS 3 lesion "probably benign" in one report and "suspicious" in another on the same patient, six months apart.
The Clinical Tools That Actually Get Used
Beyond the basic risk calculators, there are newer blood-based tests that have entered routine practice. The 4Kscore test measures four kallikrein markers and combines them with PSA, DRE, and prior biopsy history to estimate the probability of high-grade disease. The PHI score combines [-2]proPSA with free and total PSA. Both cost roughly $200 to $400 out of pocket in the US, and insurance coverage varies wildly by plan and region. I keep a spreadsheet of which tests my colleagues actually use and which ones collect dust. The 4Kscore gets ordered maybe twice a week at our center. PHI is rarer. Most urologists fall back on what they know: repeat PSA, check the density, get an MRI if the numbers don't add up. It's not glamorous, but it works for the majority of cases. The rare cases are what burn you. Genomic testing on biopsy specimens represents the frontier right now. Tests like Decipher, Oncotype DX GPS, and Prolaris analyze gene expression from tumor tissue to predict metastasis risk after prostatectomy. These are expensive, typically $3,000 to $5,000, and most insurance companies require prior authorization that takes two to three weeks. The data supporting their use is strongest for intermediate-risk patients undergoing radical prostatectomy. For low-risk disease, the tests add nothing. I've reviewed reports where the genomic risk came back "intermediate" on a Gleason 6 tumor that would have been active surveillance material regardless. The test didn't change the management.
Get the Full Details
What Goes Wrong When You're Actually Doing This
The edge case that sticks with me involves a patient whose risk assessment kept bouncing between "low" and "indeterminate" across three different models. His PSA was slowly climbing from 2.8 to 4.1 over 18 months. PSA density was 0.11, right in the gray zone. His first MRI was PI-RADS 2, read as low likelihood of clinically significant cancer. We followed him. Six months later, repeat MRI showed a new PI-RADS 3 lesion in the left peripheral zone. We did a targeted biopsy and found a Gleason 3+4=7 adenocarcinoma, 30% core involvement. The lesion hadn't been visible on the first scan because it was small and the radiologist was relatively new to mpMRI reading. This is the real risk with imaging: inter-reader variability is substantial. Studies report kappa statistics for PI-RADS interpretation ranging from 0.45 to 0.72 depending on reader experience. Another common failure mode is over-relying on family history. The risk calculators weight a first-degree relative with prostate cancer at roughly 2x the baseline risk. But most men with a positive family history never get diagnosed. The penetrance of the common prostate cancer susceptibility variants is modest. BRCA2 mutations carry real risk, maybe 20% lifetime risk of aggressive disease. BRCA1 is less clear. POLH and ATM variants have smaller effects. I always ask about the specific type of cancer in relatives and the age at diagnosis. A brother diagnosed at 71 with Gleason 6 is different from a brother diagnosed at 52 with Gleason 8.
The Practical Workflow I Follow
When a new patient walks in with an elevated PSA, here's the sequence I use. First, confirm the elevation with a repeat PSA in 6 to 8 weeks, making sure the patient has no active UTI, hasn't had recent ejaculation, and hasn't done prolonged cycling. These factors can transiently raise PSA by 0.5 to 1.5 ng/mL. Second, get a transrectal ultrasound to measure prostate volume and calculate PSA density. Third, order a multiparametric MRI before any biopsy. Fourth, if the MRI is PI-RADS 3 or higher, proceed to MRI-ultrasound fusion targeted biopsy with systematic cores. If the MRI is PI-RADS 1 or 2, discuss active surveillance with repeat PSA and MRI in 12 months. This workflow has one major limitation that the guidelines don't adequately address: access. A multiparametric MRI for prostate imaging requires a protocol with diffusion-weighted imaging and dynamic contrast enhancement. Not every imaging center has the expertise or the equipment. In rural areas, men might wait 8 to 12 weeks for an appointment. During that wait, some men's PSA will continue to climb, creating anxiety and potentially advancing disease stage. There's no good solution for this except improving referral pathways and training more radiologists in prostate MRI.
What the Risk Calculators Miss
The biggest gap in current risk assessment is the treatment of race. Black men have a 70% higher incidence rate and a 240% higher mortality rate from prostate cancer compared to white men in the US. The PCPT and ERSPC calculators both underperform in Black populations. I recently saw a 54-year-old Black man with a PSA of 3.5, normal DRE, and a calculated risk of 8% by PCPT. His MRI showed a PI-RADS 4 lesion. The targeted biopsy revealed Gleason 4+3=7. The calculator would have sent him home. This is why I always manually adjust the risk upward by one category for Black patients, regardless of what the model says. It's not in any guideline yet, but it's what the epidemiology demands. Another gap is the handling of 5-alpha reductase inhibitors. Men taking finasteride or dutasteride for BPH have their PSA values roughly halved. The standard approach is to multiply the PSA by 2 before entering it into a risk calculator. But this correction is imperfect. It doesn't account for the fact that these drugs also reduce prostate volume and change the PSA density relationship. I've found that the corrected PSA approach underestimates risk in men on 5-ARIs, particularly those with a PSA between 1.5 and 3.0 after correction. In these cases, I skip the calculator and go straight to MRI if the clinical picture feels off.

When to Stop Assessing and Start Acting
The hardest part of this job isn't the science, it's knowing when enough is enough. I had a patient in his late 60s who came in with a PSA of 4.8, normal MRI, and a strong desire to "know everything." We ran the 4Kscore, the PHI, discussed genomic testing. He wanted all of it. The numbers were consistently low risk. He kept asking for more tests. I spent 45 minutes explaining that more testing wouldn't make him safer and might actually cause harm through false positives and unnecessary biopsies. He left satisfied in the sense that we'd exhausted the options, but I worry we reinforced the idea that more data is always better. The evidence for screening benefit is real but narrow. The US Preventive Services Task Force gives a C recommendation for men aged 55 to 69, meaning the net benefit is small. The European Randomized Study of Screening for Prostate Cancer showed a 20% reduction in mortality after 14 years of follow-up, but you need to screen 1,000 men to prevent one death, and 48 men will be overdiagnosed and overtreated. These numbers haven't changed meaningfully in 20 years. The risk assessment tools help you pick which men to watch closely, but they can't eliminate the fundamental uncertainty that comes with screening for a slow-growing cancer in an aging population. If you're sitting on the other side of this conversation and your PSA is elevated, the best thing you can do is find a clinician who will walk you through each step rather than pushing you toward or away from biopsy based on a single number. Ask about PSA density. Ask whether MRI is available. Ask about their PI-RADS reading consistency. These are practical questions that matter more than any risk calculator you'll find online.