The Glute Bridge at a Pain-Producing Angle
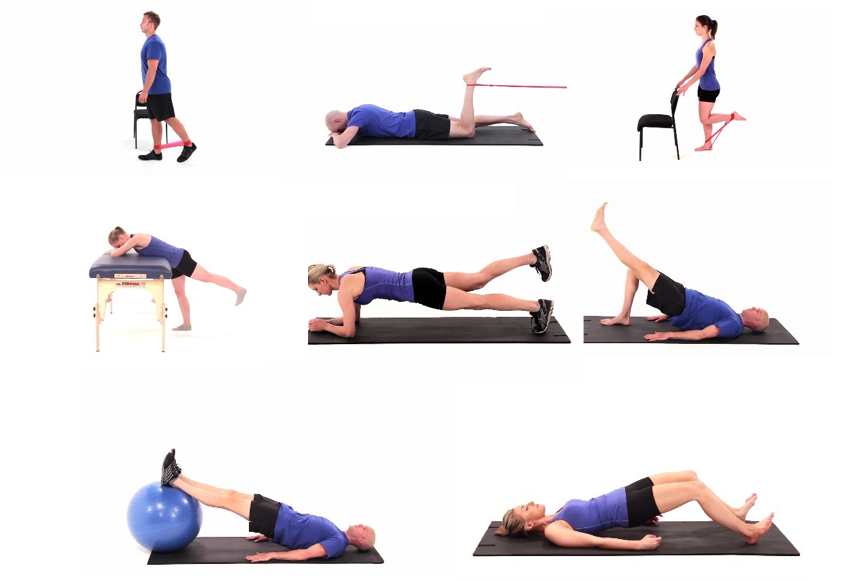
I used to tell patients to just keep squatting through hamstring pain because "load management matters." That advice was wrong for proximal hamstring tendinopathy, and it took me two years of watching the same people worsen before I changed my approach. The issue is that a standard squat or Romanian deadlift loads the hamstring origin at roughly 70 to 90 degrees of hip flexion, which is exactly where the tendon gets compressed against the ischial tuberosity. Compression plus load equals flare. What actually works is loading the tendon in a more open hip angle where the tendon slides freely without being pinched. The exercises you need focus on isometric holds first, then slow eccentrics, all performed with the hip in a moderately extended position rather than deeply flexed. Here is how the progression actually looks in practice. Isometrics are not a placebo. They reduce tendon pain for 30 to 45 minutes after the set, which gives you a window to start building capacity. Start with a prone hip extension hold. Lie on your stomach with your legs straight, tuck a small towel under your foreheads if it helps, and lift your thighs off the table by squeezing your hamstrings and glutes. Hold for 30 to 45 seconds. That is one rep. Do three reps with two minutes rest between each one. You should feel the effort in the upper hamstring near the sit bone, not in the middle of the belly. If you feel a sharp pinch at the ischial attachment, you are lifting too high or holding too long. Drop the range and the time.
I had a runner come in with a two-year history of proximal hamstring pain who could not sit for more than 20 minutes without needing to shift. We started her on isometrics at 50 percent effort, not 70, because at 70 she was flaring the next morning. She did them every other day for six weeks before moving to phase two. The pain rating dropped from 6 out of 10 down to 3 within three weeks. She did not do stretching. Stretching the proximal hamstring through end-range hip flexion loaded the already irritated tendon and delayed progress.
Phase Two: Slow Eccentric Hamstring Curl
Once the isometrics are tolerated without a next-day flare, you add controlled eccentrics. Use a machine hamstring curl or a slider on a smooth floor. The movement is the slow lowering phase, about four to six seconds down, no bounce at the bottom. Start at 40 to 50 percent of your maximal load. Perform three sets of eight reps with two minutes rest. The key detail that most people miss is the end range. At full knee flexion, the hamstring tendon wraps around the femoral condyle and experiences peak tension. That is the part that matters for proximal pathology, but it is also the part that irritates if you rush it. The four-to-six second tempo forces you through that range with control. A physical therapist I worked with once prescribed Nordic curls to someone with proximal hamstring tendinopathy without modifying the range. The patient came back four days later with a severe flare. Nordic curls place enormous load on the hamstring in deep knee flexion, which is a different mechanical demand than a standard curl and often too aggressive for proximal cases in the early stages. Stick to the controlled machine or slider version first. If you want to progress to bodyweight, do partial-range Nordics where you only lower to about 45 degrees of knee flexion and use your hands to push back up. That still builds eccentric capacity without the extreme tensile load.
Get the Full Details

Phase Three: Hip Hinge Under Control
The Romanian deadlift belongs in this phase, not the first one. The hip hinge loads the hamstring at a moderate hip flexion angle where there is less compression at the proximal origin. Use a light dumbbell or kettlebell. Start with the weight at your sides, hinge forward by pushing your hips back while keeping a soft but fixed knee angle. Go only as far as you can without any pain at the sit bone during the movement. Two seconds down, one second pause, three seconds up. Three sets of six to eight reps. If you feel a twinge at the top of the ascent, the weight is too heavy or your range is too deep. The counter-intuitive part here is that most people with proximal hamstring tendinopathy have weak glutes and poor hip hinge mechanics, so they compensate by overloading the hamstring origin instead of using the glutes and posterior chain as a unit. Adding a glute-focused exercise like a hip thrust or a banded lateral walk before the RDL actually reduces hamstring pain during the hinge. It sounds backwards but it works because the glutes take some of the load that the hamstring would otherwise carry at the insertion.
What This Approach Does Not Fix
Isometric holds will not rebuild the tendon if you never progress past them. Doing isometrics indefinitely is a bottleneck. Most people plateau around week eight if they stay in phase one because isometrics modulate pain but do not significantly increase tendon load capacity. You have to move to eccentric and strength work for remodeling to occur. Running is also a separate problem. Tendinopathy exercises do not prepare the tendon for the ground reaction forces of running until you have completed at least eight weeks of progressive loading. A common mistake is adding back jogging while still doing only isometrics. The tendon is pain-free during the exercise but still structurally weak under impact. If you want to return to running, add a walk-run protocol only after you can do three sets of eight slow eccentrics at 70 percent of your body weight without a next-day symptom increase. Lumbar radiculopathy can mimic proximal hamstring pain, and these exercises will not help if the source is actually L5 or S1 nerve root irritation. If you have numbness, tingling, or pain that travels below the knee, get imaging before committing to a six-week tendon loading protocol. About 12 to 15 percent of people who present with proximal hamstring pain actually have a disc issue referring symptoms to the same region.
The Workaround I Learned the Hard Way
One patient told me his pain was worst when he sat on a hard chair and leaned forward, like at a desk. Standard isometrics did not help because the seated flexion position compressed the tendon before he even started moving. I had him try a seated isometric contraction instead: sitting on the edge of a table with feet on the floor, gently squeeze the hamstrings by pushing the pelvis backward slightly while keeping the spine neutral. Hold for 30 seconds. That loaded the tendon in a position closer to his pain trigger without the extreme compression of full hip flexion. It was an unusual modification but it broke the cycle. He could do it at work during the day, and the pain decreased enough that phase two exercises became tolerable within four weeks.

Tracking Progress
Use a simple scale. Rate your pain during the exercise and the next morning. If the next-morning pain is higher than your baseline, the load was too much. Drop the weight or the reps by 20 percent and try again the next session. Progress should be measured week over week, not day to day. Tendon adaptations take 12 to 16 weeks to become clinically meaningful. Most people give up around week six because they expect faster results. The protocol works if you stay in it long enough.