Working with pseudostratified respiratory epithelium in the lab
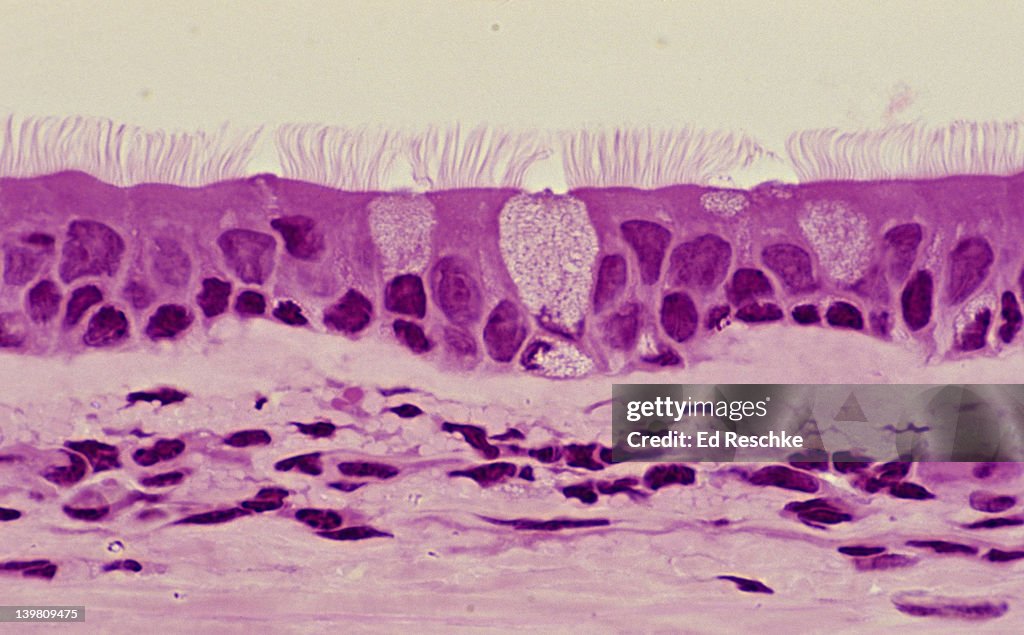
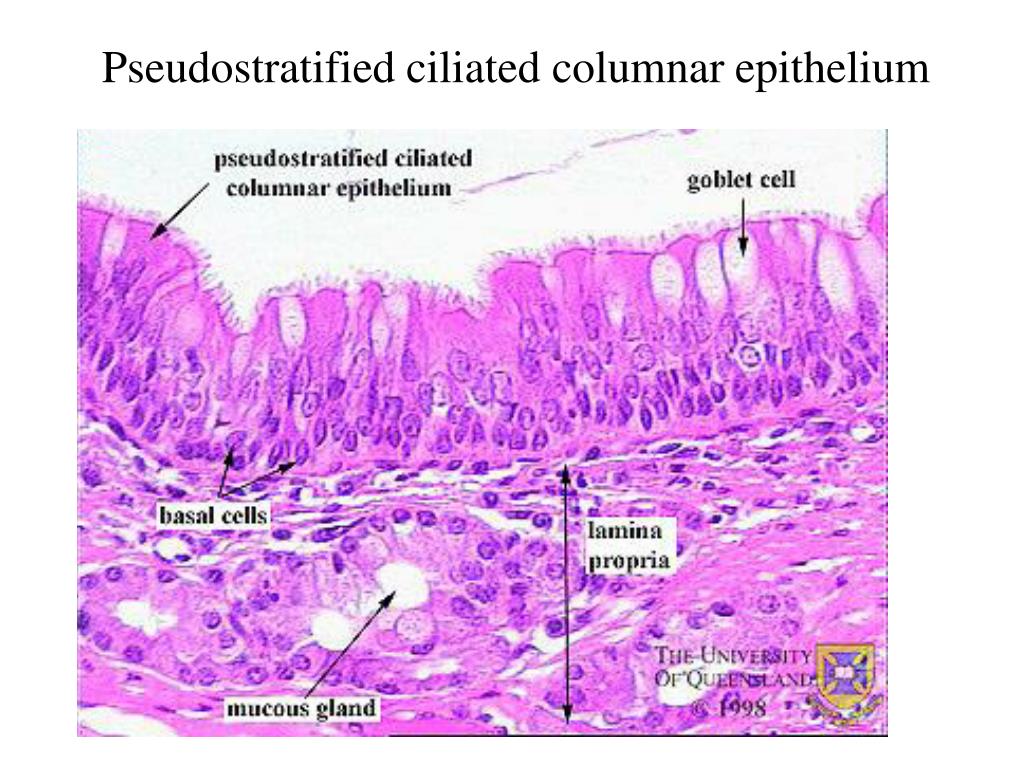
Most people learning histology or pathology hit a wall when they first try to identify this tissue. The name itself is the problem. It describes what the tissue looks like, not what it actually is. Under a scope, the nuclei sit at all sorts of different heights, creating this illusion of multiple cell layers. It looks stratified. It isn't. Every single cell in this epithelium touches the basement membrane. Some just don't reach the apical surface, and that's all there is to it. The cells that make this up are mostly tall columnar cells bearing motile cilia on their apical surfaces. Interspersed among them are goblet cells packed with mucin granules, and below both of those, resting directly on the basement membrane, are basal cells—small, dark, not reaching the surface at all. The whole arrangement sits on a thin basement membrane above a layer of loose connective tissue. That's the basic layout. In practice, telling it apart from other respiratory-looking tissue takes careful attention to where the nuclei are and whether you can actually trace each one back down to that membrane. The most common places this shows up are the nasal cavity, paranasal sinuses, trachea, and the larger bronchi. You'll also find a modified version in the male reproductive tract—the epididymis and vas deferens—but there the "cilia" are stereocilia, which are actually long microvilli, not true motile cilia. They don't beat. The ones in the respiratory tract do, and they do it in coordinated waves.
Here's something most people miss about the cilia themselves. They're nearly invisible on standard H&E staining. The ciliary shaft is almost entirely microtubules with very little cytoplasm, so it takes on very little hematoxylin or eosin. What you're really seeing on a routine slide are the nuclei and the general cell shape, not the actual ciliary apparatus. If you need to evaluate ciliary structure or density—which you have to do in cases of suspected primary ciliary dyskinesia or chronic rhinosinusitis—you need special stains. Periodic acid-Schiff will highlight the goblet cell mucins in magenta, which helps orient you to the tissue, but it won't show cilia. For that, I use acetylated alpha-tubulin immunohistochemistry. It labels the stable microtubule cores of the cilia and gives you a clear, specific signal on formalin-fixed paraffin-embedded tissue. It's the standard I rely on now instead of trying to eke information out of H&E alone. A few years ago I was reviewing a series of bronchial biopsies from a young patient with recurrent sinus infections and bronchiectasis. The H&E sections looked essentially unremarkable—some mild chronic inflammation, a few expanded goblet cells, but nothing that explained the clinical picture. I'd have signed it out as non-specific changes and moved on if I hadn't pushed for electron microscopy. Under EM, the cilia were clearly abnormal: misoriented, some missing entirely, others showing defective dynein arms. That's primary ciliary dyskinesia. On H&E alone, that diagnosis is essentially invisible. The workaround was straightforward once I knew what to do—I switched to IHC for acetylated tubulin on the remaining tissue block and got clear visualization of the ciliary defects without needing to go straight to EM, which cuts turnaround time significantly. If you're dealing with a small biopsy and the cilia aren't visible on H&E, don't stop there. Special staining or EM changes the yield. The mucociliary escalator is the functional output of this tissue, and it's more mechanically complex than most introductory courses cover. The cilia beat in a metachronal rhythm, which means they propagate waves of coordination across the epithelial surface. Each cilium has a stiff power stroke that pushes fluid and trapped particles backward toward the pharynx, followed by a slow, curved recovery stroke that minimizes backward force. The coordination depends on interciliary mechanical coupling and gap junction signaling between cells. If the periciliary liquid layer—that thin aqueous layer sitting between the basement membrane and the overlying mucus—is depleted or too viscous, the cilia can't beat effectively. They either get bogged down in the mucus or they beat in the liquid layer without reaching it. This is why hydration status and ionic composition matter clinically, and why hypertonic saline is used in cystic fibrosis management.
Basal cells are the stem cell population here. They're small, round, and sit on the basement membrane without contacting the lumen. After injury—viral infection, smoke exposure, chemical irritant—they proliferate and differentiate to replace the lost ciliated and goblet cells. In smokers, you'll see basal cell hyperplasia as a compensatory response. It's one of the earliest histologic changes you can detect. The problem is that chronic proliferation eventually leads to squamous metaplasia, where the pseudostratified epithelium gets replaced by stratified squamous epithelium. Once that happens, you've lost the cilia and the mucus production entirely in that area. The tissue is now just a protective barrier with no clearance function. Goblet cell hyperplasia is another common finding, especially in asthma and chronic bronchitis. The number of goblet cells increases, and they extend further into the smaller airways where they normally aren't found. This produces excess mucus, and when combined with any ciliary dysfunction, you get mucus plugging. The Reid index measures mucous gland size in larger airways, but it misses goblet cell changes in the bronchioles. If you're evaluating a biopsy for chronic airway disease, count goblet cells per unit length of basement membrane in the small airways. It's a more complete picture. A practical note on sample handling. This epithelium is fragile. Cilia shear off during routine processing if the tissue is handled roughly or if dehydration is too aggressive. I've seen cases where the cilia were completely absent on the final slide and the pathologist called it squamous metaplasia, only for the clinician to push back because the endoscopic appearance was clearly respiratory epithelium. Sometimes the cilia just didn't survive the processing. If you're doing a ciliary assessment, fix the tissue properly in formalin for 24 to 48 hours, avoid excessive mechanical agitation during processing, and consider that artifact before calling true ciliary loss.
Get the Full Details
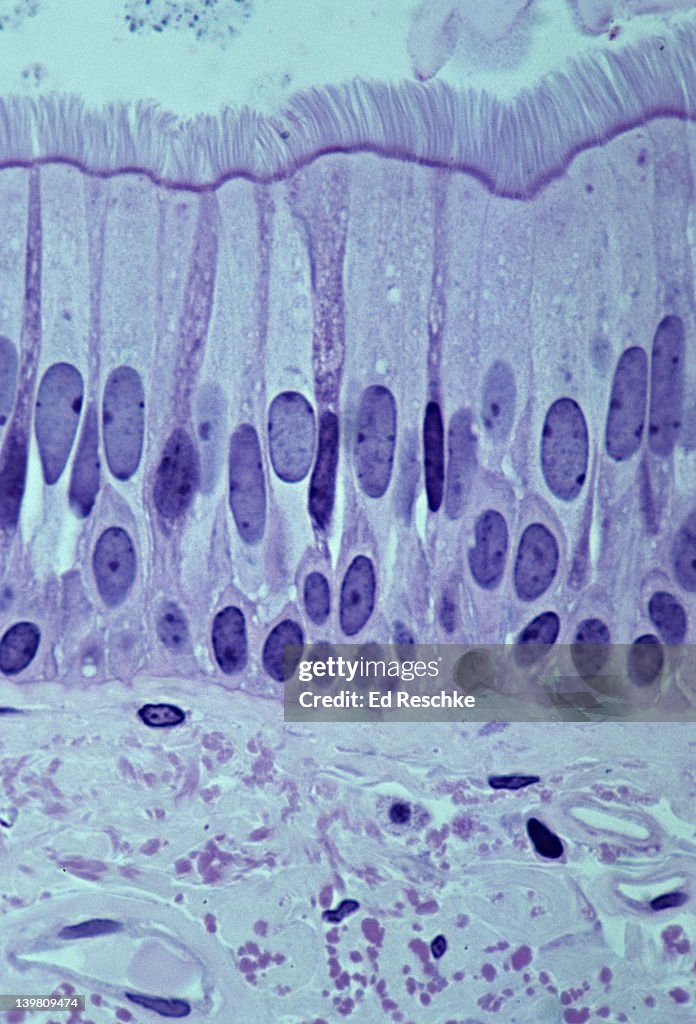
Developmentally, this epithelium comes from the endoderm of the foregut. The transcription factor FOXJ1 is the master regulator of motile ciliogenesis. If FOXJ1 is mutated or epigenetically silenced, the cilia don't form correctly or at all. Some cases of primary ciliary dyskinesia are FOXJ1-related and won't show obvious structural defects on routine EM. Genetic testing has become part of the diagnostic workup when you have a clinical suspicion but negative ultrastructural findings. It's worth keeping in mind if you're evaluating a case that doesn't fit the classic patterns. The biggest limitation of this tissue type from a diagnostic standpoint is that it's often sampled in tiny pieces. Endobronchial biopsies and nasal brushings give you fragments that may not include enough of the basement membrane to confirm the pseudostratified architecture. If you're only looking at a small cluster of columnar cells without the full epithelial context, you can't reliably distinguish pseudostratified from simple columnar or from early metaplastic changes. Orientation matters enormously. A tangentially cut section can make this tissue look like it has fewer cell layers than it actually does, or it can obscure the basal cell population entirely. Always check the orientation before committing to a diagnosis. When I'm grading these specimens now, I look at four things in order: the basement membrane continuity, the presence of basal cells attached to it, the height and nuclear stratification of the overlying cells, and the integrity of the ciliary border. If all four are intact, it's normal pseudostratified ciliated columnar epithelium. If the cilia are gone but the rest is there, it could be artifact or early injury. If the basal cells are proliferating and the apical cells are changing shape, think metaplasia. If the whole architecture is flattened into stratified squamous, the metaplasia is established. That's the sequence I follow, and it keeps me from misreading partial or processed samples.