Staining pseudostratified ciliated columnar epithelium without losing your mind
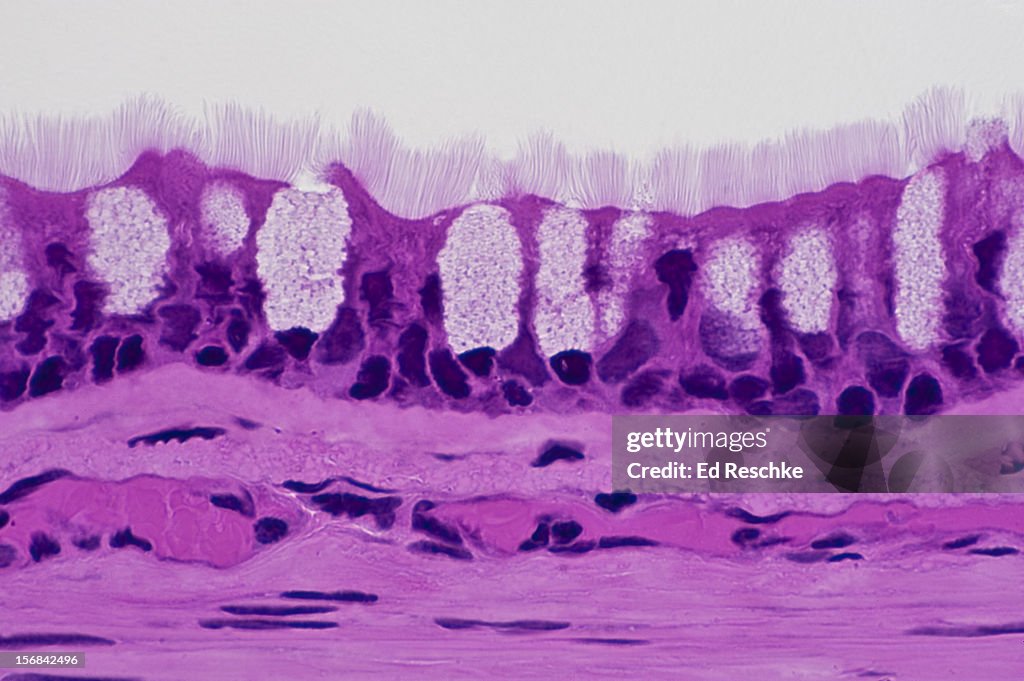
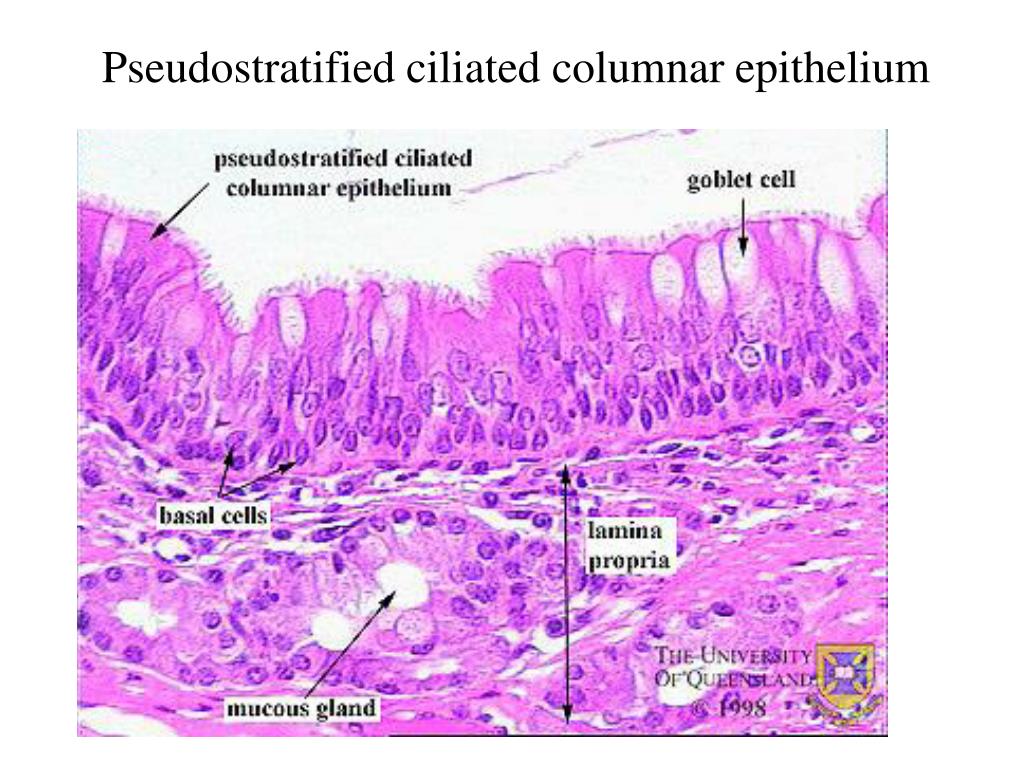
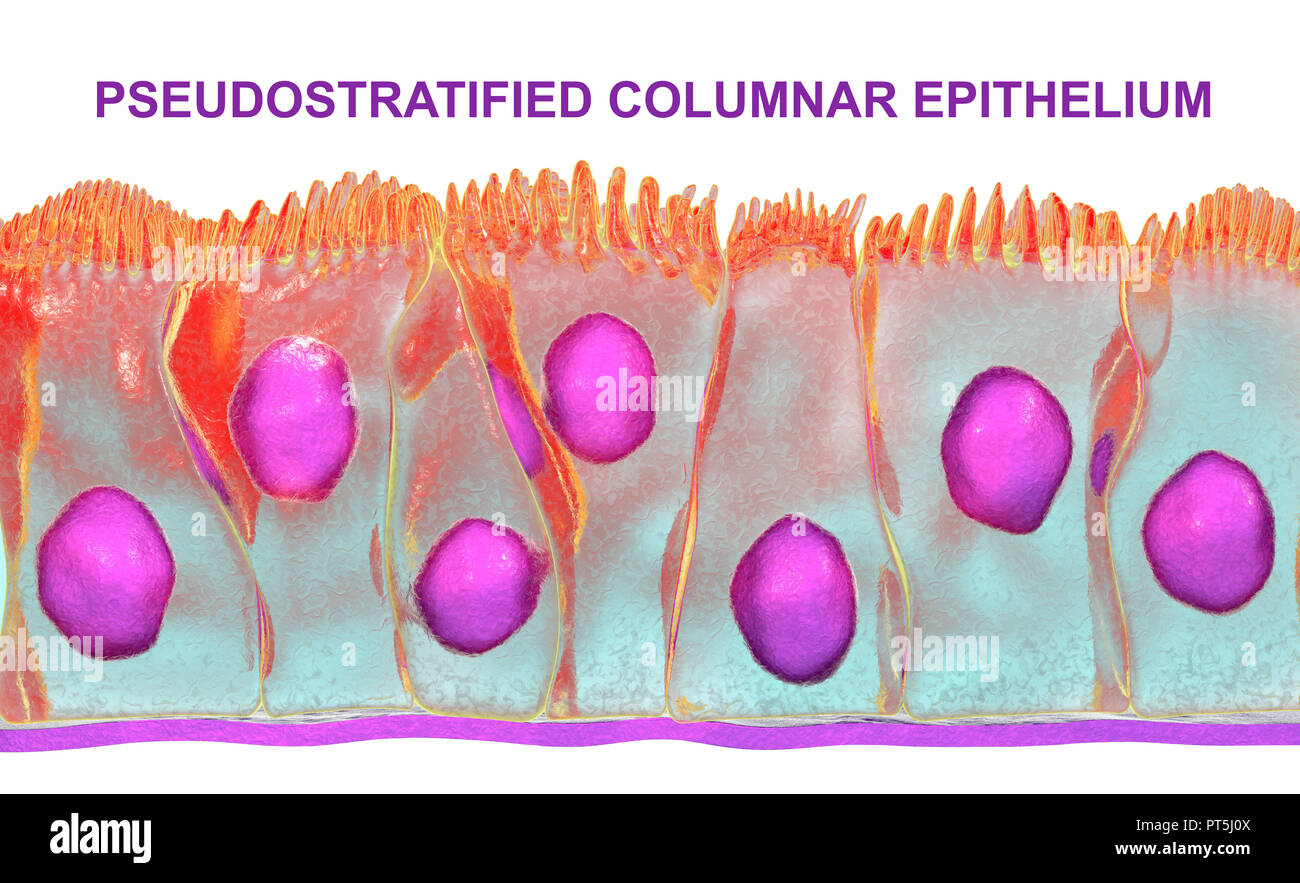
I spent three weeks struggling with H&E stains on respiratory tissue sections before I finally got consistent, clear results. The problem was never the tissue itself, it was the section thickness and how different fixatives handle ciliary structures. Here is what I learned working through it. Pseudostratified ciliated columnar epithelial tissue is not actually stratified, despite what the name implies. The nuclei sit at different levels, which creates that visual illusion of multiple cell layers, but every cell contacts the basement membrane. This matters when you are trying to identify it under a microscope because beginners often miscount layers or assume goblet cells belong to a separate tissue type. The most common location is the conductive zone of the respiratory tract, specifically the trachea and bronchi. You will also find it in the nasal cavity and the male reproductive system, though the cilia in the epididymis function differently than those in the airway.
Cilia are motile microtubule-based projections, arranged in a 9 plus 2 pattern, and they beat in coordinated waves to move mucus and trapped particles. Goblet cells interspersed among the ciliated cells secrete mucin, which hydrates into mucus. The submucosal glands beneath the epithelium contribute additional serous and mucous secretions.
Sectioning and staining that actually works
I cut sections at 5 micrometers using a rotary microtome. Thicker sections blur the nuclear stratification pattern and make the cilia indistinguishable from artifact. Thinner sections under 4 micrometers tend to damage the ciliary border during mounting, especially if you use xylene-based clearing for too long. Formalin fixation is standard, but prolonged fixation beyond 48 hours makes the cilia brittle and prone to shearing during sectioning. I learned this the hard way after processing a batch of tracheal specimens that sat in formalin for six days. The cilia were virtually invisible under high power, and I had to recount the whole set with freshly fixed tissue. For H&E staining, I use a modified protocol. Hematoxylin for 5 minutes, bluing in warm water for 2 minutes, eosin for 90 seconds. The cilia take up the eosin stain as a faint pink fringe along the apical surface, and if your section is clean, you can see individual cilia extending beyond the cell border. Goblet cells appear as clear vacuoles because the mucin washes out during processing, leaving empty-looking spaces between the stained nuclei.
Get the Full Details

A common mistake is over-dehydrating the tissue in alcohol steps before clearing. The ciliary structures become fragile and collapse. I keep the 95 percent ethanol step to exactly 2 minutes and the 100 percent ethanol to 90 seconds per change. This preserves enough structural integrity to distinguish true cilia from stain precipitate.
Identification pitfalls
The biggest issue people run into is confusing simple ciliated columnar epithelium with the pseudostratified variant. In simple epithelium, all nuclei sit at roughly the same level. In pseudostratified, the basal, intermediate, and apical nuclei create that false layering effect. The key is to scan along the basement membrane and confirm every cell touches it. If even one cell appears to float above the membrane, you are looking at pseudostratified tissue. Another pitfall is the olfactory epithelium, which is also pseudostratified but lacks cilia on most of its cell types. It has microvilli instead and specialized olfactory receptor cells. If you are examining nasal tissue and expect to see cilia everywhere, you will be confused. The ciliated cells in olfactory epithelium are limited to supporting cells and only present in certain regions. I also encountered a problematic case where chronic inflammation had replaced normal pseudostratified epithelium with squamous metaplasia in a bronchial specimen. The cilia were completely gone, replaced by stratified squamous layers. This is a real clinical finding in smokers and patients with chronic bronchitis, but it can throw off anyone expecting classic histology. The workaround was to examine adjacent non-inflamed bronchioles for comparison and correlate with the clinical history.
Special stains for difficult cases
When H&E is not giving you enough contrast on the cilia, PAS stain highlights the mucin in goblet cells as a magenta color. Alcian blue at pH 2.5 differentiates acidic mucins from neutral ones, staining the goblet cell mucin blue while PAS leaves it magenta. Using both together on adjacent sections helps characterize the mucus composition. For visualizing cilia structure specifically, a silver impregnation method like the Bodian stain can outline individual cilia against the background. This takes considerably longer than standard H&E, usually 6 to 8 hours including preparation, but it reveals details that routine stains simply cannot show. I use this only when I need to assess ciliary density or detect structural abnormalities like shortened or absent cilia. Electron microscopy is the gold standard for ultrastructural analysis of cilia, revealing the axoneme, dense fibers, and radial spokes. But it requires specialized equipment and sample preparation, so it is not practical for routine identification. If you have access to an EM facility, sending a small tissue fragment fixed in glutaraldehyde rather than formalin gives significantly better preservation of the ciliary membrane and underlying cytoskeleton.
Functional significance worth remembering
The mucociliary escalator is the primary defense mechanism of the lower respiratory tract. Cilia beat at approximately 15 to 20 times per second, moving the mucus layer toward the pharynx at a rate of about 10 to 20 millimeters per minute. This is not fast by most mechanical standards, but it is continuous and requires very little metabolic energy relative to other clearance mechanisms. Dysfunction occurs with primary ciliary dyskinesia, a genetic disorder affecting dynein arms in the cilia. Patients present with chronic sinusitis, bronchiectasis, and laterality defects. Under the microscope, the cilia may appear randomly oriented or completely absent. Recognizing this pattern requires comparing multiple fields and ruling out fixation artifact first, which brings us back to the staining quality issue. Environmental exposures like cigarette smoke and particulate matter temporarily paralyze ciliary beating through oxidative stress on the ciliary membrane. This is reversible within days of exposure cessation, but chronic exposure leads to permanent structural changes including ciliary loss and goblet cell hyperplasia. Histologically, this presents as increased mucin content, reduced ciliary density, and sometimes squamous metaplasia replacing the normal epithelium entirely.
The tissue also adapts to altitude and humidity changes. In dry environments, the mucus layer becomes more viscous and ciliary function slows. This is why people report more respiratory discomfort in heated indoor air during winter, even without any infection present. The epithelium responds by increasing goblet cell density over time, which is visible as an increased goblet cell to ciliated cell ratio on biopsy specimens.
Sample preparation workflow
Here is the sequence I follow for reliable results: Cut tissue into pieces no larger than 0.5 centimeters thick before fixing. Anything larger results in uneven fixation and poor staining throughout the core of the specimen. Fix in 10 percent neutral buffered formalin for 24 hours maximum. Do not extend this unless you are doing special stains that require prolonged fixation, and even then, 48 hours is typically the upper limit.
Process through a graded alcohol series with timed steps as noted above. Include a xylene clearing step of exactly 10 minutes divided into two 5-minute changes. Embed in paraffin and cut at 5 micrometers. Float sections on a 42-degree Celsius water bath, not higher, to avoid distorting the ciliary border. Mount on charged slides and bake at 60 degrees Celsius for 1 hour before deparaffinization and staining.
This workflow takes roughly 16 hours from fresh tissue to stained slide, including processing time. It is not fast, but it produces consistent results that allow confident identification of Pseudostratified Ciliated Columnar Epithelial Tissue and its components.
Common equipment and reagent notes
Standard brightfield microscopy at 400x magnification is sufficient for routine identification. Oil immersion at 1000x helps confirm individual cilia and assess ciliary density, but it is not necessary for basic classification. Phase contrast microscopy can enhance ciliary visualization without special staining, though it requires a phase condenser and objective. Most pathology laboratories stock H&E, PAS, and Alcian blue reagents. If you are setting up a new lab, prioritize getting the pH meters calibrated for the Alcian blue solution because the pH 2.5 requirement is strict and deviations above 3.0 will not differentiate acidic from neutral mucins properly. I lost an entire batch of staining runs because the meter drift went unchecked for a week. Micromomes vary in consistency between manufacturers. Leica and Thermo Fisher models tend to hold calibration better over time, but they also cost significantly more. A well-maintained budget microtome works fine if you check the blade angle and section thickness calibration weekly. I use a diamond knife for routine work and switch to a glass knife only when cutting particularly hard or calcified specimens, which is rare for respiratory tissue but common in airway biopsies from patients with chronic granulomatous disease.