Mapping Pseudostratified Columnar Epithelium Location in Histology Work
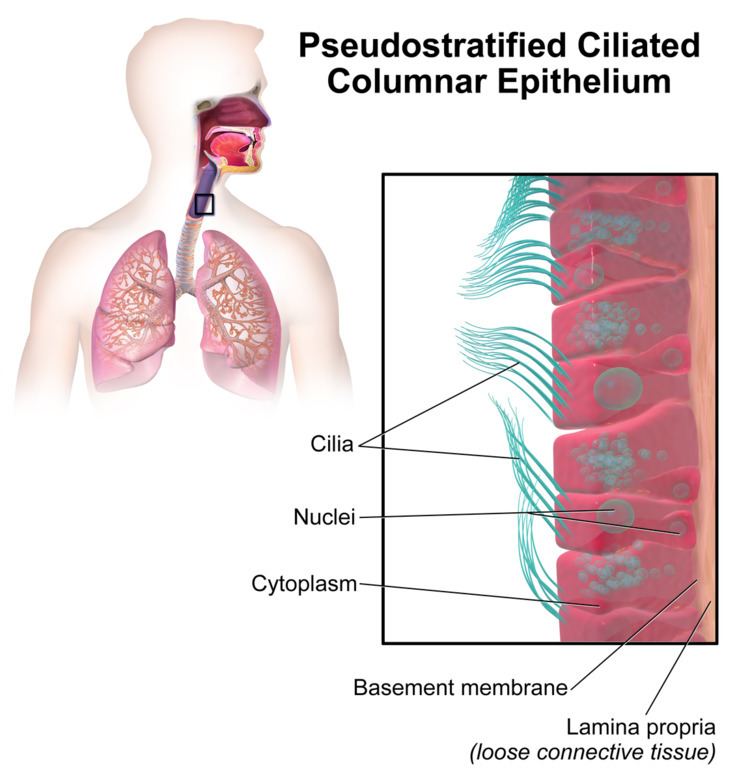
I've spent years going back to the same trouble spots when I need to confirm whether a tissue section actually has pseudostratified columnar epithelium or if it's just some other layer that looks similar under poor staining. The most common place people get tripped up is the respiratory tract, but the actual locations run deeper than that, and recognizing the architecture correctly matters more than memorizing a list. The primary sites are the trachea, bronchi, and the larger bronchioles before you hit the respiratory zone. Beyond that, the epithelium lines the nasal cavity, the paranasal sinuses, the auditory tube, the nasopharynx, and the male reproductive ducts including the epididymis and the vas deferens. The efferent ductules of the testis are a smaller but important site where the same epithelium appears in a highly specialized form with a mix of ciliated and absorptive cells. When I'm looking at a slide and trying to nail down the location, the first thing I check is the basement membrane. In true stratified epithelium, you have multiple layers sitting on top of each other. In pseudostratified, every cell touches the basement membrane even though the nuclei sit at different heights, which creates that false impression of layers. That nuclear staggering is the diagnostic feature, not the number of cell layers.
I ran into a problem recently with a set of sections from the proximal male reproductive tract where the epididymis epithelium was partially collapsed during processing. The stereocilia were laid flat against the lumen surface and the nuclei looked so compressed I almost called it simple columnar. What saved me was checking for the characteristic basal cells tucked between the taller columnar cells near the basement membrane. They're small, dark, and sit below the main epithelial row. Once I confirmed their presence, the identification locked in. Staining makes a huge difference here. Hematoxylin and eosin will show you the nuclear arrangement well enough for a routine call, but if you need to confirm cilia versus stereocilia, you're better off with a periodic acid-Schiff stain or simply scanning at higher magnification. Cilia move like a fringe and sit at the apical surface. Stereocilia are longer, branched, and don't beat. Confusing the two leads you down the wrong anatomical path entirely. Cilia point to respiratory or efferent ductule origin. Stereocilia point to epididymal or vas deferens origin. One counter-intuitive thing that most textbooks gloss over is that pseudostratified columnar epithelium is not exclusively a respiratory lining. The epididymal variant is functionally absorption-dominant, not secretion-dominant, and the cilia there serve a different mechanical purpose than in the trachea. The epithelium adapts to local demands. If you're studying a section and the function doesn't match the typical respiratory pattern, reconsider the anatomical site before you force it into a default category.
Another pitfall involves the transition zones. The boundary between pseudostratified columnar and simple columnar epithelium in the distal bronchi is gradual, not abrupt. A single serial section might show what looks like simple columnar cells because the pseudostratified region has thinned out or been cut tangentially. If you're relying on one slice, you can easily misidentify the epithelium type. Running at least three consecutive sections at 40-micron intervals usually resolves the ambiguity. The downsides of this approach are straightforward. Serial sectioning takes time and generates more slides to store and manage. The tangential cutting issue means that even experienced eyes can make errors on single sections, particularly when the tissue has been poorly oriented during embedding. I've seen specimens where the epithelium was sliced almost parallel to the surface, flattening the pseudostratified appearance into something that looked remarkably like stratified squamous epithelium under low power. It wasn't, but it took a second plane of sectioning to prove it. If you need a faster route and can't do serial sections, immunohistochemistry for cytokeratin 8 and 18 helps distinguish glandular columnar elements from the surrounding stroma, and alpha-tubulin staining clarifies ciliary presence. Those markers cost more and require additional reagents, but they cut confirmation time down significantly when the morphology is ambiguous.
Get the Full Details
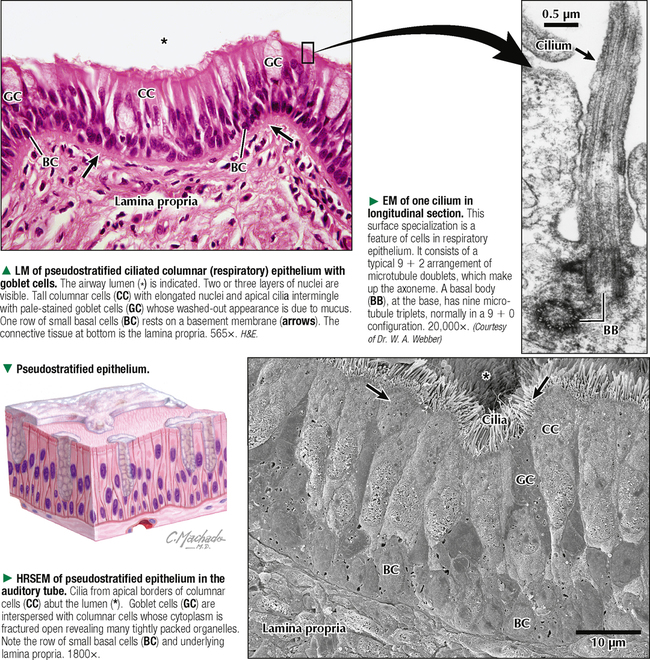
The take away is that Pseudostratified Columnar Epithelium Location isn't a static list. It's a set of regions where the cells share a common architectural logic, and that logic shows up in slightly different forms depending on the organ. Respiratory regions emphasize cilia and mucus. Reproductive conduits emphasize absorption and sperm transport. Once you train yourself to read the nuclear positions and the basal cell layer rather than just the general shape, the identification becomes far less guesswork and far more repeatable.