Why Most Psychological Assessment Reports Suck (And How to Write One That Does Its Job)
A psychological assessment report is a document that synthesizes clinical interview data, standardized test results, behavioral observations, and collateral information into a coherent narrative that answers a specific referral question. It is not a data dump. Clinicians and attorneys are the primary readers, and both groups will skim past any section that does not serve the question at hand. I have spent years writing these reports and reading the ones written by other people, and the gap between a report that changes a treatment plan and one that gets filed unread is much smaller than most clinicians realize. The biggest problem I see is structural confusion. Beginners tend to organize around the tests they administered rather than the questions the referral asked. This produces reports that read like an inventory list. A better approach is to start with the referral question, then let every section of the report answer that question. The test results come later as supporting evidence, not as the framework.
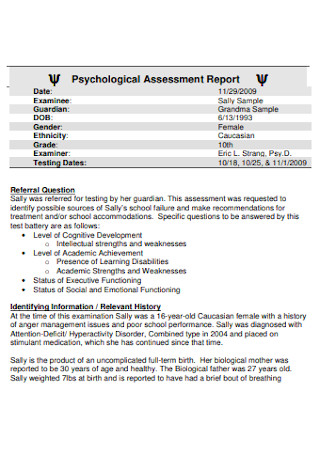
Psychological Assessment Report Sample
Here is a simplified sample structure that has held up across disability evaluations, forensic cases, and clinical referrals: Referral Question: One or two sentences. Example: "Determine whether the client meets criteria for major neurocognitive disorder due to Alzheimer's disease." Short. No fluff. Background Information: Demographics, reason for referral, source of referral, relevant medical history, current medications, educational and occupational history, substance use history, psychiatric history. Keep this tight. The reader needs to know who you are assessing and why, not their entire life story.
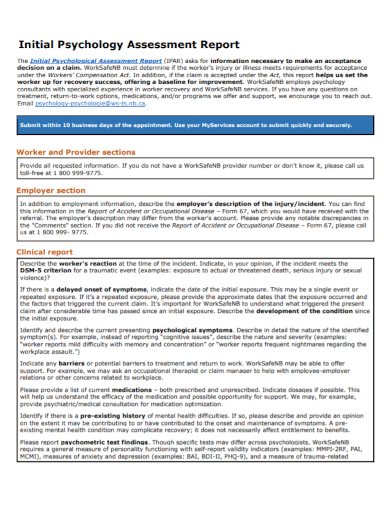
Clinical Interview Findings: Observed behavior during the interview, mental status exam findings, patient's self-reported symptoms, apparent effort and engagement. This is where many clinicians underinvest. The interview is data, not just a warm-up. Documenting effort is critical, especially in forensic or disability contexts where malingering or exaggerated symptoms are possible. Test Results: Organized by domain, not by test name. Cognitive functioning, neuropsychological functioning, personality/emotional functioning, adaptive behavior. For each domain, report the standardized scores, confidence intervals, and clinical interpretations. Do not just list raw scores. A standard score of 85 means nothing without the classification label and the context of what was measured. Clinical Impressions and Summary: This is the most important section and the one most people rush. Every finding here must tie back to the referral question. Use DSM-5-TR or ICD-11 criteria when making diagnostic statements. If criteria are not met, say so explicitly. Ambiguity here causes the most litigation and treatment misdirection.
Get the Full Details
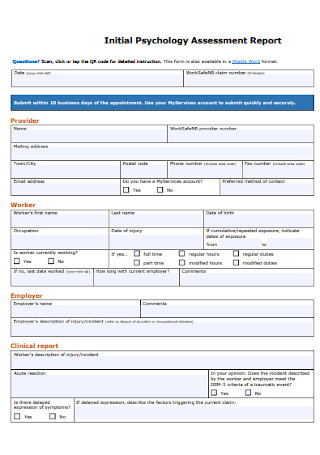
Recommendations: Specific, actionable, and tied to findings. Not "continue current treatment." Instead: "Recommend neuropsychological re-evaluation in 12 months given the progressive nature of observed deficits." "Recommend trial ofSSRI-class medication with psychiatrist." Vague recommendations are the easiest thing for a reader to ignore.
What Nobody Tells You About Writing These Reports
The most counter-intuitive thing I have learned is that specificity actually saves time in the long run. The harder part is not writing the report, it is getting it right the first time so you are not defending it six months later. I once spent three weeks revising a report because I had written "average cognitive functioning" without specifying the scale or the percentile range. The reviewing attorney demanded I either produce the full WAIS-IV table or retract the statement. I produced the table, but it cost me a week of billing that I will never get back. Another thing that surprises people: collaborative report writing is almost always superior to solo report writing when the clinician has access to records. Getting the medical records before you write the test results section means you can note where test findings align or contradict the medical record early on. When I used to write the test results first and then review records, I found discrepancies I should have flagged in the initial draft. Fixing them after the fact meant rewriting the interpretation sections, which is where the real work lives. Effort assessment is not optional. I have seen reports dismissed entirely because the examiner did not document sufficient effort measurement. The Conners Continuous Performance Test, the WAIS-IV Wechsler Adult Intelligence Scale - IV, the Word Memory Test, and the Test of Memory Malingering are standard tools for this. Pick at least two and document the results. If a client fails effort tests, report it. Do not quietly exclude the data and move on. That is the fastest way to destroy your credibility.
Tools and Formats I Use (And Why)
I write reports in a word processor with a strict template. The template includes standard headings, a table for test scores, and pre-written phrases for common interpretations. This cuts my drafting time from about four hours to roughly two hours for a standard clinical referral. Forensic reports take longer regardless of template work, usually six to eight hours because the cross-referencing with records is more intensive. For the test score tables, I use structured templates that auto-calculate standard scores from raw scores. This eliminates the most common error I see in other people's reports: incorrect standard score transcription. A single wrong digit in a IQ score can change a classification from average to borderline, and that changes the entire clinical picture. I double-check every score against the manual before finalizing, even when the software calculates it.
When a Psychological Assessment Report Is Not the Right Tool
There are situations where a full psychological assessment report is not appropriate, and writing one anyway is where clinicians get themselves in trouble. Acute crisis situations are the main example. If someone presents in active suicidal crisis, you do not administer a full battery. You conduct a risk assessment and write a brief risk report. A comprehensive psychological assessment report in that context delays treatment and can be harmful. Another scenario is when the referral question is too broad. "Assess for psychological issues" is not a valid referral question. Without a specific question, the report will be vague, and vague reports are legally and clinically useless. I have declined referrals on this basis multiple times. A good referral question looks like: "Evaluate for ADHD in an adult presenting with chronic procrastination and time management difficulties." Narrow enough to guide testing, broad enough to allow clinical flexibility. The limitation I hit most often is cost and accessibility. A full psychological assessment can run several thousand dollars and require multiple appointments. For clients who cannot afford it or cannot attend multiple sessions, a brief screening report may be the only realistic option. It will not be as thorough, but it can still answer a specific question and guide initial treatment decisions.
Final Practical Notes
Write the recommendations before you write the body of the report. This sounds backward, but it forces you to be clear about what you intend to recommend before you get lost in the test data. When I switched to this order, my recommendation sections became significantly stronger and more specific. The rest of the report tends to flow naturally from a clear set of recommendations. Use plain language. "The client scored in the fifth percentile on the memory subtest" is clearer than "The client exhibited significant memory deficits consistent with a broad-based cognitive impairment profile." The latter sounds more professional but conveys less information. Readers appreciate precision over sophistication. Keep copies of all raw data and scoring worksheets. Not because you expect to need them, but because you will. A reviewing clinician or attorney will ask for them eventually, and the request will come at an inconvenient time. Having them organized from day one makes that moment manageable instead of catastrophic.