Understanding the Difference Between Psychological and Physiological Dependence
Psychological Dependence Vs Physiological Dependence: A Practical Guide
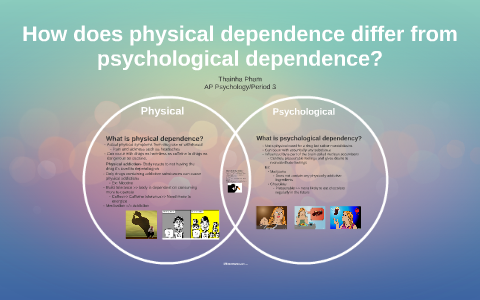
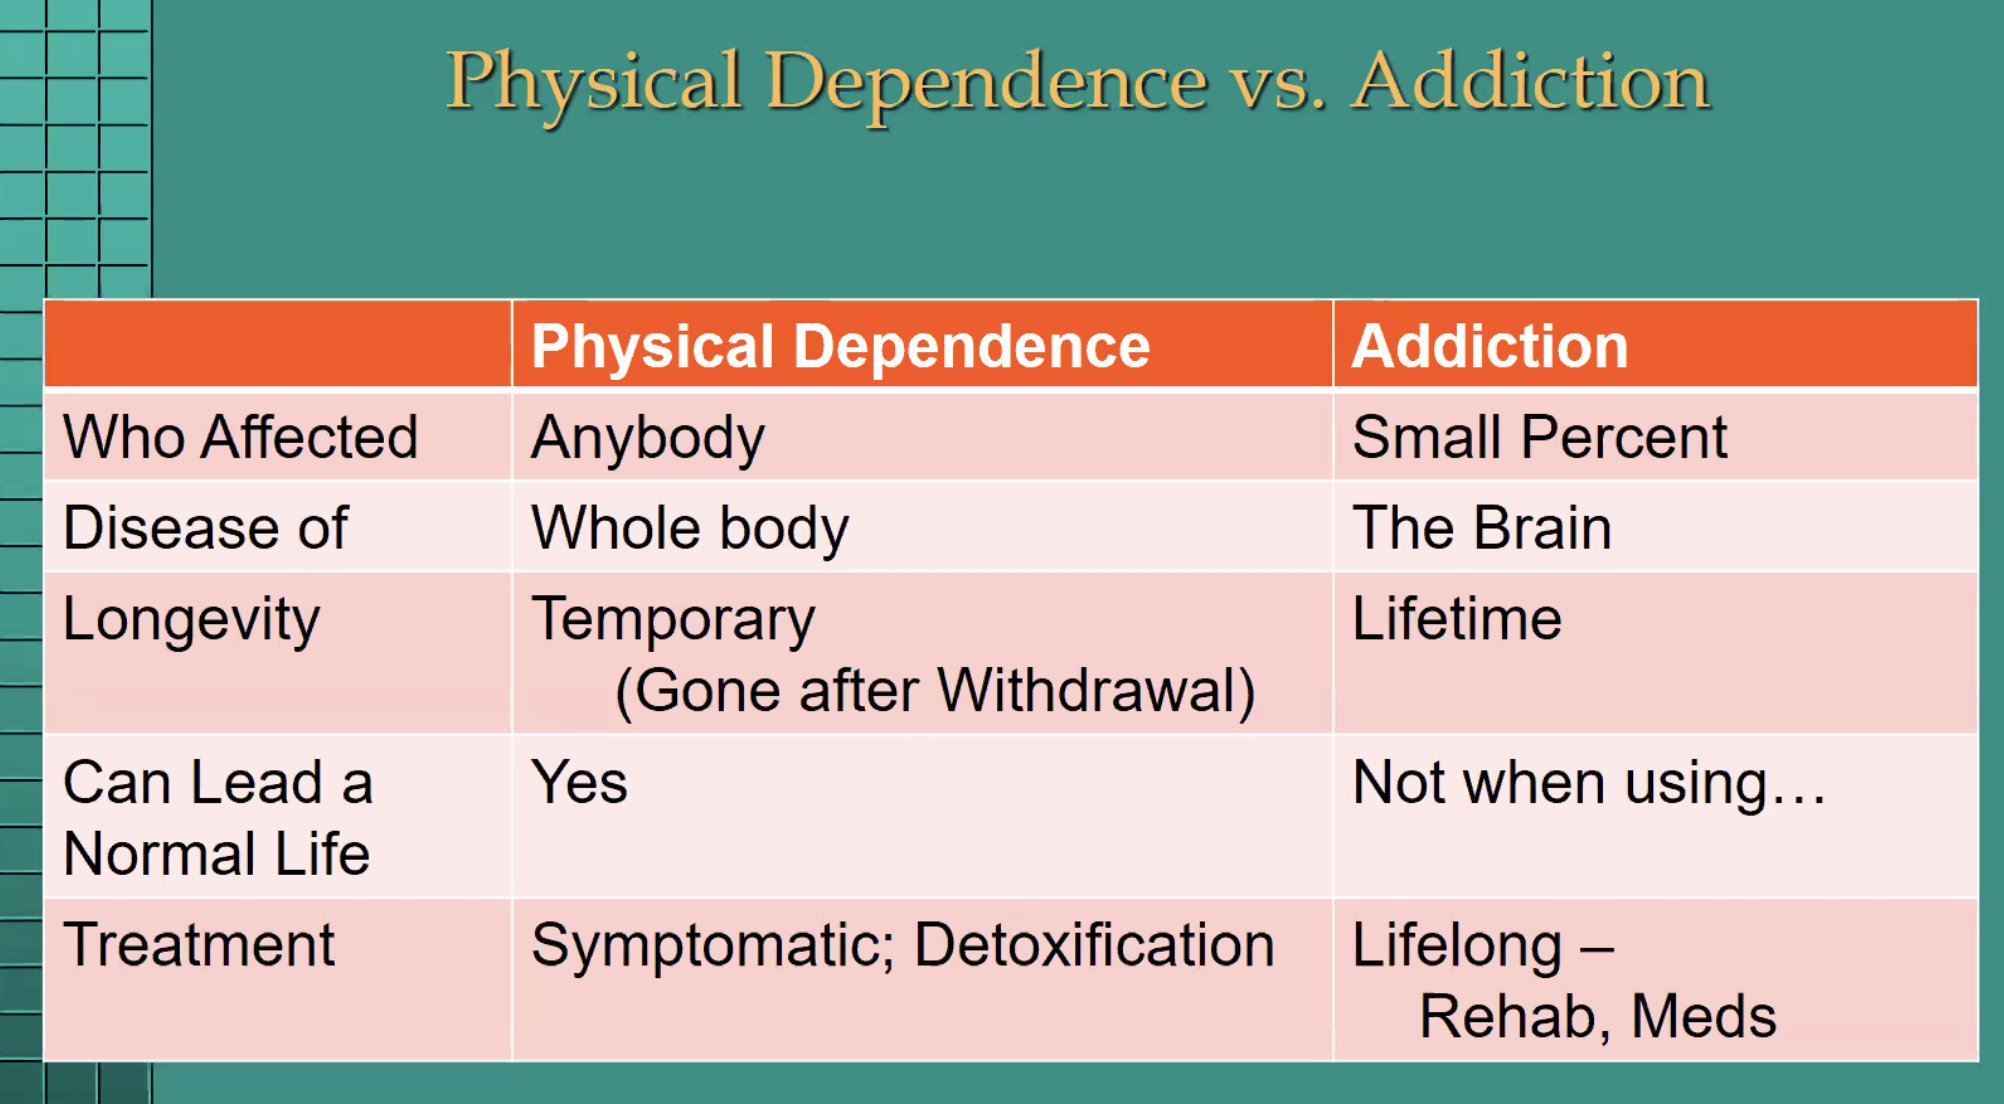
The distinction between psychological and physiological dependence matters more in practice than most people realize. When I worked in addiction counseling, I saw the same patient come back month after month because the treatment only addressed one form and not the other. The definitions are straightforward but the real-world application is messy. Physiological dependence means your body has adapted to a substance and needs it to function normally. Without it, you get measurable physical withdrawal symptoms. Psychological dependence means you crave the substance or behavior for emotional relief, habit, or reward, even though your body isn't physically dependent. Most substances cause both. Alcohol is a common example. Chronic heavy drinking produces physiological withdrawal—tremors, seizures, delirium tremens—while also creating a powerful psychological urge to drink that persists long after the body has detoxed. Caffeine causes mild physiological dependence with headaches and fatigue upon withdrawal, but the compulsion to have your morning cup is largely psychological. Some behaviors, like gambling, create purely psychological dependence with no physiological component at all. The trick is figuring out which type dominates in any given case because it determines what treatment approach will actually work. This is where things get complicated in practice.
How to Tell Them Apart
The simplest method is timing. Physiological withdrawal from substances like opioids typically begins within hours of the last dose and peaks within a few days. Psychological cravings don't follow that timeline. They can appear weeks or months later, triggered by cues—people, places, emotions—not by the absence of a substance in your bloodstream. Another practical test: ask whether the person would still want the substance if they knew they couldn't get physically ill without it. If the answer is no, the dependence was primarily physiological. If they still want it intensely despite understanding the physical risks, psychological dependence is at play. This isn't always clean. People rationalize their cravings constantly. I encountered a specific case a few years back that illustrated this well. A patient in a methadone maintenance program reported severe cravings that made him want to leave the treatment. He described shaking, nausea, and restlessness. I assumed physiological withdrawal breakthrough. Instead, it turned out his wife had just moved out and he was experiencing acute anxiety and loneliness. His body wasn't going into withdrawal. His brain was seeking the numbing effect methadone provided during emotional distress. The exact workaround was switching his appointment times to during daylight hours when he had more social contact, adding brief counseling sessions focused on his relationship situation, and adjusting his methadone dosage slightly upward for two weeks to cover the anxiety spike. Within three weeks the cravings had dropped significantly. Treating the psychological component changed the entire picture.
Counter-Intuitive Truths About Dependence
Here is something most resources don't mention clearly. Psychological dependence can be stronger and harder to break than physiological dependence in the long term. Physical withdrawal is unpleasant but time-limited. It passes. The body recalibrates. Psychological dependence doesn't have an expiration date. Cues in the environment can trigger intense cravings years after someone has stopped using. This is why people who have been sober for a decade sometimes relapse after one encounter with their old drug-using friends. Another overlooked point: severity of physical withdrawal does not predict the strength of psychological dependence. Someone going through mild physical withdrawal from cannabis can develop a deep psychological dependence that is extremely resistant to change. Meanwhile, someone experiencing severe opioid withdrawal may find that once the physical symptoms pass, the psychological urge is manageable with the right support. People who have gone through severe physical withdrawal sometimes overestimate their ability to resist because they think they've "earned" their sobriety through suffering. That assumption often leads to relapse within the first few months. The terminology itself is also getting blurry. The DSM-5 replaced the separate diagnoses of substance abuse and substance dependence with a single diagnosis called substance use disorder, graded on a spectrum. This reflects the reality that the line between psychological and physiological dependence is not always clear-cut. Co-occurring conditions like depression and anxiety can mimic or worsen withdrawal symptoms, making it harder to tell whether someone is physically dependent or psychologically dependent on a substance to self-medicate.
Get the Full Details

What Works for Each Type
Physiological dependence responds best to medically supervised detox. Benzodiazepines for alcohol withdrawal, buprenorphine for opioid dependence, and clonidine for stimulant withdrawal are standard tools. These treatments reduce the physical suffering and prevent dangerous complications. The process usually takes one to two weeks for most substances, longer for alcohol and benzodiazepines themselves. Psychological dependence requires behavioral interventions. Cognitive behavioral therapy, motivational enhancement therapy, and contingency management are the evidence-based approaches. Support groups like SMART Recovery or traditional 12-step programs address the psychological component through community and structured coping strategies. The timeline here is different. Behavioral change typically takes months to years, not days or weeks. The most effective treatment combines both approaches because most people have both types of dependence. Medication-assisted treatment followed by sustained behavioral therapy has the highest long-term success rates across nearly all substances. The medication manages the physiological side while the therapy addresses the psychological drivers. This combined approach usually cuts the relapse rate by about half compared to either method alone, based on clinical studies.
Where This Framework Falls Short
The biggest limitation is that the distinction breaks down completely for some behaviors and substances. Internet and smartphone addiction appears to involve both physiological changes—dopamine system adaptation—and psychological components like behavior and emotional regulation. There is no FDA-approved medication for behavioral addictions, so treatment relies entirely on behavioral interventions that are still being refined. Another limitation: the framework doesn't account well for polydrug use. Someone using alcohol and cocaine together creates a complex interaction where physiological withdrawal from one substance masks or amplifies psychological dependence on the other. Treatment plans become significantly more difficult to construct. Also worth noting, the psychological dependence framework struggles with substances that have minimal physiological withdrawal but strong addictive potential, like certain prescription stimulants used correctly for ADHD. The dependence is almost entirely behavioral and psychological in these cases, but the treatment approaches were designed primarily for substances with clear physical withdrawal profiles.
For people trying to understand their own situation, the most useful takeaway is to pay attention to the triggers. If cravings spike at the same time each day, in the same place, or after specific emotions, psychological dependence is likely the primary driver. If cravings come with physical symptoms like sweating, shaking, nausea, or pain regardless of context, physiological dependence is playing a larger role. Tracking this for two weeks usually gives a clearer picture than any self-diagnosis attempt.