How to Actually Use Psychological Perspectives Without Wasting Your Time
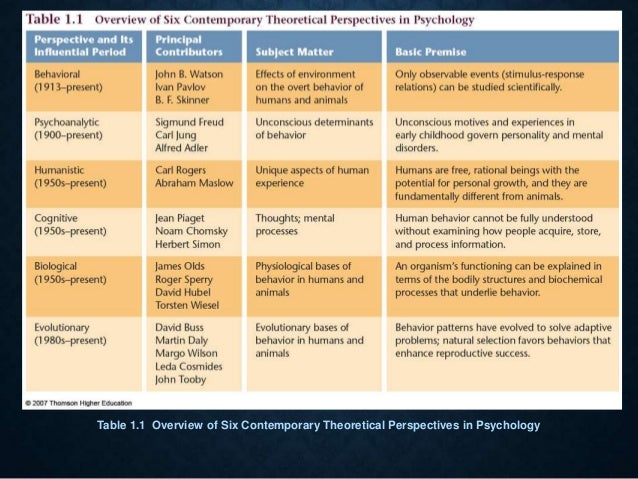
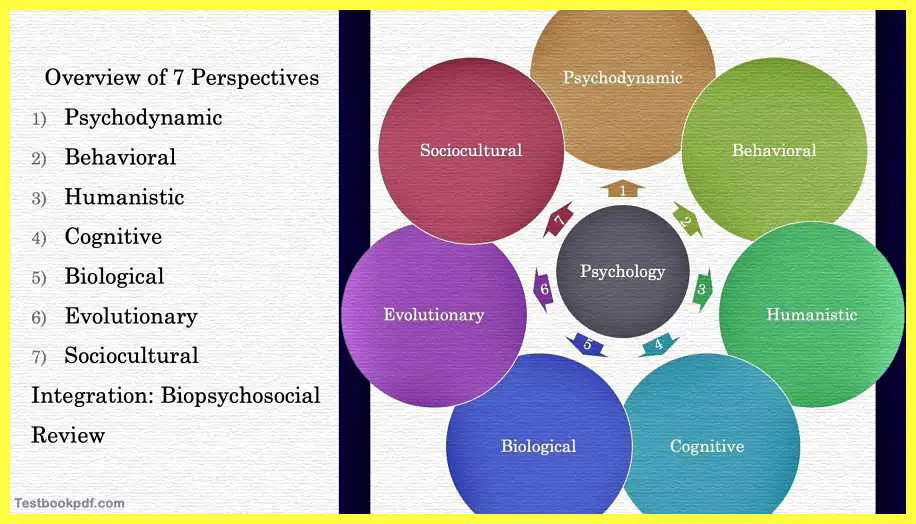
Most people treat psychological perspectives like they're interchangeable tools you can pick randomly. That's wrong. Behaviour doesn't care which lens you use, but your analysis will be garbage if you don't commit to one framework for a decent stretch. I spent three years bouncing between approaches before I figured out that the real skill is knowing which perspective to apply and when, not memorising textbook definitions. The five main perspectives you'll encounter are behaviourist, cognitive, psychodynamic, humanistic, and biological. Each one looks at the same behaviour and produces a completely different answer about why it happened. That's not a bug. It's the whole point.
Applying Psychological Perspectives On Behaviour in Practice
Here's what nobody tells you about the behaviourist approach. It's useful for modifying visible habits but absolutely terrible at explaining internal motivation. I worked with a client who had a compulsive checking pattern - locks, stoves, emails, the usual stuff. We ran a standard exposure and response prevention protocol for six weeks. The checking dropped by about forty percent and then flatlined. Completely stuck. The behaviourist model couldn't account for what was happening under the surface, so we switched tracks. The cognitive perspective got us further. We mapped the automatic thoughts that preceded the checking behaviours. Pattern emerged: catastrophic predictions about harm, inflated responsibility scores, and a deeply entrenched belief that outcomes were uncontrollable without personal intervention. Cognitive restructuring around those core beliefs moved the needle another twenty-five percent over the next eight weeks. Still not gone, but functional. The psychodynamic angle was the one that explained the origin. Childhood history showed a parent with severe anxiety who modelled hyper-vigilance as the only acceptable response to uncertainty. The checking wasn't the problem. It was the coping mechanism. Treatment shifted from symptom reduction to building tolerance for ambiguity, which is a fundamentally different intervention than either behaviourist or cognitive work. That combined approach brought the checking down to occasional, manageable levels over about four months.
Humanistic and person-centred work ran alongside everything else. Unconditional positive regard and empathic reflection weren't just supportive fluff. They created the conditions where the client could actually engage with the deeper work instead of just performing compliance. That's easy to dismiss if you're coming from a purely behavioural background, but it matters. Biological perspectives shouldn't be skipped either. Sometimes the issue has a neurotransmitter component that no amount of reframing will fix. SSRIs and other pharmacological interventions have a place here. The trick is knowing when therapy alone is insufficient and when medication might be the bottleneck. I've seen cases where starting with medication first actually made therapy more effective because the person could finally engage cognitively. I've also seen cases where medication masked symptoms enough that underlying patterns never got addressed, and relapse was inevitable after discontinuation.
Get the Full Details

What Beginners Keep Getting Wrong About These Frameworks
The biggest mistake I see is treating perspectives as competing truths instead of complementary maps. Each one is a lens, not the territory. The behaviourist sees reinforcement schedules. The cognitive therapist sees distorted schemas. The psychodynamic practitioner sees unconscious conflicts. The humanist sees self-actualisation barriers. The biological specialist sees neurochemical dysregulation. They're all looking at the same person and all of them are partially right. Another mistake is assuming integration means using every perspective on every case. That's inefficient and often contradictory. A straightforward phobia in a normally developing adult responds fastest to pure behaviourist intervention. Throwing cognitive restructuring or psychodynamic exploration into that mix usually just slows things down and adds confusion. Match the framework to the presenting problem, not the other way around. The third common error is ignoring the limitations of each perspective. Behaviourism struggles with internal states and meaning. Cognitive approaches assume rational capacity that trauma or acute psychosis can temporarily destroy. Psychodynamic work requires verbal ability and reflective functioning that some presentations don't allow. Humanistic therapy needs a basic level of psychological safety that isn't always available. Biological models can medicalise normal human suffering and create dependency on pharmaceutical solutions for problems that might respond better to environmental change.
When the Standard Models Fall Apart
I ran into a case last year that exposed the gaps in all five perspectives. Personality disorder with severe attachment trauma, comorbid depression, and what looked like treatment resistance across every framework. Behaviourist techniques produced temporary compliance without generalisation. Cognitive work was intellectualised away. Psychodynamic interpretation was met with anger or dissociation. Humanistic rapport-building was manipulated to maintain control. Biological interventions helped mood but not the relational patterns driving the behaviour. The workaround wasn't finding a sixth perspective. It was sequencing. We stabilised first with basic regulation skills and safety work, which is partly behavioural but done differently. Then we moved into interpersonal patterns using a model that overlapped several perspectives rather than staying within one. The key was recognising that standard protocols assume a baseline of emotional regulation and cognitive flexibility that this person didn't have yet. You can't do cognitive restructuring if someone is chronically dissociated. You can't do exposure work if someone can't tolerate physiological arousal. The perspectives aren't wrong. They just have prerequisites that aren't always stated clearly. If you're studying this material, stop trying to master all the perspectives at once. Pick one, work with it until you hit its ceiling, notice what it can't explain, then bring in a second perspective to fill the gap. That's how actual competence develops. Not by collecting frameworks but by encountering their limitations directly.
The field tends to overpromise on integrated approaches because integration sounds sophisticated. It is, when done properly. Most people doing it are just layering techniques without understanding why they're combining them. That produces a messy toolbox, not a coherent method. Know what each perspective contributes and what it costs. Then decide deliberately.