Understanding How Psychological Trauma And The Brain Actually Work
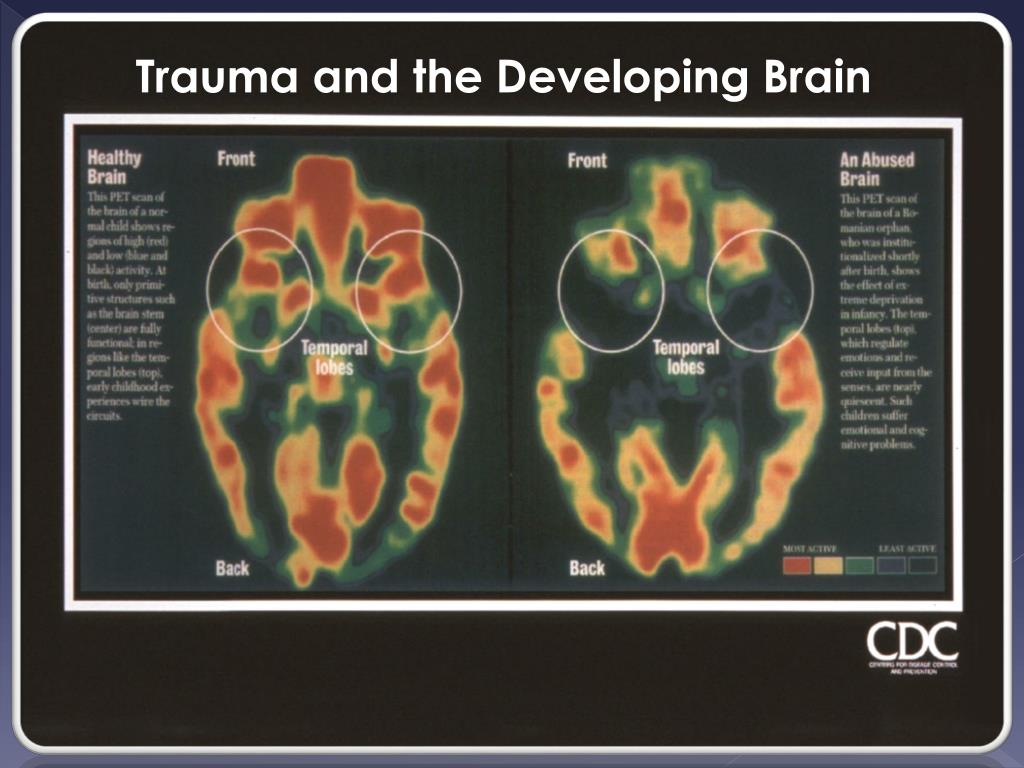
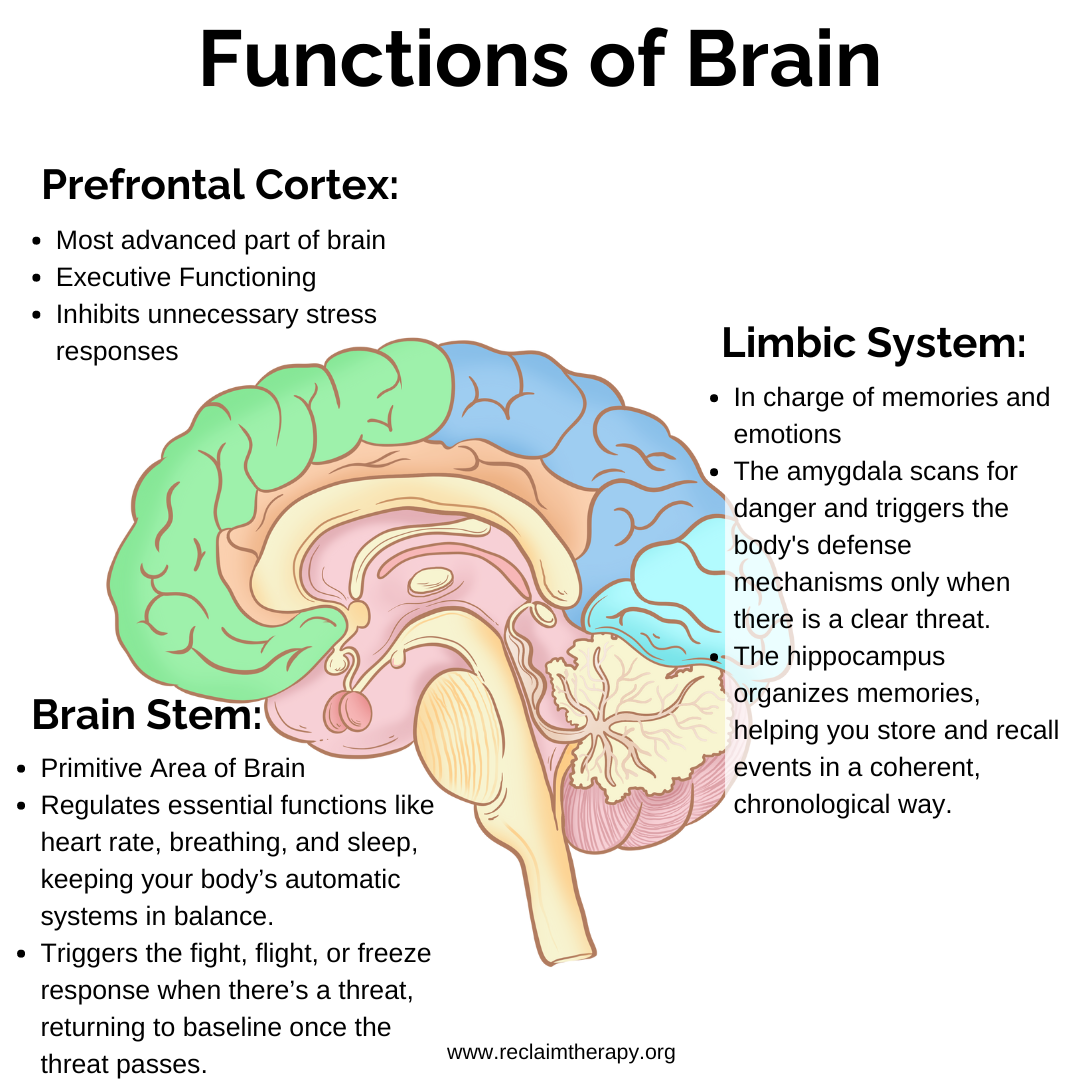
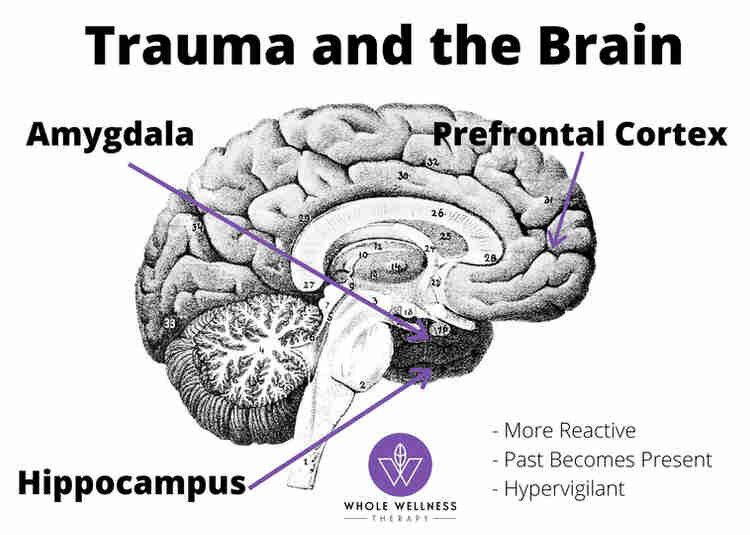
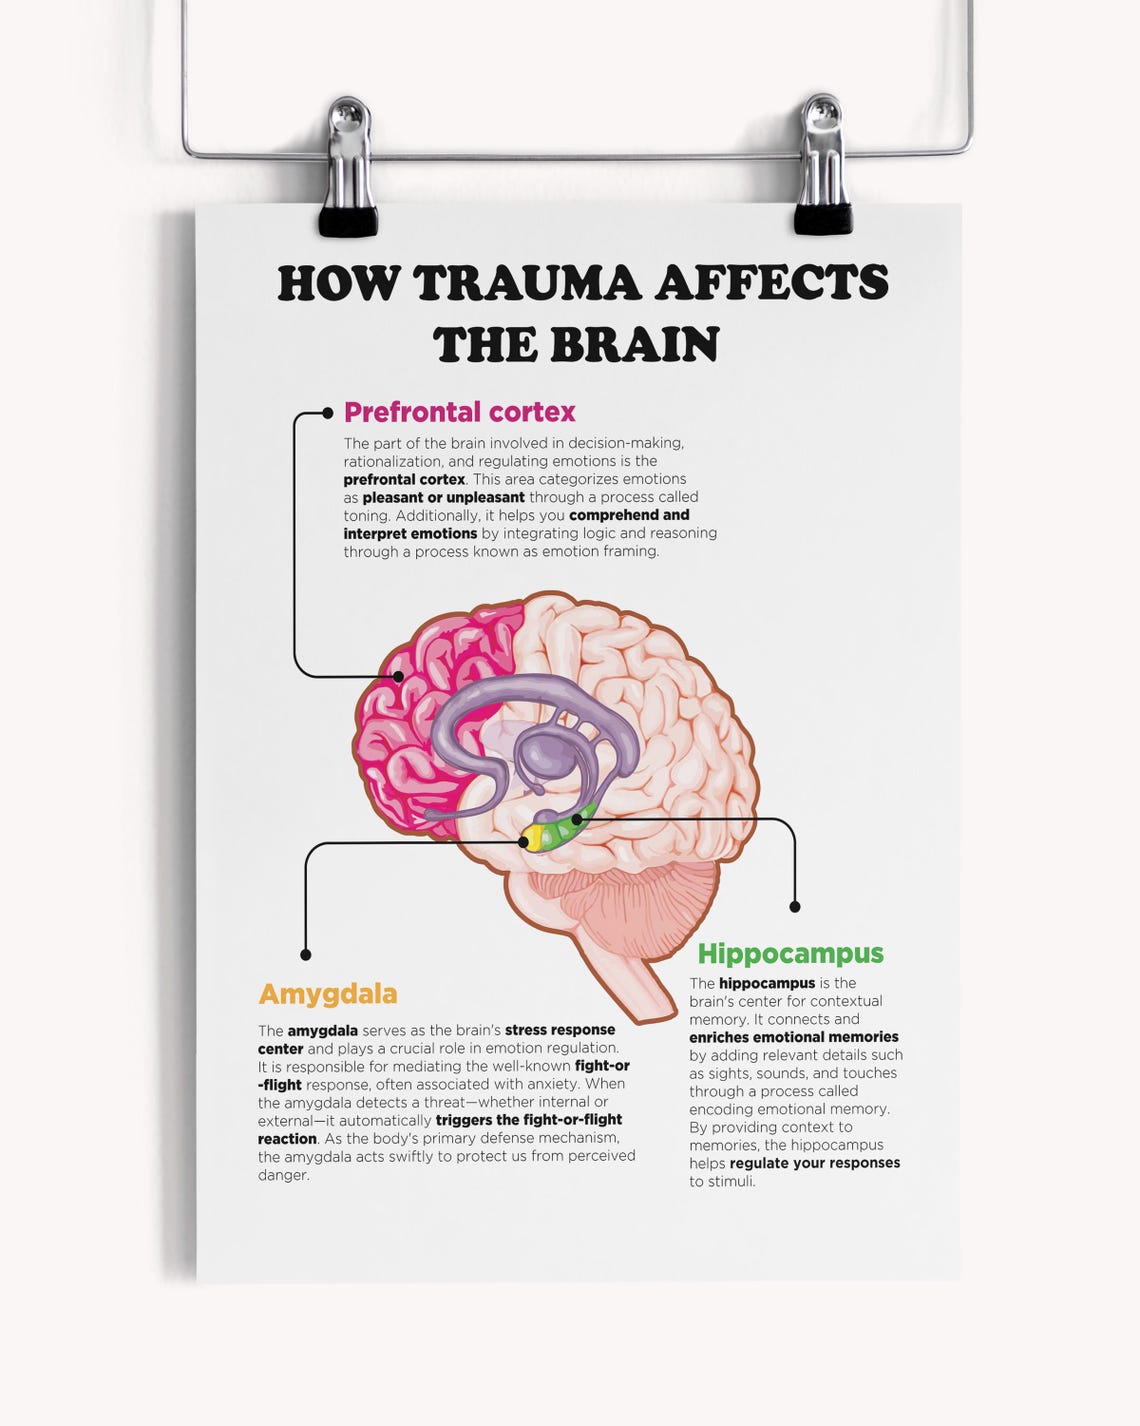
The amygdala is a small almond-shaped cluster of nuclei in the temporal lobe. It processes fear responses. When trauma hits, the amygdala tags a memory as critical threat data and starts storing it differently than normal memories. This isn't a metaphor. It's measurable neural activity. The prefrontal cortex, which handles reasoning and context, gets less engagement during and after traumatic events. That's why people under extreme stress sometimes can't think clearly or make logical decisions in the moment. The circuitry literally shifts priority. Most beginner explanations stop at "trauma happens, brain changes, therapy fixes it." That's accurate to a point but misses how the actual mechanisms operate day to day. One thing that doesn't get enough attention is the role of the hippocampus in traumatic memory consolidation. The hippocampus normally helps you tag when and where an event occurred, creating a clear timeline. Under severe stress, cortisol floods the system and suppresses hippocampal function. The result is fragmented, time-less memories. A person might experience a flashback that feels like it's happening now rather than a memory of something that happened years ago. This is why trauma-informed therapy focuses on re-establishing contextual grounding, not just "talking about it." I worked with a client a few years back who had been in a serious car accident. Standard exposure therapy was making things worse, not better. The problem wasn't the therapy technique itself. It was that her hippocampal encoding was so disrupted that each recall session was essentially recreating the disorientation of the original event without the benefit of present-moment awareness. She'd leave sessions more dysregulated than when she arrived. The workaround was to slow the pacing dramatically and introduce somatic tracking exercises first. We spent six sessions just teaching her to notice bodily sensations in real time without connecting them to the memory. Only after that did we gradually introduce the narrative component. It added about eight weeks to the treatment timeline, but it prevented a re-traumatization spiral that would've set her back months.
Another counter-intuitive point: not all trauma produces the same neural pattern. There's a difference between acute trauma from a single event and complex trauma from prolonged exposure, and they show up differently in brain imaging. Complex trauma tends to produce more widespread changes across the default mode network and can affect emotional regulation circuits more diffusely. Single-event trauma often shows more localized activation patterns centered on the amygdala-hippocampus axis. Treatment approaches that work well for one type don't always transfer to the other. EMDR, for instance, has strong evidence for single-event PTSD but mixed results for complex trauma cases. That's not a flaw in EMDR. It's a mismatch between the mechanism and the pathology.
Practical Steps For Processing Trauma-Related Neural Changes
If you're working through this yourself or guiding someone else, the first step is understanding that the brain changes from trauma are adaptive, not broken. The nervous system did exactly what it was designed to do. It prioritized survival over everything else. The goal isn't to fix a malfunction. It's to help the system learn that the threat is over and recalibrate accordingly. Sleep is the most underrated factor in trauma recovery. During REM sleep, the brain processes emotional memories and weakens the physiological charge attached to them. Trauma disrupts sleep architecture, which means the very mechanism that helps process traumatic memories gets compromised. This creates a feedback loop. Poor sleep leads to poorer emotional processing, which leads to more sleep disruption. Addressing sleep hygiene and, if necessary, using targeted interventions like sleep restructuring can accelerate recovery timelines by weeks in some cases. Vagus nerve stimulation through breathing exercises, cold exposure, or specific vocal techniques like humming can help shift the nervous system from sympathetic dominance toward parasympetic engagement. This isn't woo. The vagus nerve connects to the brainstem and modulates heart rate, inflammation, and the stress response. Controlled diaphragmatic breathing at a rate of about six breaths per minute has been shown in studies to increase heart rate variability, which is a marker of nervous system flexibility and resilience.
Get the Full Details
Body-based therapies like sensorimotor psychotherapy or somatic experiencing address the fact that trauma gets stored in the body as much as in declarative memory. People who've experienced trauma sometimes report physical symptoms with no clear medical cause, like chronic pain, gastrointestinal issues, or unexplained fatigue. These aren't imaginary. They're manifestations of the nervous system stuck in a heightened state of alert. Working with a trained practitioner who understands this connection can be more effective than talk therapy alone for certain symptoms.
Limitations And When Professional Help Is Necessary
Self-guided work has real limits. If you're experiencing flashbacks, severe dissociation, suicidal ideation, or symptoms that significantly impair daily functioning, professional support is non-negotiable. There's no shortcut around that. Some neural patterns formed during severe or prolonged trauma require structured intervention that can't be replicated through reading or self-help tools. Medication can help in specific cases. SSRIs are FDA-approved for PTSD and can reduce the intensity of symptoms enough that therapy becomes more effective. But medication alone rarely resolves the underlying neural adaptations. It's a tool, not a solution. The combination of medication and therapy typically produces better outcomes than either approach alone, according to the VA and APA clinical guidelines. Not every approach works for every person. What helped one individual might worsen another's symptoms. Trauma recovery isn't linear, and the timeline varies enormously based on the nature of the trauma, the person's support system, their history, and a dozen other variables. There's no standard protocol that applies universally. The best approach is one that respects individual differences and adjusts based on ongoing assessment rather than following a rigid treatment plan.