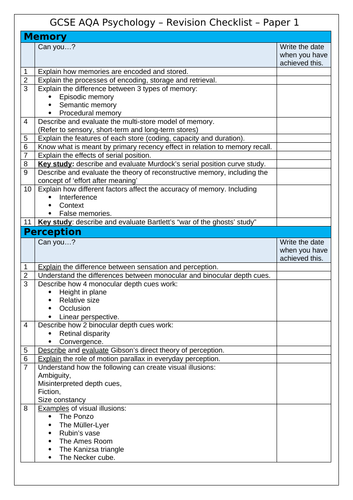
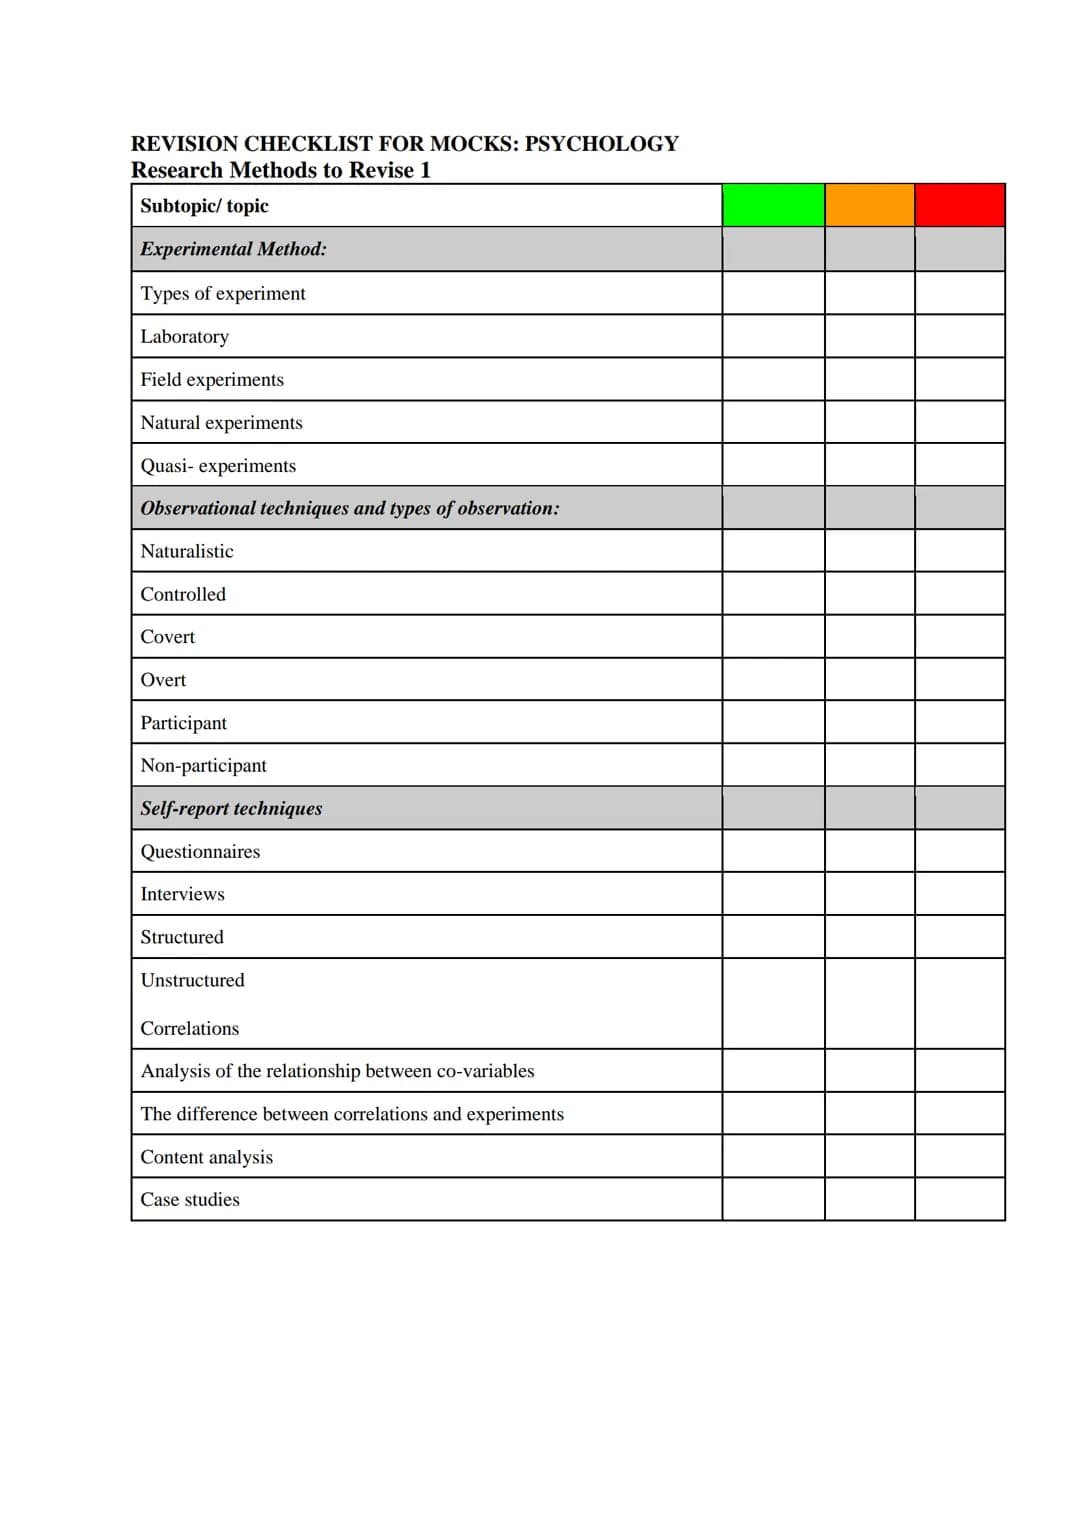
Building a practical Psychology Checklist Essential
I started using a structured checklist back in 2009 when I was running intake sessions for a community mental health clinic. We had turnover issues, new staff members forgetting basic screening steps, and insurance audits that flagged incomplete documentation regularly. The checklist didn't solve all of those problems, but it cut our documentation errors by roughly sixty percent within three months. That's the actual use case here: reducing errors under pressure, not building a philosophical framework for understanding human behavior. The Psychology Checklist Essential is really just a structured list of routine steps that clinicians or therapists follow during an assessment or session. It covers things like consent documentation, risk screening, goal-setting, and follow-up planning. Some people treat it like a rigid script, which is a mistake. The checklist should support your clinical judgment, not replace it. I've seen clinicians read from their checklists verbatim and it comes across as robotic and alienating to clients. The trick is memorizing the sequence well enough that you only reference it mentally.
What goes into a Psychology Checklist Essential
Most solid versions include these sections: Risk assessment items: Suicidal ideation screening, self-harm history, homicidal ideation, substance use, access to lethal means. This isn't optional. If you skip the risk screen on fifteen minutes of conversation alone, you're working without proper safeguards regardless of how warm and empathetic your session was. Consent and boundaries: Informed consent documentation, confidentiality limits explained, treatment expectations discussed, emergency contact obtained. Newer clinicians especially tend to rush through consent at the start of a session. It takes about ninety seconds to do properly and it protects you legally if something goes wrong later.
Presenting problem clarification: Chief complaint stated in the client's own words, onset timing, duration and frequency patterns, previous treatments tried, current stressors. Clients rarely volunteer the complete picture unprompted. A checklist reminds you to ask the follow-up questions that turn vague complaints into actionable case formulation material. Goal and treatment planning: At least one measurable short-term goal, estimated timeline, referral considerations if needed, next appointment scheduled before they leave. Without scheduling the next visit in the same session, no-show rates climb dramatically. Data from a few practice management studies suggest a gap of more than two weeks between sessions increases attrition by nearly thirty percent. Documentation requirements: Session notes completed the same day, billing codes verified, any mandatory reporting obligations addressed. I once had a client who disclosed abuse two weeks into treatment. I had documented the initial disclosures but failed to note the new information in my progress records until a month later. The gap looked suspicious during a license board review even though my intent was just sloppy record-keeping. This is the kind of failure a checklist prevents.
Get the Full Details

How to actually use it without sounding like a robot
Here's what works in practice. Keep the checklist on a tablet or printed card at your desk where you can reference it quickly between clients. Review it silently while the client is completing paperwork or settling in. Don't announce that you're going through a checklist. Just do it. During the session itself, weave the items naturally into conversation. Risk assessment doesn't have to sound like an interrogation when you frame it properly. Instead of asking "Have you had thoughts of suicide?" try "When things have been really heavy, have you ever felt like life wasn't worth living anymore?" The clinical content is identical. The delivery determines whether the client answers honestly. I run into a specific edge case with the checklist that people don't always anticipate. When a client is in acute crisis and pouring out trauma narrative, the last thing you want to do is stop and check off boxes. I keep a secondary abbreviated version for crisis sessions that includes only risk screening, safety planning, and documentation commitments. The full Psychology Checklist Essential waits until the acute intensity passes. You'll miss nothing important if you secure safety first and do the thorough assessment in the next session or toward the end of the current one.
Another nuance: the checklist should adapt to your modality. Cognitive behavioral therapists will weight goal-setting and homework assignment differently than psychodynamic clinicians who might emphasize transference observations and unconscious conflict identification. A one-size-fits-all checklist usually ends up satisfying nobody well. Build yours around your actual therapeutic orientation.
Pitfalls and where the checklist falls apart
Checklists create a false sense of completeness. Having checked every box doesn't mean you understood the client. I've sat across from people where I completed the entire assessment checklist in forty minutes but still had a fundamentally incomplete picture because I was going through the motions mechanically. The checklist should flag gaps in your understanding, not pretend they don't exist. There's also the documentation time problem. Adding checklist-based documentation typically adds eight to twelve minutes per session. In a busy practice seeing twenty clients daily, that's three to four hours of extra administrative work every week. Some clinicians respond by cutting corners on the actual clinical work to save documentation time, which defeats the whole purpose. If your caseload makes the full checklist impractical, consider using a streamlined version and reserving the comprehensive form for initial assessments and quarterly reviews. The biggest failure mode I've observed is checklist fatigue. After using a structured tool for several years, clinicians naturally begin skipping steps mentally. They think they remembered to ask about suicide risk when they actually didn't. The workaround is periodic peer review or case consultation where someone else checks whether your documentation actually matches what happened in the room. One colleague in my former clinic did this informally every Friday. It caught several genuine oversights over two years and reinforced good habits across the practice.
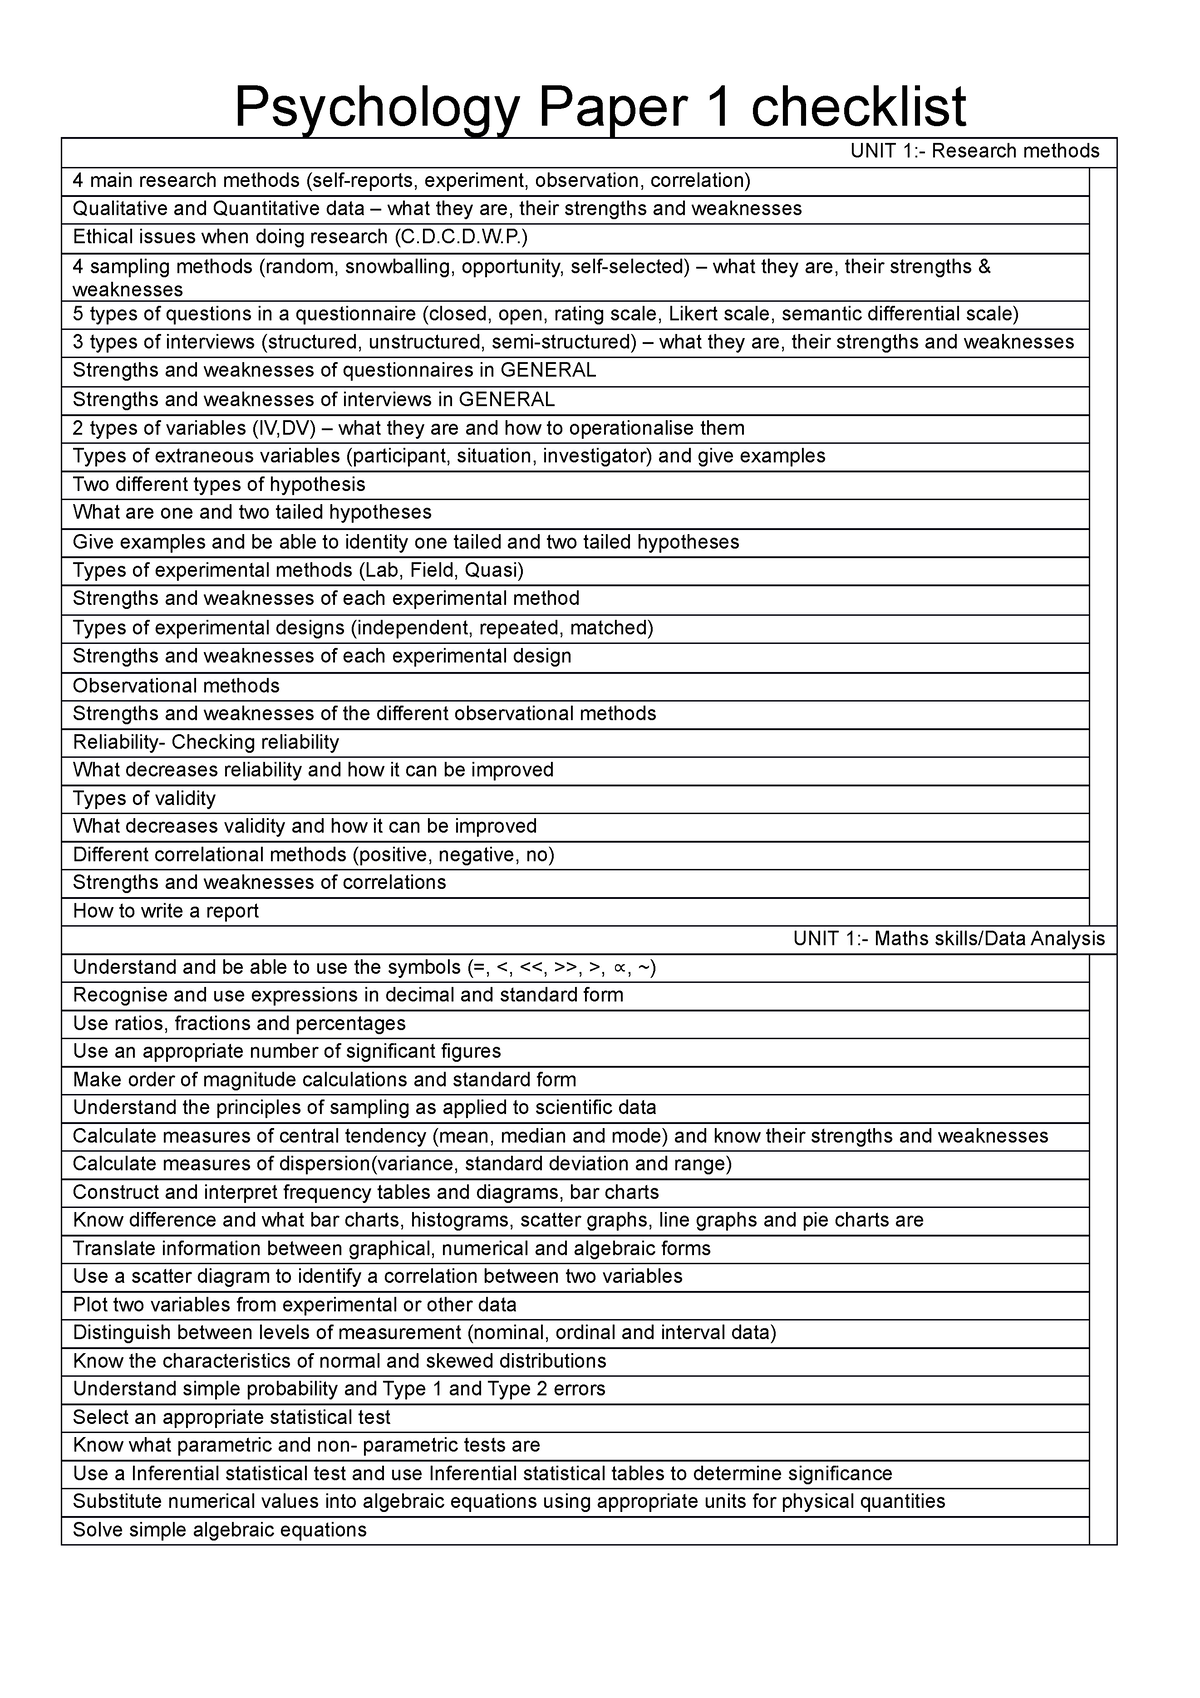
For clients with complex trauma histories or dissociative disorders, the standard checklist sequence can actually be triggering. Moving directly from intake paperwork into risk screening without adequate grounding and rapport establishment can shut down disclosure rather than encourage it. In those cases, I reverse the order somewhat, spending the first two or three sessions primarily on stabilization and psychoeducation before introducing the full structured assessment. The Psychology Checklist Essential still applies, just on a stretched timeline.
Getting started if you haven't built one yet
Look at your state or province licensing board requirements first. Most jurisdictions have specific documentation mandates that must appear in any functional checklist. These vary by location but typically include risk assessment, informed consent, and progress note standards. Your checklist needs to satisfy those minimums before you add anything else. Next, adapt an existing template rather than building from scratch. Organizations like the American Psychological Association and the National Register offer sample forms. Modify them heavily for your population and setting. A children's clinic checklist looks very different from an adult eating disorder program checklist even though the core structure overlaps significantly. Test the checklist with one or two clients before rolling it out fully. You'll discover which items are redundant, which ones you never actually use, and which critical steps are missing. Most clinicians spend about two weeks refining their first version before stabilizing on something that works reliably. That adjustment period is normal and expected.
The Psychology Checklist Essential isn't glamorous. It won't make you a better therapist by itself. But the structured consistency it provides reduces errors, protects your license, and frees up mental energy during sessions so you can focus on the actual therapeutic work instead of wondering whether you forgot to document something important. That's the real value proposition.