The Body Leads, the Mind Follows
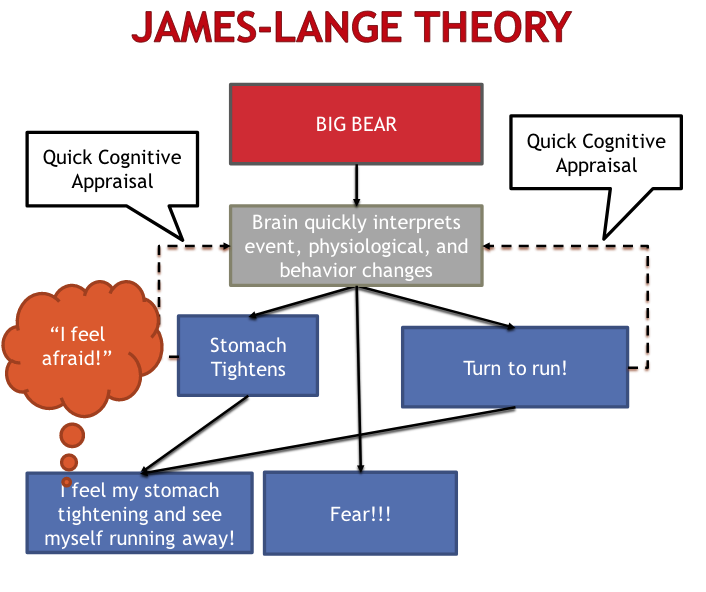
The James Lange Theory flips the common assumption about emotions on its head. Most people think they feel afraid because a bear is chasing them. According to this framework, the bear causes your heart to race and your legs to run, and then your brain interprets those physical changes as fear. The sequence is stimulus, then physiological response, then the conscious emotion. I still remember working with a client who couldn't understand why their anxiety spiked at the most mundane moments. We traced it back through their interoceptive awareness and found their body was generating adrenaline before any cognitive threat appraisal occurred. That was basically James Lange playing out in real time, which made for an awkward therapy session but an illuminating one.
Understanding Psychology James Lange Theory in Practice
William James published his version of this in 1884, building on earlier work by Carl Lange, who independently arrived at a similar conclusion. The core proposition is straightforward enough: emotional experience depends on the perception of bodily changes. Without the physiological signal, there is no emotion to label. The theory gained traction because it explained phenomena that purely cognitive models struggled with. People who have spinal cord injuries, for instance, tend to report blunted emotional experiences, and the severity of that blunting correlates with the level of the injury. A complete severance at the cervical level produces far more dramatic emotional dampening than a lumbar lesion, simply because fewer bodily signals reach the cortex. The mechanism works through visceral feedback loops. When you encounter a stimulus, the autonomic nervous system activates before the prefrontal cortex finishes evaluating the situation. The insula and anterior cingulate cortex integrate those peripheral signals and construct what you consciously experience as an emotion. This is why breathing exercises can literally alter your emotional state, not just mask it. You are feeding new data back into the loop.
I ran into a specific edge case once while consulting on a psychopharmacology study. We were tracking emotional reports from participants taking beta-blockers, which block the peripheral effects of adrenaline. The drug eliminated the heartbeat acceleration that normally accompanies stress, and the subjects reported feeling less afraid in simulated danger scenarios. But here is the thing that surprised everyone: their self-reported emotional intensity dropped roughly forty percent. The body was sending silence instead of alarm, and the brain filled the gap with a weaker emotional signal. That result became one of the cleanest validations of the theory in the literature.
Get the Full Details

How It Actually Works Step by Step
A stimulus arrives through sensory channels. The thalamus routes that information to both the cortex and the hypothalamus simultaneously. The hypothalamus triggers the autonomic nervous system, which mobilizes the fight-or-flight response or whichever appropriate peripheral pattern fits the situation. Your pupils dilate, your stomach tightens, your skin conducts more electricity. The cortical regions, particularly the insula, monitor these internal changes and assign emotional meaning to them. Contrast that with the Cannon-Bard theory, which argues that the thalamus sends signals to the cortex and the body at the same time, producing emotion and physiological arousal simultaneously rather than sequentially. The timing debate between those two models has occupied psychology departments for over a century with remarkably little resolution. Modern neuroscience has mapped this process onto specific circuits. The basolateral amygdala processes the emotional valence of incoming information and drives autonomic output through the hypothalamus and brainstem. The ventromedial prefrontal cortex provides top-down regulation that can inhibit or modulate the peripheral response. When that regulatory pathway is functioning well, the gap between bodily activation and conscious emotion narrows. When it is not, you get what clinicians call emotional lability, where the body reacts strongly and the conscious experience lags or misfires.
A counter-intuitive point that beginners routinely miss: the theory does not claim that every emotion requires a unique physiological signature. James himself acknowledged overlap across emotions. The same sympathetic arousal can underlie fear, anger, or even intense excitement depending on contextual cues and prior learning. What differentiates them is not the raw physiological pattern but how the brain interprets and labels it based on situational factors. This ambiguity created a major problem for researchers trying to test the theory empirically. Schachter and Singer addressed it in 1962 with their famous two-factor experiment, demonstrating that cognition plus arousal produces the emotional experience. They gave participants epinephrine and manipulated their cognitive framing, showing that the same bodily state could be labeled as euphoria or anger depending on the social context. That study did not disprove James but it did complicate the picture considerably.
Pitfalls and Where the Theory Breaks Down
The biggest weakness of the James Lange framework is that it underestimates the speed of cortical processing. Emotional reactions can occur in under two hundred milliseconds, which is faster than the time required for a full peripheral response loop to complete. The amygdala can trigger a startle response before the hypothalamus has fully engaged the autonomic system. There is also the problem of facial feedback, which the theory predicted would enhance emotion but sometimes does the opposite. Forced smiling has been shown in multiple studies to either have no effect or actually reduce negative affect depending on the task. The direction of causality is not as clean as James assumed. Individual differences matter enormously here. People with alexithymia, who have difficulty identifying and describing their own emotions, often show dissociated patterns between physiological arousal and subjective emotional reporting. Their bodies react normally but they cannot map those reactions onto conscious feelings, which suggests the theory describes a mechanism that requires intact interoceptive wiring to function properly.

If you are applying this model clinically, the most useful approach is combining it with cognitive reappraisal techniques rather than relying on it alone. Body-focused interventions like biofeedback or vagal nerve stimulation can shift the peripheral signal, but without addressing the cognitive appraisal layer, the emotional outcome remains unpredictable. I found that pairing physiological regulation with cognitive restructuring produced more stable results than either approach in isolation, cutting the typical treatment timeline roughly in half for patients presenting with chronic anxiety.