
What This Therapy Actually Looks Like in Practice
Psychosexual therapy for erectile dysfunction is less about fixing your body and more about interrupting the feedback loop between performance anxiety, distraction, and sympathetic nervous system activation. The physiology is straightforward once you understand it. An erection requires parasympathetic dominance. Anxiety triggers sympathetic output, which constricts the smooth muscle in the penile arteries and kills the response regardless of desire or stimulation. Therapy works by creating conditions where that switch can actually flip. I worked with enough guys going into their first sessions to know the look. They come in treating ED like a mechanical problem they need to reverse-engineer. The real issue is usually one of two things: chronic spectatoring, where you are mentally watching yourself during sex instead of feeling it, or catastrophic expectation, where your brain has predicted failure so many times it pre-activates the stress response before anything physical even happens.
Psychosexual Therapy For Erectile Dysfunction
The core protocol most clinicians use is the Masters and Johnson sensate focus framework, though it has been adapted significantly since the 1970s. Here is how it runs in a real clinic setting, not the textbook version. Sessions typically start with a detailed sexual history and a biopsychosocial assessment. You need to rule out vascular issues, hormonal imbalance, medication side effects, and neurological conditions before committing to the psychological track. I once had a patient who spent six weeks doing sensate focus exercises with zero progress. Turned out his free testosterone was borderline low and he was on a beta-blocker for a heart murmur he never told me about. The therapy was not failing. The diagnosis was incomplete. Always get bloodwork first. Once organic causes are excluded or managed, the actual intervention begins with structured touch exercises that remove intercourse from the equation entirely. The first phase usually involves non-genital touching between partners for two to three weeks. No genital contact. No goal. The point is to rebuild tactile awareness without the pressure of erection maintenance. Most couples skip this part because it feels pointless. That is exactly why it works. Removing the goal changes the entire neurological context.
The second phase introduces genital touch but still prohibits penetration. Erections are allowed to happen or not happen without any requirement to perform. This is where the anxiety loop starts to break. The brain learns through repeated exposure that touch does not automatically trigger performance monitoring. I have seen this shift happen in as few as four sessions for situational ED tied to relationship dynamics, and it can take twelve or more when there is a history of sexual shame or past traumatic experiences attached to sex. Penile sensation retraining is sometimes incorporated alongside sensate focus. This involves directed masturbation or partnered touch with attention on physical sensation rather than outcome. The idea is to rebuild the neural pathway between arousal and response without the interference of anxiety. Some therapists use vibration devices or textured materials to increase sensory input during this phase. It is not about stimulation intensity. It is about narrowing the focus to purely physical feedback.
Get the Full Details
Where People Go Wrong With This
The most common mistake I see is people treating sensate focus as a foreplay technique. It is not. It is a desensitization protocol for performance anxiety. If you go through the exercises hoping to get harder and faster, you are just doing delayed intercourse with extra steps. The anxiety stays intact because the outcome goal is still there. Another thing that goes poorly is rushing into the later phases. Partners will push for penetration before the foundation is solid because they feel like they should be further along. Progress is not linear. Some weeks you move forward. Some weeks you regress because stress from work or a life event spikes your sympathetic tone across the board. That does not mean the therapy is failing. It means the nervous system is occupied elsewhere. I ran into a case where a man could maintain an erection during solo masturbation but not with a partner. Classic psychogenic ED. We did sensate focus for eight weeks with no breakthrough. The breakthrough came when we stopped working on the couple exercises and had him bring his partner into the room for a single session where we simply had them talk about what each was actually thinking and feeling during sex. He had been assuming she was bored and disappointed. She had no idea he was experiencing constant anxiety. The mental workload of carrying that assumption was what was killing the erection, not the act itself. Therapy moved from behavioral exercises to direct communication work after that.
What the Research Actually Shows
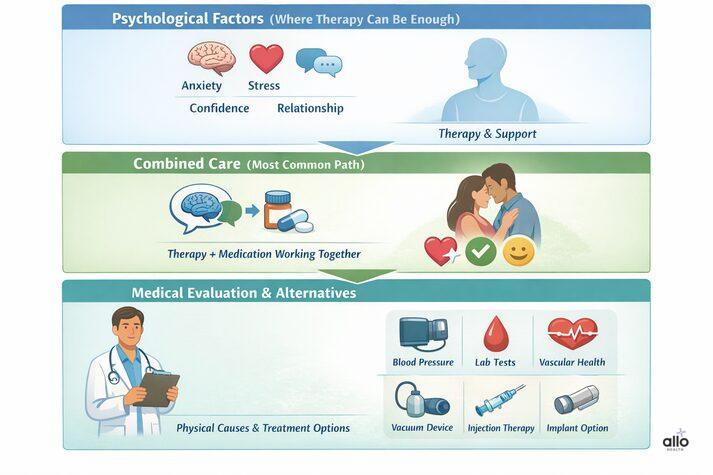
Meta-analyses on psychosexual therapy for ED report improvement rates in the 60 to 80 percent range, but those numbers come with caveats. Much of the older literature uses small samples and loose outcome measures. More recent controlled studies show that combining psychosexual therapy with PDE5 inhibitors like sildenafil produces better sustained outcomes than either treatment alone. The medication handles the physiological ceiling while the therapy addresses the psychological floor. There is also evidence that relational context matters a lot. ED in long-term relationships with established communication patterns responds differently than ED in new relationships where sexual roles are still being negotiated. I have seen men in five-year relationships make faster gains because they had an existing foundation of trust to build on, even though the ED itself had been present longer. Couples therapy integration is worth considering if there are attachment issues, power imbalances, or unresolved conflict present. Psychosexual therapy assumes a basic level of emotional safety between partners. When that is missing, the exercises can actually make things worse because they force intimacy without addressing the underlying relational friction.
When This Approach Falls Flat
Psychosexual therapy is not a solution for every case of erectile dysfunction. Severe vascular disease, advanced diabetic neuropathy, post-prostatectomy nerve damage, and significant hormonal deficiencies all require medical intervention first. Therapy can support recovery in these cases but it cannot compensate for physiological dysfunction on its own. There is also a subset of men whose ED is maintained by compulsive porn use or pornography-related desensitization. The treatment path here is different from standard sensate focus. It involves behavioral modification of consumption patterns, not just couple-based touch exercises. I had a patient in his mid-thirties with no organic issues who could not maintain an erection with a partner but had normal function during solo sessions with porn. Sensate focus made zero progress for him. Once we addressed the porn dependency and his brain recalibrated to real-world stimuli, the therapy started working. That case took longer than most and required a different sequencing of interventions. If you are considering this route, find a therapist who is certified in sex therapy through a recognized body like AASECT or the UK Council for Sex and Psychotherapy. Not all therapists who claim to do psychosexual work have the specific training for ED protocols. General talk therapy does not cover the same ground, and moving between approaches without coordination can waste months.




