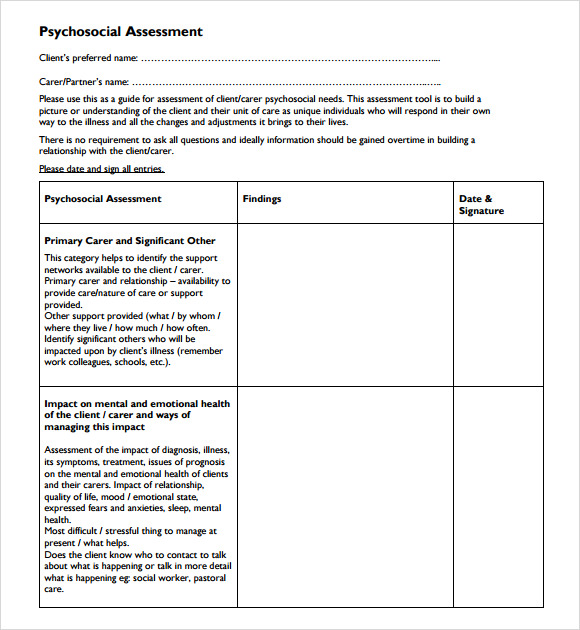
What a Psychosocial Assessment Actually Looks Like
A psychosocial assessment is a structured way of understanding a client's life situation across multiple domains. It is not a test, it is not a diagnostic tool by itself, and it does not produce a single answer. What it does is create a comprehensive picture that guides intervention planning. In practice, you spend 45 to 90 minutes gathering information across several areas, and then you synthesize it into a written document that becomes part of the client's permanent record. The format varies by agency and by jurisdiction. Some organizations use standardized templates with mandatory fields. Others give you a general framework and expect you to fill in whatever seems relevant. The underlying logic is roughly the same everywhere, though, and it rests on the biopsychosocial model that has been the backbone of social work practice for decades.
Understanding Psychosocial Assessment Example Social Work in Practice
Let me walk through what this looks like when you are actually sitting in a room with someone, or talking to them on the phone. The assessment typically covers seven to ten domains. You do not need to force every single one into every session, but you should have a plan to touch on each over the course of the engagement. Presentation and chief complaint is where you start. The client tells you why they are here. You record their words as closely as possible. Do not paraphrase too much at this stage because the exact language matters. If someone says they are "struggling to keep it together," that is different from saying they "cannot manage daily tasks." The clinical team will read your words later, and the phrasing shapes how they understand the situation. Presenting problems and symptoms comes next. You are documenting observable and reported issues. This includes mental health symptoms, substance use, physical health concerns, and any behavioral patterns that are causing difficulty. Keep it factual. Avoid interpretive language here. Let the later sections do the analysis.
Psychological functioning is where many people make mistakes. This is not just a checklist of diagnoses. You need to assess cognitive functioning, emotional regulation, coping skills, insight, judgment, and the client's own understanding of their situation. A client might have a schizophrenia diagnosis but demonstrate good insight into how medication affects their stability. Another client with no formal diagnosis might show significant impairment in executive functioning. Both require different approaches. Social functioning covers relationships, social support, isolation, and community involvement. I once worked with a client who had an extensive network on paper, but every relationship was transactional and conflict-driven. When I asked about who they actually turned to during a crisis, the silence lasted about forty seconds. That gap between social network size and social support quality is something no form can capture unless you ask the right follow-up questions. Environmental factors includes housing, income, transportation, neighborhood safety, access to services, and any systemic barriers. Housing instability alone can explain a cascade of other problems, or it can be one of many overlapping issues. You need to understand the hierarchy of stressors before you can prioritize interventions.
Get the Full Details

Family history and dynamics requires careful handling. Family can be a source of support or a source of ongoing harm. Some clients disclose trauma related to family systems during the assessment itself. You need to be ready to pause, check in, and possibly adjust the pace. This is not something you power through to finish the form. Cultural and identity factors are not an afterthought. Accurate assessment requires understanding how culture, religion, sexual orientation, gender identity, race, ethnicity, and disability shape the client's experience and their help-seeking behavior. A checklist item for "cultural background" does not accomplish this. You need contextual information.
The Documented Structure
Here is what a typical completed psychosocial assessment looks like in written form. I will use a composite case based on real work, not a copy of any actual document. Client: Maria G., female, 34 years old Date of Assessment: March 12, 2025
Referral Source: Intake screening by county mental health outreach team Presenting Concern: Client reports increasing anxiety, difficulty maintaining employment, and social isolation over the past six months. Notes that symptoms worsened following eviction from previous residence in January 2025. History of Present Illness: Symptoms began approximately eight months ago, initially presenting as sleep disturbance and worry about financial stability. Over time, client developed avoidant behaviors including declining social invitations and calling in sick to work without illness. Client sought emergency department visit in November 2024 for panic symptoms. Prescribed lorazepam PRN and referred to outpatient counseling. Client reports inconsistent attendance at therapy, attending approximately four of ten scheduled sessions.

Past Psychiatric History: No prior psychiatric hospitalizations. No history of suicide attempts. Client reports no previous diagnosis but describes childhood experiences of emotional neglect and an alcoholic parent. Client connects current symptoms to these early experiences during assessment. Medical History: Hypothyroidism, managed with levothyroxine. No known substance use. Client declined substance use screening, stating she does not use alcohol or drugs. Collateral information from pharmacy indicates consistent prescription fill history. No discrepancies noted. Strengths and Coping Resources: Client has a college degree in communications and previous employment history in administrative roles. Maintains contact with younger sister who lives in another state. Client expresses desire for stability and improvement. Attends religious services weekly, though reports feeling judged by congregation members regarding her current circumstances. Client has access to transportation through a community transit program for individuals with disabilities, though she has not yet applied for relevant documentation.
Risk Assessment: No active suicidal ideation, plan, or intent. No homicidal ideation. Client reports passive hopelessness but denies self-harm behaviors. Risk level: moderate. Safety planning discussed and client agreed to contact crisis line if thoughts escalate. Diagnostic Impression: Adjustment disorder with mixed anxiety and depressed mood, V-code for housing instability. Rule out generalized anxiety disorder. Recommend comprehensive psychiatric evaluation if symptoms persist despite intervention. Treatment Recommendations: Short-term CBT-based individual therapy focused on anxiety management and behavioral activation. Referral to housing stabilization program. Coordination with case management for employment support services. Follow-up assessment in thirty days.
Common Problems and How to Handle Them
The most frequent issue in psychosocial assessments is incomplete information. Clients do not always remember details, they may minimize problems, or they may not have encountered certain systems. I had a client who listed "employed" in the demographic section but could not describe what he did for work. He had been filling out job applications for eight months without securing a position. The field was technically accurate but functionally misleading. Always probe one level deeper. Another common problem is the temptation to overpathologize. When someone presents with homelessness, substance use, and a criminal record, it is easy to stack diagnoses and present the person as a collection of deficits. That approach produces a poor assessment and worse outcomes. I learned this early in my career by watching a colleague write a psychosocial assessment that read like a laundry list of problems with zero attention to the client's actual strengths or protective factors. The treatment team responded by lowering expectations rather than building a plan. The client was not motivated. It was a self-fulfilling prophecy. There is also the problem of assessing people who are not fully present. Some clients come to assessments in crisis, others are on medications that affect cognition, and some are simply exhausted by having to retell their stories repeatedly. I worked with a veteran whose assessment was compromised because he was experiencing untreated PTSD flashbacks during the interview. He would go quiet for several minutes and then return to the conversation as if nothing happened. We stopped the formal assessment and rescheduled. The second session produced usable data. Rushing through a compromised assessment wastes everyone's time because the resulting document requires revision anyway.

Language barriers present a different kind of challenge. Using a professional interpreter is essential, but the dynamics shift noticeably. Clients may disclose less sensitive information with an interpreter present than they would in a private conversation. They may also interpret the interpreter's presence as a lack of confidentiality. I have found that building rapport before launching into structured questions helps significantly. The first fifteen minutes of an assessment conducted with an interpreter often feels slower, but the quality of information improves substantially compared to starting with a barrage of direct questions.
What This Method Does Not Do Well
A psychosocial assessment is a snapshot, not a movie. It captures a moment in time and whatever the client is willing and able to share in that moment. It does not track changes over time. It does not replace ongoing clinical observation. If you treat the assessment as the final word on a client's situation, you will miss developments that occur after the document is filed. The method also depends heavily on the client's willingness to engage. Motivated clients with good insight and stable circumstances produce thorough assessments. Clients who are mandated to participate, who are experiencing acute psychosis, or who have significant cognitive impairments produce assessments that are either sparse or unreliable. There is no workaround for that except to note the limitation clearly in the documentation and plan for repeat assessment at a more appropriate time. Another limitation is the cultural bias embedded in many standardized assessment frameworks. The questions assume a particular understanding of family, employment, and mental health that may not apply across cultures. A client from a collectivist culture might describe family support differently than the form expects. A client whose concept of mental health is shaped by spiritual or religious frameworks may not map their experience onto DSM categories. Good practitioners account for this explicitly rather than forcing information into boxes where it does not fit.
Where to Find Standardized Templates
Most agencies develop their own forms, but several organizations publish widely used templates. The National Association of Social Workers does not provide a single standardized psychosocial assessment form, but many state licensing boards and hospital systems use variations of the biopsychosocial template. County mental health departments typically have their own required formats. If you are working in private practice, you may create your own based on these models. The core components remain consistent regardless of the template: identifying information, presenting problem, history, psychological functioning, social functioning, environmental factors, family history, strengths, risk assessment, diagnostic impression, and treatment plan. Any competent assessment covers these areas. The details vary. For a concrete Psychosocial Assessment Example Social Work document that you can adapt, search for templates from state mental health authorities or university social work programs. Many have open-access resources. The University of Michigan School of Social Work and the Boston University School of Social Work both publish assessment guides that include sample documentation. These are more useful than generic forms because they include commentary on what each section should contain and common errors to avoid.

The practical takeaway is that the assessment itself is only as good as the information gathered and the accuracy of the synthesis. A beautifully formatted document with vague or inaccurate content is worse than a rougher document with precise, well-observed detail. The latter helps a team make decisions. The former just takes up space in a file.

