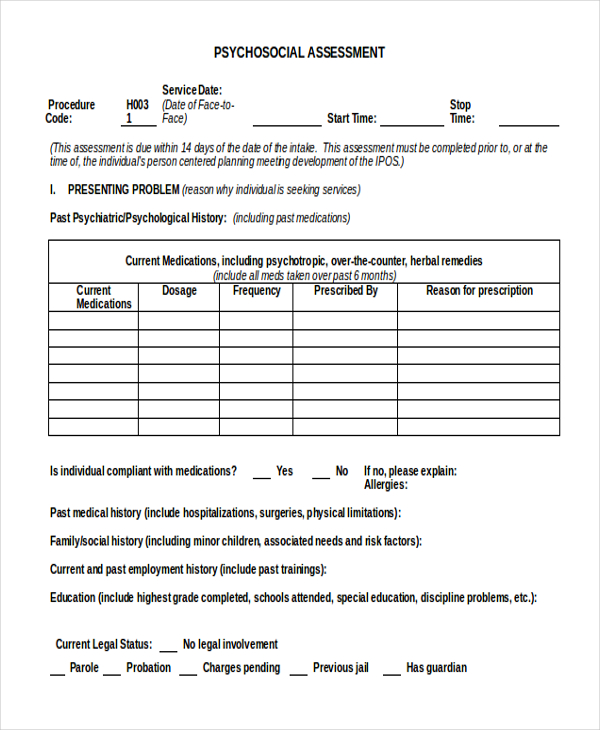
Why Most Psychosocial Assessment Templates Are Trash
The templates floating around the internet are usually copy-pasted from government PDFs that haven't been updated since 2009. They look professional but they're impossible to actually fill out without spending forty-five minutes reformatting fields. I've rebuilt at least a dozen versions of these because the standard format doesn't match how real clinicians work. A proper Psychosocial Assessment Template Word document needs to balance comprehensiveness with the reality that you'll be typing this while the client is sitting across from you. A solid template breaks into six sections: identifying information, presenting problem, psychiatric history, medical and substance use history, social and environmental context, and mental status exam findings. The trick isn't in the headings. It's in how the fields are laid out so you can move through them without constantly resizing text boxes or chasing formatting issues. I keep mine in a single-column layout with bold field labels followed by underlined spacing. That way I can type directly into the document during sessions instead of filling out separate forms later. Start with whatever baseline structure your agency requires. If you work in a state clinic, pull the most recent assessment form from your intranet. Private practice people should grab a standard DIAN or DSMT-style framework and strip out anything redundant. I remove the redundant questions immediately. If you're asking about substance use once, don't ask again three sections later under a different heading. Duplicate fields create inconsistent data and waste review time.
Set up your page layout before adding content. Use 11-point Calibri or Times New Roman. Set margins to 0.75 inches on all sides. That gives you enough room to write by hand if the client needs accommodations without pushing everything onto a third page. Your first version should fit comfortably on two pages. If it spills past page two, you've included too much fluff. Psychosocial assessments rarely need more than two pages unless you're documenting a forensic evaluation with supporting attachments. Here's where most people mess up. They build beautiful templates with nested tables and color-coded sections. Nested tables in Word break constantly. Colors distract readers. I learned this the hard way when a template I'd spent six hours refining turned into a formatting nightmare after someone opened it on a Mac with an older version of Office. The text boxes shifted, fields duplicated, and the whole document became unusable. Since then I avoid any formatting that isn't plain text with bold labels and standard table structures. Simple tables with one cell per field are fine. Three-level nested tables are a disaster waiting to happen.
Field-by-Field Breakdown
The identifying information section should capture name, date of birth, referral source, date of assessment, and assessor name. Add a line for case or file number if your setting uses tracking systems. Keep it to five lines maximum. Anything more clutters the top of the document without adding clinical value. The presenting problem section is where I see the most variation. Write one or two sentences describing why the person is being assessed right now. This is not the place for detailed history. Just the reason and the timeframe. Something like "Evaluation requested by outpatient counselor following three crisis presentations over eight weeks." Short. Specific. No drama. Psychiatric history needs subsections for prior diagnoses, previous treatment, hospitalizations, and current medications. I use bullet points under each subheading. Bullets are easier to scan during peer reviews and insurance audits than block paragraphs. For medications, always include dose, frequency, and prescribing provider. Omitting the prescriber name creates problems when you need to verify information later.
Get the Full Details

Medical history gets its own section. Chronic conditions, current diagnoses, and recent test results belong here. I also add a line for primary care provider contact information. It sounds minor but having that number saved in the assessment document saves phone calls during follow-up coordination. Substance use history should separate past use from current use. Include type of substance, frequency, route of administration, last use date, and any treatment episodes. The DSM-5 criteria for substance use disorders map cleanly onto this section. If you're comfortable with that framework, you can structure the questions around the ten criteria and note which ones apply. Social and environmental context covers family, relationships, employment, education, housing, and legal issues. This is the section that typically runs longest. I cap it by using bullet points and limiting each category to three to four lines. If someone has ten jobs in the past year, you don't list all ten. You note the pattern and summarize. Same principle applies to legal history. Document the charges and current status, not every courtroom appearance.
The mental status exam section deserves its own formatting treatment. I use a table with two columns: domain and findings. Domains include appearance, behavior, speech, mood, affect, thought process, thought content, perception, cognition, insight, and judgment. This visual separation makes it faster to write and easier for anyone reading the document to locate specific information quickly.
Technical Setup Details
Turn on auto-save. Word's cloud sync or manual save every five minutes will prevent the frustration of losing a completed assessment. Set up your default font style in File > Options > Advanced so you don't have to redefine it each time you create a new document. Configure your paragraph styles for consistent heading hierarchy. Use Heading 1 for main sections and Heading 2 for subsections. Screen readers and document reviewers both benefit from this structure. If you share assessments with other professionals regularly, convert your final template to PDF before sending. Word documents shift formatting across different versions. PDF locks everything in place. I keep both versions in the same folder. The Word file stays as the working template and the PDF becomes the shareable archive copy.

Common Pitfalls to Avoid
Using clinical jargon that the client or their family members won't understand. If you write "patient demonstrated circumstantiality with loose associations," rewrite it as "thoughts were tangential and difficult to follow." Plain language assessments serve everyone better, including the courts and insurance reviewers who may not have clinical backgrounds. Leaving fields blank and moving on. Every empty section raises questions during review. If a domain doesn't apply, write "not applicable" or "no history reported." Never leave a field completely blank. Blank fields imply missing information rather than intentionally excluded information. Writing narratives that go off track. I once spent forty minutes describing a client's childhood in the social history section when the actual reason for assessment was a medication evaluation. The narrative drifted because I was comfortable with that part of the document. Stay focused on what the assessment is for. Background information belongs there only if it directly relates to the clinical question.
One Specific Problem I Ran Into
I was using a template with a date field formatted as MM/DD/YYYY. A colleague reviewing the document entered dates in DD/MM/YYYY format because that's how they were trained. The system flagged three dates as invalid because month sixteen doesn't exist. This caused a delay in processing a referral. I switched all date fields to text format and added a note below each field specifying the required format. Now everyone enters dates consistently and there's no ambiguity. It took me ten seconds to fix but saved a week of back-and-forth communication later. A Word template works well for individual therapy evaluations and most outpatient settings. It does not scale for high-volume intake operations where fifteen assessments happen daily. In those environments, structured electronic forms with dropdown menus and validation rules perform better. Word templates require manual entry and manual consistency checks. If you're processing fifty assessments a week, spend the budget on a proper EMR or assessment platform instead of maintaining a Word document. The time savings from automation outweigh the setup cost within the first month of use. Another limitation: Word templates don't enforce completeness. There's no built-in warning if you skip the substance use section or forget to document suicide risk. Electronic systems can flag missing fields. Word cannot. You have to rely on your own review process or have a second clinician check the document before it goes into the record. That's an extra step that adds time but improves accuracy.
Getting Started
Create a blank Word document. Set your margins and default font. Build the six core sections using the heading structure I described. Add your field labels with bold formatting. Insert a simple table for the mental status exam. Test it by filling it out with a fictional client. Time yourself. If it takes longer than thirty minutes to complete, trim unnecessary fields. Repeat until the document feels fast to use. That's your finished template. Save it with a clear filename like Psychosocial_Assessment_Template_v1.docx. Version numbers matter because you will update this document. People will find older versions in shared folders and assume they're current. Naming conventions prevent that confusion. Share it with one or two colleagues and ask them to use it on actual assessments. Real-world usage reveals problems that simulation doesn't catch. Someone will point out a field they never use. Another will suggest adding a section you forgot. Incorporate useful feedback and create version 2. Keep iterating until the template matches how your team actually works. Then stop tweaking and start using it consistently.