How to Actually Fill Out a Psychosocial Assessment Without Losing Your Mind
A psychosocial nursing assessment is just a structured way to find out what is happening in a patient's life outside their physical symptoms. You are looking for stressors, support systems, coping mechanisms, mental health history, substance use, and cultural factors that affect their care. The form itself is usually straightforward, but the part where you actually get real answers is where most people struggle. I have spent more years than I want to admit watching nurses read questions off a clipboard and get zero useful data in return. Here is how I do it. I start with the presenting problem and work outward. If someone comes in with a diabetic ulcer, I am not just documenting their blood sugar levels. I am figuring out whether they can afford insulin, whether they have anyone to help them change dressings, whether they are drinking heavily, whether they have a history of depression that makes them indifferent to self-care, and whether they understand why any of this matters. A solid Psychosocial Nursing Assessment Example ties every behavioral factor back to the clinical plan.
What Goes Into a Psychosocial Nursing Assessment Example
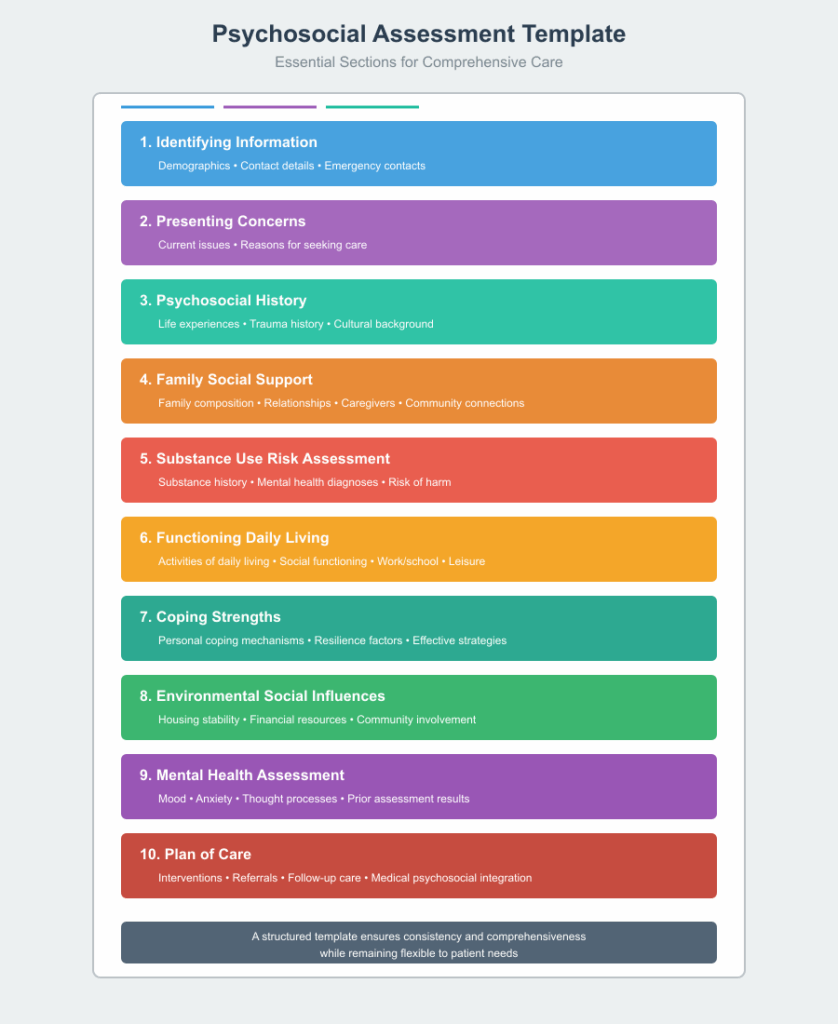
The core domains are fairly standardized across most hospital systems: Mental and emotional status: Mood, affect, thought process, insight, judgment, any history of psychiatric diagnosis or current medication. Are they oriented? Do they seem anxious, flat, labile, or appropriately reactive? Social support network: Who is actually in their life. Not just the name on an emergency contact card. I have seen patients list a sister who lives three states away and hasn't spoken to them in five years as their primary support. Ask who they would call at 2 AM. Ask who brings them groceries. Ask who actually shows up.
Living situation and functional status: Do they live alone? Is the home safe? Can they manage activities of daily living independently? Stairs? Stove? Getting to appointments? A patient recovering from hip replacement has a very different prognosis if they live in a fourth-floor walk-up with no elevator access. Substance use: Alcohol, tobacco, illicit drugs, prescription misuse. Be direct. "Do you drink alcohol?" gets better answers than "Have you ever had a problem with alcohol?" I once missed a benzodiazepine dependency because I used indirect language during a busy shift. The patient smiled and said they only took "sleeping pills" when stressed, which turned out to be three different prescriptions from three different doctors. Switched to asking specifically: "What helps you sleep at night?" and "What helps you relax during the day?" The picture came together in under a minute. Cultural and spiritual factors: Dietary restrictions, end-of-life preferences, family decision-making dynamics, traditional healing practices, health beliefs that may conflict with treatment. This is not checkbox stuff. A patient refusing a blood transfusion for religious reasons changes your entire perioperative plan.
Get the Full Details

Economic and educational factors: Health literacy level, insurance status, employment, ability to afford medications or medical equipment. I had a patient who kept "losing" their CPAP mask and never using the machine. It turned out they could not afford the replacement costs and were too embarrassed to say so. Once they admitted it, we got them a medical assistance program and the obstructive sleep apnea finally started getting treated properly. History of trauma and abuse: Domestic violence, past psychiatric hospitalizations, prior substance abuse, exposure to violence. Screen for this early but with care. The question should feel like a natural part of the conversation, not an interrogation.
The Practical Workflow
Most hospitals use a standardized form, often integrated into the EMR. The process usually takes between 20 and 40 minutes depending on patient complexity. On a busy medical-surgical floor, I typically complete it within the first four hours of admission, before the initial provider exam. That way the social work and case management teams can start their pieces in parallel rather than waiting for the assessment to be finished and filed. Here is the sequence I follow: 1. Review the chart for existing psychiatric history, current medications, and social work notes from prior admissions. This saves you from asking redundant questions.
2. Introduce the assessment to the patient as part of standard admission. Frame it as understanding their whole situation, not as an evaluation. Most patients respond better when they do not feel like they are being judged. 3. Start with open-ended questions and move toward specific domains. Let them talk. The first two minutes of unstructured conversation usually give you more useful information than the first ten closed questions on the form. 4. Document using the actual form fields. Do not paraphrase in your head and fill it in later. Memory fades fast during a 12-hour shift. Fill each section as you go.

5. Flag anything that requires immediate social work, psychiatry, or case management involvement. Suicidal ideation, active domestic violence, inability to care for oneself, suspected elder abuse — these are not "complete later" items. 6. Have the patient or a family member confirm key points. Especially around discharge planning. If you write that they are going home to a supportive family and they actually live alone with no visitors, the discharge falls apart at 3 PM.
Where This Goes Wrong
The biggest mistake I see is treating the psychosocial assessment as a paperwork exercise. It is not. It is a clinical tool. When nurses rush through it, they miss the signal. A patient who gives one-word answers to everything might be depressed. A patient who talks excessively about their hobbies might be masking anxiety. A patient who seems perfectly fine emotionally but keeps checking their phone every two minutes might be coordinating care for an aging parent back home and is quietly overwhelmed. Another common pitfall is assuming that what the patient tells you on admission is what stays true at discharge. People's situations change during a hospital stay. A son who seemed supportive on day one might reveal on day three that he cannot take the patient home because of his own medical condition. The assessment needs to be revisited, not just completed once and filed away. The tool also has real limitations. It relies heavily on patient honesty and self-awareness. Patients with cognitive impairment, acute intoxication, active psychosis, or significant health literacy barriers will not give you reliable psychosocial data through interview alone. In those cases, you pull from collateral sources — family members, prior records, medical social workers, and observation over time. No single assessment tool covers that gap perfectly.
If your facility does not have an integrated psychosocial screening protocol built into the EMR, consider pushing for one. Paper forms get lost. Free-text fields get skipped. Hardcoded required fields with dropdown options and branching logic ensure nothing gets accidentally bypassed. I worked at a unit where the psychosocial section was a two-page free-text add-on to the nursing admission sheet, and we had three adverse events in six months because substance use history was never documented. After we moved it into the EMR as a mandatory section, documentation compliance went from roughly 40 percent to 95 percent within three months. The clinical outcomes improved too, because the right services were actually being activated.

A Realistic Note on Downloadable Forms
You will find psychosocial assessment templates everywhere online, and most of them are fine as starting points. The ones from professional nursing organizations tend to be the most thorough. What matters less is the exact template and more is whether your form forces you to address every domain and captures actionable information rather than just checkboxes. A form that asks "Does the patient have social support?" with yes or no boxes is almost useless. A form that asks "Who provides transportation to appointments?" and "Who assists with medication management?" is functional. The goal is a document that actually guides your interventions and communicates clearly to the rest of the team. Everything else is decoration.


