What Actually Moves the Shoulder Back When It Is Stuck
Frozen shoulder is frustrating because it does not behave like a regular muscle strain. The joint capsule itself thickens and contracts, which means generic stretching routines often fail or make things worse if the timing is wrong. I have watched too many patients blast through a standardized YouTube routine for six weeks, only to discover their pain levels doubled and their range of motion shrank. The difference between progress and regression usually comes down to knowing which stage you are in and picking movements that respect the capsular pattern of restriction. The most effective approach targets the specific planes where adhesive capsulitis restricts you first. External rotation is almost always the first movement to go. If you cannot rotate your arm outward at all, you have a capsular pattern problem, not a rotator cuff problem. Pendulum swings come next because they are one of the few movements that actually do something mechanical rather than just irritating an inflamed joint. They create gentle traction across the glenohumeral space without forcing the capsule beyond its current limit. I had a patient last winter who came in after her physical therapist had been pounding her with cross-body stretches every session. She was already in the freezing stage with severe pain at night. The aggressive stretching was causing reactive inflammation that tightened the capsule further. I switched her to sustained low-load positions instead. She held a gentle external rotation stretch with a cane for thirty seconds, rested for twenty, and repeated it five times. No bouncing. No pushing through sharp pain. Within two weeks her night pain dropped by half and her external rotation improved by about fifteen degrees. The trick was stopping the irritation cycle before the capsule decided to tighten even more.
The Stage Matters More Than the Exercise
Adhesive capsulitis has three phases and each one requires a completely different strategy. The freezing stage is characterized by increasing pain and decreasing range of motion over roughly two to nine months. Aggressive stretching during this phase is counterproductive because the joint is actively inflamed. You work with pain-free motion only, stick to pendulums and gentle gravitational assists, and protect the shoulder from painful impingement positions. The frozen stage brings less pain but severe stiffness that persists for four to twelve months. This is when you introduce loaded stretching, continuous passive motion devices if available, and more aggressive mobilization. The thawing stage is when range slowly returns on its own, but the process can take another twelve to months without intervention. Most people skip straight to aggressive stretching without recognizing which stage they are actually in. They feel stiff and assume stretching will fix it. Painful stiff is a different signal entirely.
Specific Exercises and How To Actually Do Them
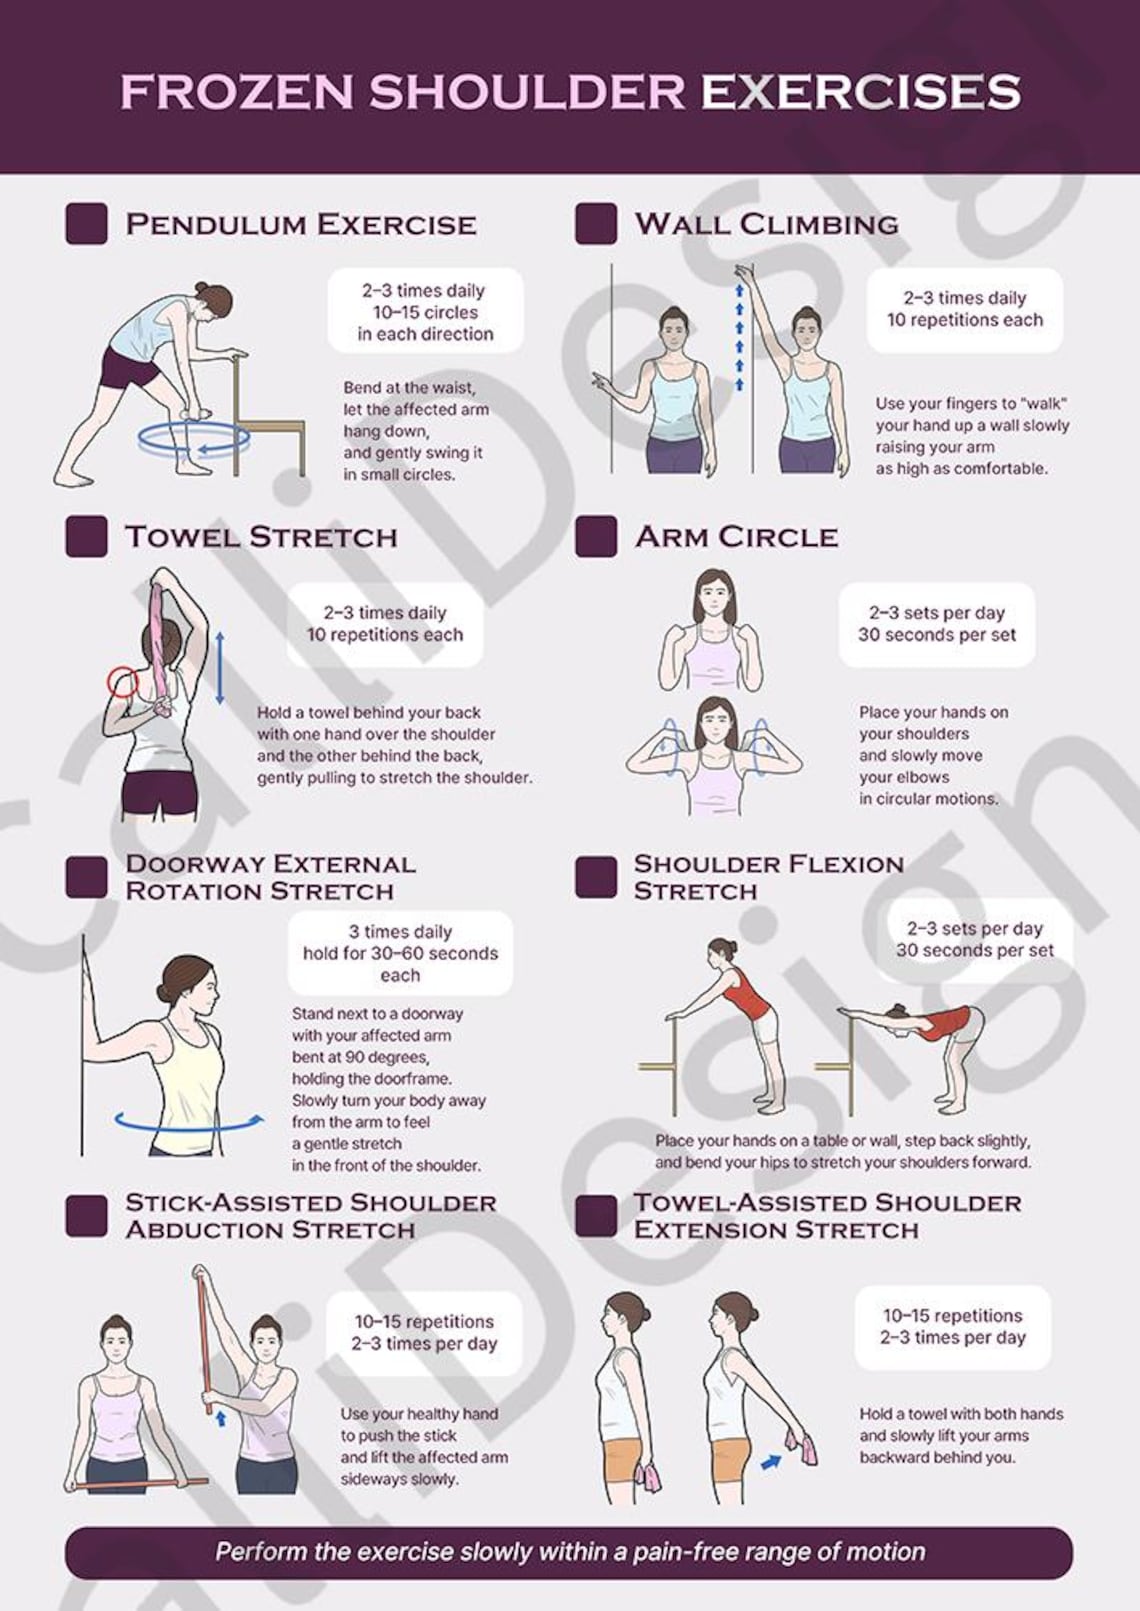
Pendulum exercises are deceptively simple. Lean forward, support yourself on a table with your good arm, and let the affected arm hang straight down. Use your body weight to create a small circular swinging motion. The goal is not to swing wildly. You want micro-movements that create joint play. Ten minutes twice daily is enough. Anything more just creates bursitis in the subacromial space. Towel behind the back stretches target internal rotation and extension, both of which are severely restricted in frozen shoulder. Hold a towel vertically behind your back with your good hand gripping the top and your affected hand gripping the bottom. Pull upward gently with the good hand until you feel a stretch in the back of the affected shoulder. Hold for thirty seconds. Repeat three times. This is a capsular-specific stretch for the posterior-inferior capsule, which is almost always the tightest area. Cross-body adduction stretches the posterior capsule directly. Pull your affected arm across your chest with your other hand, holding behind the elbow, not the wrist. Wrist grips change the lever arm and put stress on the shoulder joint unnecessarily. Hold for thirty seconds. Three repetitions. Do not bounce. Bouncing triggers the stretch reflex and the capsule tightens back immediately.
Get the Full Details

External rotation with a stick is probably the single most important exercise. Lie on your back with your affected arm at your side, elbow bent at ninety degrees. Hold a stick or broom handle with both hands. Use your good arm to push the affected arm upward toward the floor, creating external rotation at the shoulder. The supine position removes gravity from the equation, which means you can use less force and still get more stretch. This matters because the less force you use, the less protective muscle guarding you trigger. Hold for thirty seconds. Three repetitions. Progress to two minutes as tolerance allows.
What Most People Get Wrong
The biggest mistake I see is treating frozen shoulder like a flexibility problem. It is not. It is a capsular contracture with an inflammatory component that shifts over time. Passive stretching alone without addressing scapular mechanics leaves the glenohumeral joint unable to move properly even when the capsule loosens. Scapular upward rotation and posterior tilting are prerequisites for full overhead motion, and patients in the frozen stage rarely achieve either. Another common error is relying solely on home exercises without supervised manual therapy. Capsular stretches require a specific direction and magnitude of force that is difficult to self-administer accurately. A skilled therapist can perform grade III and IV glenohumeral joint mobilizations that reach posterior and inferior capsular segments no amount of towel stretch will access. These grades of mobilization involve oscillatory movements within the available range of motion without forcing beyond it. They are technically straightforward but clinically significant. Without them, home exercise programs plateau quickly. I also notice patients pushing into sharp, stabbing pain and calling it normal. That is not normal. Sharp pain means you are compressing structures that should not be compressed at that angle. Dull ache and stretching sensation are acceptable. Sharp pain is tissue damage. The distinction matters more than most people realize because repeated microtrauma from incorrect stretching extends the freezing stage indefinitely. Patients who make this mistake regularly add four to eight months to their recovery timeline.
When Exercises Are Not Enough
Some cases simply do not respond to conservative management within a reasonable timeframe. If you have maintained a consistent exercise program for twelve to sixteen weeks with no meaningful improvement in range of motion, further stretching becomes diminishing returns. Manipulation under anesthesia or arthroscopic capsular release are the next steps. These procedures address the actual contracted capsule directly rather than trying to remodel it through tensile load over many months. Corticosteroid injections into the joint capsule can break the inflammatory cycle in the early freezing stage and create a window where exercises actually work. Without addressing the inflammation first, stretching exercises mainly feed the inflammatory response. The injection reduces synovial inflammation and capsular vascularization, which allows the capsule to begin remodeling without constant irritation. Diabetics and thyroid patients face a harder road regardless of which treatment path they choose. Recovery timelines are longer, recurrence rates are higher, and the capsule tends to recontract even after surgical release. Setting realistic expectations early prevents unnecessary frustration and repeated failed interventions.

A Practical Weekly Structure
Morning: pendulum swings for five minutes, towel stretch behind the back for three sets of thirty seconds, external rotation stick stretch for three sets of thirty seconds. Afternoon or evening: cross-body adduction stretch for three sets of thirty seconds, scapular retraction and depression holds for ten repetitions holding five seconds each. Rest days are fine. The capsule does not need daily aggressive loading. It needs consistent gentle loading over time. Six days a week minimum. Eight weeks minimum before expecting measurable change. Most people quit around week three because they expect results that the biological timeline does not support. The exact protocol will vary depending on your stage, comorbidities, and how your shoulder responds week to week. But the underlying principle stays the same. Respect the pain. Match the intensity to the stage. Prioritize external rotation and posterior capsular stretches. Add scapular control. Stop pushing into sharp pain. Get manual therapy if you can access it. Be patient for at least three months before declaring anything a failure.