
Navigating Pt Ot Speech Therapy When You Actually Need It
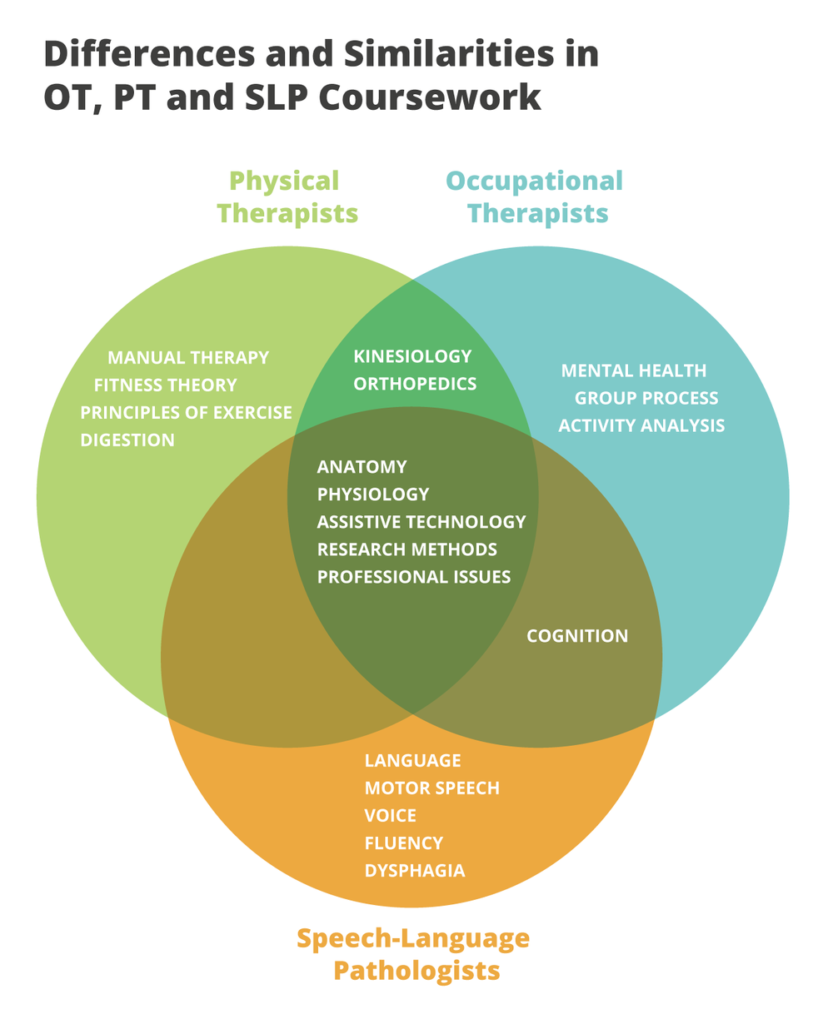
You get discharged from the hospital with a stack of paperwork and three referrals you don't understand. Physical therapy, occupational therapy, speech therapy. They're lumped together sometimes as Pt Ot Speech Therapy on billing forms, which makes them look like one service when they're completely different disciplines. I've spent years coordinating these for patients and families, and the first thing I always say is that knowing how they overlap and where they diverge will save you weeks of back-and-forth. Physical therapy focuses on movement, strength, balance, and mobility after injury or surgery. Occupational therapy deals with ADLs — activities of daily living — like dressing, cooking, eating independently, and returning to work. Speech-language pathology handles swallowing disorders, language processing issues, cognitive-communication deficits, and yes, actual speech production problems. They share a common origin in rehabilitation medicine but their day-to-day work is very different. The confusion starts at the insurance level. Many plans bundle these under a single outpatient rehab benefit with a visit limit, sometimes 20 to 60 visits per year. That cap applies across all three disciplines combined, not per discipline. I had a patient last year who maxed out his 30-visit benefit on physical therapy alone and then couldn't access speech therapy for his dysphagia because the bucket was empty. We ended up switching him to a different plan mid-year through a hardship exception, but it took six weeks of appeals.
How to Actually Get Started
Start with the referral. Most insurance plans require a physician's written order before a therapist will accept a new patient. That order should specify which discipline you need and the diagnosis code. Don't leave it vague. "Lower extremity strengthening" gets you physical therapy. "Difficulty swallowing and word-finding" gets you speech therapy. If your doctor writes "rehabilitation services" without specifics, call around and you'll get bounced between clinics. Check your network. Not every clinic accepts every plan. Medicare Advantage plans in particular have narrow networks compared to traditional Medicare. A quick call to the clinic's billing department asking whether they accept your specific plan ID will save you from showing up and getting turned away. I've seen people drive an hour to a clinic only to find out they're out of network and the visit costs $200 out of pocket. When you show up for your first appointment, bring your imaging reports, surgical notes, and a list of current medications. Therapists need this context. The physical therapist needs to know you had a hip replacement six weeks ago. The occupational therapist needs to know you're on blood thinners so they don't push balance exercises too aggressively. The speech therapist needs to know about any cognitive changes from your stay in the hospital. This isn't optional administrative stuff — it changes the treatment plan.
Common Pitfalls Nobody Warns You About
The biggest issue I see is people treating these therapies as sequential when they often need to run concurrently. A stroke patient might need speech therapy for aphasia and physical therapy for hemiparesis at the same time. Scheduling them on alternating days isn't just convenient — research shows concurrent rehabilitation produces better outcomes for neurological conditions. But your insurance coordinator might not tell you this. You have to ask for it. Another problem is the home exercise program. Therapists give you sheets of exercises and you file them away. Then nothing happens. The evidence is clear that home program adherence directly correlates with discharge outcomes. I started having patients record themselves doing the exercises on their phone and sending them to the therapist via a secure portal. It took three seconds to set up and dramatically improved accountability. The therapist could see exactly where the patient was struggling and adjust the plan at the next session instead of waiting two weeks. Here's something most people don't realize: speech therapy isn't just for speech. If you've had a brain injury, stroke, or even prolonged intubation, you may need swallow evaluation (modified barium swallow study) and cognitive-communication therapy. I had a trauma patient who couldn't speak clearly because of velopharyngeal insufficiency from facial fractures, not because of an aphasia. He was sent to the wrong type of speech therapist initially because the referral just said "speech issues." Getting him to a specialist in neurogenic speech disorders changed everything. Three sessions and he had functional communication again.
Get the Full Details
What to Do When Therapy Isn't Working
If you've completed eight to ten sessions and you're not seeing measurable progress, request a re-evaluation in writing. Therapists are required by Medicare guidelines to reassess at least every 30 days, but you should push for it sooner if things aren't moving. Ask for the outcome measures they're using — the FIM scale, the Berg Balance Scale, the Western Aphasia Battery. These aren't just forms. They're standardized tools that tell you whether you're actually improving or just going through the motions. When I've hit a wall with a patient, the workaround is usually one of three things: switching therapists, changing the setting, or adding a different discipline. A patient who isn't progressing in a clinic environment might do better with home health therapy. Someone stuck on balance training might benefit from adding vestibular rehabilitation specifically. Sometimes the issue is simply that the therapist's specialty doesn't match your condition. There's nothing wrong with asking to be transferred. For severe cases that plateau, consider a comprehensive inpatient rehabilitation facility. These are different from skilled nursing facilities. IRFs provide three hours of therapy per day across multiple disciplines, seven days a week, with physician oversight daily. The threshold is that you must be able to tolerate that intensity. If you can't, it's not appropriate. But for eligible patients, the outcomes are substantially better than outpatient therapy alone, particularly for stroke and traumatic brain injury.
The bottom line is that Pt Ot Speech Therapy isn't a single service you opt into. It's a system of overlapping disciplines with their own referral paths, billing codes, and clinical boundaries. Figure out which one you actually need, verify your coverage before you commit, track your progress with actual measurements, and don't hesitate to push back when something isn't working. The system moves slowly unless you make it move.



