How Paclitaxel Coated Stent Therapy Actually Works In Practice
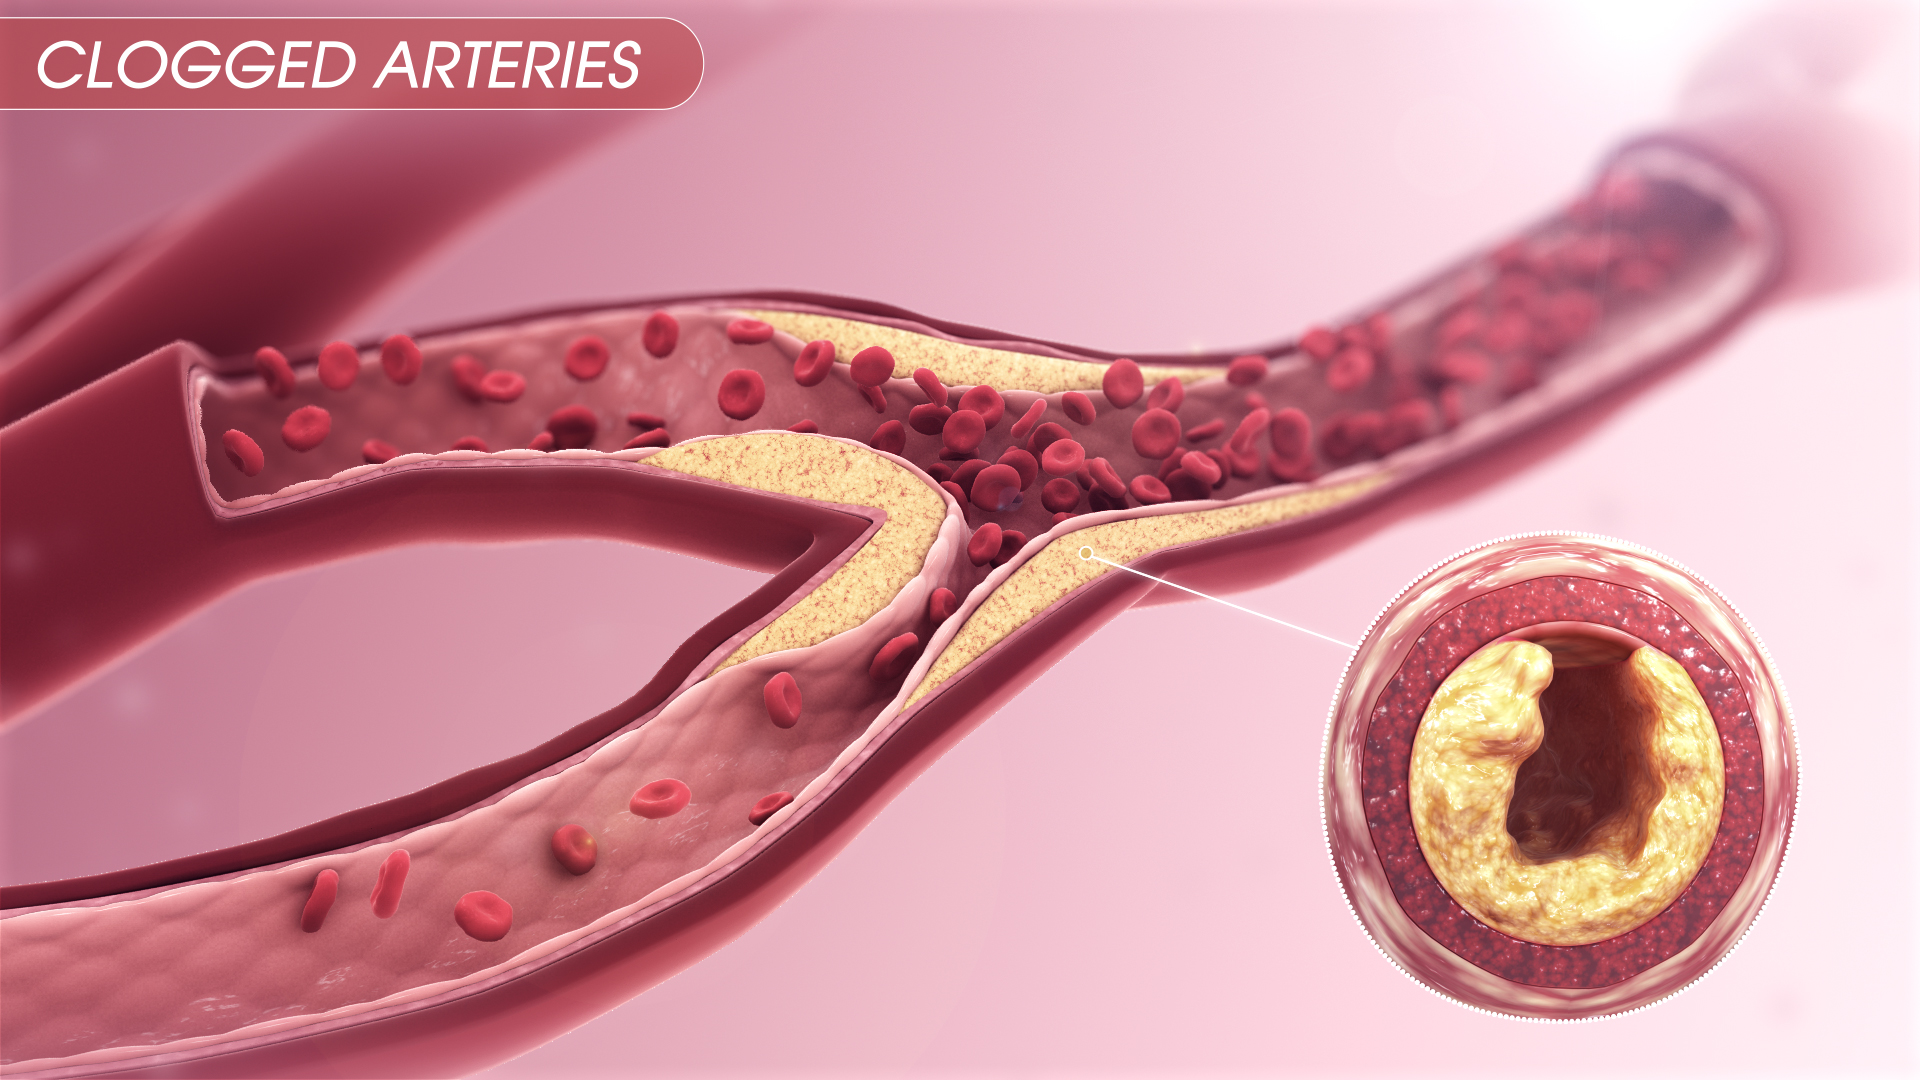
Paclitaxel therapy for clogged arteries centers on drug-eluting stents coated with paclitaxel, an antiproliferative compound originally developed for cancer treatment before someone figured out it also stops smooth muscle cells from overgrowing inside a stented vessel. That overgrowth is what causes restenosis, and it was the single biggest problem with bare-metal stents when they first came out. Patients would get a stent placed, feel fine for six months, then come back with the same chest pain because the artery had essentially re-blocked itself from the inside. When interventional cardiologists talk about Ptx Therapy For Clogged Arteries, they are referring to the use of paclitaxel-coated devices — either drug-eluting stents or, less commonly, drug-coated balloons — to deliver the medication directly to the arterial wall at the site of a blockage. The standard approach involves placing a balloon-mounted or self-expanding stent that has a polymer matrix containing paclitaxel on its outer surface. Once the stent is expanded against the arterial wall, the drug slowly elutes over a period that typically ranges from 30 to 90 days depending on the specific device formulation. During that window, the paclitaxel suppresses the proliferation of medial smooth muscle cells and fibroblasts that would otherwise lay down excessive extracellular matrix and narrow the lumen again. The mechanism is straightforward pharmacology. Paclitaxel binds to beta-tubulin and stabilizes microtubules, which locks cells in the G2/M phase of the cell cycle and prevents division. Smooth muscle cells are the primary culprits behind restenosis, and they are highly sensitive to this mechanism. The trick, and it is a real one, is getting enough drug into the vessel wall without washing it all away into systemic circulation or causing local toxicity that delays endothelial healing.
I spent years watching this evolve from the early Taxus stents through the second and third generations. The first paclitaxel-eluting stents used a polybutylmethacrylate copolymer as the drug reservoir. That polymer worked for delivering the drug but turned out to be a persistent foreign body that kept inflammatory cells around long after the paclitaxel had done its job. We started seeing late stent thrombosis more often than we liked, particularly in patients who stopped their dual antiplatelet therapy too early because the stent never seemed to fully endothelialize. That was the big lesson: keeping the artery open is only half the problem. Getting the vessel to heal cleanly on the inside is the other half, and paclitaxel actively fights against that healing process. The workaround that eventually emerged involved switching to more biocompatible polymers or going polymer-free entirely. Some newer paclitaxel devices use abluminal delivery systems where the drug is applied to the outside of a bare-metal scaffold and the polymer is minimized or eliminated. There are also biodegradable polymer coatings that shed the drug during the critical early period and then dissolve away, leaving behind a relatively clean metal surface. The clinical data generally shows similar or slightly better restenosis rates compared to the older sirolimus-eluting stents, with a slightly different risk profile rather than a clear winner. One thing most patient education materials don't emphasize enough is that paclitaxel-coated balloons, sometimes called DCB or drug-coated balloons, are now used for in-stent restenosis — meaning when a paclitaxel stent fails, you can treat the recurrence with a balloon that deposits paclitaxel directly onto the restenotic tissue without placing another stent. This is called a stent-less strategy and it has gained considerable traction in Europe over the past decade. The rationale is simple: if the problem with the first stent was chronic inflammation from the polymer, adding another stent with more polymer might just repeat the cycle. A DCB gives you the drug without the hardware.
There is a specific edge case I ran into repeatedly that deserves mention. In small vessel disease — arteries under 2.5 millimeters in diameter — paclitaxel-eluting stents show dramatically better results than bare-metal stents, but they still underperform compared to larger vessels. The problem is that smaller vessels have less total arterial wall mass to absorb the drug, so the relative concentration per millimeter of tissue is higher. This actually helps with restenosis suppression but it also means any delayed endothelial healing is proportionally more dangerous. I had a patient, roughly 2.3 millimeter distal left anterior descending artery, who developed a very late stent thrombosis at seven months because he had gone off clopidogrel after a dental procedure. The stent was a first-generation taxus with the persistent polymer. It was a narrow vessel, the drug had delayed healing, and the plaque rupture from the exposed struts triggered a full occlusion. He made it to the cath lab in time but it was close. After that case, I became much more aggressive about confirming dual antiplatelet therapy compliance in small vessel paclitaxel cases and much more reluctant to use first-generation devices in vessels below 2.75 millimeters. Modern polymer-free or biodegradable-polymer devices have reduced this risk considerably, but the principle remains: smaller vessels demand more careful patient selection and stricter antiplatelet management.
Get the Full Details
The Procedure And What To Expect
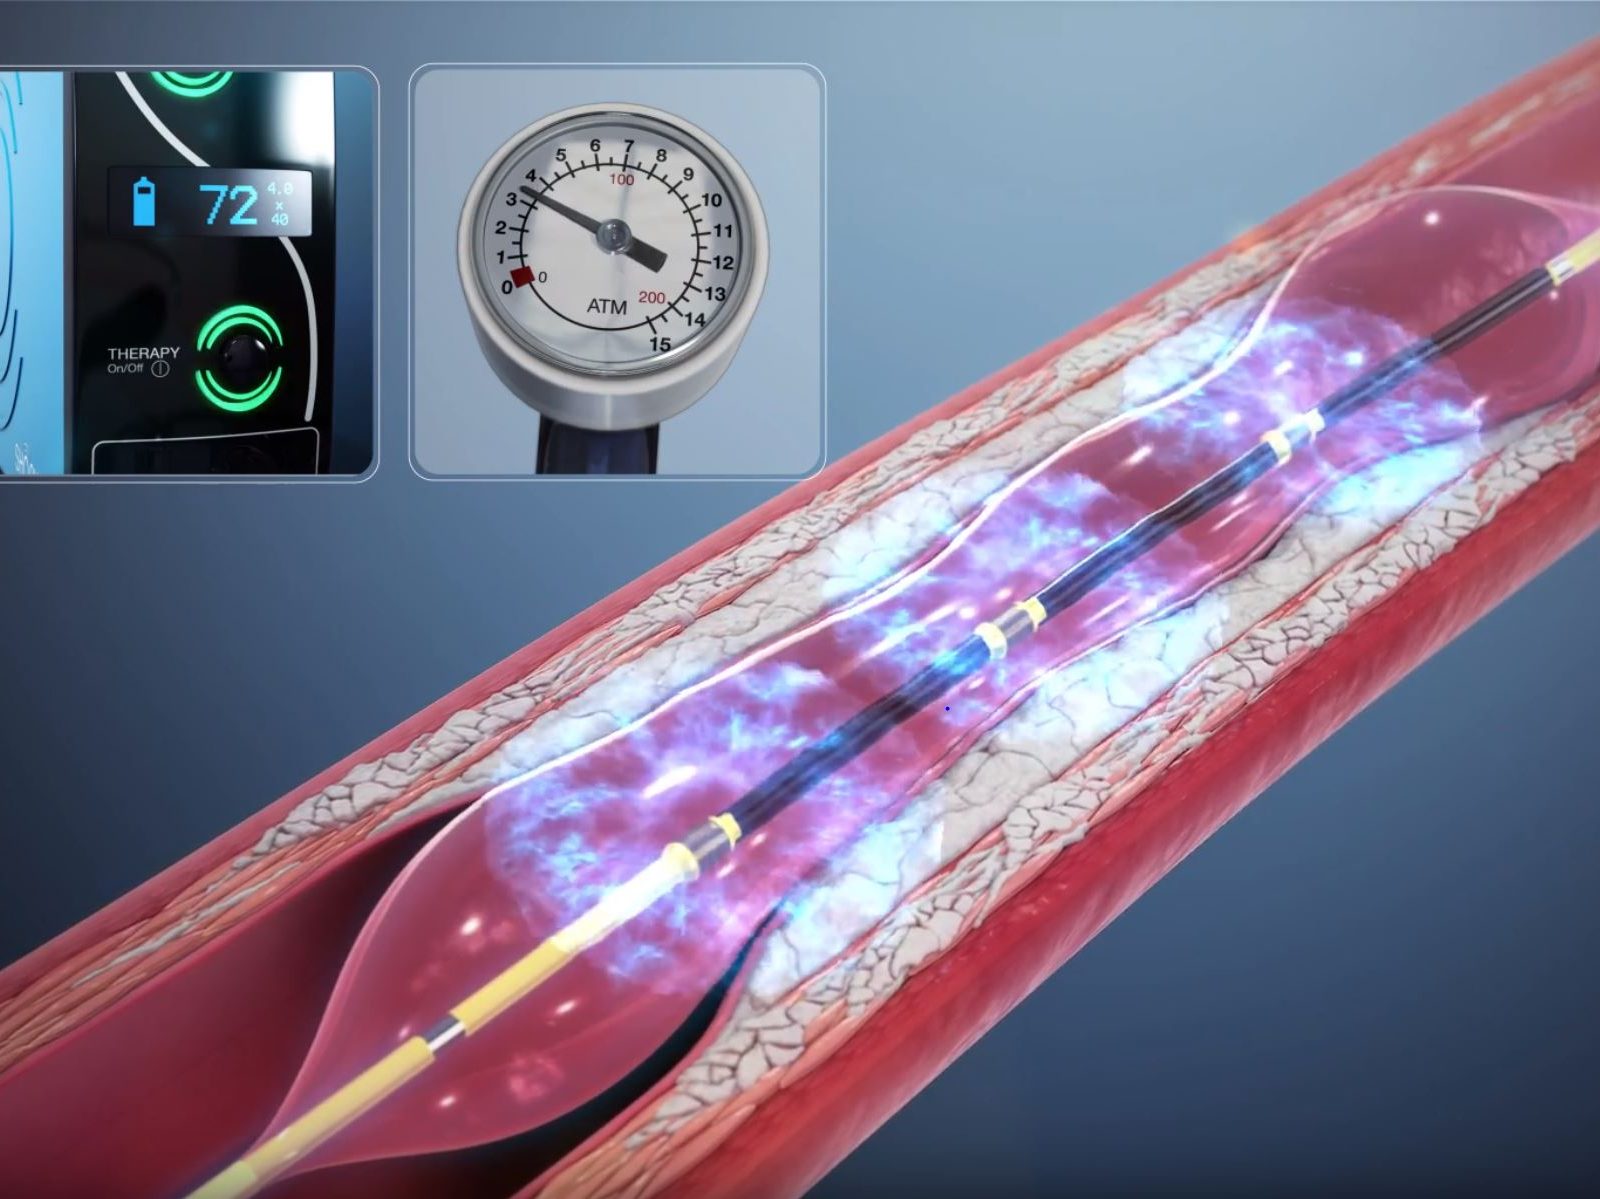
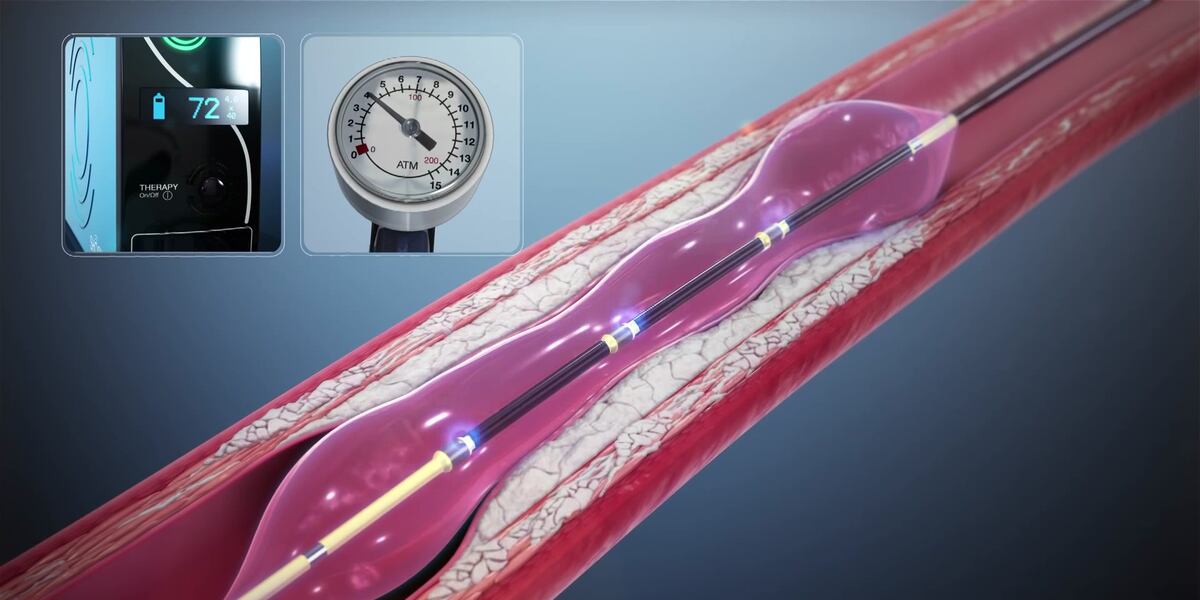
The actual procedural workflow for paclitaxel stent placement follows the standard percutaneous coronary intervention protocol with a few important modifications. You get femoral or radial access, cross the lesion with a guidewire, pre-dilate with a non-compliant balloon if needed, then deploy the paclitaxel-eluting stent at low pressures — usually starting around 8 to 10 atmospheres and only escalating if the stent is not fully expanded. Post-dilation is typically done with a non-compliant balloon at higher pressure, but you have to be careful because aggressive post-dilation can strip the drug coating from the stent surface before it has fully transferred into the vessel wall. The recommended post-dilation balloon diameter is usually no more than 0.5 millimeters larger than the stent nominal diameter, and inflation time should be kept short, around 30 seconds or less. For drug-coated balloon procedures, the technique is different enough that it bears explaining separately. You prepare the lesion with atherectomy or scoring balloon if there is significant plaque burden, then run the paclitaxel-coated balloon through the lesion at moderate pressure for exactly 60 seconds. That sixty-second window is not arbitrary — it is the time required for adequate drug absorption into the neointima. Deflate slowly over five to ten seconds to minimize recoil, then remove the balloon. No stent is left behind. The entire procedure typically takes 20 to 40 minutes depending on lesion complexity, and recovery is usually faster than with stent placement since there is no foreign body permanently implanted. The downtime after the procedure is the part patients struggle with most, and honestly it is unnecessarily alarming in some cases. After a paclitaxel-eluting stent, you are on dual antiplatelet therapy — typically aspirin plus ticagrelor or clopidogrel — for at least six to twelve months. The old guidelines pushed for a full twelve months across the board, but newer evidence supports shorter durations in low-bleeding-risk patients. Still, cutting DAPT short in a paclitaxel stent, especially in a small vessel or a complex lesion, is asking for late thrombosis. I see patients who feel fine at three months and want to stop the second pill. They can't. The paclitaxel is still suppressing cellular activity in the vessel wall, and the endothelial layer is incomplete. The stent struts are still essentially foreign material until that layer matures, which can take six to twelve months depending on the device.
There is also a lingering controversy around paclitaxel and systemic safety that deserves an honest look. Around 2020, several observational studies raised concerns about increased mortality with paclitaxel-coated devices, particularly in peripheral arterial disease. The data in coronary applications has been more reassuring, but the signal was strong enough that the FDA issued a warning and some manufacturers added boxed warnings to their labeling. Subsequent meta-analyses have largely clarified that the absolute risk, if it exists at all, is very small — on the order of a fraction of a percent over several years — and the benefit of preventing repeat procedures in diseased arteries far outweighs the theoretical risk for most patients. Still, it is a real consideration, especially in patients who already have high cardiovascular risk profiles and limited life expectancy. In those cases, a bare-metal stent or balloon angioplasty alone might be the more prudent choice, even with higher restenosis rates, simply because you are not exposing the patient to systemic paclitaxel absorption at all. The practical takeaway is that paclitaxel-based therapy for clogged arteries is a mature, well-understood technology with real trade-offs rather than a miracle solution. It has dramatically reduced the need for repeat interventions in suitable candidates. It is not suitable for everyone, particularly patients with high bleeding risk who cannot tolerate prolonged dual antiplatelet therapy, or those with very small vessels where the thrombosis risk is higher. If you are considering this, the questions that actually matter are: what size is your vessel, what type of lesion are you dealing with, and can you commit to the antiplatelet regimen. Everything else is secondary.