What Puberty Actually Looks Like When You're Living Through It
I spent three years working as a school counselor, and the thing I learned fastest is that puberty doesn't arrive the same way to every kid. The textbooks make it sound like a timeline you can clockwork predict. It isn't. Some boys hit their growth spurt at twelve and are towering over their classmates by thirteen. Others don't bud until fifteen and spend two years getting picked last for everything. Girls are the same story. Early bloomers deal with a whole different social minefield than kids who start later, and neither experience is wrong or better. They just exist. The medical term for this phase is adolescence, spanning roughly ten to eighteen years old, but nobody going through it feels like they're hitting a textbook milestone. They feel confused, sometimes frustrated, occasionally thrilled, and mostly just trying to figure out why their body is doing things without asking permission first.
Understanding Puberty In Boys And Girls: The Biological Machinery
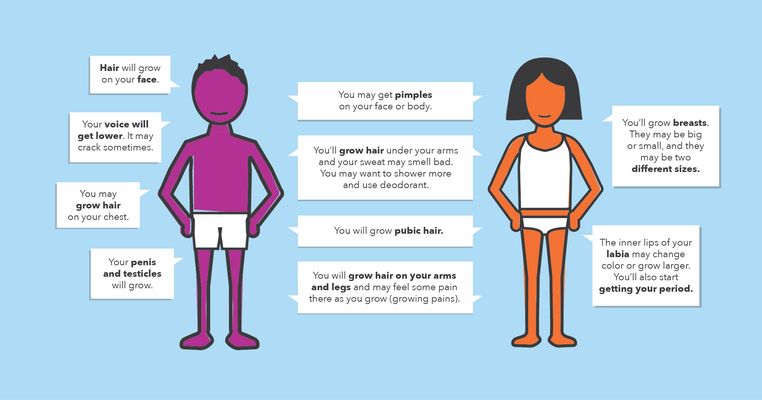
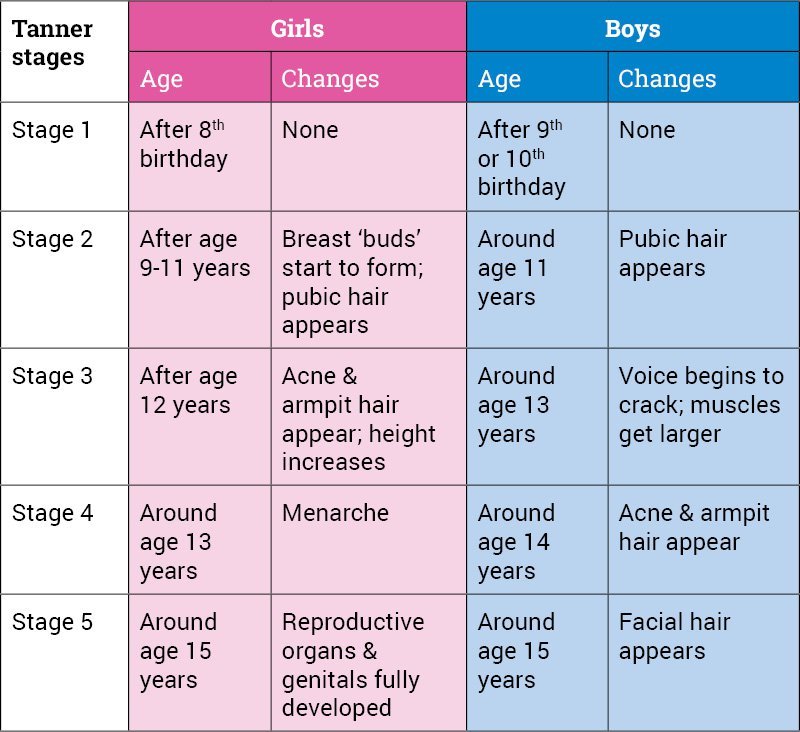
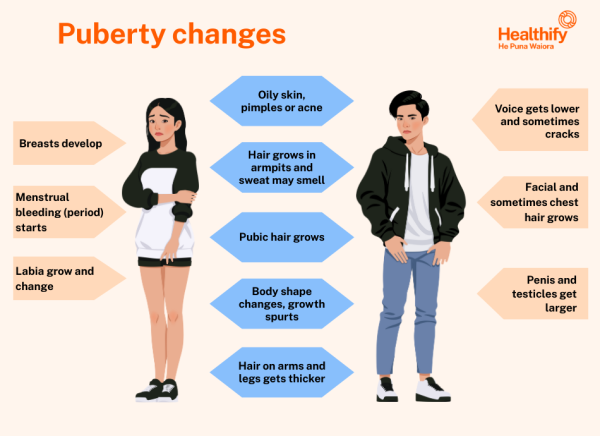
At its core, puberty is the body shifting from a child's hormonal profile to an adult one. The hypothalamus, a small region at the base of the brain, starts releasing gonadotropin-releasing hormone in pulses. That signals the pituitary gland to pump out follicle-stimulating hormone and luteinizing hormone. Those two hormones travel to the gonads and tell them to start producing sex steroids. In boys, that's testosterone. In girls, it's primarily estrogen and progesterone. Here's where most people get it wrong. The timing of when this cascade begins matters more than the mechanics. The average age for girls to start showing signs is around ten years old. For boys, it's closer to eleven. But the normal range is wide. A girl starting at eight is on the early side but still within typical bounds. A boy not showing any change until fourteen usually isn't a cause for alarm either, though worth a checkup. I once worked with a kid who was fourteen and hadn't entered puberty at all, and his pediatrician caught a treatable hormonal issue. Early evaluation doesn't hurt, even when the kid seems fine otherwise. The physical changes in boys include testicular enlargement as the first sign, followed by pubic hair, growth of the penis, voice deepening, facial and body hair, muscle mass increasing, and acne appearing. Growth peaks around fourteen to fifteen but can extend into the late teens. In girls, breast development is usually the first visible change, typically starting between eight and thirteen. Pubic hair follows. Menarche, the first period, averages around twelve to thirteen but can happen anywhere from eleven to fifteen and still be normal. Hip widening and body fat redistribution happen during this window too.
What Nobody Tells You About the Emotional Side
The hormonal surge doesn't just remodel bodies. It remaps moods and emotional responses. I remember one girl, fourteen, who came into my office crying because her best friend had stopped talking to her. The friendship hadn't ended over anything dramatic. She'd gained weight during a growth spurt, felt self-conscious, and pulled away gradually. Her friend didn't notice or didn't know how to address it. The girl's emotional reaction was intense, but it wasn't irrational. Her brain was literally processing social rejection differently because of estrogen fluctuations interacting with a prefrontal cortex that hadn't finished developing. That's the part parents and even some teachers miss. Kids aren't being dramatic. Their nervous systems are under construction. The amygdala, which handles emotional responses, matures faster than the prefrontal cortex, which handles impulse control and rational decision-making. This gap means teenagers can feel things more intensely than they can regulate them. It's not a personality flaw. It's biology. Boys face a different but equally real emotional landscape. Testosterone increases drive competitiveness, risk-taking, and sometimes aggression, but it also amplifies the capacity for motivation and focus when channeled correctly. The stereotype of the moody teenage boy exists for a reason, but reducing it to a mood swing overlooks what's actually happening neurologically.
Get the Full Details

Common Pitfalls Parents and Kids Should Avoid
One pattern I saw repeatedly: adults treating early physical development as a problem to solve rather than a variation to support. An eleven-year-old girl who's already developed breasts while her peers haven't often faces unwanted attention and social pressure. She might try to bind her chest or wear baggy clothes to hide. This is normal behavior in an abnormal situation, and the right response is validation, not correction. She needs to know her body is fine and the problem is other people's reactions, not hers. For boys, the opposite concern shows up. A-year-old who hasn't started puberty yet often assumes something is broken inside him. The reassurance that genetics play a huge role here is important. If his father or maternal grandfather went through a late puberty, he very likely will too. That said, I always recommend a pediatric visit to rule out underlying issues. It takes one blood test and a bone age X-ray to give an answer, and peace of mind is worth far more than the copay. Acne is another universal challenge, and the market is flooded with products that promise miracles. Most of them deliver irritation and empty promises. A simple routine of gentle cleanser, benzoyl peroxide or salicylic acid, and a non-comedogenic moisturizer works better than ninety percent of over-the-counter six-step regimens. I've watched kids spend hours each night following elaborate routines that stripped their skin barrier and made things worse. Less is more, especially when the skin is already reacting to hormonal shifts.
Practical Support Strategies That Actually Work
Communication is the foundation, but most parents don't know how to start. The best approach I've seen is casual, ongoing, and unembarrassed. Sitting the kid down for one serious talk doesn't work because by the time you're ready to have it, they've either moved on or felt pressured. Instead, treat it as a series of small conversations spread across months. Answer questions directly. Don't over-explain. If a twelve-year-old asks why he's getting pimples, say "hormones. It's normal and it gets better." That's it. No lecture needed. Nutrition and sleep matter more during puberty than at any other developmental stage outside infancy. The body is building bone density, muscle, and neural connections at a rapid pace. Sleep deprivation during this window has long-term consequences for cognition and emotional regulation that extend well past the teenage years. I've counseled teens who couldn't concentrate in school and thought they were just lazy, when they were actually sleeping five hours a night because of screens and social pressure. Eight to ten hours is the target. It's not negotiable if the kid wants to function at a reasonable level. Physical activity is another area where puberty creates unique demands. Growth plates in bones are still open, which means high-impact sports carry a slightly elevated injury risk during peak growth phases. That doesn't mean kids should avoid sports. It means coaches and parents should be aware that a sudden growth spurt can temporarily affect coordination. Kids who were graceful at twelve might feel clumsy at thirteen. It passes. The body is adapting to new limb lengths and center of gravity.
When to Actually Worry
Most changes fall within a broad normal range, but there are red flags worth paying attention to. For girls, starting puberty before eight or not starting by thirteen warrants a pediatric evaluation. Boys showing signs before nine or none by fourteen should also be checked. Other concerns include severe emotional distress that interferes with daily life, rapid weight changes without explanation, or signs of depression lasting more than two weeks. Puberty is hard, but persistent inability to function isn't a rite of passage. It's a signal that professional support might help. I worked with a boy who developed severe anxiety about his body during puberty and became withdrawn to the point where he stopped attending school. The root cause wasn't puberty itself. It was untreated ADHD that became more apparent when the academic and social demands of middle school increased alongside hormonal changes. The two issues compounded each other. Treating only the anxiety wouldn't have helped. Addressing both did. This is why comprehensive evaluation matters when things seem off, even if the surface problem appears to be purely physical or emotional. Puberty is a biological event, but it plays out in a social world that doesn't always accommodate it kindly. The kids who navigate it best aren't the ones with perfect bodies or zero emotions. They're the ones who have people around them who understand what's happening, don't panic, and offer steady support without making it a big deal. That's the real takeaway, and it's something worth carrying forward regardless of timing.