What You Actually See on a CXR When Suspecting PE
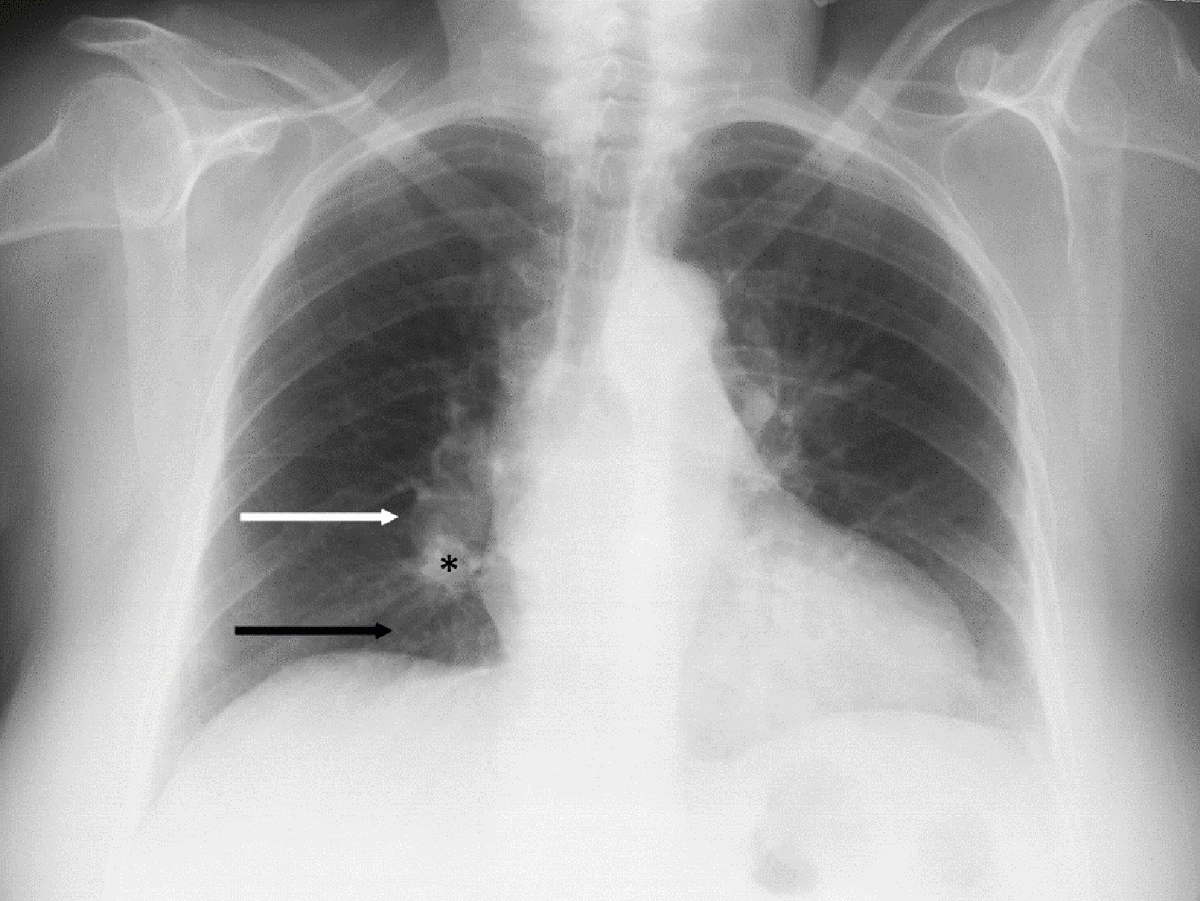
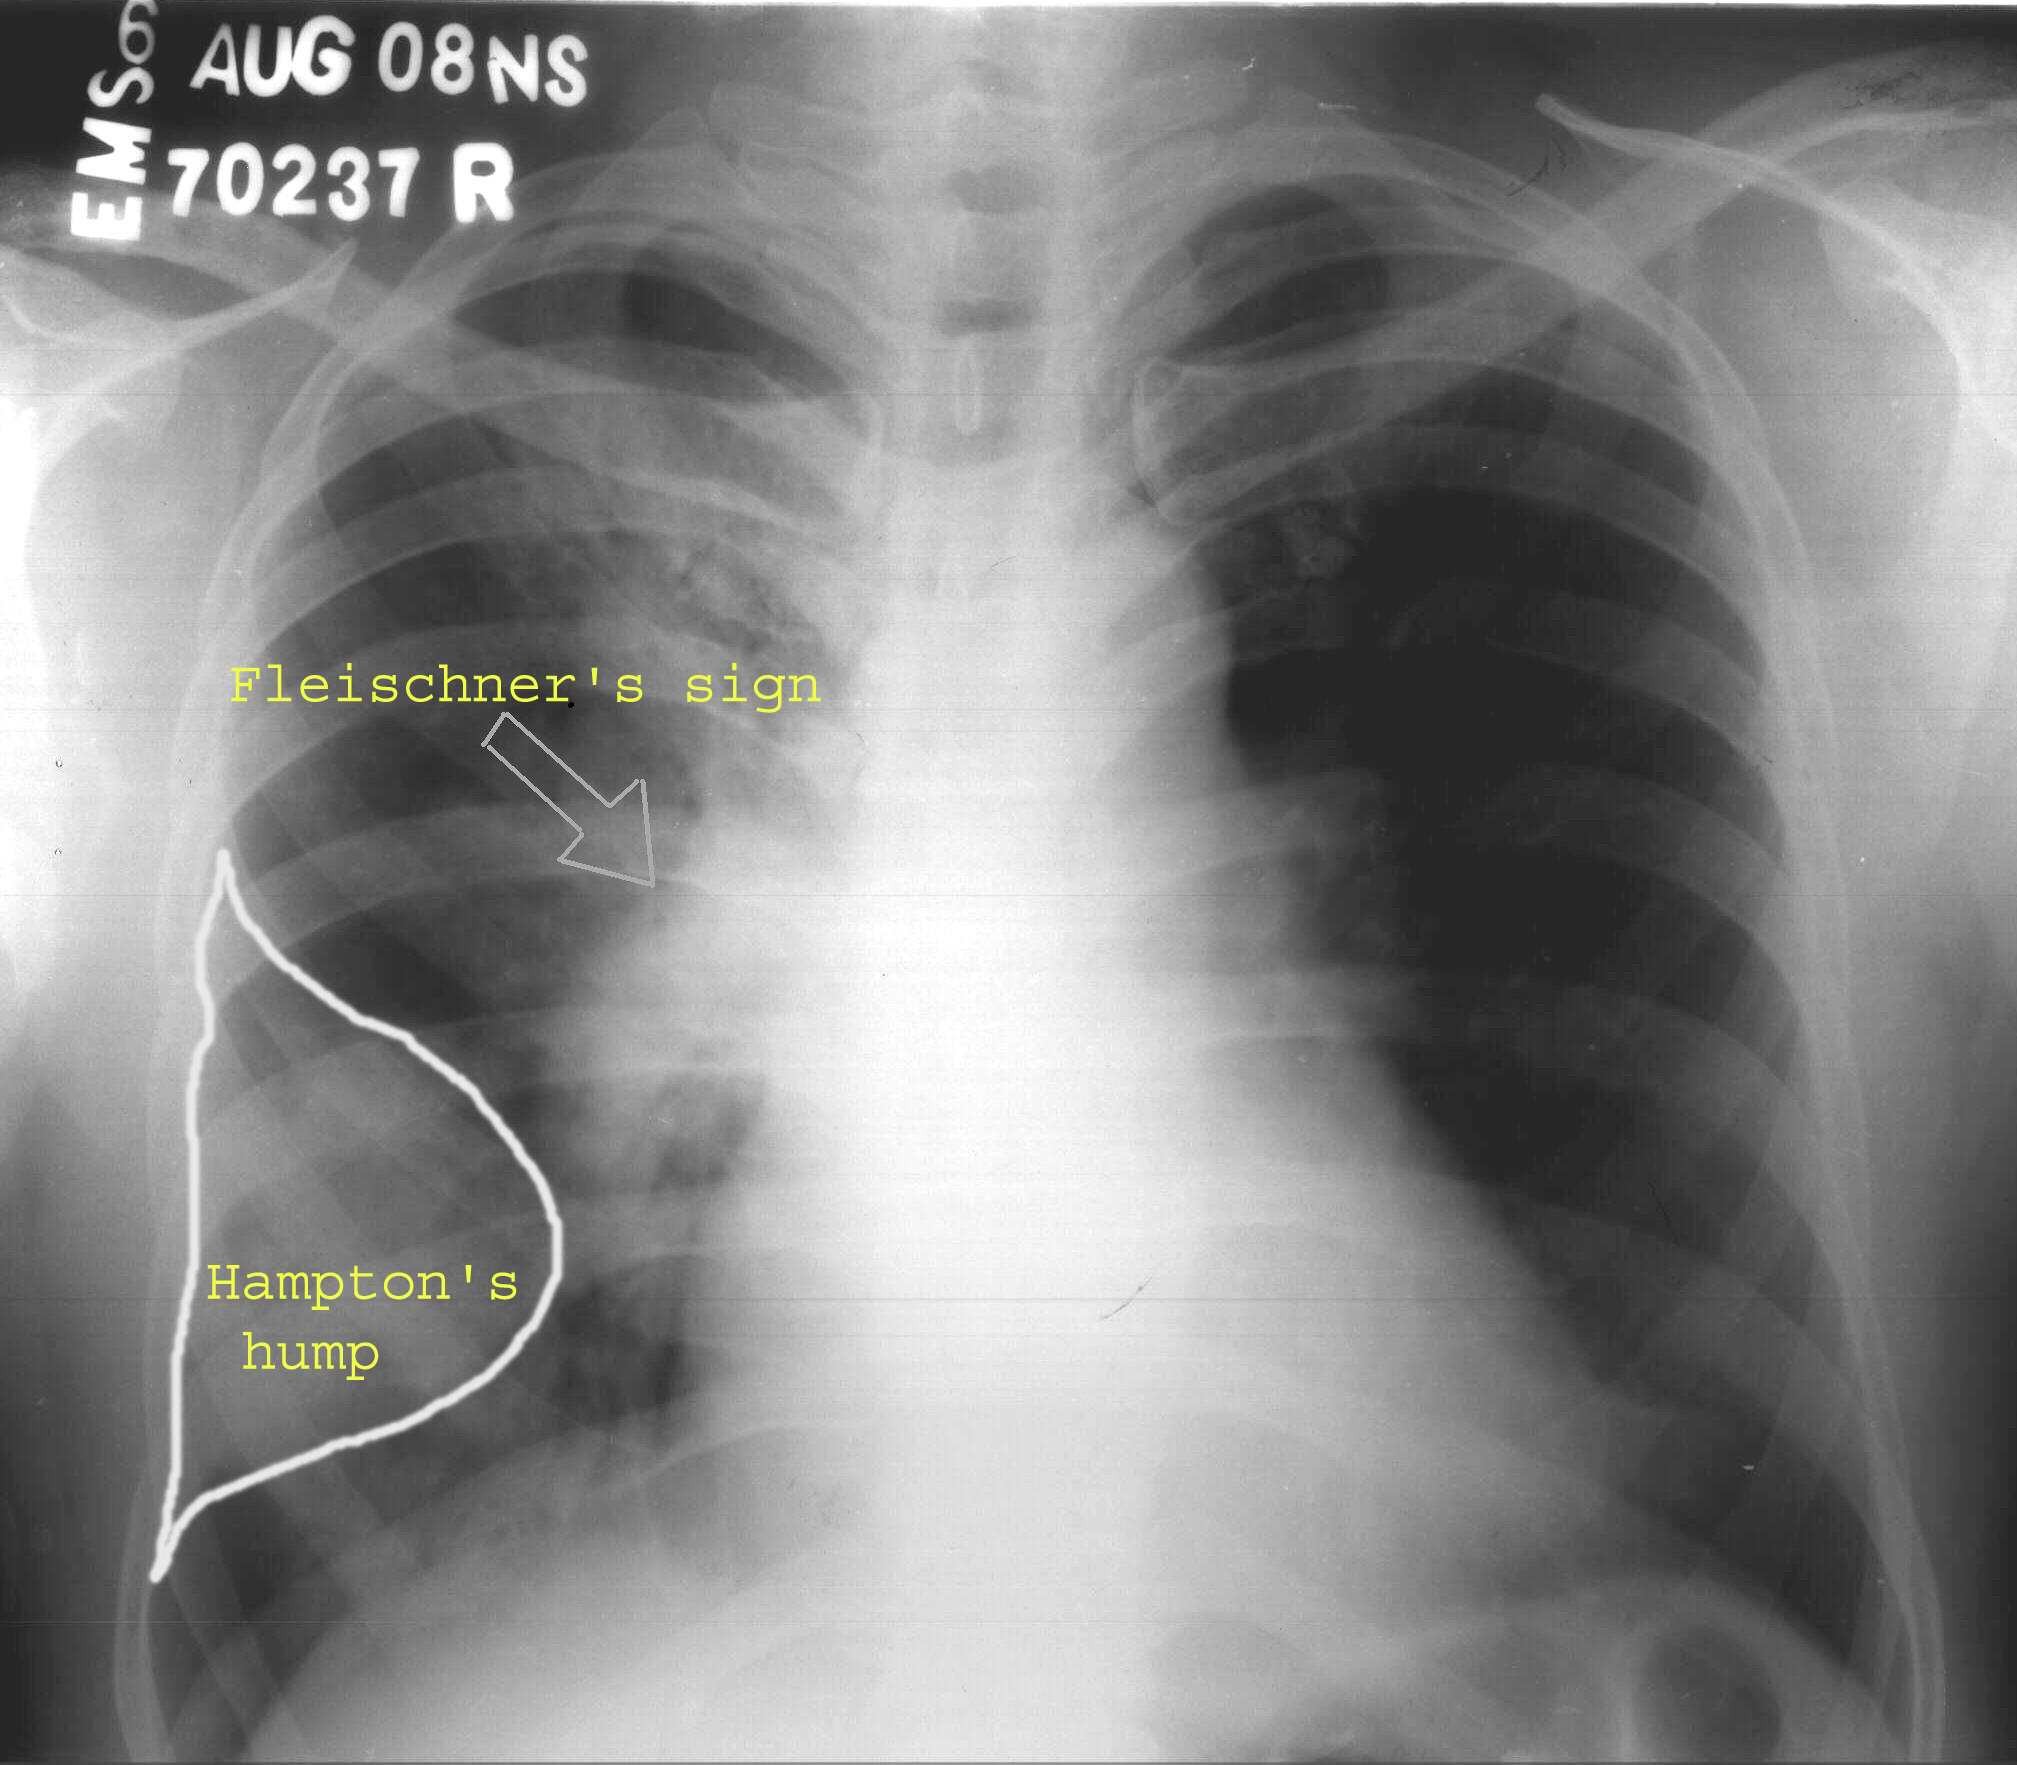
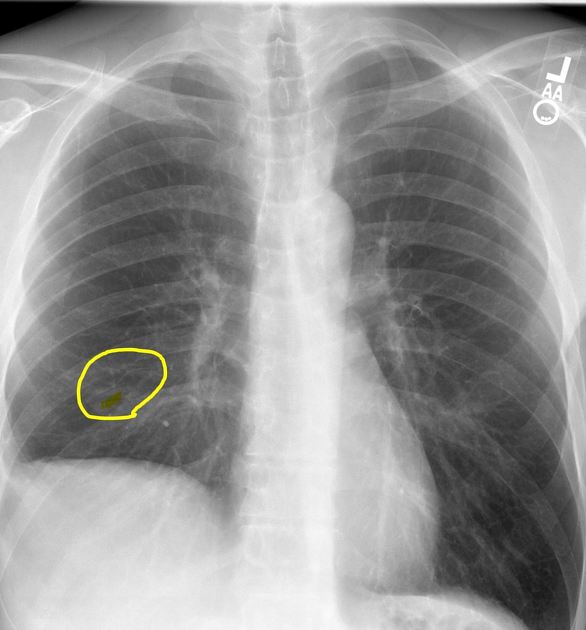
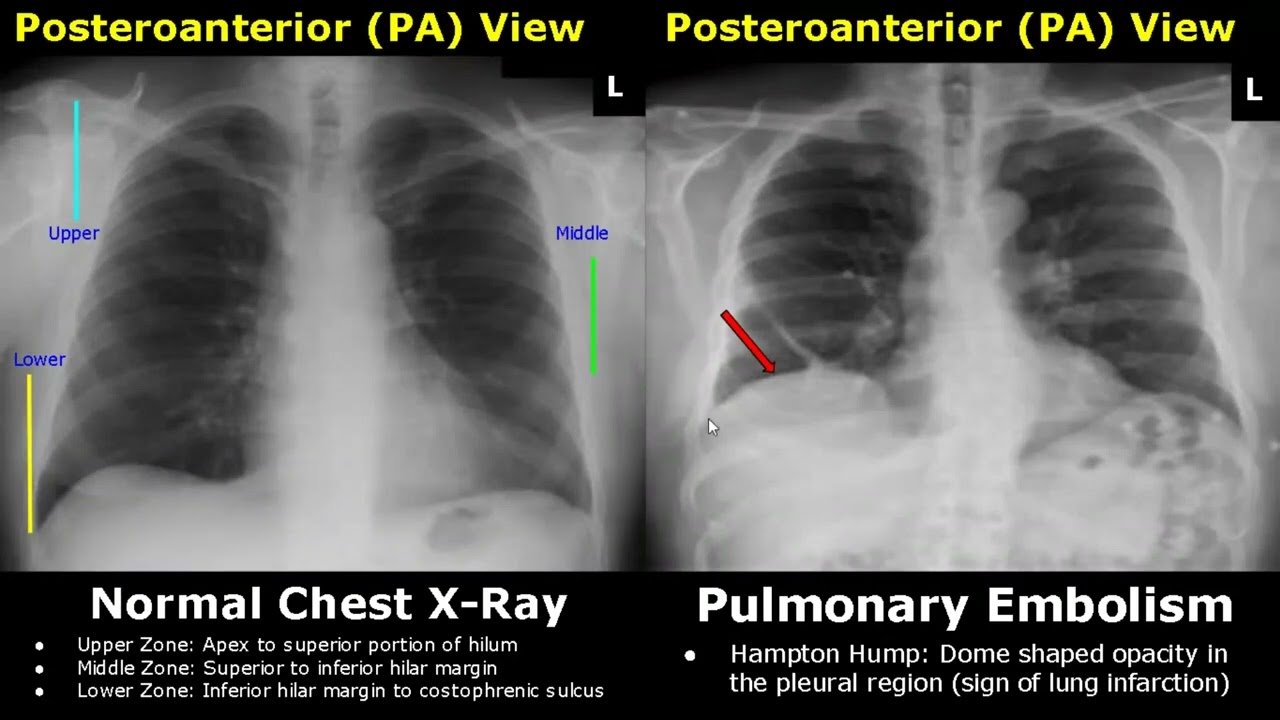
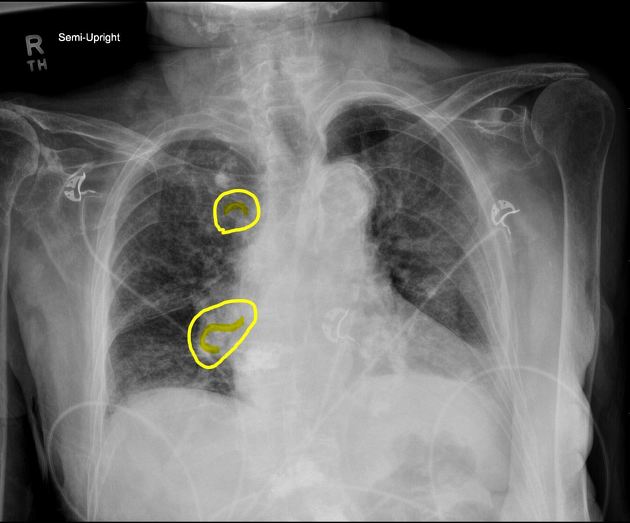
A pulmonary embolism X Ray is almost never diagnostic on its own. That is the first thing you need to accept before you send any chest radiographs for review. The standard PA and lateral chest film will frequently look entirely normal in confirmed PE cases. I have seen this repeatedly in the ED reading room, where a perfectly clear CXR sat next to a positive CTPA report. Do not let a normal chest x-ray give you false reassurance, and do not let an abnormal one confirm PE either. The utility of a plain film in this context is exclusionary, not confirmatory. You order it to rule out alternative diagnoses: pneumothorax, large consolidation, pleural effusion, pulmonary edema, or a mass that might explain the patient's symptoms. If the film shows extensive bilateral infiltrates and pleural effusions, you are likely looking at heart failure rather than an embolic event. If you see a visible pleural line with absent lung markings peripherally, that is your pneumothorax and the PE workup goes down a different track. The classic textbook signs of PE on x-ray are Westermark sign, which is focal oligemia or pruning of the pulmonary vasculature distal to an occluded artery, and Hampton hump, which is a peripheral wedge-shaped opacity representing pulmonary infarction. Neither appears often. Westermark sign shows up in roughly 2 percent of confirmed cases. Hampton hump appears in somewhere between 5 and 16 percent, and only when infarction has actually occurred, which means the embolus is large enough to cause tissue death and the patient has had time for that process to develop. Most PEs do not infarct. Most chest x-rays in PE patients are unremarkable.
I also routinely see atelectasis, small effusions, and nonspecific interstitial markings in these films. These are reactive changes from shallow breathing, immobility, or underlying lung disease. They are not diagnostic of PE. A junior resident once flagged a patchy right lower lobe opacity as suspicious for infarction. It was aspiration pneumonia from a seizure. The CT angiogram showed no embolus. The x-ray finding was real but misattributed.
Reading the Film Systematically
Start with technical quality. Rotation, inspiration, penetration. A rotated film makes the mediastinum look wider than it is. Poor inspiration masks basilar atelectasis and makes heart size difficult to judge. I usually reject films that do not show at least nine posterior ribs before I commit to a diagnostic read. Then move through the lungs. Check each zone systematically. Look for areas of decreased vascular markings that might suggest oligemia. Look for peripheral opacities that could represent infarction. Look for effusions, especially small ones that layer posteriorly on the lateral view. The lateral film is essential here. Small pleural effusions are easy to miss on PA alone. Check the heart size and contour. Cardiomegaly points away from PE as the primary diagnosis. Check the mediastinum. Widening might indicate aortic pathology or lymphadenopathy. Check the hila. Enlargement could suggest malignancy or chronic thromboembolic disease. The right descending pulmonary artery should measure less than 16 millimeters on the PA view. Enlargement here is a soft sign of pulmonary hypertension, which can be a sequela of chronic thromboembolic disease.
Get the Full Details
Look at the diaphragm and costophrenic angles. Elevation might suggest subpulmonic effusion or eventration. Blunting suggests fluid. Check the bones and soft tissues for incidental findings.
When the X-Ray Actually Helps
The one scenario where a chest x-ray meaningfully changes management in suspected PE is when it reveals a contraindication to CT contrast. Severe renal impairment, active contrast allergy, or pregnancy might prompt you toward a V/Q scan instead. The x-ray is the first step in that algorithm because a normal chest film makes a V/Q scan interpretable, while an abnormal film often renders it indeterminate. I had a case last year where the CXR showed diffuse bilateral nodular opacities. The V/Q scan that followed was non-diagnostic because of the underlying parenchymal disease. We went straight to CTPA instead. The x-ray saved us from ordering a test we knew would not give a clear answer. Chronic thromboembolic pulmonary hypertension is another scenario where the plain film carries more weight. Enlarged central pulmonary arteries, pruning of peripheral vessels, and right heart enlargement on serial films can build a compelling picture over time. This is where the x-ray earns its keep.
Pitfalls and Limitations
The biggest pitfall is overinterpreting normal variants. A prominent hilar shadow is not necessarily enlarged. A slightly widened mediastinum on an AP portable film is often just patient positioning and low inspiration. I have caught myself second-guessing normal anatomy multiple times because I was looking too hard for PE signs that were not there. Another pitfall is undercalling subtle signs. In one case, a faint linear opacity along the right heart border turned out to be a pleural tag from a small organized effusion. The attending radiologist caught it. I missed it initially because my attention was fixed on the lung fields looking for infarction. The real pathology was on the pleural surface and it was small. Chest x-ray has near-zero sensitivity and specificity for acute PE. Sensitivity ranges from about 10 to 40 percent depending on the study. Specificity is similarly unreliable. No radiologist should feel confident ruling in or ruling out PE based on a plain film alone. If clinical probability is moderate to high, you proceed to CT angiography regardless of what the x-ray shows.
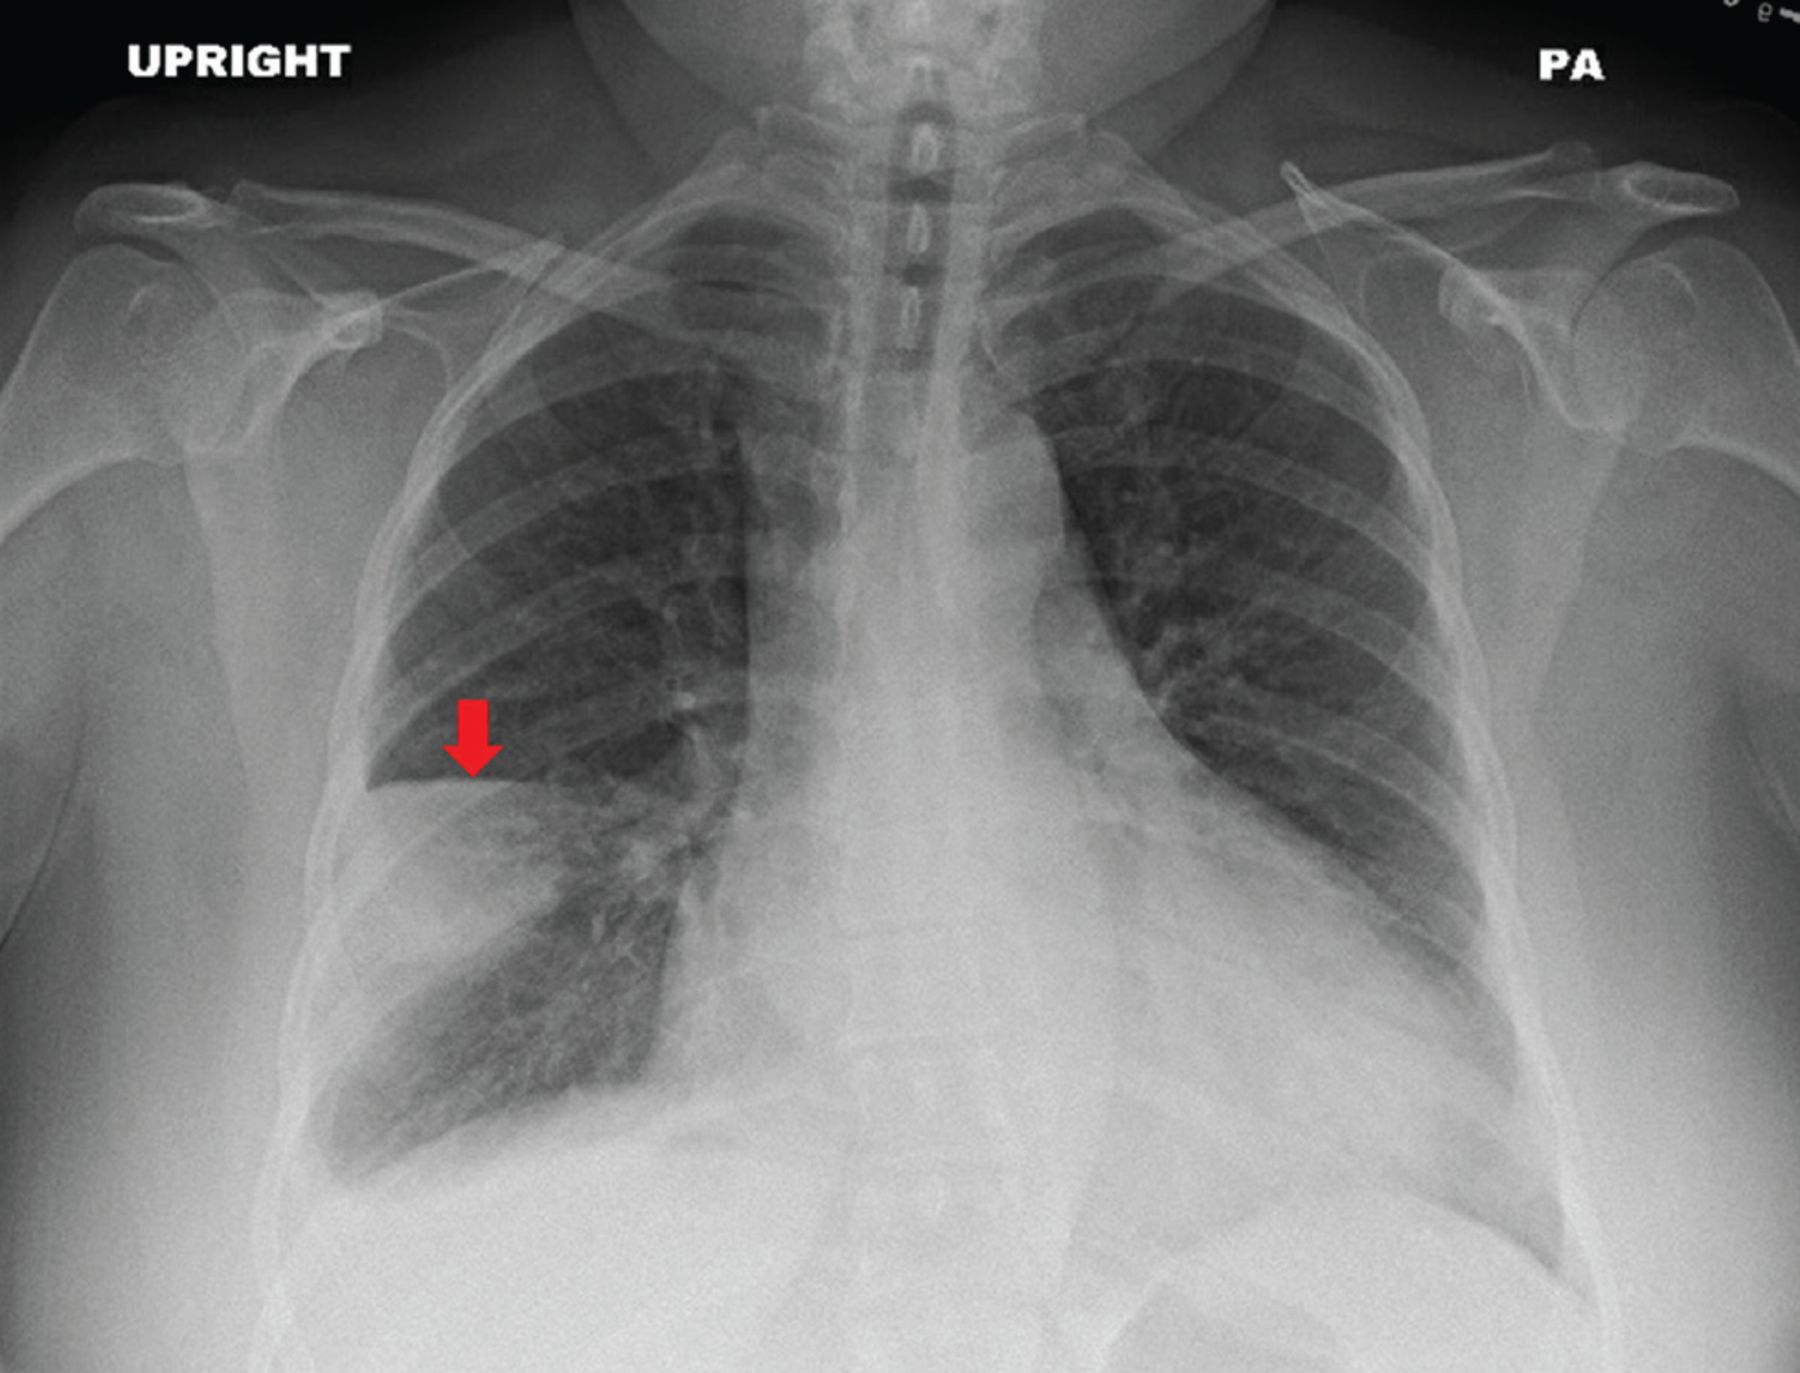
The workaround I use when I suspect PE but the x-ray is completely normal is to document the normalcy clearly and move on. Do not pad the report with speculative language like "no radiographic evidence of PE." Say "no acute cardiopulmonary abnormality identified." That is accurate and it stops someone from misreading your caution as concern.
Practical Workflow
Order the PA and lateral chest x-ray first in any patient with suspected PE. Review it before sending for CT. Document the findings objectively. Use the results to guide downstream testing decisions rather than as a diagnostic endpoint. If the film is abnormal in a way that explains the symptoms, reconsider the PE workup. If it is normal or shows only nonspecific changes, proceed to CTPA as indicated by the Wells score or PERC rule. This approach typically takes about three minutes for an experienced reader and another five to ten minutes dictating a brief report. It is fast because you are not searching for a diagnosis the test cannot provide. You are ruling out alternatives and documenting baseline findings. That is its actual job.