Understanding Dual Pump Mechanics in Human Physiology
Most textbooks teach pulmonary and systemic circulation as two separate loops, but that framing obscures more than it reveals. They are a single circuit split into two pressure domains by the right and left ventricles sitting side by side. The septum between them is the only real boundary. I spent years working with neonatal ICU patients, and the moment you actually deal with fetal circulation transitioning to adult circulation, you realize how brutally unforgiving the system is when either side stumbles. Pulmonary vascular resistance has to drop and systemic vascular resistance has to rise at roughly the same time in a newborn. When that doesn't happen smoothly, you get persistent pulmonary hypertension of the newborn or ductal-dependent lesions where one circuit is silently failing because the other is compensating in a way that masks the problem until it's critical.
Key Differences in Pulmonary Vs Systemic Circulation
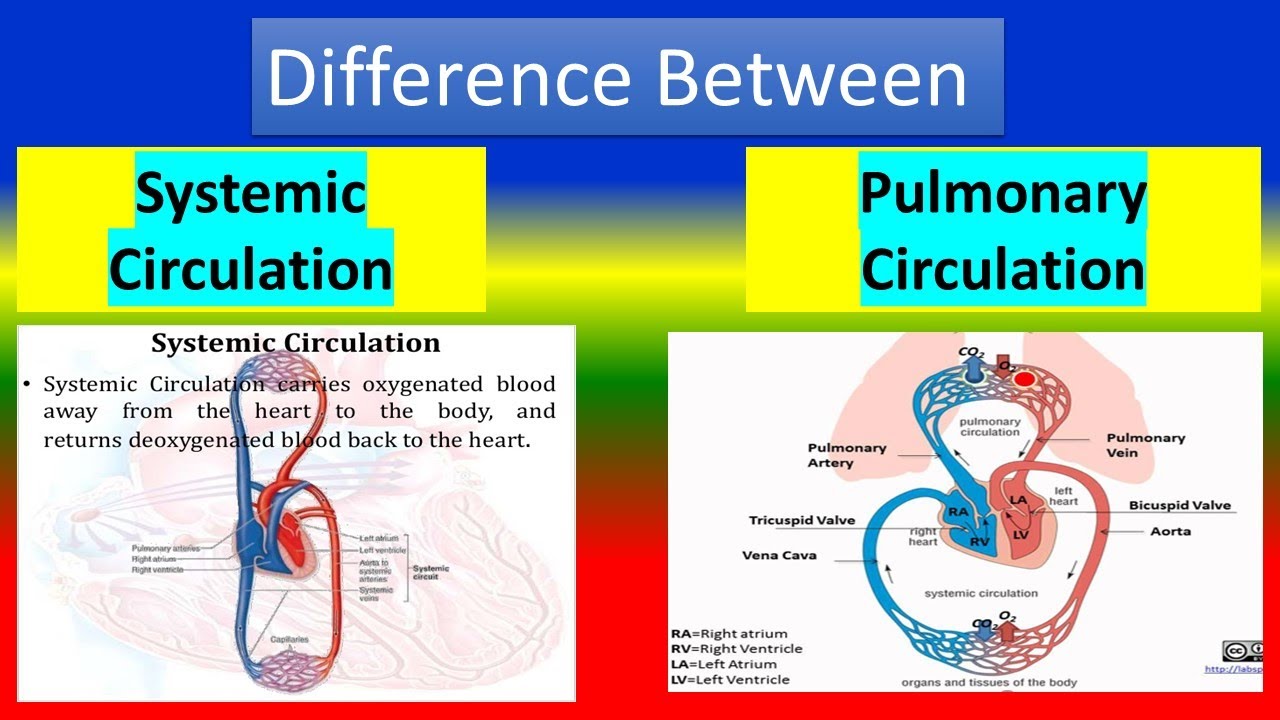
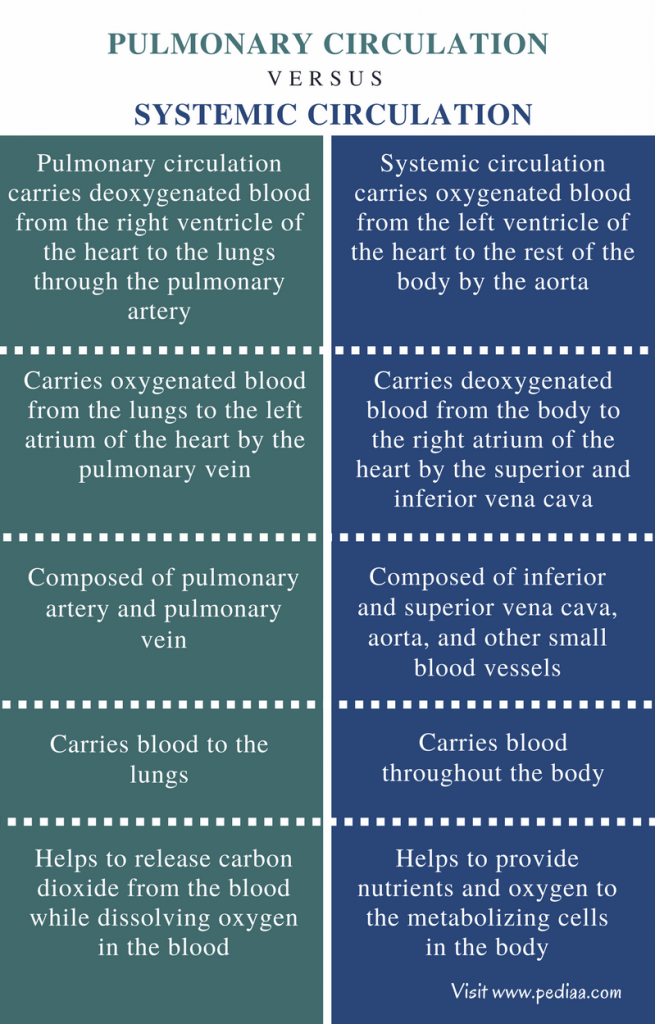
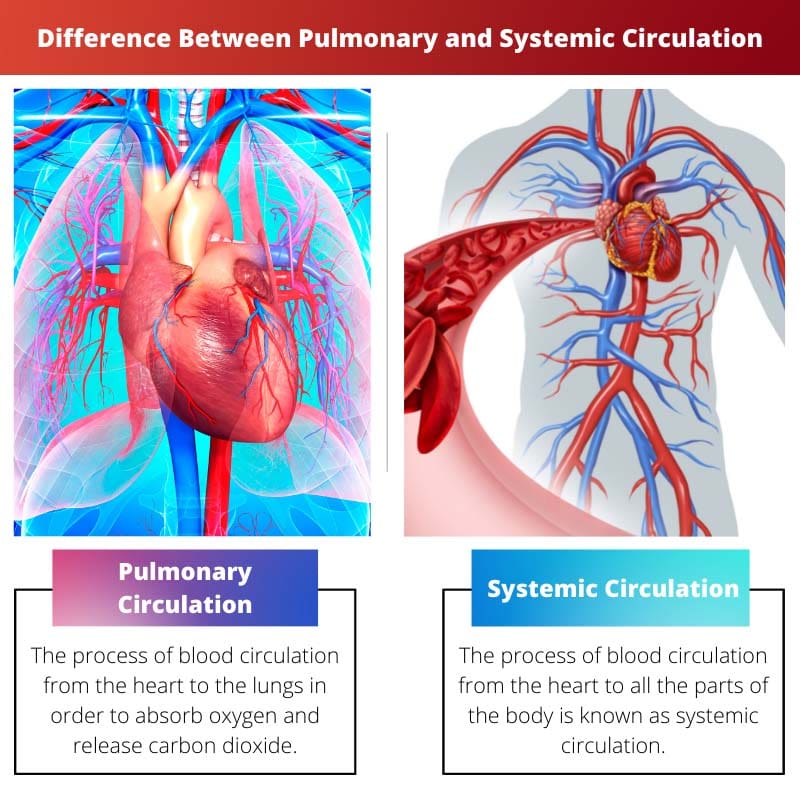
Let me break down the actual hemodynamic numbers instead of relying on rote memorization. The systemic circuit operates at approximately 120 over 80 millimeters of mercury. Mean arterial pressure sits around 93 mmHg. The pulmonary circuit runs at roughly 25 over 8 mmHg with a mean pressure of about 15 mmHg. That is not a rounding error. The pulmonary vasculature runs at one-seventh the pressure of the systemic vasculature and that difference is maintained by structural and functional adaptations in the vessel walls. Systemic arteries have thick muscular walls with significant smooth muscle content to handle high pressure and actively regulate flow through vasoconstriction and vasodilation. Pulmonary arteries are far more distensible with thinner walls and less smooth muscle. This isn't arbitrary design. It's the difference between a high-pressure delivery network and a low-pressure gas exchange network. The oxygenation state is also reversed between the two circuits. Deoxygenated blood from the superior and inferior vena cava enters the right atrium, passes through the tricuspid valve into the right ventricle, and gets pumped through the pulmonary artery to the lungs. Oxygenated blood returns via the four pulmonary veins to the left atrium, moves through the mitral valve into the left ventricle, and is ejected through the aortic valve into the aorta for distribution to every organ in the body. The direction of oxygenation shift matters when you're reading an echocardiogram or interpreting an arterial blood gas.
What Beginners Miss About This System
Here is the part nobody emphasizes enough: the pulmonary and systemic circulations are perfectly serial. Whatever the right ventricle pumps must be returned and pumped by the left ventricle. Over minutes to hours, stroke volumes equalize. If they don't, you have a shunt or an obstruction. I've seen residents miss this because they treat each circuit independently on paper but then panic when clinical data doesn't fit the simplified model. Another counter-intuitive point: the pulmonary circulation is a capillary-rich bed with enormous reserve capacity. At rest, only about half the pulmonary capillaries are perfused. During exercise, recruitment of the remaining half can reduce pulmonary vascular resistance by nearly 50 percent. The systemic circulation doesn't do that. Its vascular beds are already more fully recruited at baseline. When I was reviewing cases of unexplained dyspnea in otherwise healthy adults, I encountered a patient whose resting pulmonary pressures looked normal but whose pulmonary vascular resistance spiked abnormally with minimal exertion. Standard echo missed it because resting measurements fell within reference ranges. The workaround was a cardiopulmonary exercise test with right heart catheterization during peak exertion. Resting numbers were normal. Exercise revealed a pulmonary vascular resistance of 5.2 Wood units, which is diagnostic of exercise-induced pulmonary hypertension. The patient was eventually found to have a small congenital left-to-right shunt that only became hemodynamically significant under stress. This is the kind of edge case that shows up repeatedly when you stop treating pulmonary and systemic circulation as static concepts.
Get the Full Details
Pitfalls and Where the Model Breaks Down
The two-circuit model assumes healthy lungs, an intact septum, and normal valvular function. It breaks down in several common clinical scenarios. With left heart failure, pulmonary venous pressure backs up into the capillaries, causing pulmonary edema while the systemic circuit may present with low output symptoms. The relationship flips: systemic disease causes pulmonary congestion. The primary pathology is in the left ventricle but the first observable signs are often in the lung fields on imaging. In chronic obstructive pulmonary disease, the story reverses again. Chronic hypoxic vasoconstriction in the lungs raises pulmonary vascular resistance, which strains the right ventricle into cor pulmonale. The systemic circulation eventually suffers from reduced preload because the right heart can't push blood through the lungs efficiently. This is why pulmonary hypertension in COPD patients is treated with supplemental oxygen first, not vasodilators. Systemic vasodilators would worsen ventilation-perfusion matching and potentially cause life-threatening hypotension. The model also fails to account for anatomical shunts. Patent foramen ovale, atrial septal defects, and ventricular septal defects create direct communication between the two circuits. In most cases, the higher pressure of the systemic side drives a left-to-right shunt that increases pulmonary blood flow over time, leading to pulmonary vascular remodeling. If untreated, that remodeling can eventually reverse the shunt direction entirely, producing Eisenmenger syndrome. This is not theoretical. It develops over years and is irreversible once established.
There is no single measurement that captures the dynamic interplay between these circuits. Echocardiography gives you structural and velocity data. Right heart catheterization gives you pressure measurements but is invasive. Cardiac MRI provides volumetric accuracy but isn't widely available and takes significant time. A combination approach, starting with clinical assessment and echocardiography and reserving catheterization for ambiguous or complex cases, is the standard pathway. It usually takes 45 to 90 minutes for a complete non-invasive workup and can identify the vast majority of clinically significant defects. Invasive procedures are reserved for when the non-invasive data is inconclusive or when intervention planning requires precise hemodynamic numbers.