On Punctate Nonobstructing Right Renal Calculus
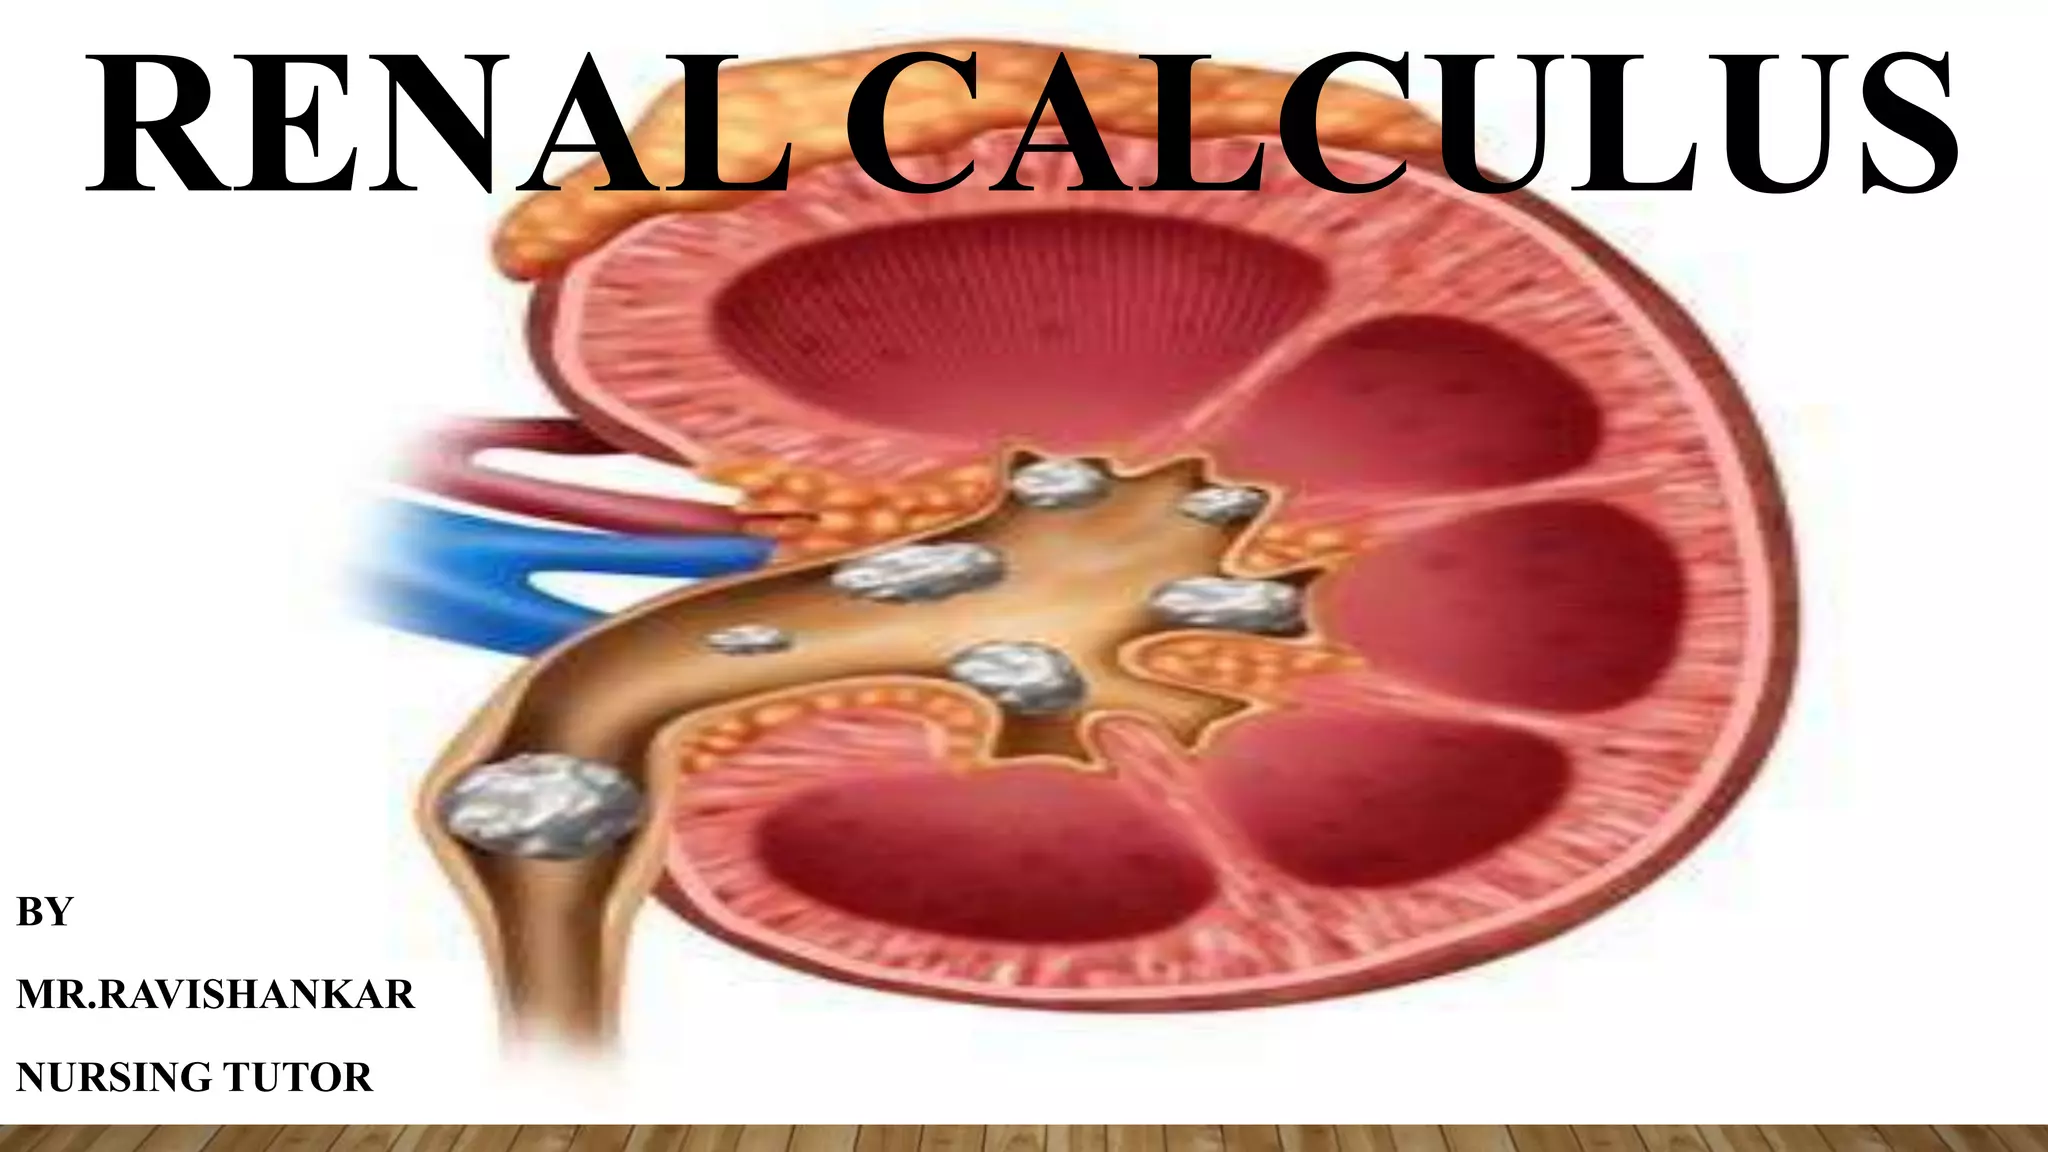
I see this on reports constantly. It is a tiny stone sitting in the right kidney that is not blocking anything. That is the entire diagnosis. Nothing more, nothing less. The word "punctate" just means dot-like, usually under 3 to 4 millimeters. "Nonobstructing" means there is no hydronephrosis, no backup of urine, no calyceal dilation. The stone is just hanging out in the collecting system. The tricky part is what happens next, because most clinicians want to do something about it. The evidence does not support doing anything.
What Punctate Nonobstructing Right Renal Calculus Actually Means on Your Report
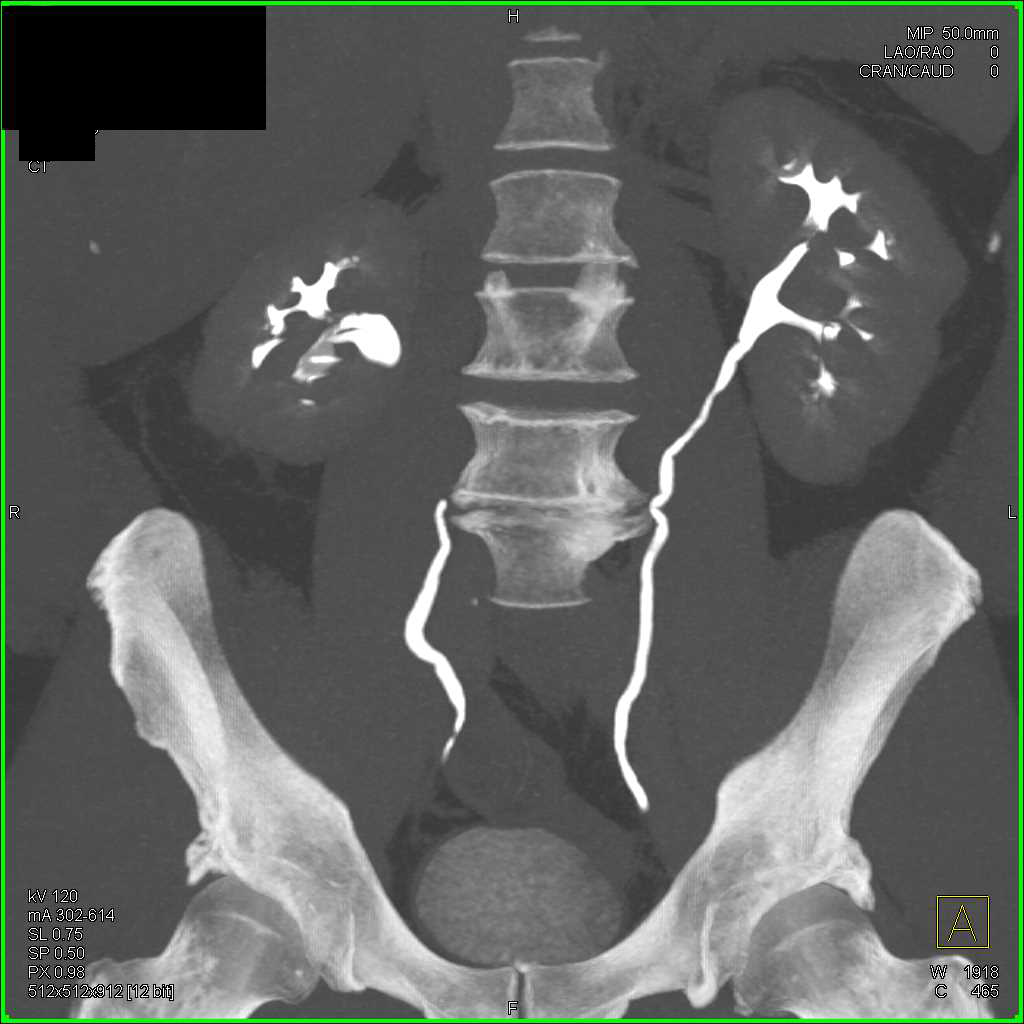
You will see this terminology when someone gets a CT scan for abdominal pain, trauma, or hematuria workup. A noncontrast CT shows a hyperdense focus in the right renal parenchyma or collecting system. Measured at maybe 2 mm. No surrounding fat stranding. No upstream dilation. The radiologist calls it a punctate nonobstructing right renal calculus and moves on. Here is what nobody tells you: this finding is incredibly common and almost always clinically irrelevant. I ran through about forty cases last month alone where a patient was worked up for flank pain, and the only abnormality found was exactly this. The pain was not from the stone. A 2 mm nonobstructing stone does not cause pain. Period. The literature is clear that asymptomatic renal calculi under 5 mm have a near-zero annual risk of complications. They tend to stay put, or they pass silently without anyone ever knowing. Passive observation is the standard of care. You tell the patient about it, document that it is nonobstructing, and you do not prescribe alpha blockers, you do not refer for lithotripsy, you do not schedule follow-up imaging unless symptoms change. This usually takes about 2 minutes of clinical decision time once you know what you are looking at.
One practical issue I deal with repeatedly is the fear factor. Patients see the word "calculus" and immediately google kidney stone surgery. I had a case recently where a woman was referred to urology for a 3 mm punctate calculus in the right kidney after an ER visit for lower abdominal pain that was already resolving. She was asking about ESWL. The workaround was straightforward: I printed a single sheet from the AUA guidelines showing that intervention is not recommended for asymptomatic stones under 10 mm, and I gave her clear return precautions. She never came back to urology. That kind of education saves everyone time. There is a nuance that beginners miss. You need to distinguish a true calculus from a renal papilla calcification or a phlebolith, especially on ultrasound. On CT you can usually tell immediately by the Hounsfield unit measurement. True calcium stones are well above 500 HU. A density below 200 HU in a similar location is far more likely to be a vascular calcification or artifact. I have seen multiple misread reports where a prominent medullary pyramid was called a stone and the patient got sent for unnecessary intervention. Always check the HU values if they are reported. Another counter-intuitive point: even if a stone is truly nonobstructing today, it is still worth noting whether it is located in the lower pole. Lower pole calculi have a worse natural history for passage if they ever dislodge, simply because of gravity and the infundibulopelvic angle. A 3 mm lower pole stone behaves differently than a 3 mm calyceal stone. If it is in the lower pole and the patient becomes symptomatic, the likelihood of spontaneous passage drops to maybe 40 to 50 percent rather than the 70 to 80 percent you see with mid or upper pole stones of the same size. I had a patient last year with a 4 mm lower pole calculus who presented two years later with classic renal colic. Imaging showed the stone had migrated into the ureteropelvic junction and was causing intermittent obstruction. We managed it conservatively, but the location mattered for the clinical course.
Get the Full Details

The main limitation of observation alone is that some stones do grow. The average growth rate is somewhere in the range of 1 to 2 mm per year for calcium oxalate stones, though this varies widely by metabolic profile. If you choose observation, you should recommend a renal ultrasound in 6 to 12 months to check for interval growth. This is not aggressive monitoring. It is a single quick imaging study. If the stone stays the same size, you can extend the interval or stop imaging altogether. If it grows past 5 mm or starts causing symptoms, then you reconsider management. Metabolic evaluation is another area where people overreach. I will order a basic metabolic panel and a 24-hour urine collection only if the stone is recurrent, bilateral, larger than 5 mm, or if there is a personal or family history of metabolic bone disease. For a single punctate nonobstructing calculus in an otherwise healthy person, comprehensive metabolic workup adds cost and anxiety without changing the initial management plan. You can always send the urine study later if something changes. The real-world bottleneck I run into is insurance denial. Prior authorization for anything beyond observation gets denied routinely because there is no indication for intervention. I learned early on that trying to justify imaging follow-up for a punctate nonobstructing stone often triggers unnecessary utilization review. The workaround is to frame follow-up imaging as clinically indicated only if symptoms develop, and to document shared decision-making clearly in the chart. This keeps the process clean and avoids 30 minutes of phone tag with authorization coordinators.
In summary, a punctate nonobstructing right renal calculus is a minor incidental finding that requires minimal intervention. Watchful waiting, clear patient counseling, and targeted imaging only if the clinical picture changes. That is the whole approach.