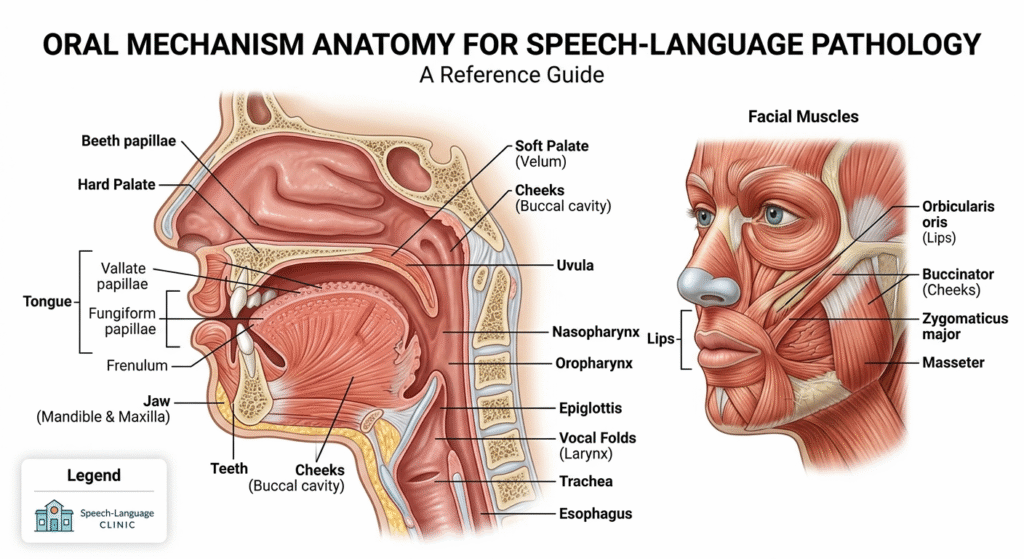
What the exam actually looks like when you're sitting across from a patient
The oral mechanism exam is a structured clinical assessment of the anatomical structures and neuromuscular control involved in speech, swallowing, and respiration. It is not a diagnostic test for a specific disease. It is a mapping tool. You are evaluating range of motion, strength, speed, coordination, and accuracy of the lips, tongue, jaw, velum, and larynx. The results inform whether a client has a structural limitation, a motor control deficit, or a sensory processing issue that could be contributing to their communication or feeding concerns. I have been doing these for over a decade, mostly in pediatric and neurogenic populations. The most useful thing I do is skip the rote checklist and focus on function. A tongue that can touch every point on a diagram is not necessarily functionally adequate for clear speech or safe swallowing. I learned that early when a kid passed every oral reflex screen with flying colors but couldn't form a single consonant cluster without severe articulation distortion. The exam found nothing because it was looking at isolated movements, not coordinated sequences. That shifted how I approach it entirely.
Purpose Of Oral Mechanism Exam
The core purpose is to establish a baseline of orofacial motor capacity and identify deficits that may underlie speech sound disorders, dysarthria, apraxia, or swallowing dysfunction. It tells you what the hardware can do before you troubleshoot the software. Without it, you are guessing. You might prescribe articulation therapy when the real issue is velopharyngeal insufficiency, or you might pursue language intervention when the bottleneck is oral sensory processing. The exam prevents that kind of misdirected effort. I start with observation. Posture, oral rest posture, breathing pattern, drooling, lip seal at rest. These baseline behaviors are easy to miss if you jump straight into the movement tasks. Then I move to structure inspection: dentition, palate shape, frenulum length, tongue tie. A high arched palate or ankyloglossia is not automatically a problem, but it changes the movement landscape and you need to know it. After structure comes function, broken into speed, strength, range, and accuracy. Range is the easiest to assess. I use a ruler for jaw opening, then check lateral excursions and protrusion of the tongue. I note asymmetry. Strength involves resistance tasks: pushing against a tongue depressor from multiple directions, lip pressure against a spatula. Speed is where most exams get rushed. I have clients do rapid alternating movements: lip retraction to rounding, tongue click to tip tap, repeated syllables like pa-ta-ka. The syllable rate per second is the metric that matters. Accuracy is the final layer. I assess gustatory, tactile, and thermal sensory response, then look at coordinated sequencing like the oral kinesthetic component of speech production.
Counter-intuitive things nobody tells you in grad school
First, a normal reflex does not rule out a disorder. The gag reflex, palatal reflex, and suck reflex are brainstem-level responses. They tell you the pathway exists, not that it is functioning well for intentional motor control. I once cleared a child for oral motor readiness because every reflex was present and symmetrical, only to find severe dyspraxia on speech sampling. The reflexes are irrelevant to cortical motor planning. Do not let them distract you from actual speech and swallow tasks. Second, tongue tie is vastly overdiagnosed. I have seen practitioners refer out for frenuloplasty based entirely on a visual estimation of lingual frenulum length without assessing functional range. A short-looking frenulum can still allow full elevation and lateralization if the surrounding tissue compensates. Conversely, a seemingly normal frenulum can restrict function if there is significant myofascial tension. The workaround I use is simple: measure functional range, not anatomical appearance. If the tongue cannot clear the upper molars, cannot elevate to the alveolar ridge for /t/ and /d/, or cannot laterally elevate for lingual closure, then the frenulum is functionally limiting regardless of how it looks. I track this with a tongue depression blade and a mirror, timing each movement for 10 seconds and comparing left to right.
Get the Full Details

Common pitfalls
The biggest one is confusing cooperation with capability. Children, especially those with autism or intellectual disability, will often comply with every instruction without genuinely having the motor capacity. They will attempt the movement and fail quietly. The solution is to give one instruction at a time, model once, and watch the actual output rather than accepting the attempt. I also avoid using standardized scoring sheets that assign point values to each movement. The literature on oral mechanism exam reliability is thin at best. Kappa statistics for inter-rater reliability hover around 0.4 to 0.6 for most components, which means two clinicians will often disagree on whether a finding is normal or abnormal. Use the exam as a clinical guide, not a measurement tool with psychometric validity. Another pitfall is ignoring the temporal dimension. Dysarthria and apraxia are fundamentally temporal disorders. Speed and rhythm matter more than raw range. I always record a 30-second sample of rapid alternating movements and calculate syllables per second. A rate below 4 syllables per second on diadochokinetic tasks is a red flag that warrants further motor speech assessment, regardless of how strong or symmetric the movements appear under resistance.
When it fails you
The oral mechanism exam is essentially useless for diagnosing receptive or expressive language disorders, phonological processing deficits, or stuttering. It will also not detect subtle velopharyngeal closure issues in clients with mild hypernasality unless you include nasometry or videoendoscopy. In these cases, the exam gives a false sense of completeness. I pair it with speech sample analysis and, when swallowing is in question, a FEES or MBS examination. The oral mechanism exam is one data point among many, not a standalone assessment. The main materials needed are a tongue depressor, a ruler, a timer, a mirror, and optionally a suction catheter for saliva management. No proprietary kits, no expensive devices. I carry these in a small pouch and set up in roughly 90 seconds. The entire exam, if done thoroughly, takes about 12 to 18 minutes depending on client cooperation and age. Rushing it to under 5 minutes renders most of the data unreliable. I used to administer this exam with a clipboard and a printed scoring sheet. Switching to a voice memo app where I narrate findings in real time cut my documentation time from 25 minutes per session down to about 6 minutes while actually improving the specificity of my notes. I just play back the memo and transcribe the key metrics. It is far more efficient than trying to fill in a rigid form while the client is sitting in front of you.



