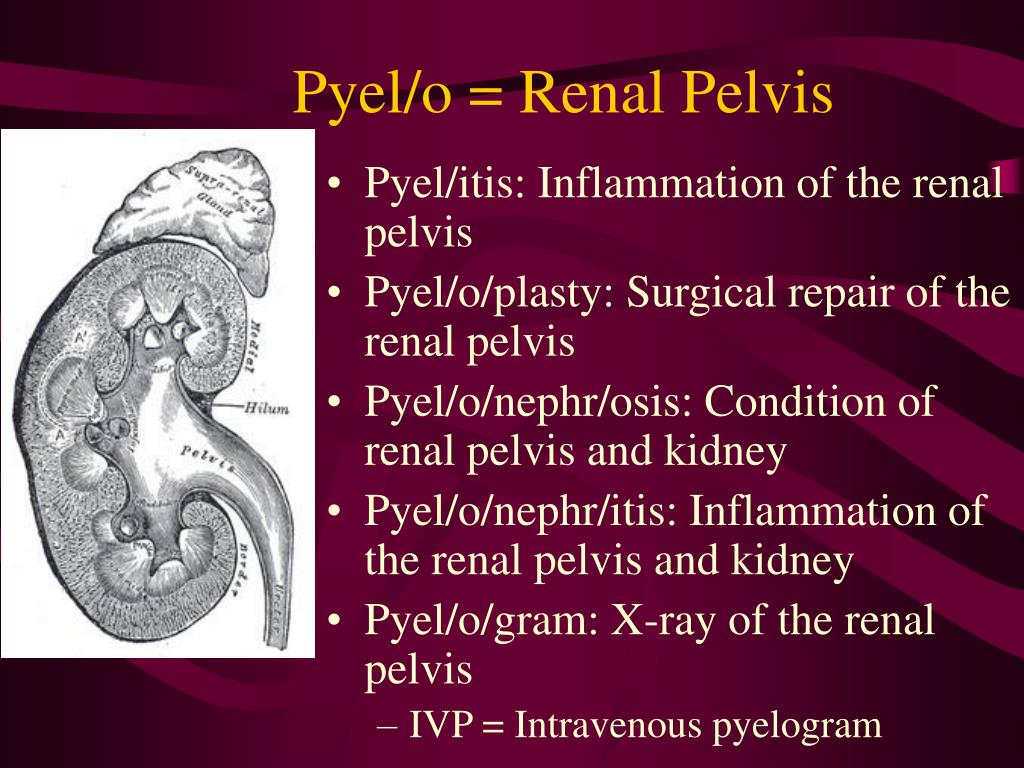
So you're looking into Pyel O and trying to figure out what it actually means.
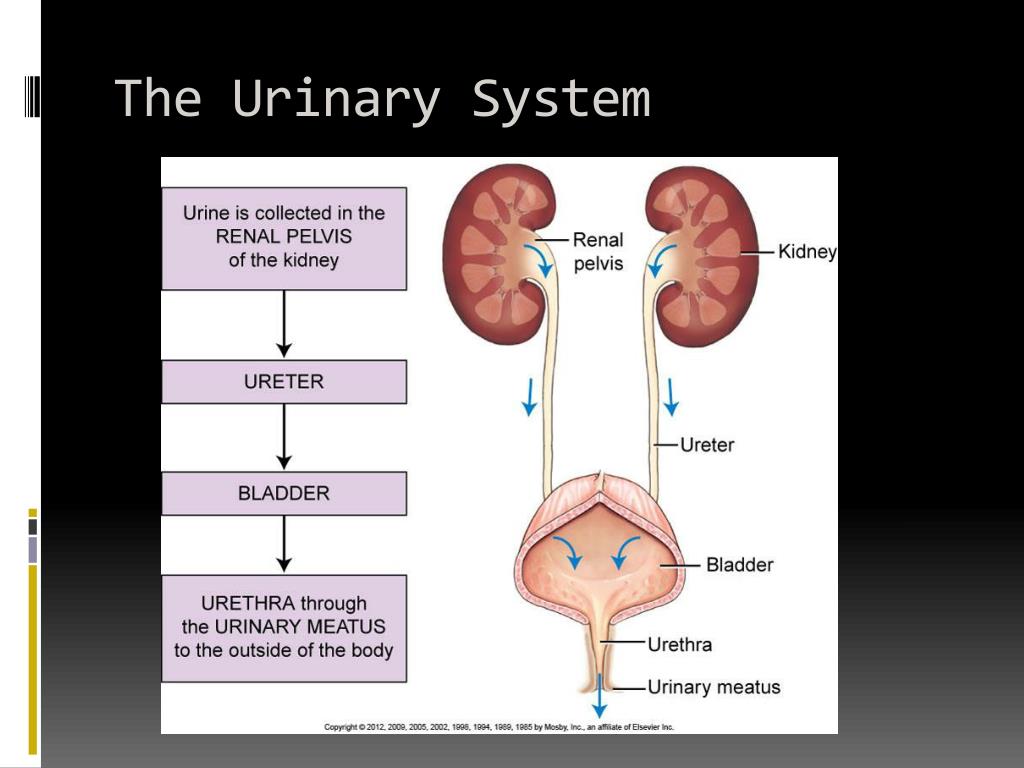
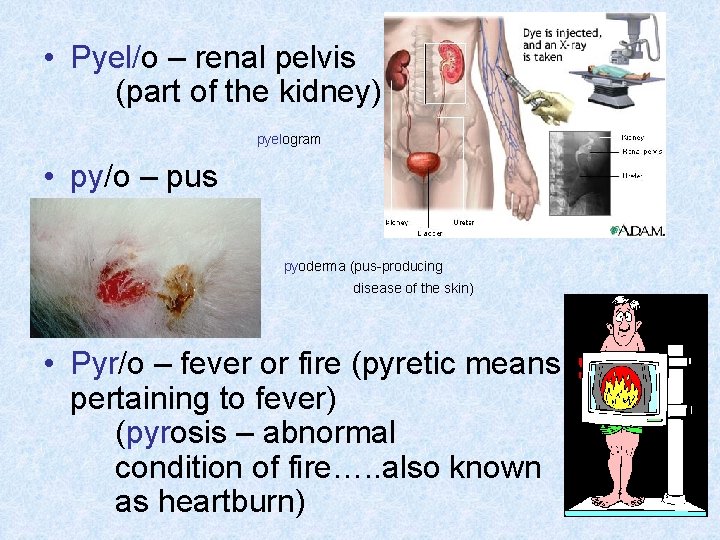
I've spent years working through medical documentation, coding, and radiology reports, and Pyel O is one of those terms that pops up occasionally enough to be frustrating but not commonly enough to have a solid reference handy. It's not something you'll find clearly defined in a standard medical dictionary. Here's what I can tell you from experience dealing with it in practice. The term comes from urology and radiology contexts. Pyel- is the root for renal pelvis, and the O in this case is used as a positional or directional marker rather than a standalone medical concept. When you see "Pyel O" in a report, it typically refers to imaging or procedural documentation of the renal pelvis in a particular orientation or phase. It is not a diagnosis itself. It is a descriptive shorthand used mainly by radiologists and urologists when documenting contrast flow, anatomy, or procedural access. I ran into this specifically a while back when a colleague was reviewing a retrograde pyelogram report. The documentation used Pyel O notation to indicate the initial opacification phase of the renal pelvis before contrast reached the calyces. The report was borderline unreadable for anyone not familiar with that shorthand, and it took me about twenty minutes to map it against the actual imaging series to confirm what was being described. I ended up asking the radiologist directly instead of trying to reverse-engineer it from a textbook, which would have taken longer and still probably left gaps.
How to interpret Pyel O notation when you encounter it
Start by looking at the modality. If it is a CT urogram, MR urogram, or conventional pyelogram, the O designation usually maps to the early filling phase. That is the baseline most people miss. They assume it means obstruction or something dramatic, when in most cases it simply denotes the temporal sequence of contrast delivery. The workable approach is to treat it as a temporal marker and cross-reference with the imaging timeline. Check the timing labels on the DICOM series, look at the contrast bolus tracking, and confirm whether the renal pelvis is fully opacified or still in early filling. This process usually takes about ten to fifteen minutes if you already know where to look. If you are doing this for the first time without institutional support or PACS access, it can stretch to an hour or more because you are figuring out the interface as you go. One thing nobody warns you about is that different hospitals use slightly different shorthand conventions for the same concept. I have seen Pyel O used to mean opposite things in two different department protocols at neighboring facilities. The only reliable workaround I found was to pull the facility's own radiology reporting guidelines and match the abbreviation against their internal nomenclature table. That saved me from misinterpreting a routine study as abnormal, which would have triggered unnecessary follow-up imaging and patient anxiety.
Pitfalls to avoid
The biggest mistake I see people make is treating Pyel O as a diagnostic finding. It is not. It is a descriptive label. If you are using it as evidence of pathology without confirming the underlying imaging characteristics, you will generate false positives at a reasonably high rate. Early contrast filling can look abnormal to someone who does not understand the phase timing, and it often gets misread as delayed emptying or partial obstruction when the anatomy is normal. Another issue is the assumption that Pyel O has a universal definition. It does not. Some institutions drop the O entirely and just label phases numerically. Others embed it in free-text reporting where context is the only disambiguator. If you are relying on external resources or generic medical databases, you will hit dead ends quickly. The term is too embedded in institutional practice to survive in a general reference format.
Get the Full Details

What to do when you cannot find a clear definition
If you are working with a specific report and need clarity, request the imaging series and trace the phase labels yourself. Review the contrast timing. Ask the originating radiologist or the reading physician for a clarification note if the terminology is ambiguous. This is the route I take when documentation is unclear, and it usually resolves the question within a single follow-up exchange rather than leaving you stuck on interpretation for days. I have also found that maintaining a personal abbreviation log across different facilities and specialties helps over time. It is tedious to set up, but once you have a few dozen cross-references mapped, you stop spending time looking things up and start recognizing patterns instinctively. That shift typically happens after six to eight months of consistent exposure, and the time savings become noticeable pretty quickly from there. If you need to apply this knowledge practically, the best starting point is any accessible urology or radiology textbook that covers pyelography protocol descriptions, not the abbreviation list itself. The protocol context is what makes the shorthand legible. Without it, you are memorizing symbols without understanding what they represent in practice.