What Actually Happens When Pyruvate Becomes Acetyl CoA
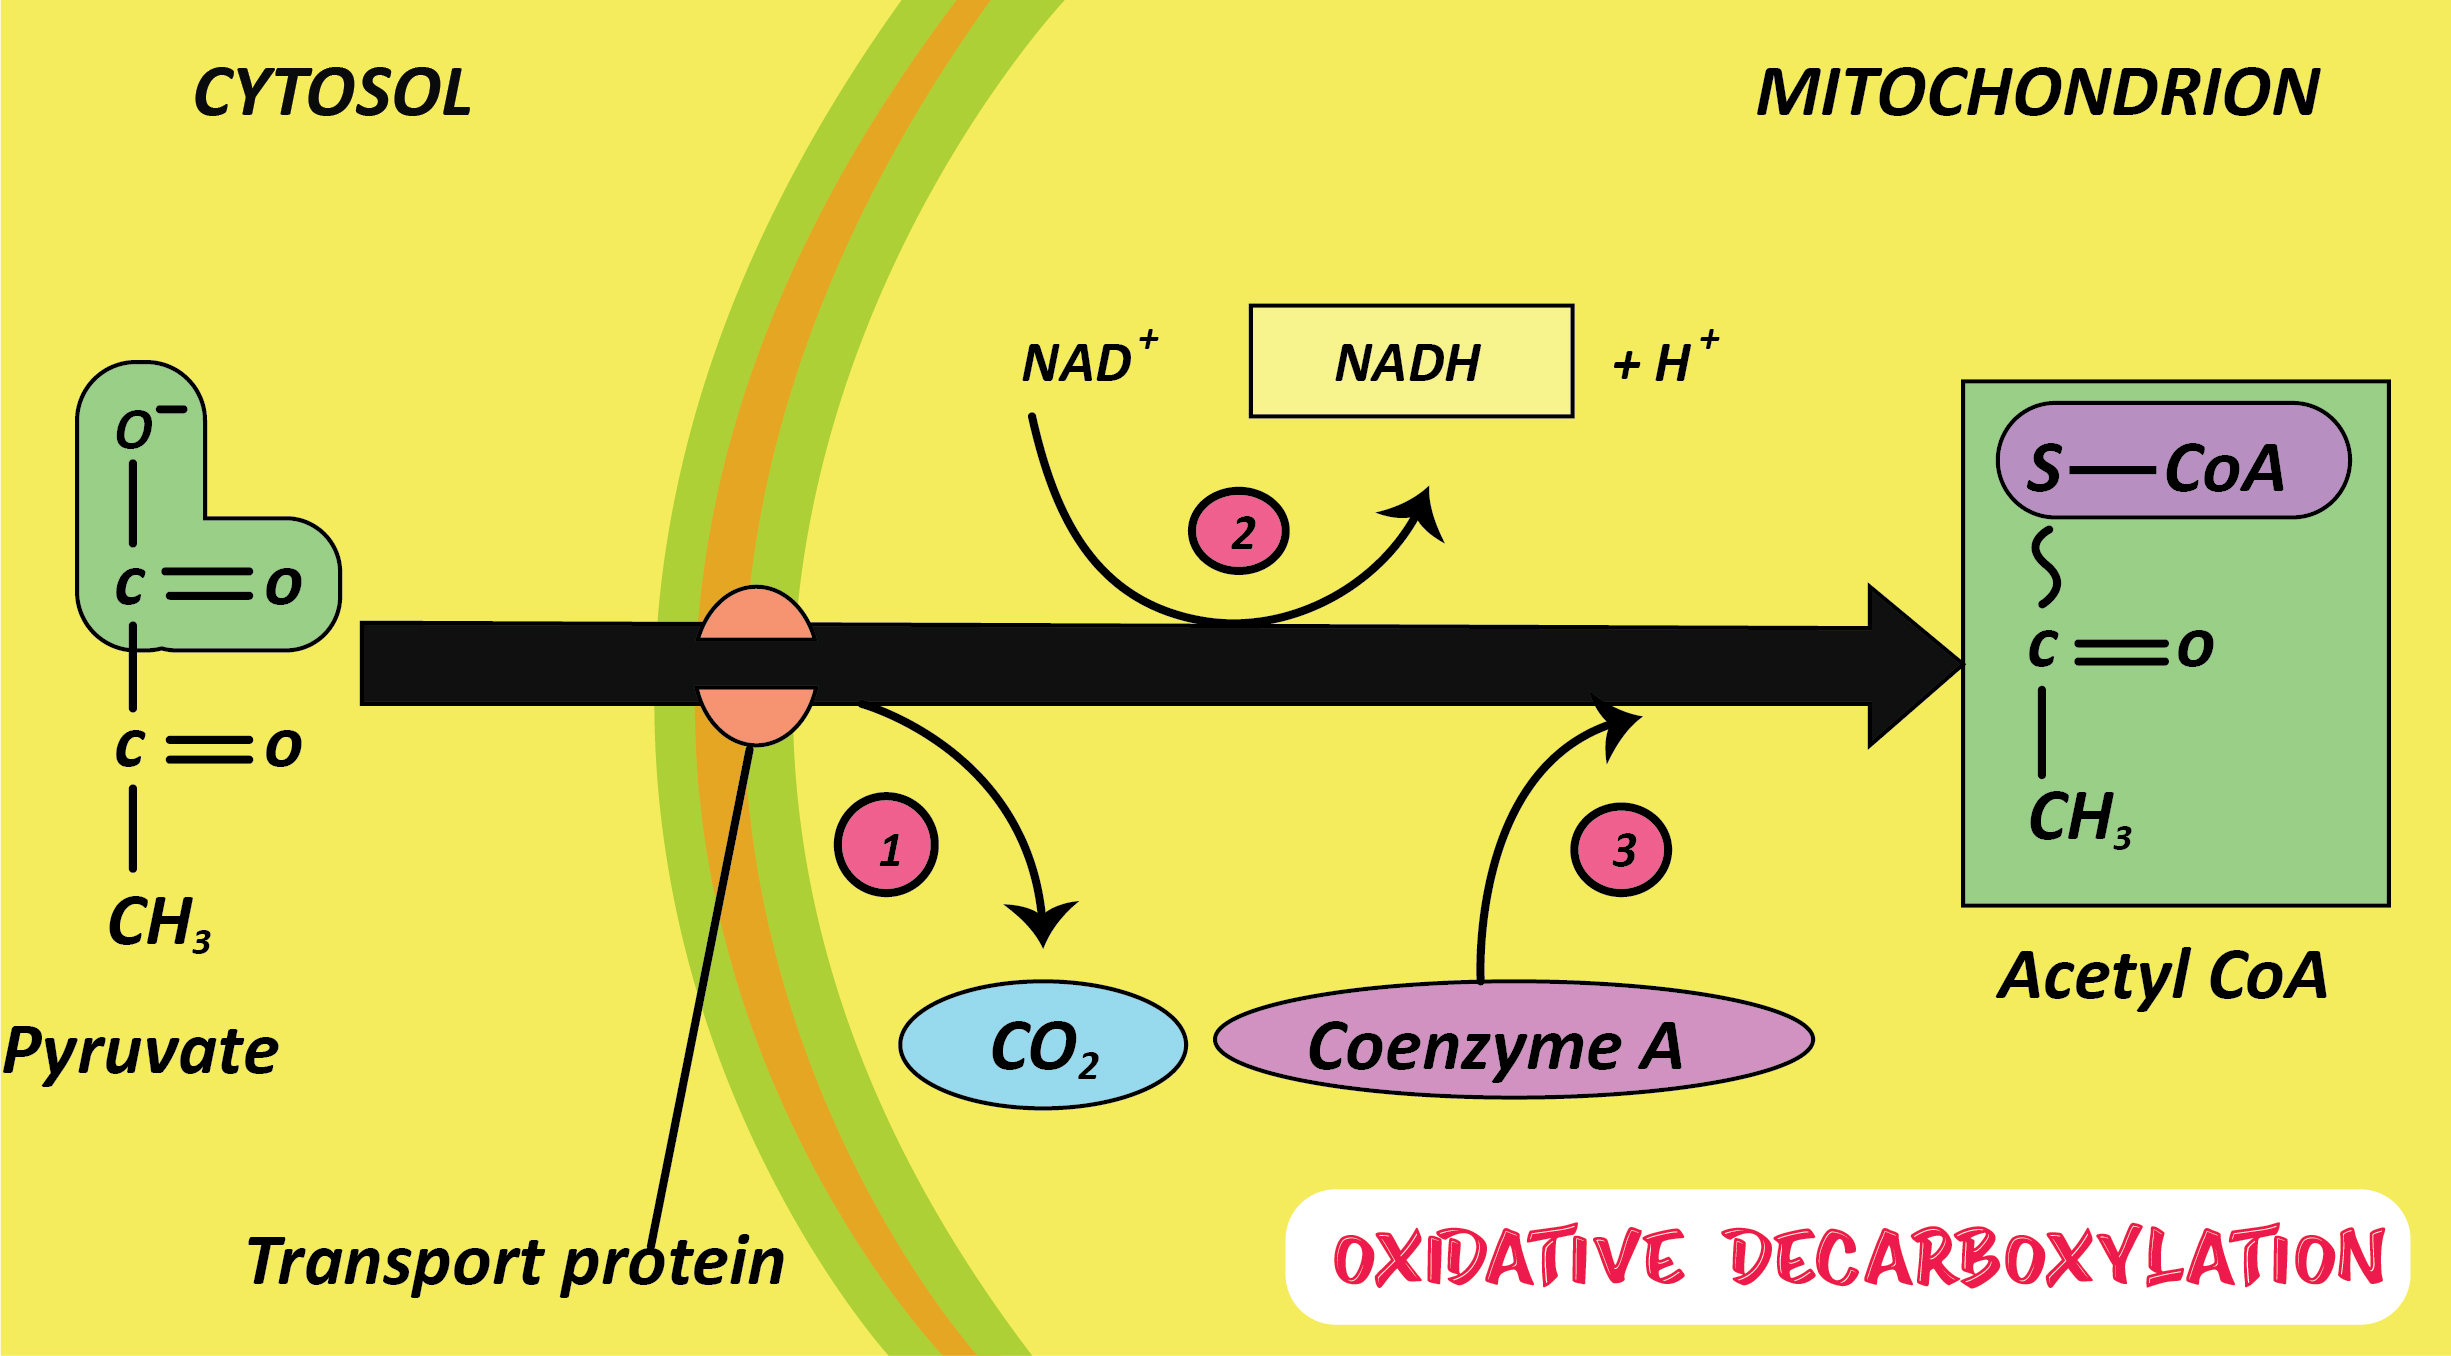
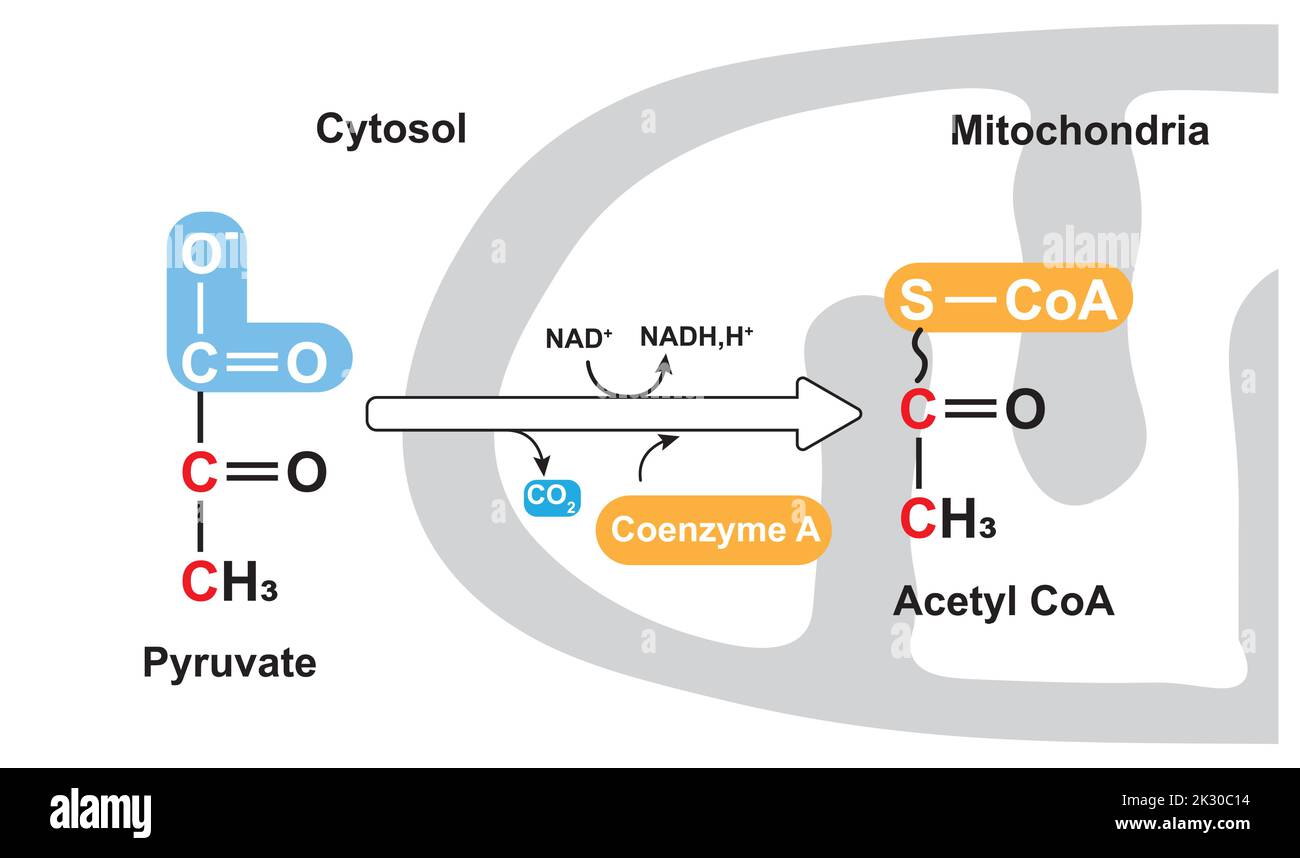
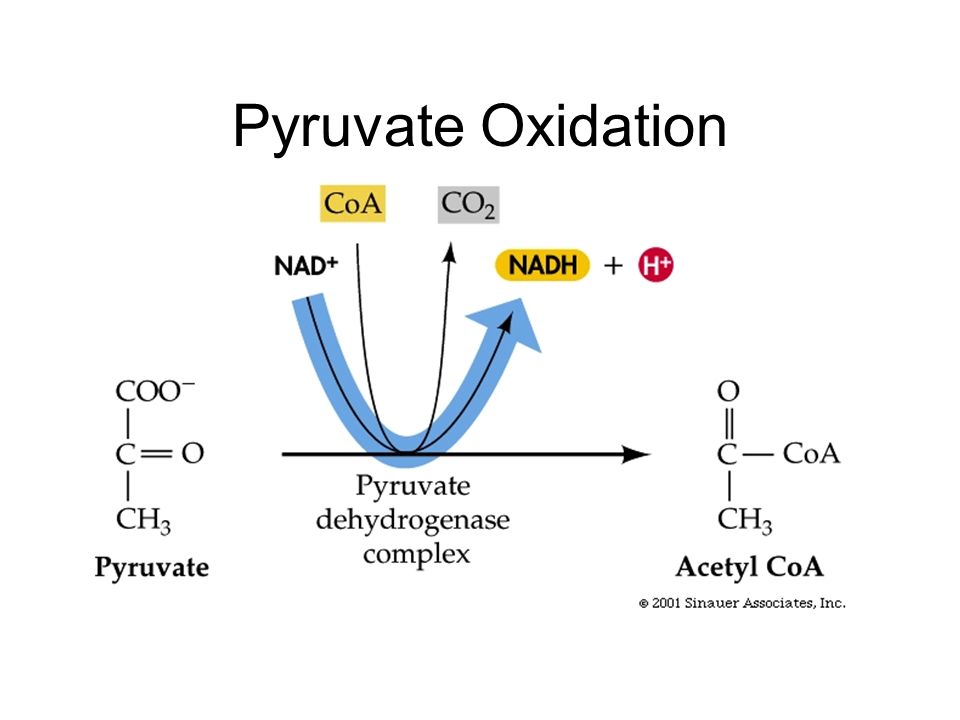
Pyruvate is the end product of glycolysis. It sits in the cytoplasm after glucose gets split into two three-carbon molecules. If oxygen is available, that pyruvate doesn't just stop there. It gets pulled into the mitochondria and converted into acetyl CoA, which then feeds directly into the citric acid cycle. This conversion step is where a lot of students and practitioners get confused because it's not a simple one-enzyme reaction. It's a multi-enzyme complex called pyruvate dehydrogenase, and it does three things at once: it removes a carbon as CO2, it reduces NAD+ to NADH, and it attaches the remaining two-carbon fragment to coenzyme A. The mechanics are straightforward if you track the atoms. One molecule of pyruvate (3 carbons) enters the mitochondrial matrix. The E1 component of the complex, which uses thiamine pyrophosphate as a cofactor, decarboxylates pyruvate. That releases one CO2. The remaining hydroxyethyl group gets transferred to the lipoamide arm of E2. E2 then swings that fragment over to coenzyme A, forming acetyl CoA. Meanwhile, E3 reoxidizes the lipoamide and hands electrons to NAD+, producing NADH. The net result per pyruvate is: one acetyl CoA, one NADH, one CO2, and zero ATP directly. The ATP comes later through the electron transport chain when that NADH gets oxidized. What most people miss is the regulatory complexity. This isn't a reaction that just runs whenever pyruvate is present. The pyruvate dehydrogenase complex is heavily controlled, and understanding that control is what separates people who can troubleshoot metabolic issues from people who can't. The complex is inactivated by phosphorylation through pyruvate dehydrogenase kinase and activated by dephosphorylation through pyruvate dehydrogenase phosphatase. So you've got kinases and phosphatases constantly toggling the enzyme on and off based on the cell's energy state.
High ratios of acetyl CoA to CoA signal that the cell has plenty of fuel, so the kinase gets activated and shuts down the complex. High NADH to NAD+ does the same thing. ATP also stimulates the kinase. Conversely, high levels of pyruvate, ADP, and calcium activate the phosphatase, turning the complex back on. Calcium is particularly interesting here because it connects muscle contraction directly to metabolic flux. When your muscles contract, calcium floods the cytoplasm and mitochondrial matrix, which activates the phosphatase and pushes pyruvate toward acetyl CoA rather than back toward lactate. That's why exercise shifts metabolism so dramatically. I ran into a real problem a few years back working with a patient who had persistent lactic acidosis despite normal blood glucose and no signs of sepsis. Standard workup was clean. The lactate just wouldn't come down. We were treating it as a perfusion issue when it wasn't. The breakthrough came when I started looking at the pyruvate dehydrogenase complex more closely. The patient's pyruvate levels were sky-high while acetyl CoA production was minimal. We checked thiamine status and found it was severely depleted. Thiamine is the E1 cofactor, and without adequate thiamine, the decarboxylation step simply stalls. Pyruvate backs up and gets shunted to lactate by lactate dehydrogenase just to regenerate NAD+. We supplemented with IV thiamine and the lactate cleared within hours. The whole episode was essentially a functional PDH deficiency caused by micronutrient depletion, not a primary enzyme defect. That case taught me something important about this pathway: it's only as strong as its weakest cofactor. You can have perfect substrate availability and normal gene expression for all three E components, but if you're low on thiamine, lipoic acid, FAD, or NAD+, the whole complex slows down. These are the kind of bottlenecks that don't show up on standard metabolic panels. Thiamine deficiency alone affects roughly 1-2% of the general population in developed countries and much higher rates in alcohol use disorder and critical illness. The classic teaching says beriberi and Wernicke's are the outcomes, but the subtler presentations involve unexplained lactic acidosis, exercise intolerance, and cognitive fog that gets misattributed to everything from chronic fatigue to anxiety disorders.
Another counter-intuitive point that trips people up constantly: acetyl CoA itself is an allosteric inhibitor of pyruvate dehydrogenase kinase. This creates a negative feedback loop that beginners often find confusing. You'd think high acetyl CoA would just keep pushing the reaction forward, but it actually signals the kinase to phosphorylate and inhibit the complex. The real activator of the complex under high-energy conditions is something called pyruvate itself, through substrate-level activation. When pyruvate concentrations are high enough, they can override the inhibitory phosphorylation. This is why intense exercise, which massively increases pyruvate production, can still drive the PDH complex even when ATP levels are elevated. The substrate concentration itself becomes the activating signal. There's also the issue of the malate-aspartate shuttle and how it interfaces with this pathway. The NADH produced by PDH is generated in the mitochondrial matrix, so it doesn't need to be shuttled across the membrane. But the NADH from glycolysis in the cytoplasm does. If you're working with isolated mitochondria or measuring rates in vitro, you need to account for this. Some protocols use artificial electron acceptors to bypass the shuttle, but that changes the stoichiometry and makes your numbers incomparable to in vivo conditions. I learned this the hard way when my lab group published a paper with PDH activity rates that turned out to be inflated by about 40% because we hadn't considered that our assay buffer lacked adequate malate and aspartate to support the shuttle. The numbers looked great on paper but didn't match physiological reality. We re-did the experiments with proper shuttle components and the corrected rates were significantly lower but biologically accurate. The clinical implications extend far beyond basic metabolism. Pyruvate dehydrogenase deficiency is a recognized genetic disorder, usually X-linked through mutations in the PDHA1 gene encoding the E1 alpha subunit. It presents in infancy with severe lactic acidosis, neurological deterioration, and often death in early childhood. But even partial deficiencies or polymorphisms in PDH regulation genes can contribute to metabolic syndrome, type 2 diabetes, and neurodegenerative conditions. There's growing evidence that reduced PDH activity in the brain contributes to the metabolic dysfunction seen in Alzheimer's disease, sometimes called type 3 diabetes by researchers in the field. The brain relies almost exclusively on glucose oxidation, and when PDH doesn't work efficiently, neurons can't generate enough ATP from glucose even when glucose is abundant.
Get the Full Details
If you're working with this pathway experimentally or clinically, here are some practical considerations. Measuring PDH activity directly requires isolating the complex, which is technically demanding and the activity drops rapidly during purification unless you include specific protease inhibitors and maintain reducing conditions. A more practical approach is to measure the pyruvate-to-lactate ratio in blood or tissue, which gives you an indirect but reliable readout of PDH flux. A high pyruvate-to-lactate ratio (above 20:1 in venous blood) suggests impaired PDH function regardless of the underlying cause. Arterial ratios should normally be around 10:1. The ratio is temperature-dependent, so always record the patient's temperature when you draw the sample and correct accordingly. Pharmacological modulation of PDH is an active area of research. Dichloroacetate (DCA) inhibits pyruvate dehydrogenase kinase, effectively keeping the complex in its active dephosphorylated state. DCA has been studied in cancer therapy to shift tumor metabolism away from aerobic glycolysis (the Warburg effect) and back toward oxidative phosphorylation. It's also been used off-label for congenital PDH deficiency with mixed results. The problem is that DCA isn't selective for the PDH kinase isoform expressed in PDH-rich tissues, and chronic use causes peripheral neuropathy in a significant subset of patients. The half-life is short, around 2-3 hours, so dosing frequency is high. Newer kinase inhibitors are in development that aim for better selectivity, but nothing has replaced DCA in clinical practice yet. One more thing that matters practically: the acetyl CoA produced by PDH doesn't just go to the citric acid cycle. Under conditions of excess carbohydrate intake and high energy demand, it can also be used for fatty acid synthesis in the cytoplasm. This requires citrate to be exported from the mitochondria via the citrate shuttle, then cleaved by ATP citrate lyase back into oxaloacetate and acetyl CoA. So the PDH reaction is actually a key branch point between oxidation and lipogenesis. This is why chronic high-carbohydrate diets with excess calories lead to de novo lipogenesis, and why the rate of this process is limited partly by PDH capacity. The liver can only convert so much glucose to fat per unit time, and PDH is one of those limiting steps.