Understanding Lupus Testing
Lupus diagnosis is messy. There is no single test that confirms it. The workup involves a combination of blood tests interpreted alongside clinical symptoms. Many people search Qu Examen Detecta El Lupus because they received a vague lab result and want clarity on what it actually means. Here is how the process works in practice. The primary screening test is the Antinuclear Antibody (ANA) test. It checks whether your immune system is producing antibodies that attack your own cell nuclei. A positive ANA is common in lupus, but it is not definitive on its own. Roughly 5 percent of healthy people, especially women, can test positive at low titers like 1:40 or 1:80. Doctors typically look for higher titers, usually 1:160 or above, combined with a specific fluorescent pattern such as homogeneous or speckled, before considering further testing. If your ANA comes back negative and you have no significant symptoms, lupus is unlikely. But about 2 to 5 percent of people with confirmed lupus will have a persistently negative ANA, which complicates things. When ANA is positive, the next step is usually an ENA panel, which breaks down into specific autoantibody markers. Anti-dsDNA and anti-Smith antibodies are the most clinically relevant for lupus. Anti-dsDNA has moderate sensitivity but high specificity for SLE. It also tracks with disease activity in many patients, meaning rising titers can signal a flare, particularly renal involvement. Anti-Smith is rarer, appearing in only about 10 to 20 percent of lupus patients, but it is nearly pathognomonic. A positive anti-Smith strongly points toward lupus even in the absence of other markers. Anti-RNP is another component of the panel. High titers suggest mixed connective tissue disease as a differential. Anti-Ro and Anti-La antibodies are relevant for conditions like Sjögren's overlap and neonatal lupus risk in pregnant patients.
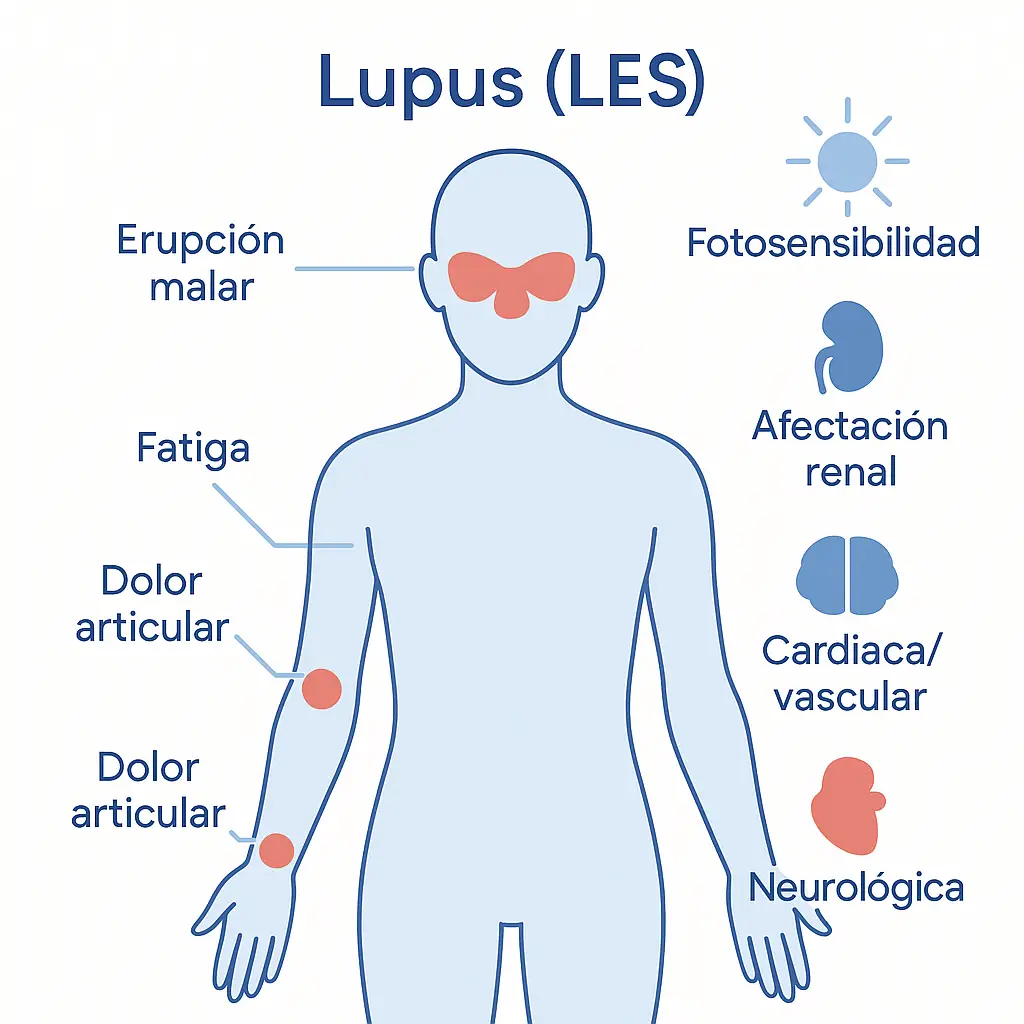
Beyond the antibody panels, complement levels are routinely checked. C3 and C4 tend to drop during active lupus, especially with kidney involvement, because the immune complexes consume them. Monitoring these values over time gives a rough picture of disease activity that antibodies alone cannot provide. ESR and CRP are also standard. ESR is typically elevated in lupus flares. CRP is less reliable here because it can stay normal even during significant inflammatory activity, unless there is an infection or serositis present. That distinction matters when you are trying to separate a lupus flare from something else. Urinalysis and kidney function tests round out the basic workup. Proteinuria, hematuria, and casts on a urine sample are early indicators of lupus nephritis, which affects roughly half of all lupus patients at some point. A spot urine protein-to-creatinine ratio is a quick way to estimate 24-hour protein excretion without waiting for a full collection. I have seen cases where kidney involvement was the presenting sign, months before any joint pain or rash appeared. In one case I dealt with, a patient had positive ANA at 1:320 with a homogeneous pattern and mild joint symptoms, but anti-dsDNA and anti-Smith were both negative. Complement levels were normal. The initial interpretation was uncertain. The patient had been on a biologic medication for rheumatoid arthritis, which can alter antibody profiles. We held off on a lupus label and repeated the full panel six weeks later after a medication adjustment. The anti-dsDNA came back positive the second time, and the clinical picture became clear. Medications like hydralazine, procainamide, and isoniazid can also cause drug-induced lupus, which typically shows positive ANA and anti-histone antibodies but lacks anti-dsDNA and anti-Smith. That pattern is important not to confuse with classic SLE.
Sometimes a lupus workup includes additional tests that are not strictly diagnostic but help rule out overlapping conditions. Anti-phospholipid antibodies, including lupus anticoagulant, anticardiolipin, and anti-beta-2 glycoprotein I, are checked because antiphospholipid syndrome frequently coexists with lupus and carries its own risks for clotting and pregnancy complications. A complete blood count often reveals cytopenias like leukopenia, lymphopenia, or thrombocytopenia, which are part of the classification criteria. Hemolytic anemia can show up as well, detected through a positive direct Coombs test. The biggest limitation of all this testing is timing. Antibodies can appear before symptoms, fluctuate during remission, or never show up at all in a subset of patients. A single negative panel does not definitively rule out lupus. The diagnosis remains clinical, based on criteria like the 2019 EULAR/ACR classification system, which weights ANA positivity as an entry criterion and then assigns points for clinical and immunological features. You need a sufficient point total along with adequate clinical context to meet classification thresholds, and even then, classification criteria are not the same as diagnostic certainty. If you are reviewing your own lab results, pay attention to the titer and pattern on the ANA, not just the yes or no. Ask whether the specific antibody panel was included. Normal complement levels during symptoms do not exclude active disease. A negative result on one marker does not rule out the disease entirely. The process is incremental, and interpretation depends heavily on the clinical context your rheumatologist has built over repeated visits.
Get the Full Details