How To Actually Use The Four Quadrant Method In Clinical Practice
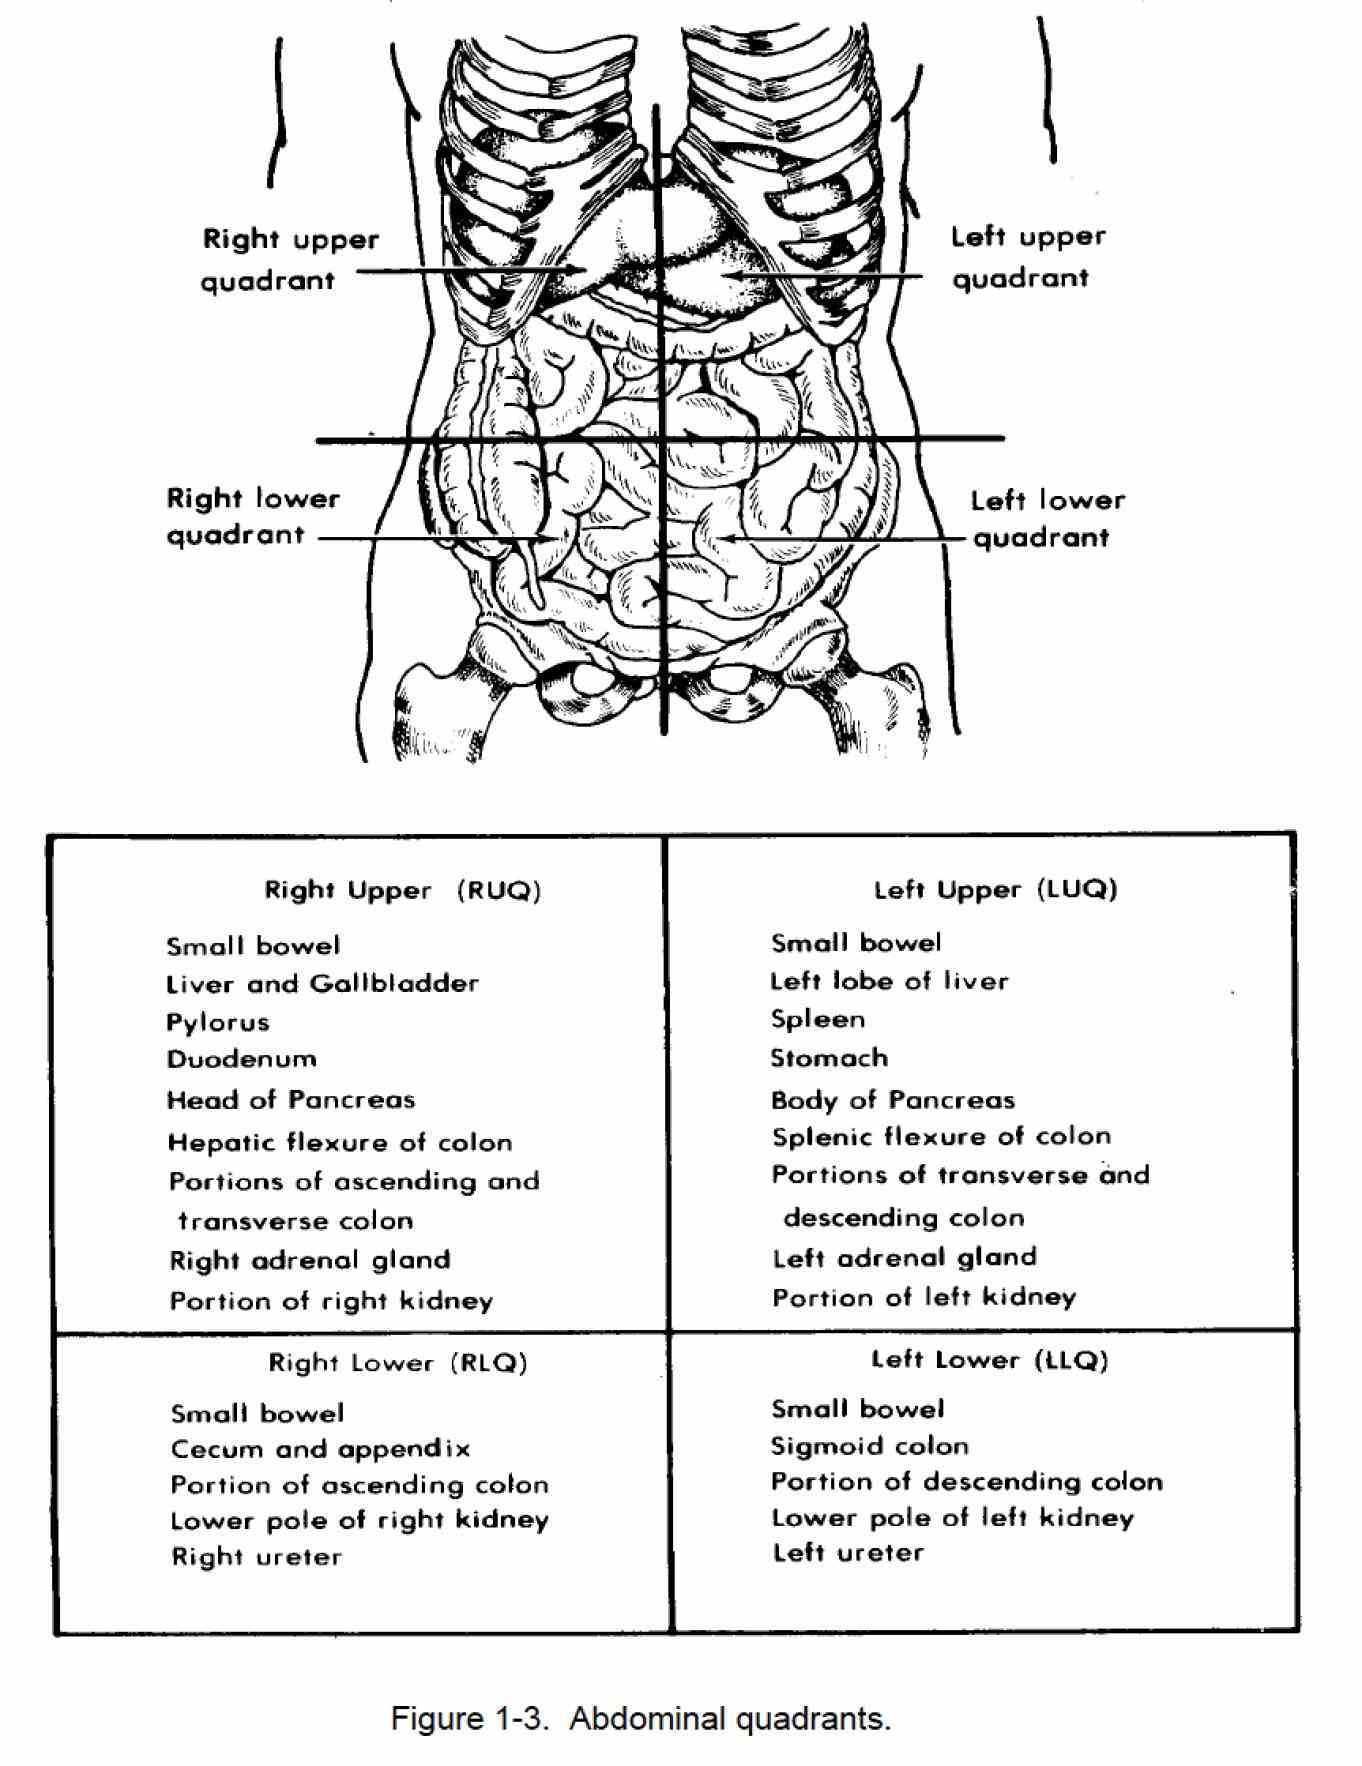
Most people learn this in their first semester and then never think about it again until they're trying to document something properly. The system itself is simple. You divide the abdomen into four sections using two imaginary lines. A vertical line running through the midclavicular point. A horizontal line at the level of the umbilicus or just below it, sometimes called the transtubercular plane depending on which textbook you're reading. That gives you the right upper quadrant, left upper quadrant, right lower quadrant, and left lower quadrant. Easy enough on paper.The real problem starts when you try to use it on actual patients. Bodies don't sit perfectly still. Organ positions vary. The classic teaching says the appendix starts near the right lower quadrant, but in practice I've seen appendicitis present with pain primarily in the right upper quadrant in at least one documented case I worked with. Pregnancy shifts everything upward. Ascites changes the percussion notes across all four sections. Relying solely on quadrant localization without additional context is a fast way to miss something. Stand on the patient's right side. That's your default position unless there's a specific reason not to. Start with inspection before anything else. Look for visible peristalsis, surgical scars, distension patterns, or skin changes. A scar in the right lower quadrant doesn't automatically mean appendectomy - it could have been a drain site for an abscess or a previous laparoscopy port. Document exactly where you see it. From there move to auscultation. Listen before you palpate because touching the abdomen changes the bowel sounds you're trying to hear. Place the bell of the stethoscope lightly over each quadrant. Listen for at least thirty seconds per area. Normal is three to five clicks or gurgles per minute. Absence of sound for a full minute in any quadrant is worth noting, especially if the patient reports nausea or vomiting.
Palpation comes next. Light palpation first across all four quadrants. Press about one to two centimeters deep. Note any areas of tenderness, rigidity, or guarding. Then do deeper palpation at two to four centimeters. Deep palpation can reveal masses that light palpation misses entirely. I once had a resident do light palpation only, documented a completely normal abdominal exam, and missed a palpable splenomegaly that extended well below the costal margin. The patient came back three days later with a hematocrit drop and we found a hematoma between the spleen and kidney that light palpation alone would never have detected. Finally percussion. It tells you whether underlying structures are fluid-filled, solid, or gas-filled. Dullness over a quadrant where you'd expect bowel gas suggests a mass or fluid collection. Hyperresonance in the right upper quadrant can indicate free air under the diaphragm, which is a surgical emergency. Don't skip percussion. It takes twenty seconds and catches things palpation won't.
Where This System Falls Short
The four-quadrant model was never designed to be a complete mapping system. It's a documentation shorthand. Some organs sit across quadrant boundaries and the line system doesn't account for that. The liver spans the right upper quadrant and extends across the midline into the left upper quadrant. The small intestine occupies almost all four quadrants. The transverse colon crosses the entire abdomen at roughly the umbilical level. When you're localizing pain to a single quadrant, you're already losing precision. There's also the issue of referred pain. Gallbladder pathology typically refers to the right scapula but presents as epigastric or right upper quadrant pain on direct palpation. Pancreatic issues often present in the left upper quadrant but the pain can radiate straight through to the back. Aortic aneurysms can cause midline tenderness that masks themselves as vague discomfort across multiple quadrants rather than a single localized point. If you're pinning symptoms to one quadrant too rigidly, you'll overlook connections. I'd recommend pairing the four-quadrant method with the nine-region anatomical division if you need more precision. The nine-region system adds the right and left flank regions, the hypochondriac regions above the quadrants, and the inguinal regions below them. It takes longer to document but catches regional differences that the four-quadrant system blurs together. For quick triage and basic documentation the four-quadrant method is sufficient. For detailed clinical work it's borderline inadequate.
Get the Full Details
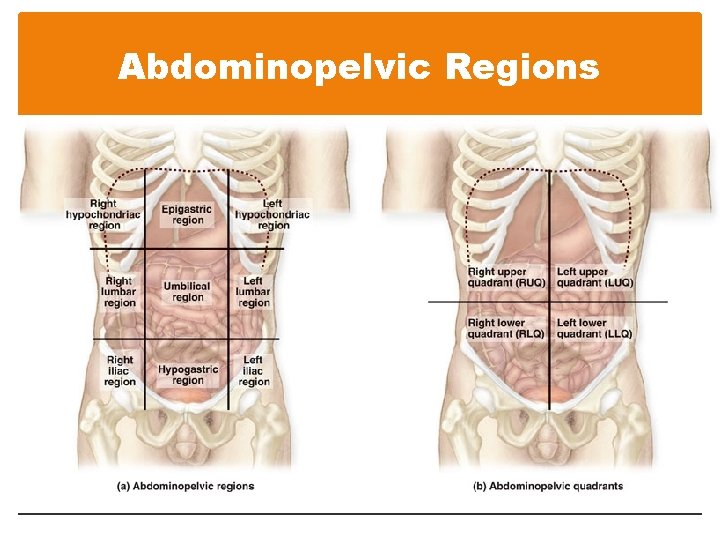
The main limitation though is that it assumes a standard anatomical position that doesn't always exist. Body habitus matters significantly. In obese patients the umbilicus can shift downward and inward, changing where you draw your horizontal reference line. In cachectic patients the organs sit differently because there's less subcutaneous tissue to displace them. Elderly patients with weakened abdominal walls can have organs that prolapse into lower quadrants more easily. One size doesn't fit all here, and recognizing that difference is what separates adequate documentation from useful clinical assessment.